Related Experiment Video
Updated: Jan 24, 2026


Modeling Stroke in Mice: Transient Middle Cerebral Artery Occlusion via the External Carotid Artery
Published on: May 24, 2021
Lower carotid revascularization rates after stroke in racial/ethnic minority-serving US hospitals
Roland Faigle1, Lisa A Cooper2, Rebecca F Gottesman2
1From the Departments of Neurology (R.F., R.F.G.) and Medicine (L.A.C.), Johns Hopkins University School of Medicine, Baltimore, MD. rfaigle1@jhmi.edu.

Insights
Patients in minority-serving hospitals received less carotid revascularization after stroke compared to white-serving hospitals. System-level factors likely explain these racial disparities in carotid revascularization procedures.
Area of Science:
- Health Services Research
- Vascular Surgery
- Health Equity
Background:
- Stroke due to carotid stenosis is a significant cause of disability.
- Carotid revascularization procedures, including carotid endarterectomy (CEA) and carotid artery stenting (CAS), are crucial treatments.
- Disparities in healthcare access and outcomes based on race and hospital type are a major concern.
Purpose of the Study:
- To investigate differences in the utilization of carotid revascularization procedures after stroke.
- To compare the use of CEA and CAS between minority-serving hospitals and predominantly white hospitals.
Main Methods:
- Analysis of ischemic stroke cases due to carotid disease (2007-2011) from the Nationwide Inpatient Sample.
- Categorization of hospitals into minority-serving (≥40% minority patients) and white-serving (<40% minority patients).
- Logistic regression models to compare CEA/CAS utilization, adjusting for patient and hospital characteristics.
Main Results:
- Patients in minority-serving hospitals were less likely to undergo CEA/CAS (17.6%) compared to those in white-serving hospitals (21.2%).
- Adjusted models showed significantly lower odds of CEA/CAS in minority-serving hospitals (OR 0.81).
- Racial disparities in CEA/CAS use persisted within hospitals, but were more pronounced in minority-serving institutions.
Conclusions:
- Carotid revascularization rates are lower in minority-serving hospitals compared to white-serving hospitals.
- System-level factors, not just individual patient race, contribute to disparities in carotid revascularization.
- Addressing these systemic issues is critical to reducing racial disparities in stroke treatment.
Objective:
We sought to determine whether the use of carotid revascularization procedures after stroke due to carotid stenosis differs between minority-serving hospitals and hospitals serving predominantly white patients.
Methods:
We identified ischemic stroke cases due to carotid disease, identified by ICD-9-CM codes, from 2007 to 2011 in the Nationwide Inpatient Sample. The use of carotid endarterectomy (CEA) and carotid artery stenting (CAS) was recorded. Hospitals with ≥40% racial/ethnic minority patients (minority-serving hospitals) were compared to hospitals with <40% minority patients (predominantly white hospitals [hereafter, abbreviated to white]). Logistic regression was used to evaluate the use of CEA/CAS among minority-serving and white hospitals.
Results:
Of the 26,189 ischemic stroke cases meeting inclusion criteria, 20,870 (79.7%) were treated at 1,113 white hospitals and 5,319 (20.3%) received care at 325 minority-serving hospitals. Compared to patients in white hospitals, patients in minority-serving hospitals were less likely to undergo CEA/CAS (17.6%, 95% confidence interval [CI] 16.6%-18.6%, in minority-serving vs 21.2%, 95% CI 20.7%-21.8%, in white hospitals; p < 0.001). In fully adjusted logistic regression models, the odds of CEA/CAS were lower in minority-serving compared to white hospitals (odds ratio 0.81, 95% CI 0.70-0.93), independent of individual patient race/ethnicity and other measured hospital characteristics. White and Hispanic individuals had significantly lower odds of CEA/CAS in minority-serving compared to white hospitals. Patient-level racial/ethnic differences in the use of carotid revascularization procedures remained within each hospital stratum.
Conclusion:
The odds of carotid revascularization after stroke is lower in minority- compared to white-serving hospitals, suggesting system-level factors as a major contributor to explain race disparities in the use of carotid revascularization.

Related Concept Videos
 00:59
Hospitals-II
Nurses that work in...
 01:28
Hospitals-I
 01:29
Self-Serving Bias
 01:25
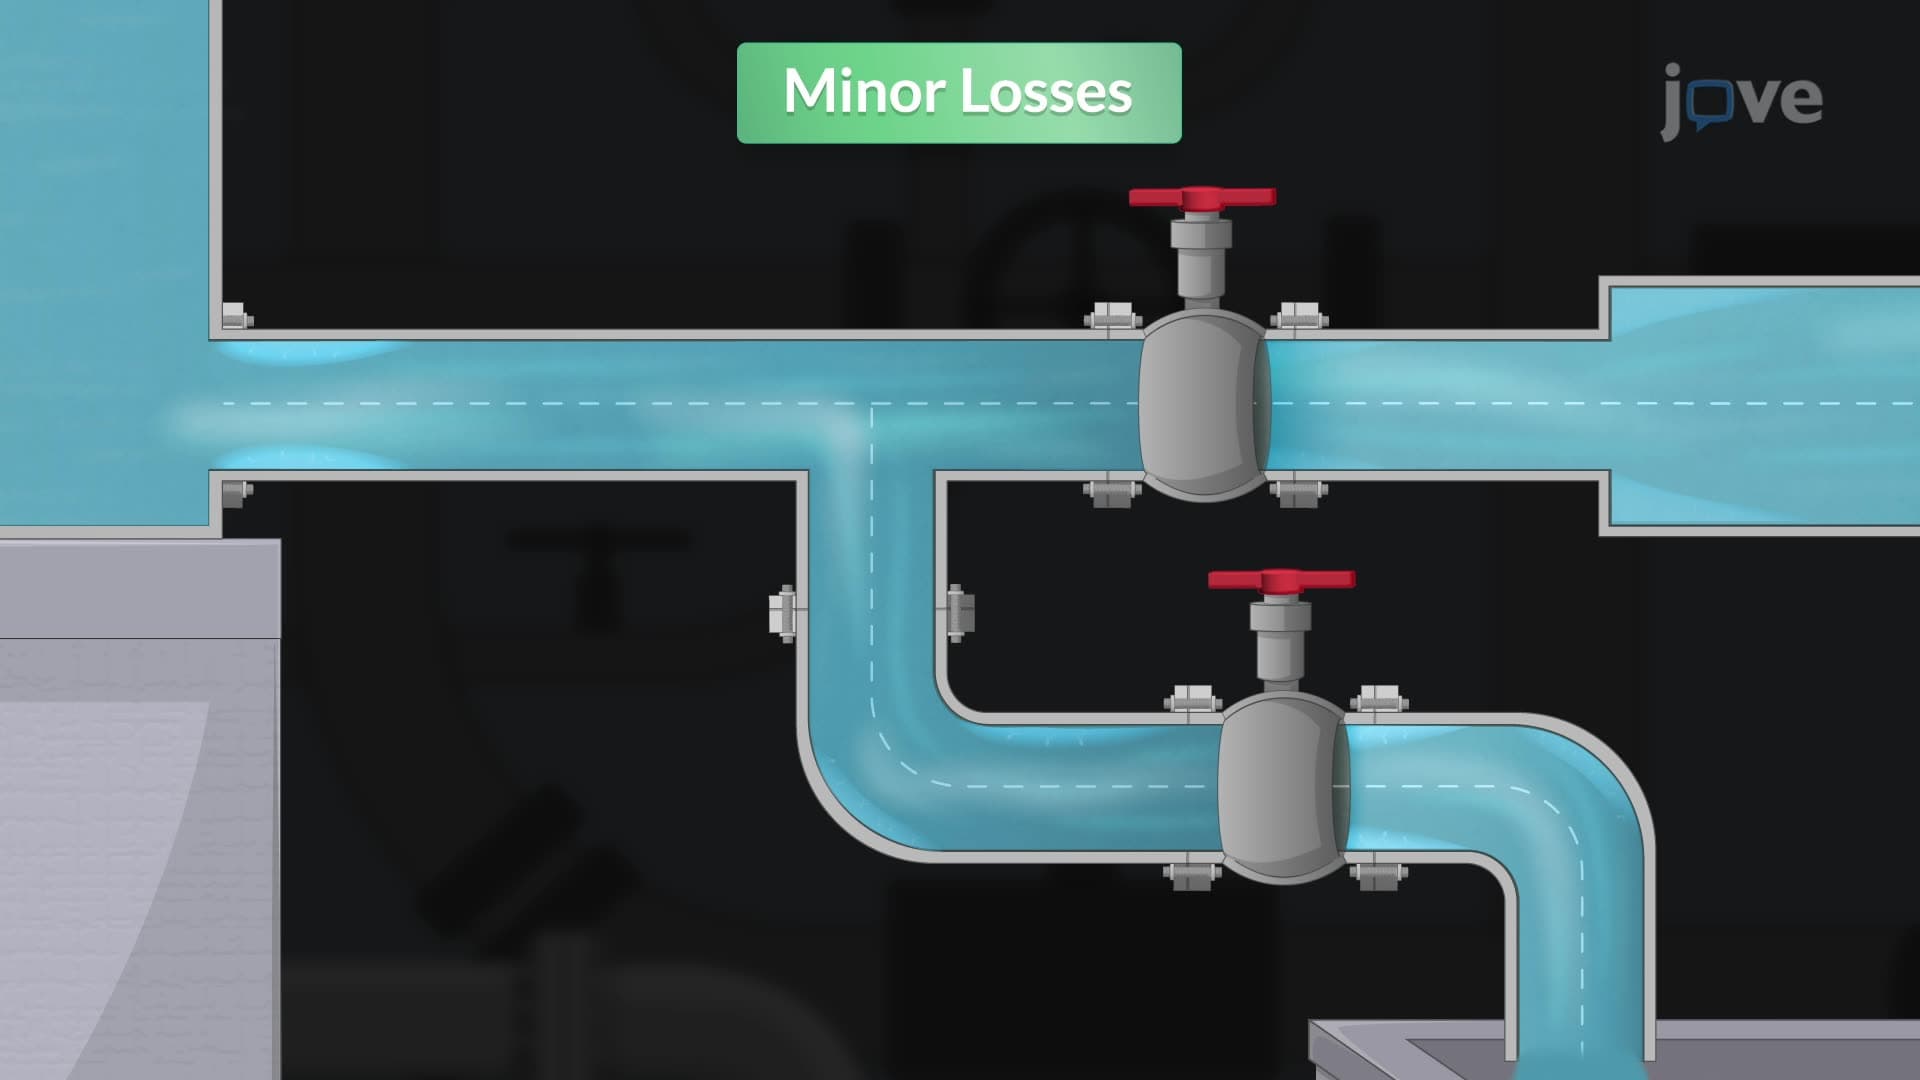
Minor Losses in Pipes
Valves play a significant role in generating minor losses by obstructing or redirecting the fluid flow. When a valve is closed or partially closed, it restricts the flow...
 01:27
Ethnic Identity within a Larger Culture
 02:53
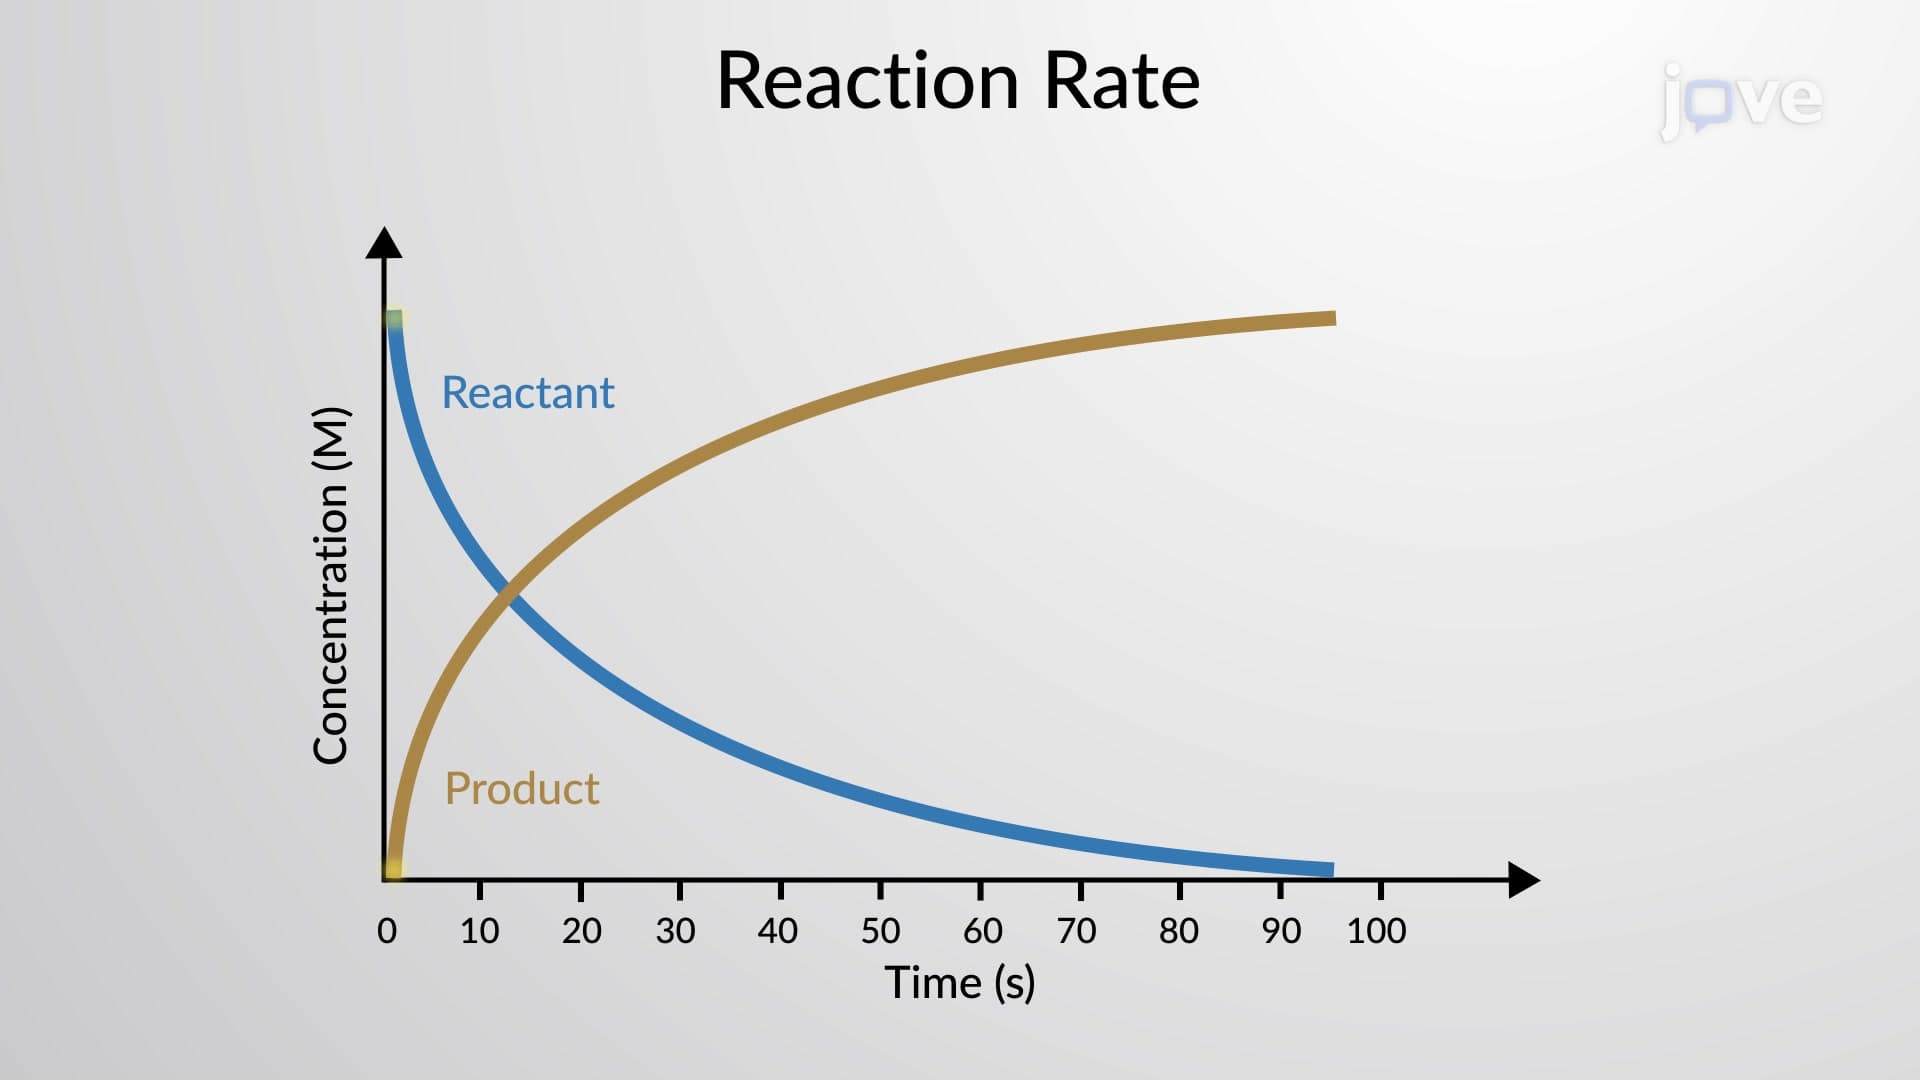
Reaction Rate
The mathematical representation of the change in the concentration of reactants and products, over time, is the rate...