Related Experiment Video
Updated: Jan 24, 2026
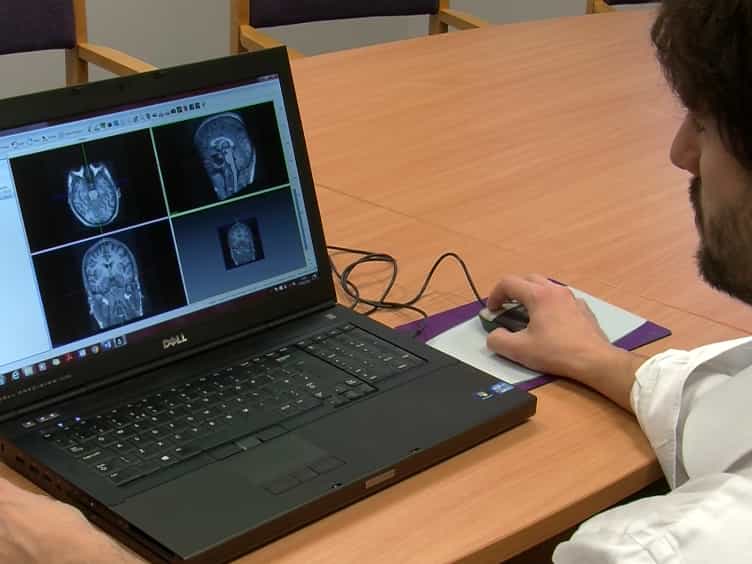

A Pipeline for 3D Multimodality Image Integration and Computer-assisted Planning in Epilepsy Surgery
Published on: May 20, 2016
One-year follow-up of a remotely delivered epilepsy self-management program in high-risk people with epilepsy
Martha Sajatovic1, Kari Colon-Zimmermann1, Mustafa Kahriman2
1Department of Neurology, Neurological & Behavioral Outcomes Center, Case Western Reserve University School of Medicine and University Hospitals Cleveland Medical Center, Cleveland, OH, USA; Department of Psychiatry, Case Western Reserve University School of Medicine and University Hospitals Cleveland Medical Center, Cleveland, OH, USA.

Objective:
"Self-management for people with epilepsy and a history of negative health events" (SMART) is a novel group-format epilepsy self-management intervention demonstrated to reduce negative health events (NHEs) such as accidents, emergency department visits, and seizures in adults with epilepsy in a 6-month prospective randomized controlled trial (RCT); SMART also reduced depressive symptoms and improved health functioning and quality of life. This report describes the longer-term (12-month) post-efficacy RCT outcomes in adults with epilepsy who received SMART.
Methods:
After completing a 6-month, prospective RCT that demonstrated efficacy of SMART vs 6-month waitlist control (WL), adults ≥18 years of age with epilepsy were followed for an additional 12 months. Individuals originally randomized to WL received the 8-week SMART intervention immediately following the conclusion of the RCT. For this long-term extension analysis, assessments were conducted at 24 weeks (the 6-month primary outcome time-point of the efficacy RCT), at 32 weeks for individuals originally randomized to WL, and at 48 weeks and 72 weeks for all individuals. Outcomes assessed included past 6-month NHE counts, depressive symptoms assessed with the 9-item Patient Health Questionnaire (PHQ-9) and Montgomery-Asberg Depression Rating Scale (MADRS), and quality of life assessed with the 10-item Quality of Life in Epilepsy (QOLIE-10).
Results:
At the beginning of this long-term observational period (24-week follow-up time point for the original RCT), there were 50 individuals in the group originally randomized to SMART and 52 originally randomized to WL. Mean age was 41.4 years, 70% women (N = 71), 64% (N = 65) African-American, and 8% Hispanic (N = 8). Study attrition from week 24 to week 72 was 8% in the arm originally randomized to SMART and 17% in the arm originally randomized to WL. During the 12-month observation period (24 weeks to 72 weeks), there were a total of 44 serious adverse events and 4 deaths, none related to study participation. There was no significant change in total past 6-month NHE counts in the group originally randomized to SMART, although the group had significantly reduced 6-month seizure counts. The group originally randomized to WL, who received SMART during this observational period, had a reduction in total NHE counts. The group originally randomized to SMART had relatively stable levels on other outcome variables except for a trend for improved MADRS (p = 0.08). In the group originally randomized to WL, there were significant improvements in PHQ-9 (p = 0.01), MADRS (p ≤ 0.01), and QOLIE-10 (p = 0.004).
Conclusions:
This post-RCT extension study suggests that adults with epilepsy who participate in the SMART intervention sustain clinical effects at 1-year follow-up and may have incremental improvements in seizure frequency and mood. Future research needs to identify opportunities for scale-up and outreach to other high-risk groups with epilepsy.

Related Concept Videos
 01:24
Epilepsy and Seizures: Overview
Various factors can trigger epilepsy, including genetic factors, brain damage, metabolic causes, and unknown etiology. Diagnosis of epilepsy involves electroencephalography (EEG), which...
 01:12
Relative Risk
 01:26
Factors Affecting the Risk of Infection
The integrity and count of the white blood cells help the body resist pathogens and fight infection. When impaired, it reduces the body's resistance to pathogens. The acidic pH levels of the gastrointestinal, genitourinary tracts, and skin...
 01:23
Oxygen Delivering System III: Tracheostomy and T-piece
Tracheostomy
A tracheostomy is a surgically created opening (stoma) in the anterior part of the trachea. It is used to establish a patient airway, bypass an upper airway obstruction, simplify the removal of secretions, permit long-term...
 01:26
Oxygen Delivering System I: Nasal Cannula and Face Mask
Nasal Cannula
A nasal cannula is a lightweight tube split at one end into two prongs and placed in the nostrils. It is typically used to deliver low to medium levels of oxygen.
Suggested flow rate: The suggested flow rate for a nasal cannula typically ranges between 1 and 6 L/min.
Oxygen percentage setting:...
 01:16
Oxygen Delivering System II: Venturi Mask and Transtracheal Oxygen
Venturi Mask
The Venturi mask, named after the Venturi effect, is designed to deliver precise oxygen concentrations. It consists of a large tube with an oxygen inlet that narrows down, causing a pressure drop that pulls air in through adjustable side ports. The mask is a lightweight,...