Related Experiment Video
Updated: Jan 24, 2026

Author Spotlight: Exploring Photodynamic Therapy with Curcumin in a Murine Model for Oral Candidiasis
Published on: October 27, 2023
The impact of delayed source control and antimicrobial therapy in 196 patients with cholecystitis-associated septic
Constantine J. Karvellas1, Victor Dong1, Juan G. Abraldes1
1From the Division of Critical Care Medicine and Gastroenterology/Hepatology, University of Alberta, Edmonton, Alta. (Karvellas); the Division of Gastroenterology and Hepatology, University of Alberta, Edmonton, Alta. (Karvellas, Dong, Abraldes); the Division of General Surgery, University of Alberta, Edmonton, Alta. (Lester); the Section of Critical Care Medicine, University of Manitoba, Winnipeg, Man. (Kumar); and the Section of Infectious Diseases, University of Manitoba, Winnipeg, Man. (Kumar).

Background:
Cholecystitis-associated septic shock carries a significant mortality. Our aim was to determine whether timing of source control affects survival in cholecystitis patients with septic shock.
Methods:
We conducted a nested cohort study of all patients with cholecystitis-associated septic shock from an international, multicentre database (1996–2015). Multivariable logistic regression was performed to determine associations between clinical factors and in-hospital mortality. The results were used to inform a classification and regression tree (CART) analysis that modelled the association between disease severity (APACHE II), time to source control and survival.
Results:
Among 196 patients with cholecystitis-associated septic shock, overall mortality was 37%. Compared with nonsurvivors (n = 72), survivors (n = 124) had lower mean admission APACHE II scores (21 v. 27, p < 0.001) and lower median admission serum lactate (2.4 v. 6.8 μmol/L, p < 0.001). Survivors were more likely to receive appropriate antimicrobial therapy earlier (median 2.8 v. 6.1 h from shock, p = 0.012). Survivors were also more likely to undergo successful source control earlier (median 9.8 v. 24.7 h from shock, p < 0.001). Adjusting for covariates, APACHE II (odds ratio [OR] 1.13, 95% confidence interval [CI] 1.06–1.21 per increment) and delayed source control > 16 h (OR 4.45, 95% CI 1.88–10.70) were independently associated with increased mortality (all p < 0.001). The CART analysis showed that patients with APACHE II scores of 15–26 benefitted most from source control within 16 h (p < 0.0001).
Conclusion:
In patients with cholecystitis-associated septic shock, admission APACHE II score and delay in source control (cholecystectomy or percutaneous cholecystostomy drainage) significantly affected hospital outcomes.

Related Concept Videos
 01:16
Treating Helicobacter pylori in Peptic Ulcers: Antimicrobial Therapy
 01:03
Drug Control Governance: Regulatory Bodies and Their Impact
 01:10
Mesh Analysis with Current Sources
Current Source in One Mesh: The analysis process is straightforward when a current source is found in only one mesh within the circuit. Mesh currents are assigned as usual, with the mesh containing the current source excluded from the analysis. Kirchhoff's voltage law...
 01:11
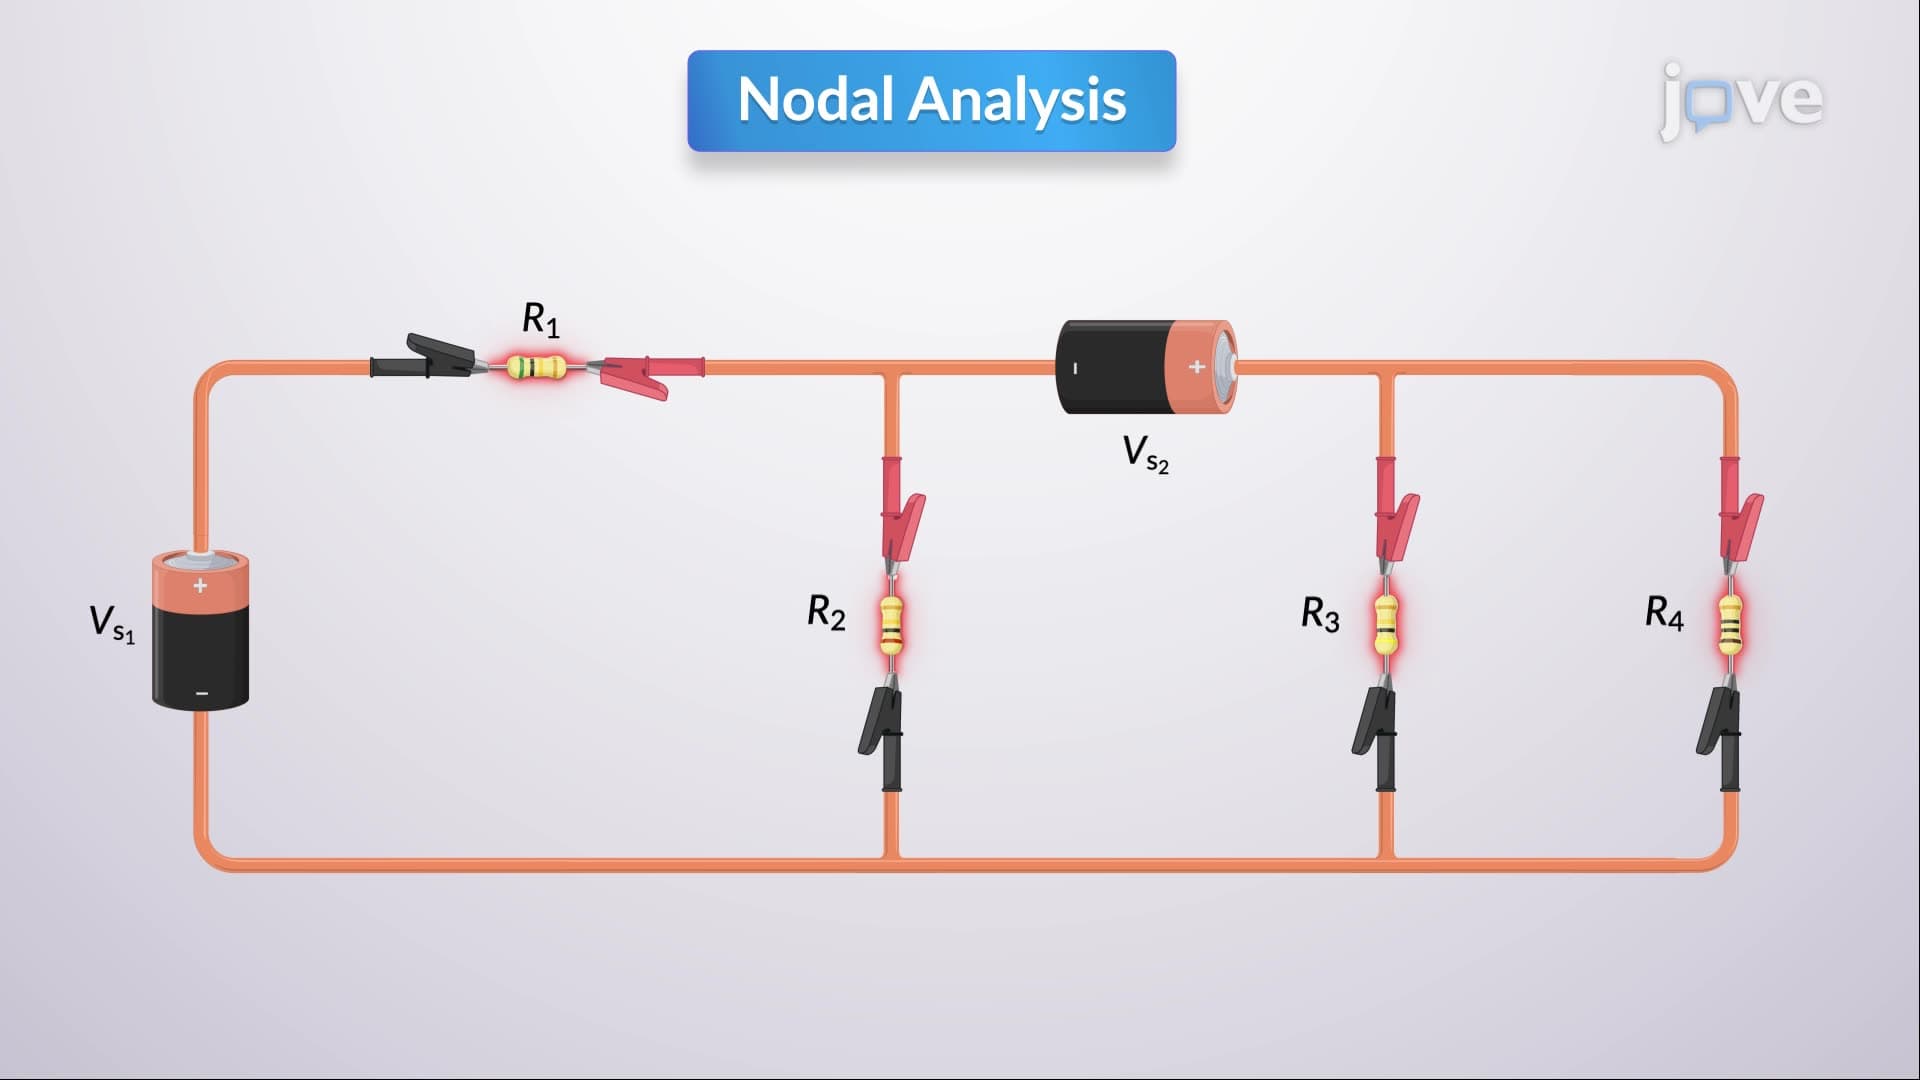
Nodal Analysis with Voltage Sources
Consider a circuit that contains four resistors and two voltage sources, as shown in Figure 1. One of these voltage sources is connected between a...
 01:28
Antimicrobial Effectiveness
 01:16
Shock Waves
When the source's speed approaches the speed of sound, constructive interference between successive wavefronts emitted by the source occurs immediately behind it. Initially, scientists believed that this constructive interference would result in such high...