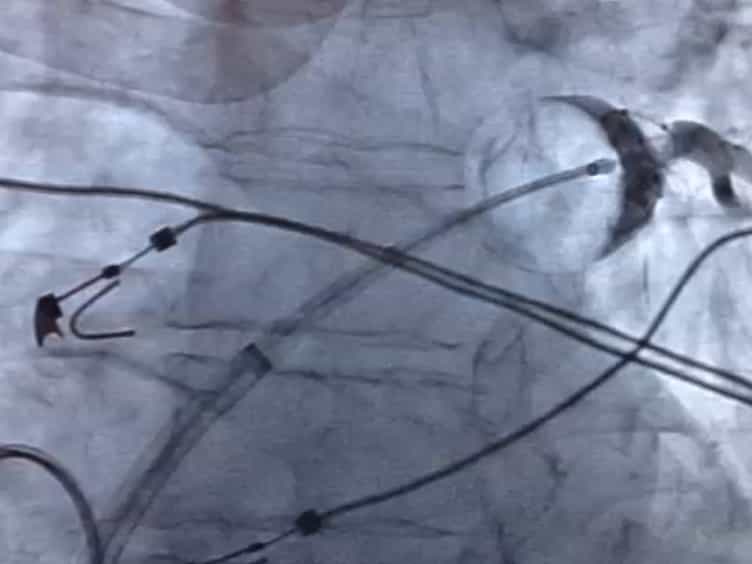
Atrioventricular septal defect and tetralogy of Fallot - A single tertiary center experience: A retrospective review
Khaled A Alhawri1, Colin J Mcmahon1, Mohammed M Alrih1
1Department of Pediatric Cardiothoracic Surgery, Our Lady's Hospital for Sick Children, Crumlin, Dublin, Ireland.

Insights
Complete atrioventricular septal defect (CAVSD) with tetralogy of Fallot (TOF) repair is complex. Staged repair using right ventricular outflow tract (RVOT) stenting shows acceptable outcomes with low mortality and morbidity.
Area of Science:
- Pediatric Cardiology
- Congenital Heart Disease Surgery
- Cardiovascular Research
Background:
- Complete atrioventricular septal defect (CAVSD) combined with tetralogy of Fallot (TOF) presents a rare and complex surgical challenge.
- Repairing this dual defect is more difficult than addressing either condition individually.
Purpose of the Study:
- To retrospectively review the management and outcomes of patients with CAVSD/TOF.
- To evaluate the effectiveness of different repair strategies, including primary versus staged repair.
Main Methods:
- Retrospective review of 16 patients with CAVSD/TOF between February 2006 and May 2017.
- Fifteen patients had trisomy 21.
- Staged repair involved right ventricular outflow tract (RVOT) stenting (n=9) or surgical shunt (n=2); RVOT stenting replaced shunts after 2012.
Main Results:
- Median age at first palliation was 46 days; median age at total repair was 6 months.
- Pulmonary valve preservation occurred in 31% of patients.
- Chylothorax occurred in 50%; one late mortality due to sepsis post-final repair.
Conclusions:
- Surgical repair of CAVSD/TOF can be achieved with low mortality and morbidity.
- Right ventricular outflow tract (RVOT) stenting is a viable alternative to surgical shunts, yielding acceptable results.
Background:
Complete atrioventricular septal defect (CAVSD) in association with tetralogy of Fallot is a rare and complex disease that makes its repair more difficult than repair of either lesion alone. We reviewed retrospectively our experience in managing this lesion.
Patients And Methods:
Between February 2006 and May 2017, 16 patients who underwent repair of CAVSD/tetralogy of Fallot (TOF) were reviewed retrospectively. Fifteen patients had trisomy 21. Five patients underwent primary repair while eleven patients went for staged repair in the form of right ventricular outflow tract (RVOT) stenting (n = 9) or systemic to pulmonary (S-P) surgical shunt (n = 2). RVOT stenting has replaced surgical shunt since 2012 in our center. Early presentation with cyanosis was the main determinant factor for staged versus primary repair.
Results:
The median age at first palliation was 46 days (range 15-99 days). The median age at total repair for both groups was 6 months (range 3-18 months); the median age for the palliated patients was 6.5 months (range 5-18 months) while the median age for primary repaired patients was 5 months (range 3-11 months). The median weight at final repair was 6.9 kg (3.7-8.2 kg). The pulmonary valve was preserved in five patients (31%), four of them had no prior palliation. Chylothorax occurred in 50% of the patients. One late mortality occurred after final repair due to sepsis.
Conclusion:
CAVSD/TOF can be repaired with low mortality and morbidity. The use of RVOT stent has replaced the surgical (S-P) shunt with acceptable results in our center.

Related Concept Videos
 01:21
Tertiary Healthcare System
 01:10
Review and Preview
Percentiles are a type of fractile that partition data into...
 01:13
Review and Preview
 01:12
Nomenclature of Secondary and Tertiary Amines
 02:33
Lattice Centering and Coordination Number
Types of Unit Cells
Imagine taking a large number of identical...
 00:58
Center of Gravity