Related Experiment Video
Updated: Jan 24, 2026

A Cell Free Assay System Estimating the Neutralizing Capacity of GM-CSF Antibody using Recombinant Soluble GM-CSF Receptor
Published on: June 27, 2011
Acute arteritis after G-CSF administration
Yasuyuki Kinjo1, Tomoko Kurita1, Taeko Ueda1
1Department of Obstetrics and Gynecology, University of Occupational and Environmental Health, Iseigaoka1-1, Yahatanishi-ku, Kitakyushu, Fukuoka Japan.

Granulocyte colony-stimulating factor (G-CSF) is commonly used in clinical practice to accelerate neutropenia recovery after chemotherapy. G-CSF is a myeloid growth factor produced by monocytes, macrophages, fibroblasts and endothelial cells. Generally, aortitis and arteritis are not a known side effect of G-CSF and is thought to be extremely rare. Here, we present a case of a 77-year-old woman who underwent adjuvant chemotherapy (combined paclitaxel and carboplatin) for ovarian cancer, and then developed acute arteritis after receiving G-CSF. She developed grade 4 neutropenia on day 7 of the third chemotherapy cycle and received six G-CSF administrations. Two days after G-CSF administration, she came down with a high-grade fever that persisted for 2 weeks. Laboratory tests revealed a white blood cell count of 8700 UI, neutrophilic sequestration of 61.5%, and C-reactive protein of 8.43 mg/dl at the highest point of her fever. Considering that we were initially treating neutropenia, we diagnosed a bacterial infection, and she was treated with a course of antibiotics. However, her blood and urinalysis cultures were negative, and antibiotics were ineffective; thus, we performed a computed tomography scan to search for the cause of her persistent fever. The computed tomography scan showed remarkable thickness of the bilateral common carotid artery and the left subclavian artery consistent with arteritis. With cessation of the antibiotics course, she was followed closely without therapy, and her condition resolved in a few days. We conclude that G-CSF induced arteritis due to our exclusion of other probable etiologies.
Granulocyte colony-stimulating factor (G-CSF) is commonly used in clinical practice to accelerate neutropenia recovery after chemotherapy. G-CSF is a myeloid growth factor produced by monocytes, macrophages, fibroblasts and endothelial cells. Generally, aortitis and arteritis are not a known side effect of G-CSF and is thought to be extremely rare. Here, we present a case of a 77-year-old woman who underwent adjuvant chemotherapy (combined paclitaxel and carboplatin) for ovarian cancer, and then developed acute arteritis after receiving G-CSF. She developed grade 4 neutropenia on day 7 of the third chemotherapy cycle and received six G-CSF administrations. Two days after G-CSF administration, she came down with a high-grade fever that persisted for 2 weeks. Laboratory tests revealed a white blood cell count of 8700 UI, neutrophilic sequestration of 61.5%, and C-reactive protein of 8.43 mg/dl at the highest point of her fever. Considering that we were initially treating neutropenia, we diagnosed a bacterial infection, and she was treated with a course of antibiotics. However, her blood and urinalysis cultures were negative, and antibiotics were ineffective; thus, we performed a computed tomography scan to search for the cause of her persistent fever. The computed tomography scan showed remarkable thickness of the bilateral common carotid artery and the left subclavian artery consistent with arteritis. With cessation of the antibiotics course, she was followed closely without therapy, and her condition resolved in a few days. We conclude that G-CSF induced arteritis due to our exclusion of other probable etiologies.


Related Concept Videos
 01:18
Additional Routes of Drug Administration
Administering drugs via inhalation allows for the direct delivery of gaseous, volatile substances or droplets to different parts of the respiratory tract. One of the advantages of the inhalation route is the rapid absorption of drugs into the circulatory system, which is possible because of the large surface area of...
 01:18
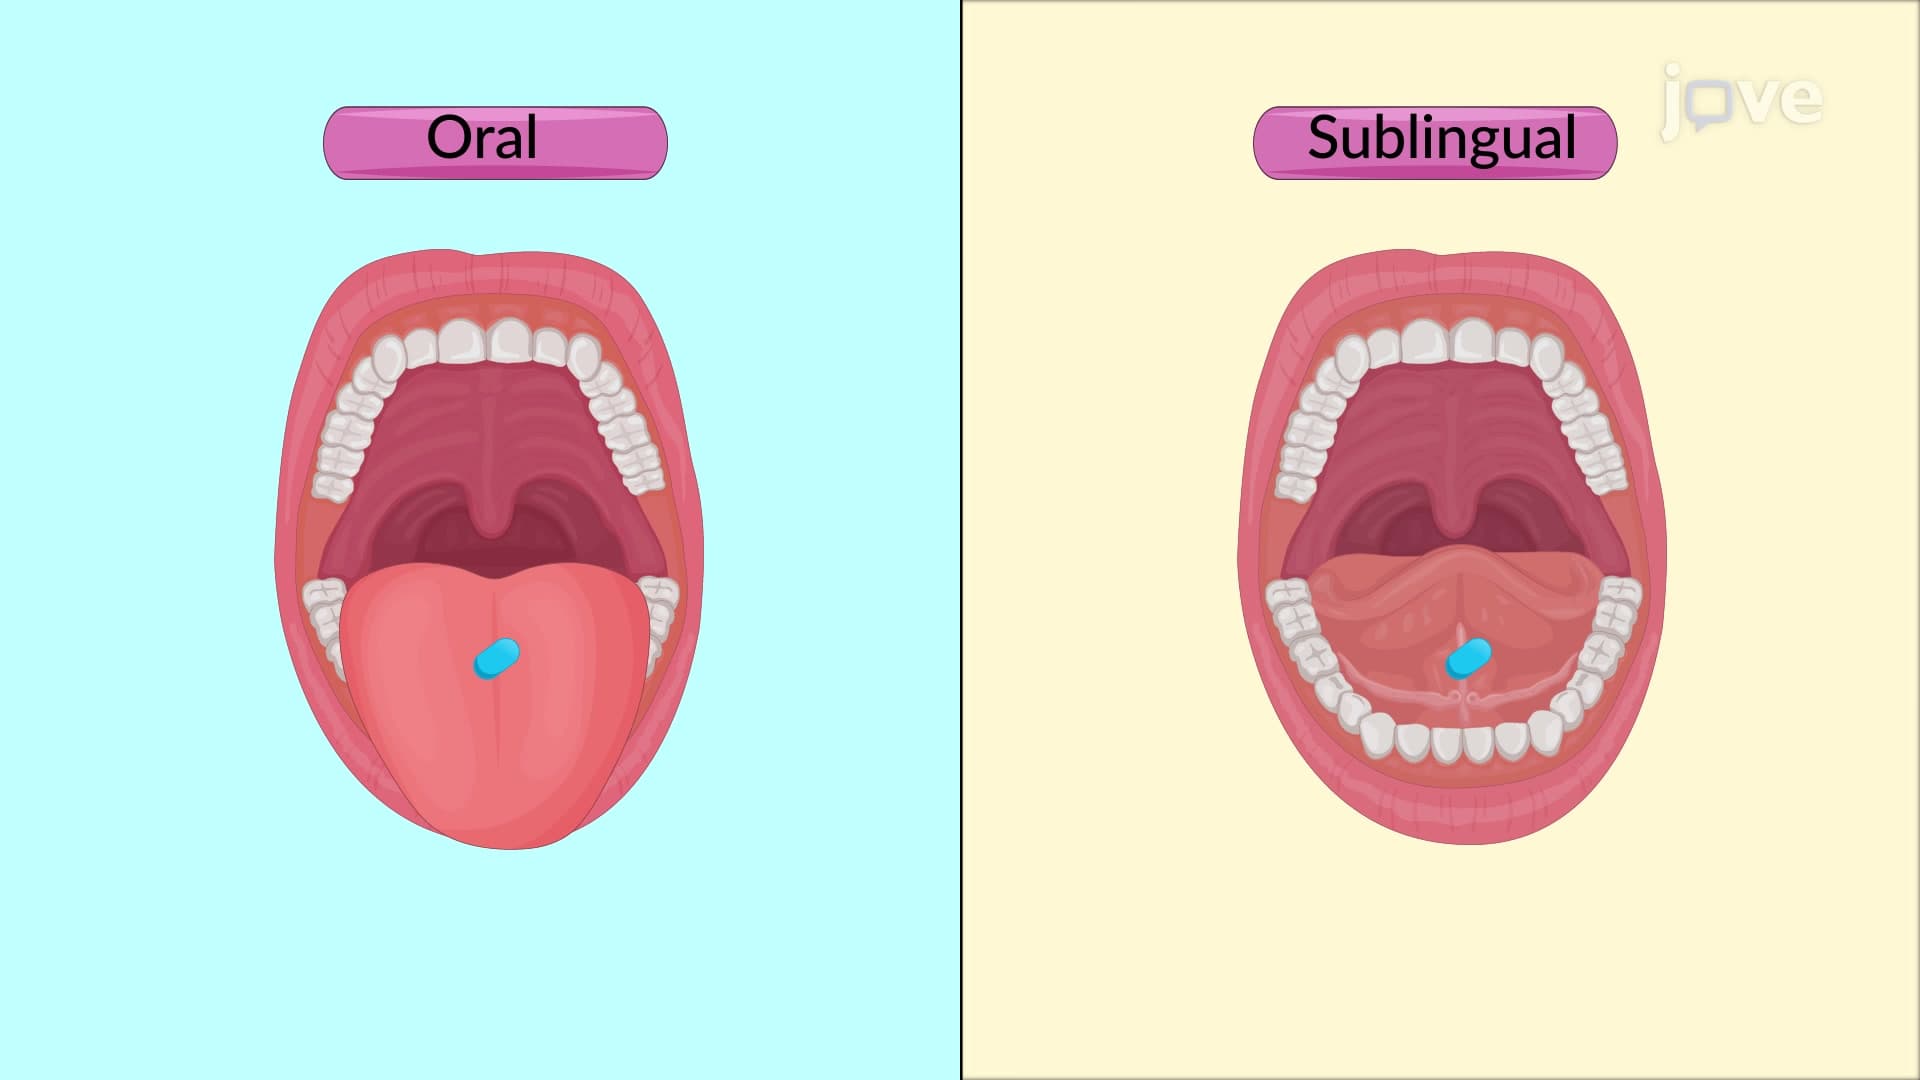
Routes of Drug Administration: Enteral
Enteral administration involves drug administration via the mouth in two ways: orally or sublingually.
Unlike sublingually drugs, drugs that are taken orally pass through the gastrointestinal (GI) tract and get metabolized by the liver. Once metabolized, the drug is absorbed into the systemic circulation, reaching different body parts via the bloodstream. However, while passing through the stomach,...
 01:12
Two-Compartment Open Model: Extravascular Administration
The absorption exponent (ka) indicates the speed at which the drug...
 01:25
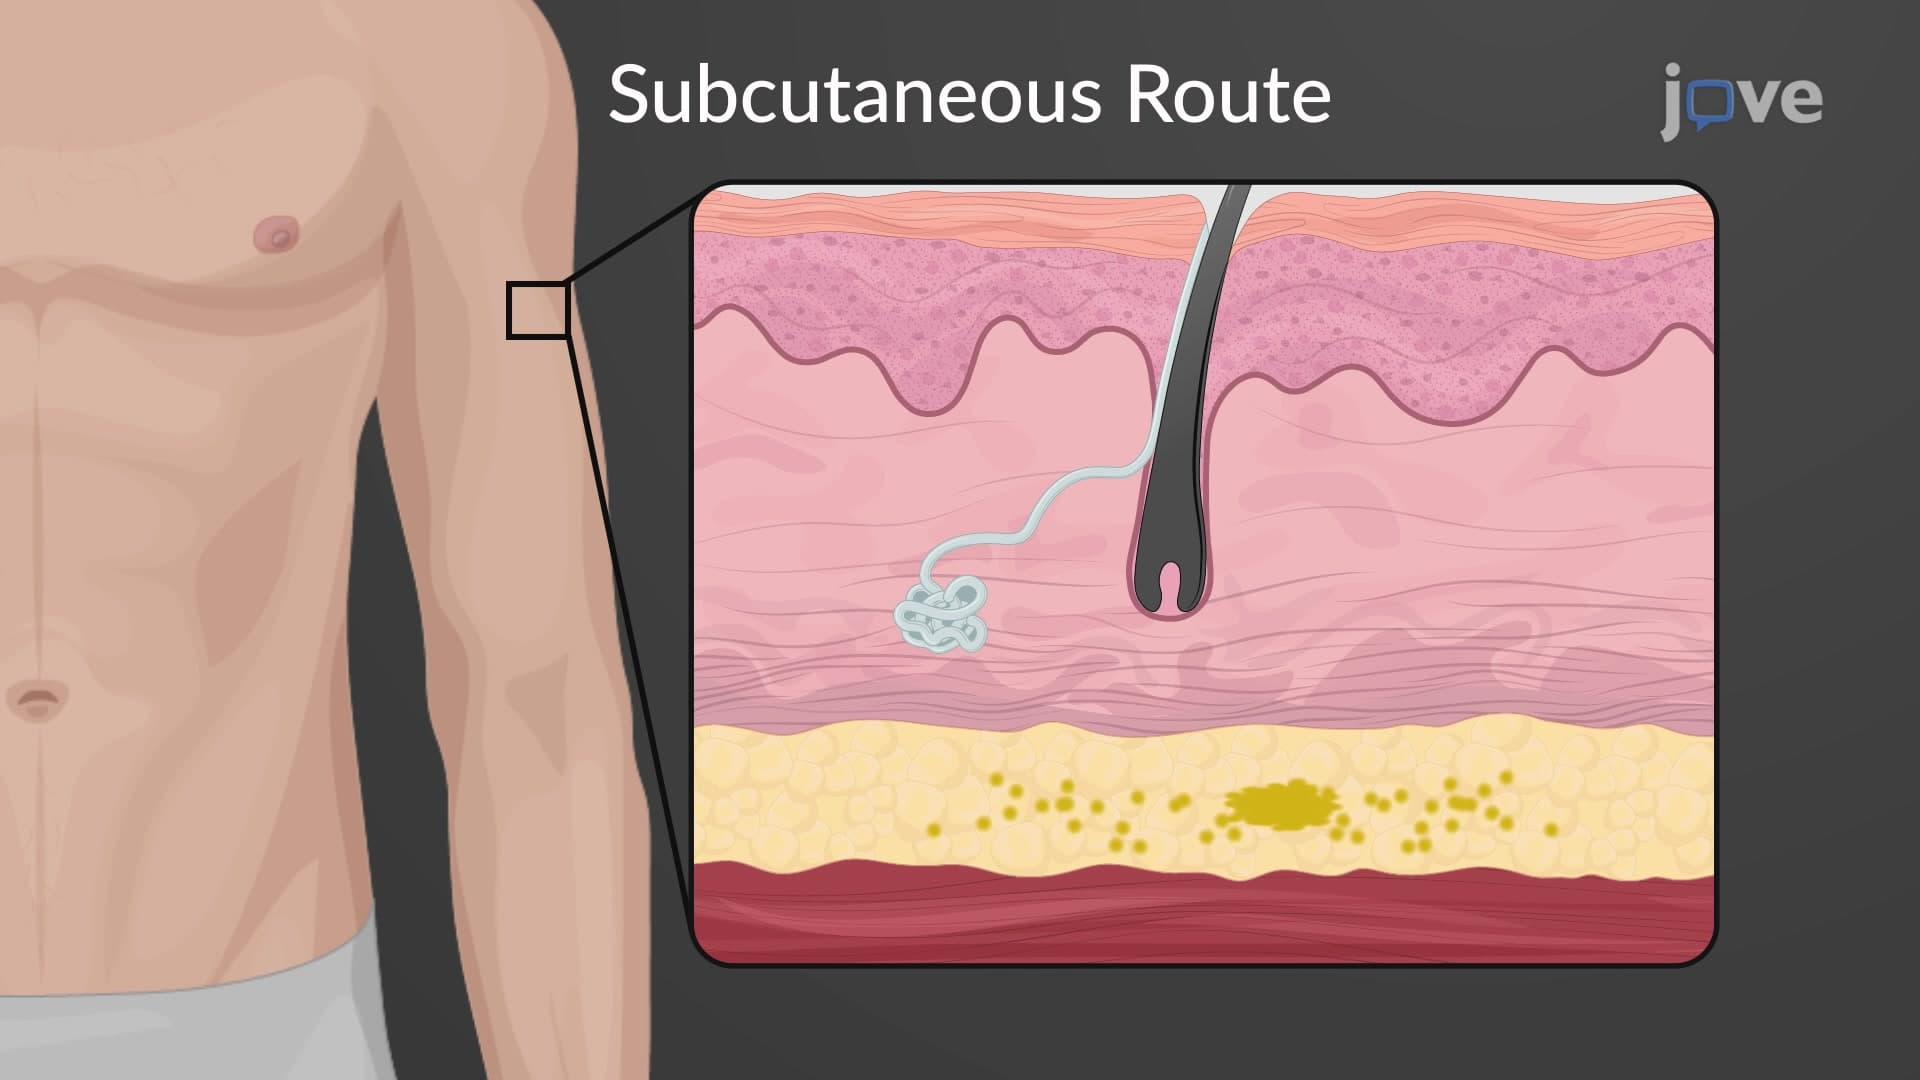
Routes of Drug Administration: Parenteral
The intravenous route (IV) of drug administration can be further categorized into two types. The bolus injection administers the entire dose rapidly, while an intravenous infusion slowly delivers smaller doses steadily.
The IV route is often...
 01:22
Routes of Drug Administration: Overview
Enteral administration refers to drugs absorbed through the gastrointestinal tract. They can be swallowed (perorally), placed under the tongue (sublingually), or on the inner lining of the cheeks (buccally). Perorally administered drugs take time to be absorbed and have a slower onset of action. The rectal route is another form of enteral administration, which allows for...
 01:30
Acute Pharyngitis
Acute pharyngitis is the inflammation of the back of the throat (pharynx), commonly resulting in a sore throat. It is a frequently encountered condition that prompts individuals to seek medical advice.
Classification
Acute pharyngitis can be categorized based on its underlying cause: