Related Experiment Video
Updated: Jan 23, 2026

Induction of Atherosclerotic Plaques Through Activation of Mineralocorticoid Receptors in Apolipoprotein E-deficient Mice
Published on: September 26, 2018
Pediatric heart failure therapy: why β1-receptor blocker, tissue ACE-I and mineralocorticoid-receptor-blocker?
Sabine Recla1, Dorle Schmidt1, Thushiha Logeswaran1
1Pediatric Heart Center, Justus-Liebig University, Giessen, Germany.

Insights
Pediatric heart failure (HF) treatment now incorporates specific beta-1 adrenergic receptor blockers (ARB), mineralocorticoid antagonists, and angiotensin-converting enzyme inhibitors (ACE-I). This evidence-based approach tailors therapy to children, improving outcomes and avoiding transplant.
Area of Science:
- Pediatric Cardiology
- Pharmacology
- Cardiovascular Medicine
Background:
- Pediatric heart failure (HF) treatment historically lags behind adult advancements.
- Limited prospective, double-blind randomized studies exist for pediatric HF pharmacotherapy.
- Current pediatric HF management often relies on extrapolations from adult data.
Purpose of the Study:
- To review and recommend specific pharmacotherapies for pediatric heart failure.
- To guide the preferred indication of beta-1 adrenergic receptor blockers (ARB), mineralocorticoid antagonists, and angiotensin-converting enzyme inhibitors (ACE-I) in children.
- To bridge the gap between evidence-based and pathophysiology-based approaches in pediatric HF.
Main Methods:
- Review of pharmacological research, clinical experience, and receptor-physiological knowledge in pediatric HF.
- Analysis of drug specificity, effectiveness, and side-effect profiles in children.
- Consideration of negative results from limited pediatric HF studies.
Main Results:
- Bisoprolol, lisinopril, and spironolactone (BLS) are recommended for specific pediatric HF populations, including those with left-right shunt lesions and reduced ejection fraction.
- Avoidance of chronic diuretic use and fluid restriction is advised to prevent neurohumoral axis overstimulation.
- Personalized treatment strategies are supported by surrogate parameters like heart rate, breath pattern, weight gain, and biomarkers.
Conclusions:
- Effective pediatric HF treatment requires a strategy that respects unique pathophysiology and receptor physiology in children.
- Personalized pharmacotherapy, such as the BLS regimen, can improve outcomes in pediatric HF patients.
- Optimized HF therapy is crucial for novel regenerative strategies and avoiding cardiac transplant in pediatric patients.
Abstract:
Pediatric heart failure (HF) treatment lagged behind the knowledge of pharmacological research and evidence-based clinical experience in adults. Considering the lack of prospective, double blind randomized studies in children, the review is focused on the preferred indication of specific β1-adrenoreceptor blockers (ARB), mineralocorticoid antagonists and tissue angiotensin-converting enzyme inhibitors (ACE-I). Our recommendations are based on the specificity in children, the effectiveness and the side-effect profile of HF-drugs, the receptor-physiological knowledge and the negative results of the few pediatric HF studies with an "evidence study label". In the interest of our pediatric patients, effective HF treatment has not longer to be postponed by balancing between evidence-based versus pathophysiology-based approach. At our institution, bisoprolol, lisinopril and spironolactone (BLS) are used treating HF in patients with left-right shunt lesions, reduced ejection fraction as well as during the inter-stage after HLHS-Hybrid approach. Chronic use of diuretics and fluid restriction is avoided, if always possible; intravascular volume deficiency stimulates further the neurohumoral axis. Pediatric HF needs to be treated with a strategy respecting the variable pathophysiology and the differences of receptor physiology between children and adult patients. The personalized treatment can be easily proofed by the surrogate parameters as heart rate, breath pattern, weight gain and image-derived parameters as well as biomarkers. Effective HF-therapy is also the basis for novel regenerative strategies in particular for young children with "end-stage" HF avoiding cardiac transplant or death.

Related Concept Videos
 01:22
Heart Failure Drugs: β-Blockers
 01:30
Antihypertensive Drugs: Angiotensin II Receptor Blockers
 01:31
Adrenergic Antagonists: ɑ and β-Receptor Blockers
 01:17
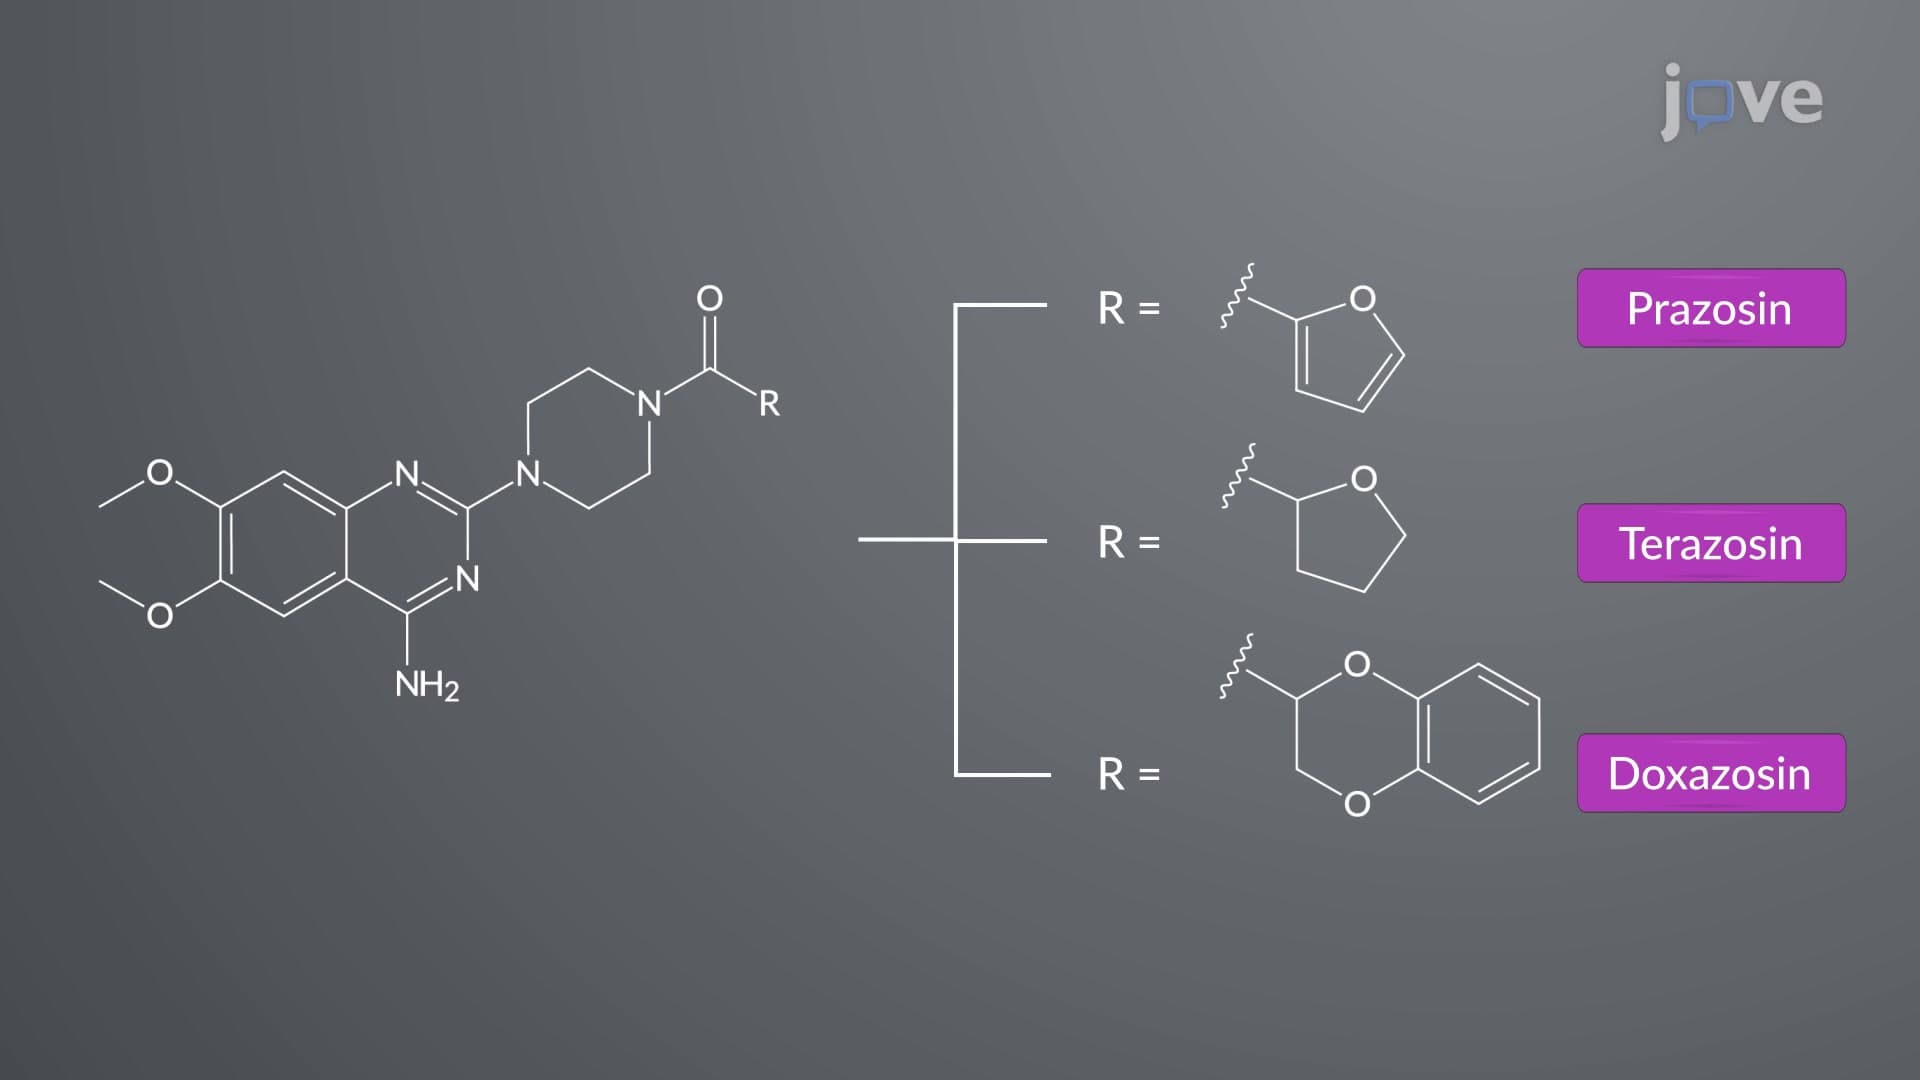
Adrenergic Antagonists: Chemistry and Classification of ɑ-Receptor Blockers
Nonselective α-blockers: Nonselective α-blockers contain haloalkylamine or imidazoline...
 01:25
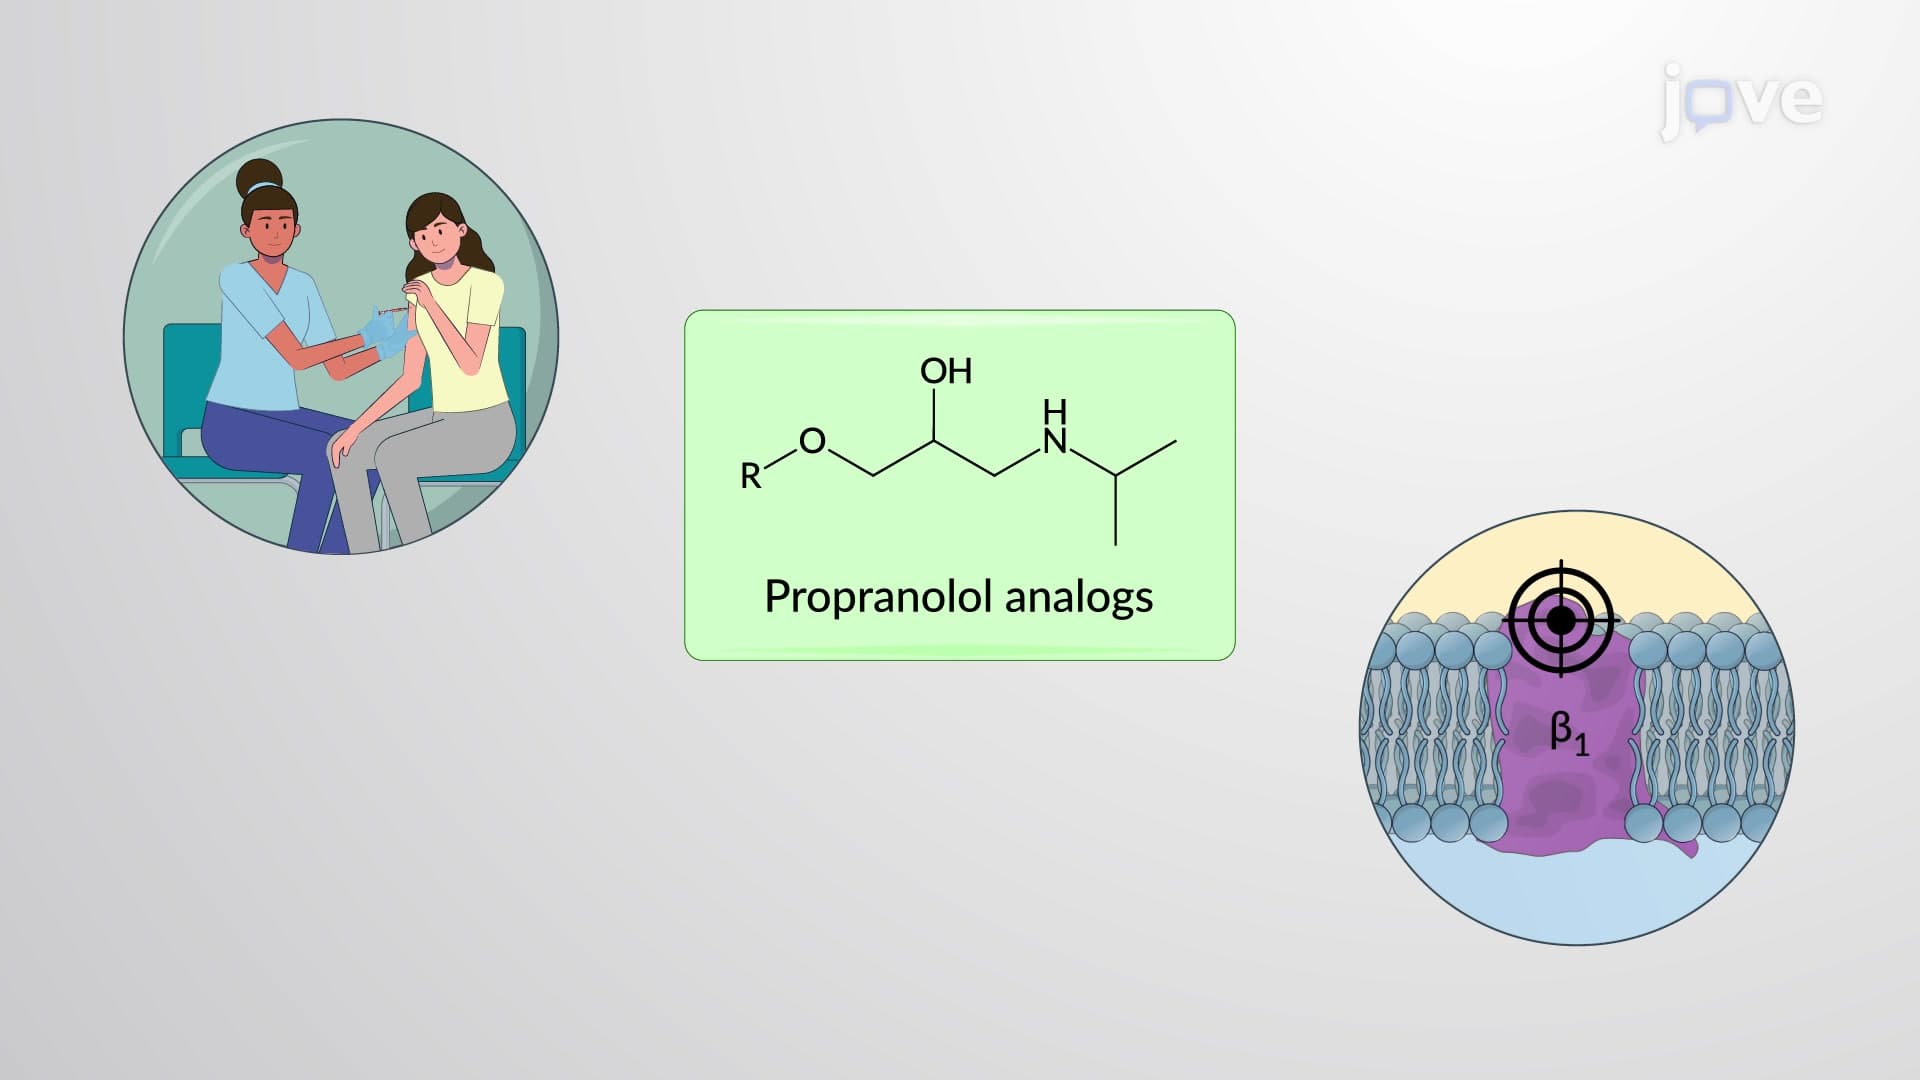
Adrenergic Antagonists: Chemistry and Classification of β-Receptor Blockers
 01:22
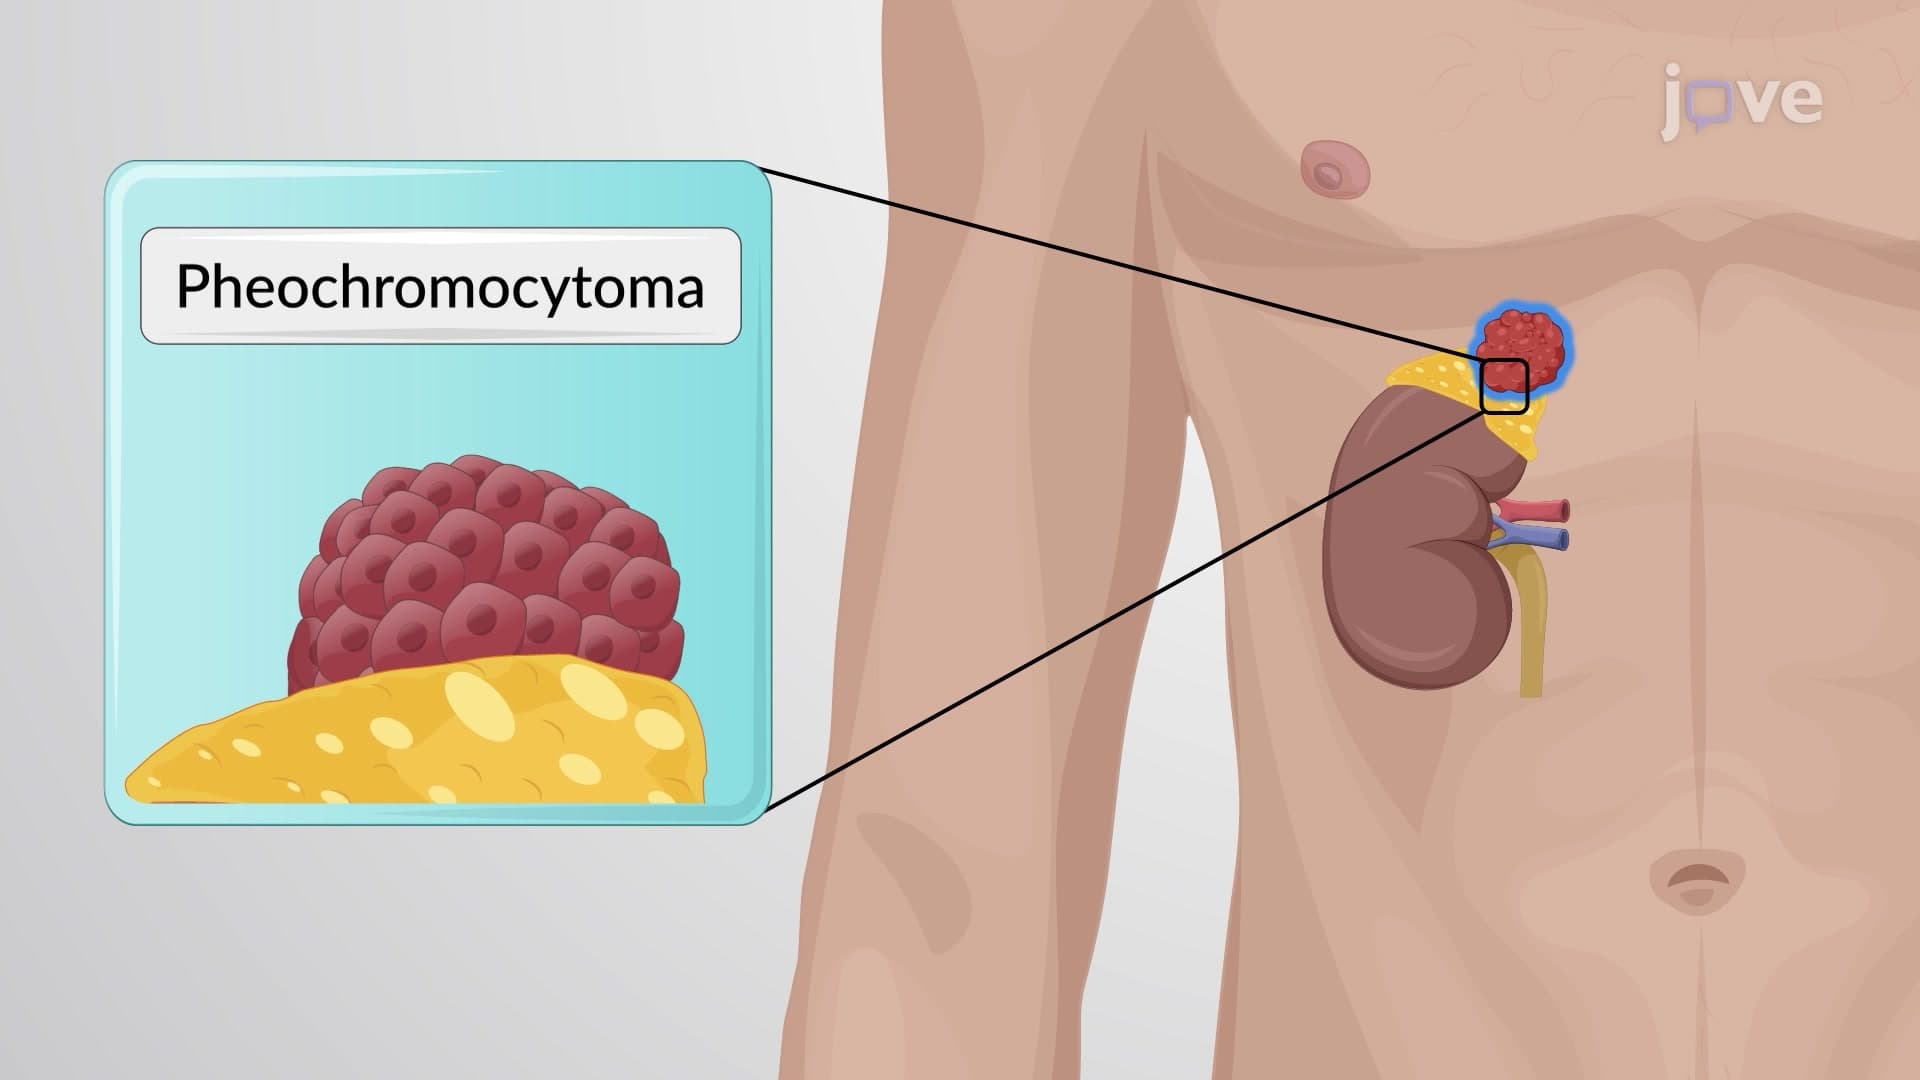
Adrenergic Antagonists: Pharmacological Actions of ɑ-Receptor Blockers
α1-blockers: These drugs inhibit α1-adrenoceptors on smooth muscle cells, resulting in vasodilation. This vasodilation lowers blood pressure, making α1-blockers valuable in treating hypertension. Additionally,...