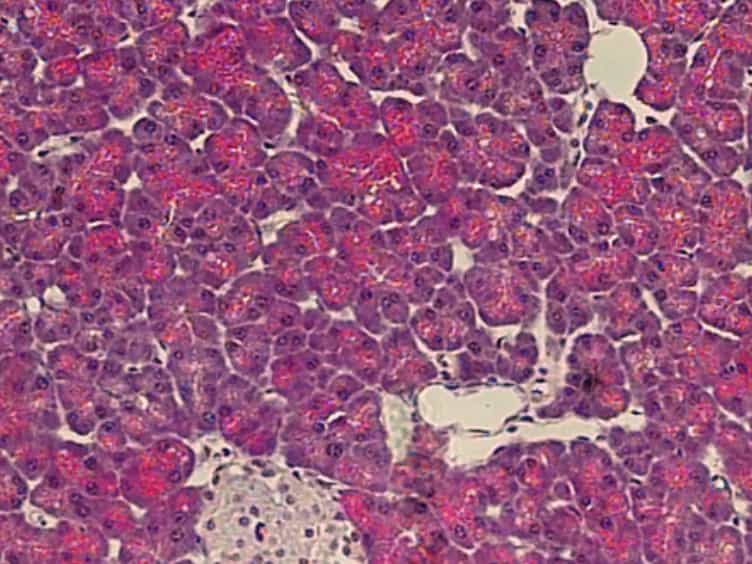

Lessons learned from isolated blunt major pancreatic injury: Surgical experience in one trauma centre
Being-Chuan Lin1, Ray-Jade Chen2, Tsann-Long Hwang3
1Division of Trauma & Emergency Surgery, Department of Surgery, Chang Gung Memorial Hospital, Chang Gung University, Tao-Yuan City, Taiwan.

Introduction:
The aim of this study was to present our surgical experience of isolated blunt major pancreatic injury (IBMPI), and to compare its characteristic outcomes with that of multi-organ injury.
Materials And Methods:
From 1994-2015, 31 patients with IBMPI and 54 patients with multi-organ injury, who underwent surgery, were retrospectively studied.
Results:
Of the 31 patients with IBMPI, 22 were male and 9 were female. The median age was 30 years (interquartile range, 20-38). Twenty-one patients were classified as the American Association for the Surgery of Trauma-Organ Injury Scale Grade III, and 10 patients as Grade IV. Patients with IBMPI had significantly lower shock-at-triage rates, lower injury severity scores, longer injury-to-surgery time, and shorter length of hospital stay than those with multi-organ injury. There were no statistically significant differences in sex, age, trauma mechanism, laboratory data, surgical procedures, and complications between the two groups. Eight patients with IBMPI underwent endoscopic retrograde pancreatography, and 5 patients with complete major pancreatic duct (MPD) disruption underwent pancreatectomy eventually. The remaining 3 patients had partial MPD injury and two of them received a pancreatic duct stent for the treatment of existing postoperative pancreatic fistula. Spleen-sacrificing distal pancreatectomy (SSDP) was performed in 13 patient with IBMPI, followed by spleen-preserving distal pancreatectomy (n = 12), peripancreatic drainage (n = 4), and central pancreatectomy with Roux-en-Y reconstruction (n = 2). The overall complication rates, related to the SSDP, SPDP, peripancreatic drainage, and central pancreatectomy, were 10/13 (77%), 4/12 (33%), 3/4 (75%), and 2/2 (100%), respectively. Three patients died resulting in a 10% mortality rate, and the other 16 patients developed intra-abdominal complications resulting in a 52% morbidity rate. In the subgroup analysis of the 25 patients who underwent distal pancreatectomy, SPDP was associated with a shorter injury-to-surgery time than SSDP.
Conclusions:
Patients with IBMPI have longer injury-to-surgery times, compared to those with multi-organ injury. Of the distal pancreatectomy patients, the time interval from injury to surgery was a significant associated factor in preserving or sacrificing the spleen.
More Related Videos


Related Concept Videos
 01:19
Major Organs of the Digestive System
Gastrointestinal tract:
 01:28
Major Losses in Pipes
Fluid flow can be classified as laminar or turbulent, primarily based on the Reynolds number. This dimensionless number reflects the relative influence of inertial to viscous...
 01:27
Major Hormones and Their Functions
Oxytocin, produced in the hypothalamus and released by the pituitary gland, plays a role in social bonding, childbirth, and...
 01:20
Anatomy of the Brain: Major Regions
The cerebrum is the largest section of the brain and divides into left and right hemispheres, separated by a deep fissure. The cerebral outer layer of grey matter — the cerebral cortex — comprises elevations called gyri and shallow groves called sulci. The inner portion of white matter includes long nerve fibers known as axons, which connect...
 01:28
Major Somatic Sensory Pathways
 01:14
Avoidance Learning and Learned Helplessness
Avoidance learning occurs when an organism learns that a specific behavior can prevent an unpleasant outcome. For example, a student who receives a bad grade may start studying harder to avoid future poor grades. This behavior persists even when the negative outcome is no longer present. Avoidance learning is powerful because it maintains behavior in the absence of the...