Related Experiment Video
Updated: Jan 23, 2026

Transaxillary First Rib Resection for Treatment of the Thoracic Outlet Syndrome
Published on: September 13, 2020
Cardiopulmonary Testing Before Lung Resection: What Are Thoracic Surgeons Doing?
James M Clark1, Angelica S Marrufo1, Benjamin D Kozower2
1Section of General Thoracic Surgery, Department of Surgery, University of California, Davis Health, Sacramento, California.

Insights
Thoracic surgeons show varied practices in preoperative cardiopulmonary assessment for lung resection, with significant differences based on practice type and experience. Adherence to American College of Chest Physicians (ACCP) guidelines is notably low among these specialists.
Area of Science:
- Thoracic Surgery
- Pulmonary Medicine
- Clinical Practice Guidelines
Background:
- Preoperative cardiopulmonary assessment is crucial for risk stratification before lung resection.
- The American College of Chest Physicians (ACCP) provides guidelines to support decision-making in these assessments.
Purpose of the Study:
- To evaluate the current cardiopulmonary assessment practices of thoracic surgeons.
- To determine the extent of adherence to ACCP guidelines among these surgeons.
Main Methods:
- An anonymous survey was distributed to 846 thoracic surgeons.
- Responses were analyzed based on practice type (general thoracic vs. cardiothoracic) and years in practice.
- Survey data was compared against ACCP guideline recommendations.
Main Results:
- A 24.0% response rate was achieved (n=203).
- Most surgeons (59.6%) used a predicted postoperative forced expiratory volume in 1 second or diffusing capacity of lung for carbon monoxide threshold of 40%.
- Experienced surgeons were more likely to vary thresholds by surgical approach (P=.007).
- Significant differences in referral practices to cardiology were observed between general thoracic and cardiothoracic surgeons (P<.001).
- Only 0.5% of respondents were 100% adherent to ACCP guidelines, with 4.4% and 45.8% adhering to 75% and 50% of guidelines, respectively.
Conclusions:
- There is considerable variation in preoperative cardiopulmonary assessment practices among thoracic surgeons.
- These variations differ by practice type and surgeon experience.
- Marked discordance with ACCP guidelines was observed, warranting further investigation into the impact of adherence on patient outcomes.
Background:
Cardiopulmonary assessment for lung resection is important for risk stratification, and the American College of Chest Physicians (ACCP) guidelines provide decision support. We ascertained the cardiopulmonary assessment practices of thoracic surgeons and determined whether they are guideline concordant.
Methods:
An anonymous survey was emailed to 846 thoracic surgeons who participate in The Society of Thoracic Surgeons General Thoracic Surgery Database. We analyzed survey responses by practice type (general thoracic [GT] versus cardiothoracic [CT]) and years in practice (0-9, 10-19, and ≥20) with the use of contingency tables. We compared adherence of survey responses with the guidelines.
Results:
The response rate was 24.0% (n = 203). Most surgeons (n = 121, 59.6%) cited a predicted postoperative forced expiratory volume in 1 second or diffusing capacity of lung for carbon monoxide threshold of 40% for further evaluation. Experienced surgeons (≥20 years) were more likely to have a threshold that varies by surgical approach (31.3% versus 23.5% with 10-19 years of experience and 15.9% for 0-9 years of experience, P = .007). Overall, 52.2% refer patients with cardiovascular risk factors to cardiology and 42.9% refer patients with abnormal stress testing. CT surgeons were more likely to refer all patients to cardiology than GT surgeons (17.6% versus 2.4%, P < .001). Only one respondent (0.5%) was 100% adherent to the ACCP guidelines, and 4.4% and 45.8% were 75% and 50% adherent, respectively.
Conclusions:
Among thoracic surgeons, there is variation in preoperative cardiopulmonary assessment practices, with differences by practice type and years in practice, and marked discordance with the ACCP guidelines. Further study of guideline adherence linked to postoperative morbidity and mortality is warranted to determine whether adherence affects outcomes.

Related Concept Videos
 01:15
Thoracic Aorta
 01:17
The Thoracic Cage: Sternum
The sternum is the elongated bony structure on the anterior side of the thoracic cage. It consists of three parts: the manubrium, the body, and the xiphoid...
 01:20
The Thoracic Cage: Ribs
Parts of a Typical Rib
A typical rib has a head, neck, and body. The posterior end of the rib is called the head, followed by a narrow neck. The head articulates primarily with the costal...
 01:21
Cardiopulmonary Resuscitation I: Adult
 01:47
Lung Capacity
 01:24
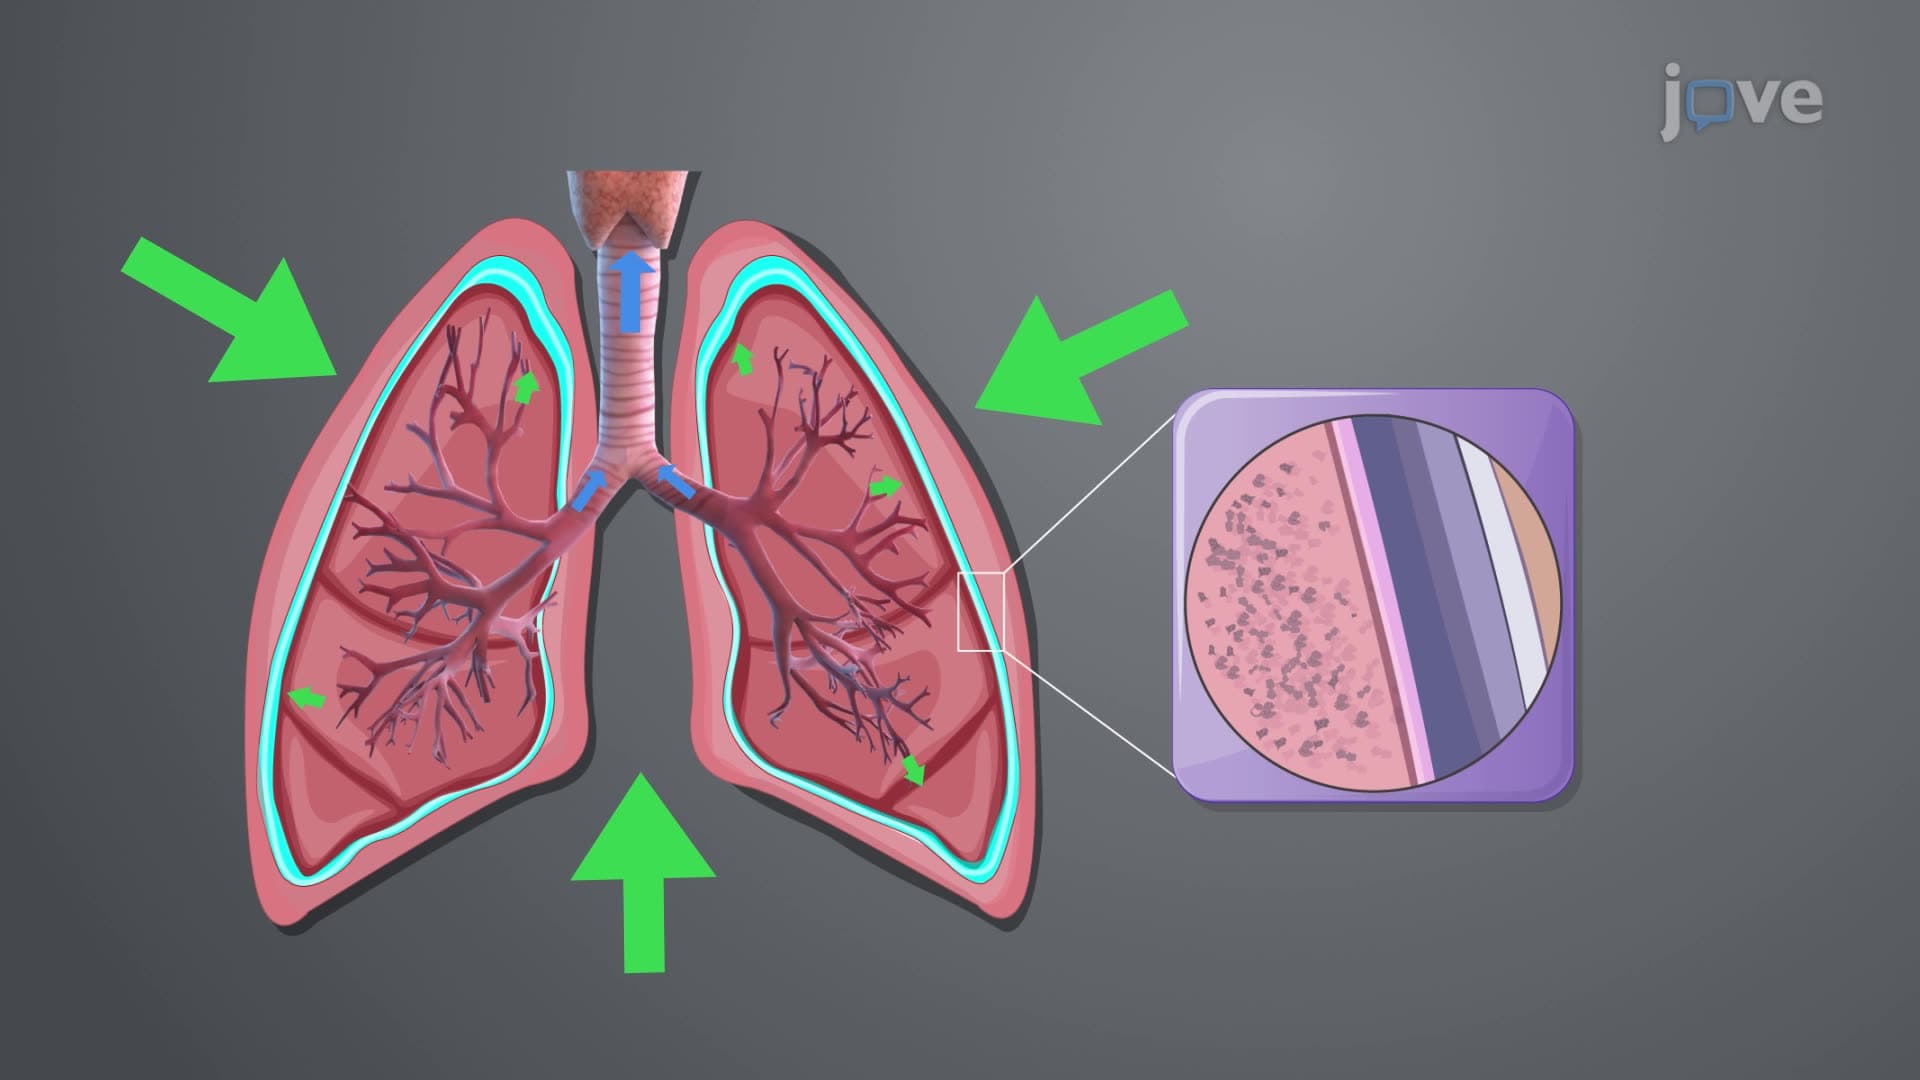
Pressure Relationships in Thoracic Cavity
Breathing Mechanisms
Both intra-alveolar and intrapleural pressures rely on specific lung properties. The ability to breathe—allowing air to enter the lungs...