Related Experiment Video
Updated: Jan 23, 2026
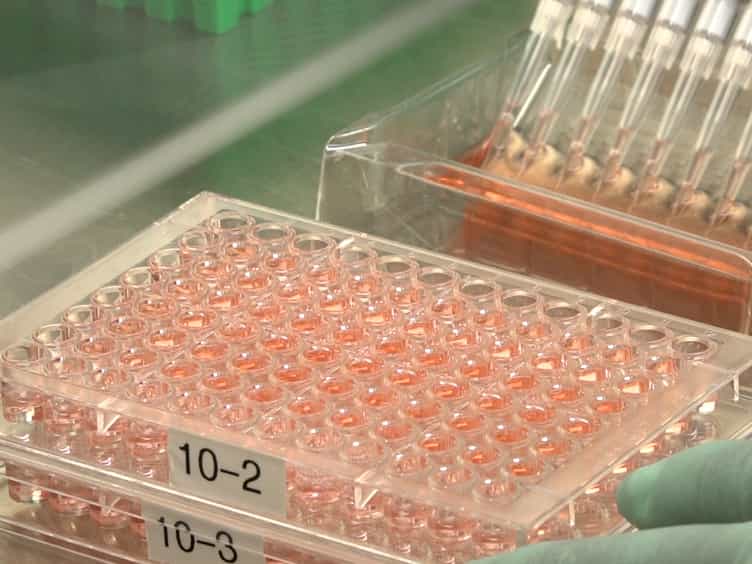

Measuring Influenza Neutralizing Antibody Responses to AH3N2 Viruses in Human Sera by Microneutralization Assays Using MDCK-SIAT1 Cells
Published on: November 22, 2017
Influenza virus-related critical illness: prevention, diagnosis, treatment
Eric J Chow1,2, Joshua D Doyle1,2, Timothy M Uyeki3
1Epidemic Intelligence Service, Centers for Disease Control and Prevention, Atlanta, GA, USA.

Abstract:
Annual seasonal influenza epidemics of variable severity result in significant morbidity and mortality in the United States (U.S.) and worldwide. In temperate climate countries, including the U.S., influenza activity peaks during the winter months. Annual influenza vaccination is recommended for all persons in the U.S. aged 6 months and older, and among those at increased risk for influenza-related complications in other parts of the world (e.g. young children, elderly). Observational studies have reported effectiveness of influenza vaccination to reduce the risks of severe disease requiring hospitalization, intensive care unit admission, and death. A diagnosis of influenza should be considered in critically ill patients admitted with complications such as exacerbation of underlying chronic comorbidities, community-acquired pneumonia, and respiratory failure during influenza season. Molecular tests are recommended for influenza testing of respiratory specimens in hospitalized patients. Antigen detection assays are not recommended in critically ill patients because of lower sensitivity; negative results of these tests should not be used to make clinical decisions, and respiratory specimens should be tested for influenza by molecular assays. Because critically ill patients with lower respiratory tract disease may have cleared influenza virus in the upper respiratory tract, but have prolonged influenza viral replication in the lower respiratory tract, an endotracheal aspirate (preferentially) or bronchoalveolar lavage fluid specimen (if collected for other diagnostic purposes) should be tested by molecular assay for detection of influenza viruses.Observational studies have reported that antiviral treatment of critically ill adult influenza patients with a neuraminidase inhibitor is associated with survival benefit. Since earlier initiation of antiviral treatment is associated with the greatest clinical benefit, standard-dose oseltamivir (75 mg twice daily in adults) for enteric administration is recommended as soon as possible as it is well absorbed in critically ill patients. Based upon observational data that suggest harms, adjunctive corticosteroid treatment is currently not recommended for children or adults hospitalized with influenza, including critically ill patients, unless clinically indicated for another reason, such as treatment of asthma or COPD exacerbation, or septic shock. A number of pharmaceutical agents are in development for treatment of severe influenza.


Related Concept Videos
 01:18
Models of Health Promotion and Illness Prevention II
The agent-host-environment model states that disease results...
 01:26
Levels of Health Promotion and Illness Prevention
In primary prevention, actions taken before disease onset prevent the disease from...
 01:25
Models of Health Promotion and Illness Prevention I
The health belief model (HBM) attempts to predict health-related behavior in specific belief patterns. According to the HBM, a person's...
 01:17
Classification of Illness
An illness is a response to a disease in which the person's level of functioning is changed compared with a previous level. The general classification of illness includes acute and chronic.
Acute illness is severe...
 01:18
Factors Affecting Illness
For instance, risk factors are connected to illness,...
 01:29
Concepts of Health and Illness