Related Experiment Video
Updated: Jan 23, 2026


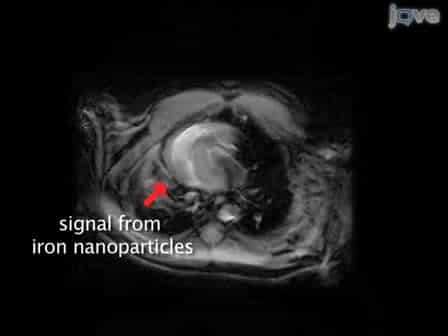
Magnetic Resonance Imaging Quantification of Pulmonary Perfusion using Calibrated Arterial Spin Labeling
Published on: May 30, 2011
Optimizing human pulmonary perfusion measurement using an in silico model of arterial spin labeling magnetic
Daniel A Addo1, Wendy Kang1, Gordon Kim Prisk2
1Auckland Bioengineering Institute, University of Auckland, Auckland, New Zealand.

Abstract:
Arterial spin labeling (ASL) magnetic resonance imaging (MRI) is an imaging methodology that uses blood as an endogenous contrast agent to quantify flow. One limitation of this method of capillary blood quantification when applied in the lung is the contribution of signals from non-capillary blood. Intensity thresholding is one approach that has been proposed for minimizing the non-capillary blood signal. This method has been tested in previous in silico modeling studies; however, it has only been tested under a restricted set of physiological conditions (supine posture and a cardiac output of 5 L/min). This study presents an in silico approach that extends previous intensity thresholding analysis to estimate the optimal "per-slice" intensity threshold value using the individual components of the simulated ASL signal (signal arising independently from capillary blood as well as pulmonary arterial and pulmonary venous blood). The aim of this study was to assess whether the threshold value should vary with slice location, posture, or cardiac output. We applied an in silico modeling approach to predict the blood flow distribution and the corresponding ASL quantification of pulmonary perfusion in multiple sagittal imaging slices. There was a significant increase in ASL signal and heterogeneity (COV = 0.90 to COV = 1.65) of ASL signals when slice location changed from lateral to medial. Heterogeneity of the ASL signal within a slice was significantly lower (P = 0.03) in prone (COV = 1.08) compared to in the supine posture (COV = 1.17). Increasing stroke volume resulted in an increase in ASL signal and conversely an increase in heart rate resulted in a decrease in ASL signal. However, when cardiac output was increased via an increase in both stroke volume and heart rate, ASL signal remained relatively constant. Despite these differences, we conclude that a threshold value of 35% provides optimal removal of large vessel signal independent of slice location, posture, and cardiac output.
More Related Videos

Related Concept Videos
 01:24
Magnetic Resonance Imaging
 01:27
Imaging Studies IV: Magnetic Resonance Imaging
 01:05
Atomic Nuclei: Magnetic Resonance
 01:07
Nuclear Magnetic Resonance (NMR): Overview
NMR spectroscopy generates a spectrum where the characteristic absorption frequencies of the sample are...
 01:28
Treatment for Pulmonary Arterial Hypertension: Phosphodiesterase Inhibitors
Among the PDE5 inhibitors, sildenafil (Revatio) stands out as a competitive and selective inhibitor. It operates by elevating cellular levels of cGMP and augmenting signaling through the cGMP-PKG pathway, promoting vasodilation. Upon oral...
 02:52
Resonance