Early Real-World Experience with EndoAnchors by Indication
Related Experiment Video
Updated: Jan 23, 2026
A Novel In Vitro Live-imaging Assay of Astrocyte-mediated Phagocytosis Using pH Indicator-conjugated Synaptosomes
Published on: February 5, 2018
Vy T Ho1, Elizabeth L George1, Anahita Dua1
1Division of Vascular Surgery, Department of Surgery, Stanford University, Stanford, CA.

Background:
The Heli-FX EndoAnchor (EA) system is a transmural aortic fixation device with Federal Drug Administration (FDA) approval for treatment of endoleaks, endograft migration, or high-risk seal zones. Published data are primarily from industry-sponsored registries highlighting safety and efficacy. Our objective is to evaluate real-world outcomes of EA usage after FDA approval across a variety of stent grafts and indications at a single institution.
Methods:
We retrospectively reviewed our prospectively maintained aneurysm database for patients undergoing endovascular aortic repair (EVAR) with Heli-FX EAs. Technical success was defined as successful EA deployment, while procedural success was defined as absence of endoleak on completion aortogram. Cohorts were divided by indication and outcomes assessed via review of clinical and radiographic data.
Results:
From 2016 to 2018, 37 patients underwent EA fixation. We divided the cohort by indication: Group A (prior EVAR with endoleak), B (intraoperative type 1A endoleak), C (high-risk seal zone), and D (thoracic EVAR). In Group A (n = 11), all endoleaks were type 1A and a mean of 10 EAs were deployed with 100% technical and 45.4% procedural success. Two perioperative reinterventions were performed (translumbar coil embolization and proximal graft extension with bilateral renal artery stents). At a mean 10.6 months of follow-up, 45.4% of patients had persistent endoleaks, with 100% aortic-related survival. In Group B (n = 10), a mean of 8.7 EAs were used with 100% technical and procedural success. One immediate adverse event occurred (right iliac dissection from wire manipulation, treated with a covered stent). At 13.6-month mean follow-up, there was significant sac regression (mean 9.75 mm) with no type 1A endoleaks. In Group C (n = 10), a mean of 9.5 EAs were deployed with 100% technical and procedural success. At 11.2-month mean follow-up, there were no residual endoleaks and significant sac regression (mean 3.4 mm). Overall survival was 100%. In Group D (n = 6), a mean of 8.3 EAs were used with 83.3% technical and 66.6% procedural success. One immediate adverse event occurred, in which an EA embolized to the left renal artery. At 9.4-month mean follow-up, overall survival was 83.3% with a mean 2.2-mm increase in sac diameter.
Conclusions:
Early experience suggests that EAs effectively treat intraoperative type 1A endoleaks and high-risk seal zones, with significant sac regression and no proximal endoleaks on follow-up. In patients treated for prior EVAR with postoperative type 1A endoleaks, fewer than half resolved after EA attempted repair. Further experience and longer term follow-up will be necessary to determine which patients most benefit from postoperative EA fixation.

Related Concept Videos
 02:39
Indicators
 01:12
What is an Experiment?
 01:29
Mechanical Ventilation I: Indication and Settings
 01:19
Respiratory Assessment: Purpose and Indications
Objectives and Importance:
The primary goal of respiratory assessment is to evaluate patients at early risk of clinical deterioration. Since respiratory distress often precedes other signs of declining health, breathing patterns and sounds become a...
 01:19
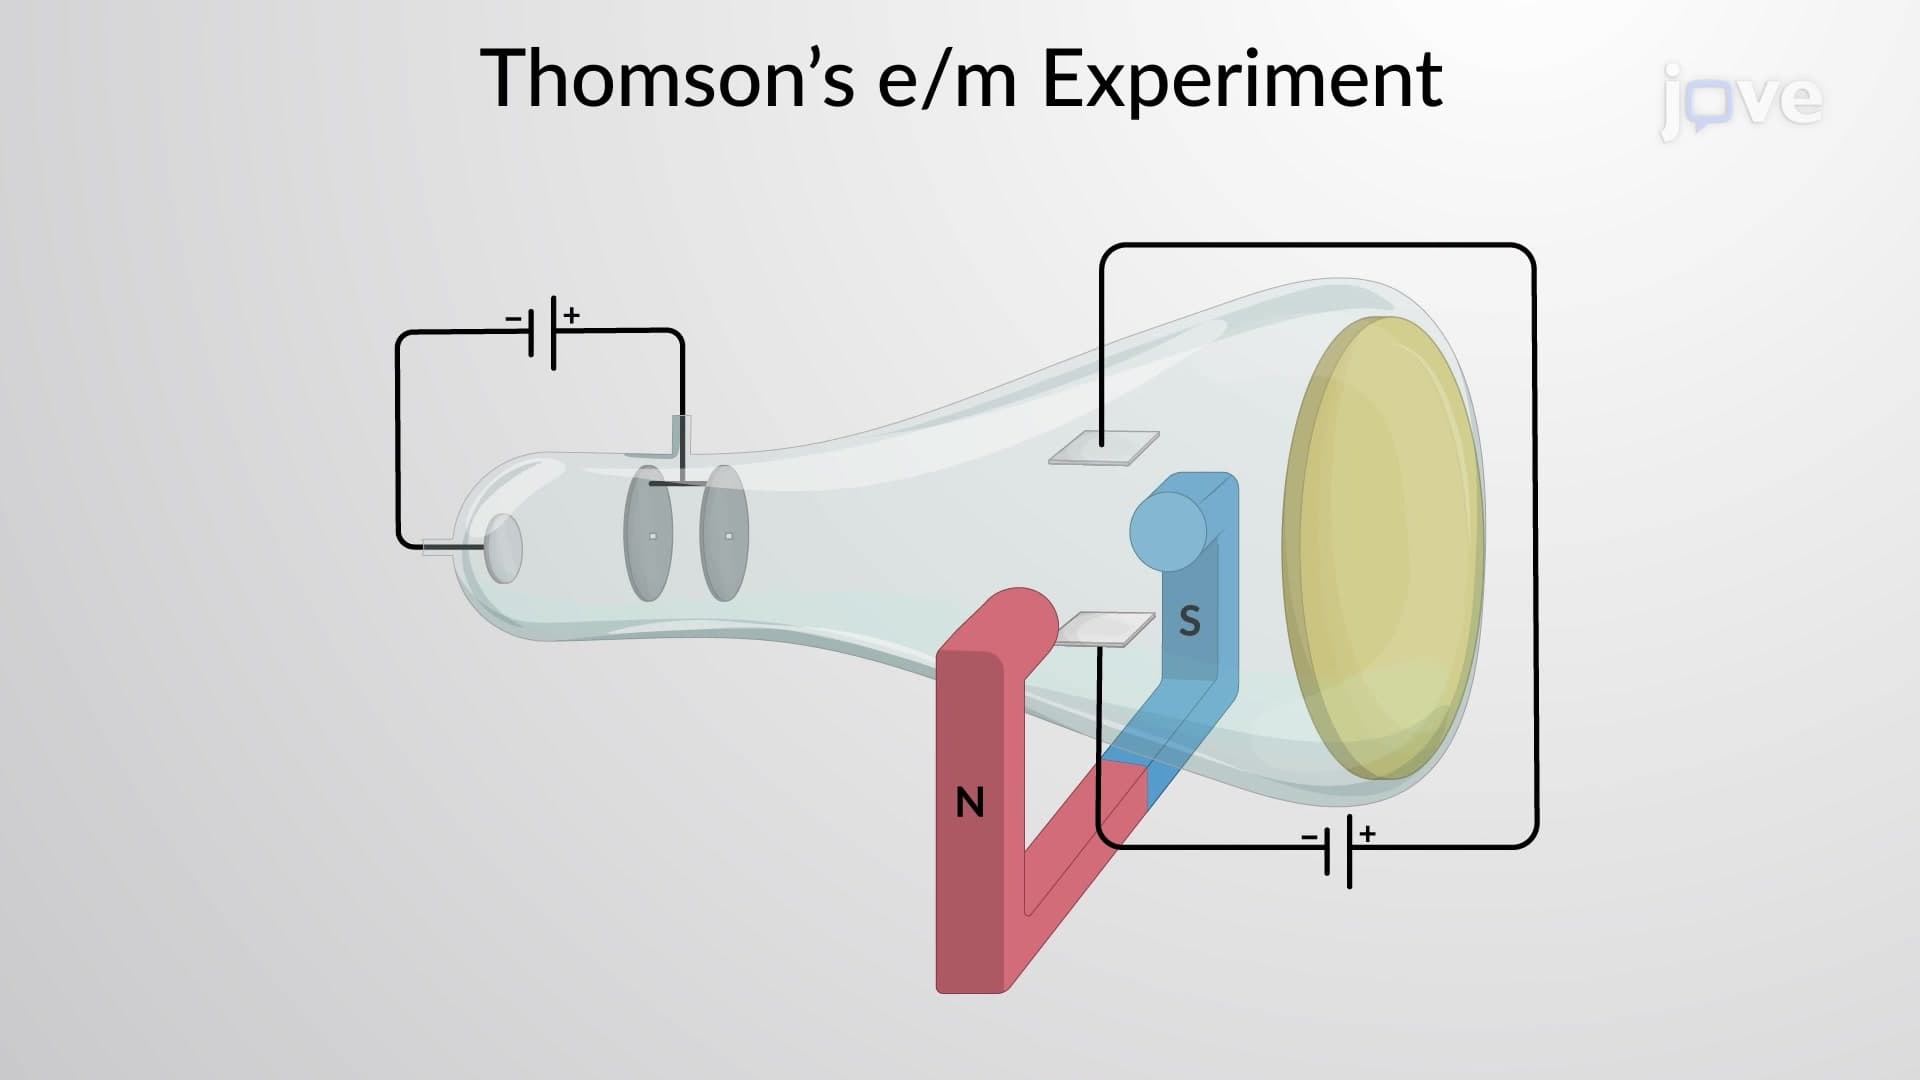
Thomson's e/m Experiment
A particle with charge q, speed v, and mass m enters an area from the top, where the magnetic and electric fields are perpendicular both to the particle's motion and to one another. The magnetic...
 01:09
Bioequivalence of Drugs: Drugs with Multiple Indications