Related Experiment Video
Updated: Jan 23, 2026
The Rabbit Model of Accelerated Atherosclerosis: A Methodological Perspective of the Iliac Artery Balloon Injury
Published on: October 3, 2017
Is it necessary to dilate stents in management of nonthrombotic iliac vein lesions?
Afsha Aurshina1, Yuriy Ostrozhynskyy1, Hoang Nguyen1
1Vascular Institute of New York, Brooklyn, NY.

Objective:
Iliac vein stenting is an evolving treatment option for chronic venous insufficiency and management of nonthrombotic iliac vein lesions (NIVLs). Currently described protocols recommend deployed stents to be dilated with balloon venoplasty before completion of the procedure, based on previous literature established from management of arterial lesions. The objective of the study was to investigate the role of balloon venoplasty after stent deployment in the management of NIVLs.
Methods:
During the course of 6 months, 71 balloon venoplasties with stenting of iliac veins (34 right and 37 left limbs) were performed. Intraoperatively, we used intravascular ultrasound to measure and to record area of iliofemoral veins. The measurement of stenosis was compared with adjacent nonstenotic iliofemoral veins. If >50% cross-sectional area or diameter reduction was found, it was treated with an appropriate balloon size (range, 10 × 40 mm to 16 × 60 mm) and Wallstent (Boston Scientific, Natick, Mass; 12-24 mm in diameter by 40-90 in mm length). All stents were dilated with a balloon after deployment. Intravascular ultrasound was used to measure the preoperative area of stenotic lesion, area of lesion after stenting, and area after balloon dilation of the stent.
Results:
The mean age of the patients was 65.34 years (range, 36-99 years; standard deviation [SD], ±13.52 years), with 27 female and 20 male patients. The location of the targeted stenosis was the common iliac vein (31), external iliac vein (36), and common femoral vein (4). The mean area of the stenotic lesion was 99.06 mm2 (range, 28-318 mm2; SD, ±45.87 mm2). The mean area after stenting was 151.51 mm2 (range, 28-303 mm2; SD, ±55.82 mm2). The mean area after dilation of the stent was 162.72 mm2 (range, 86-367 mm2; SD, ±51.94 mm2; P = .22). No statistically significant correlation was found between difference in areas and age of the patient, clinical class (C2-C6), sex, lesion, laterality, and location of targeted lesion. One patient developed an intraluminal partial thrombus within 30 days of intervention.
Conclusions:
Our preliminary data show no significant clinical or technical benefit with use of balloon venoplasty to dilate stents after deployment in NIVLs. Postdilation should thus be limited to only those with suboptimal self-expansion of stent after initial deployment on fluoroscopic imaging.

Related Concept Videos
 01:30
Cardiomyopathy II: Dilated Cardiomyopathy
 01:17
Veins
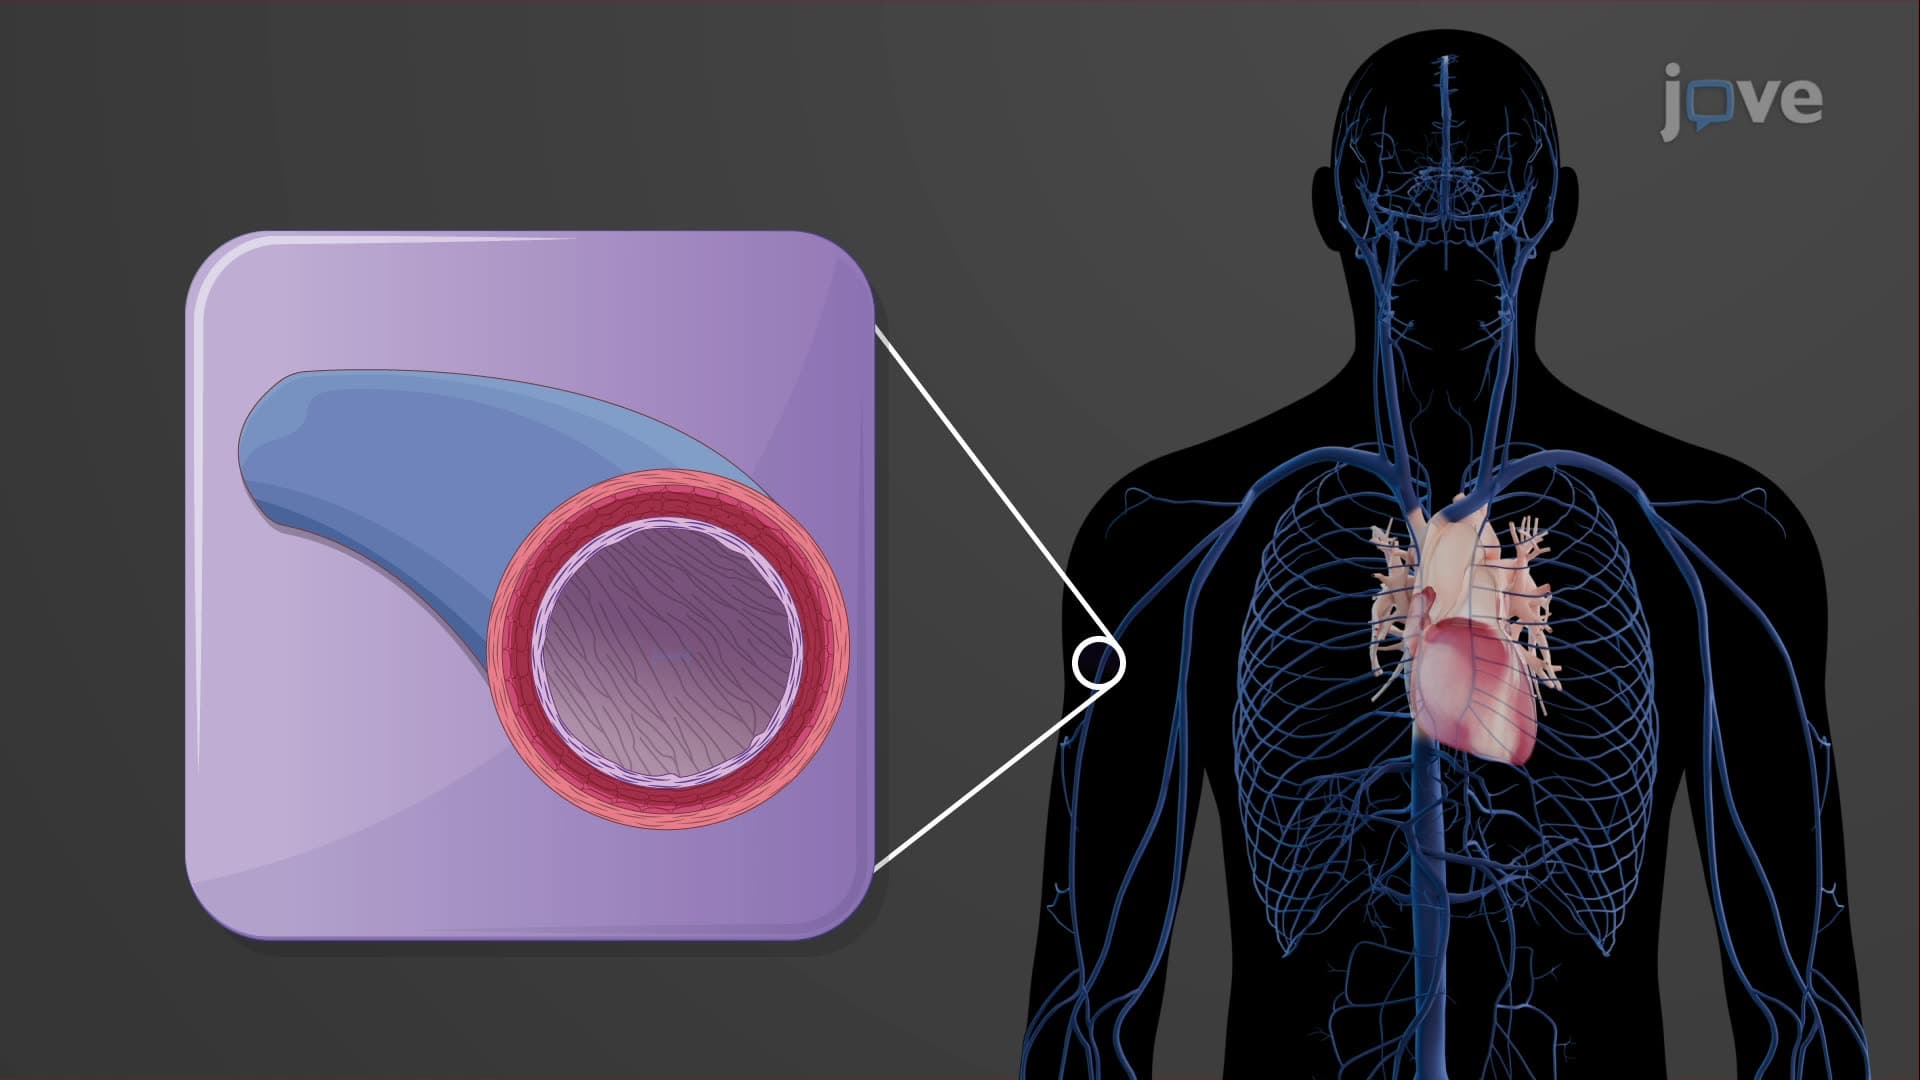
Structure of Veins:
The structure of veins is specifically designed to assist in the low-pressure transportation of...
 01:19
Veins of Thorax
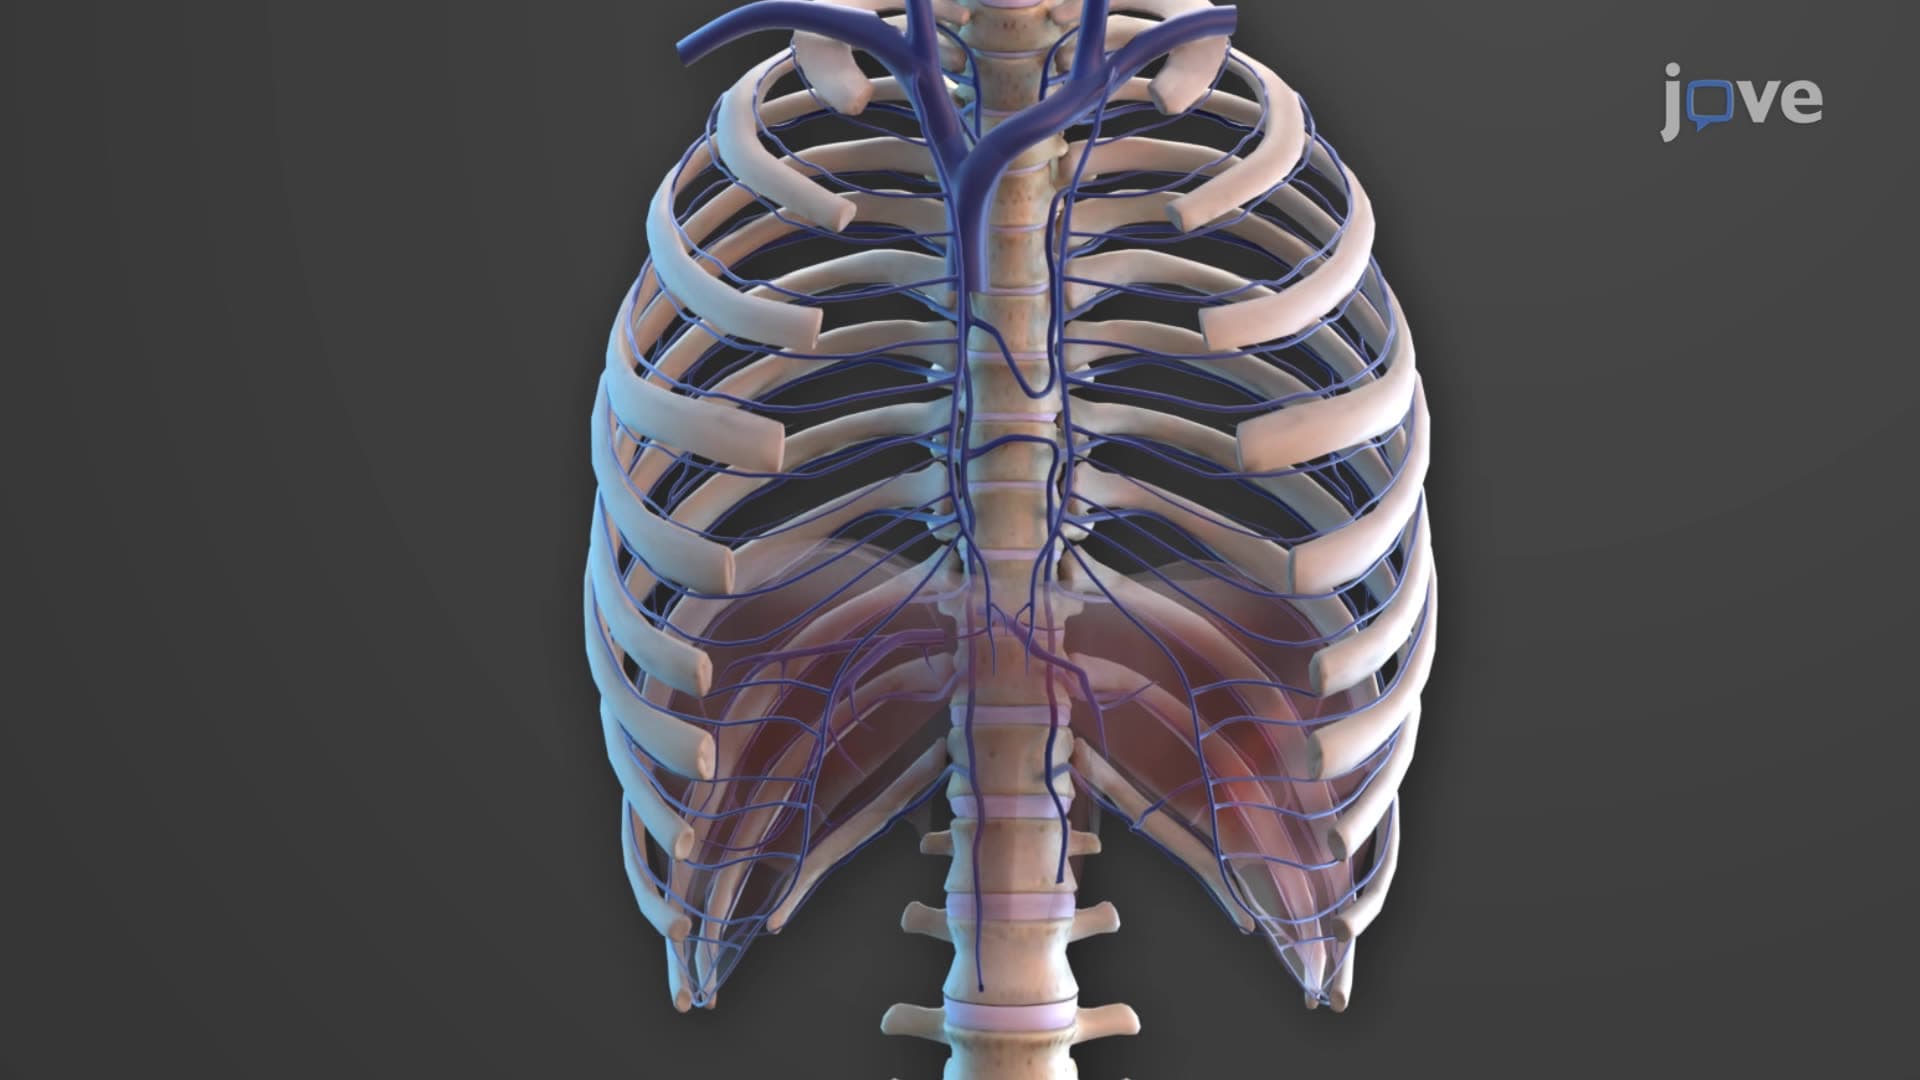
The azygos vein, positioned just right of the midline and anterior to the vertebral column, begins at the junction of the right ascending lumbar and subcostal veins, terminating in the superior vena cava. This vein drains blood from the right side of the thoracic wall, thoracic viscera, and posterior abdominal wall.
The...
 01:15
Veins of Lower Limbs
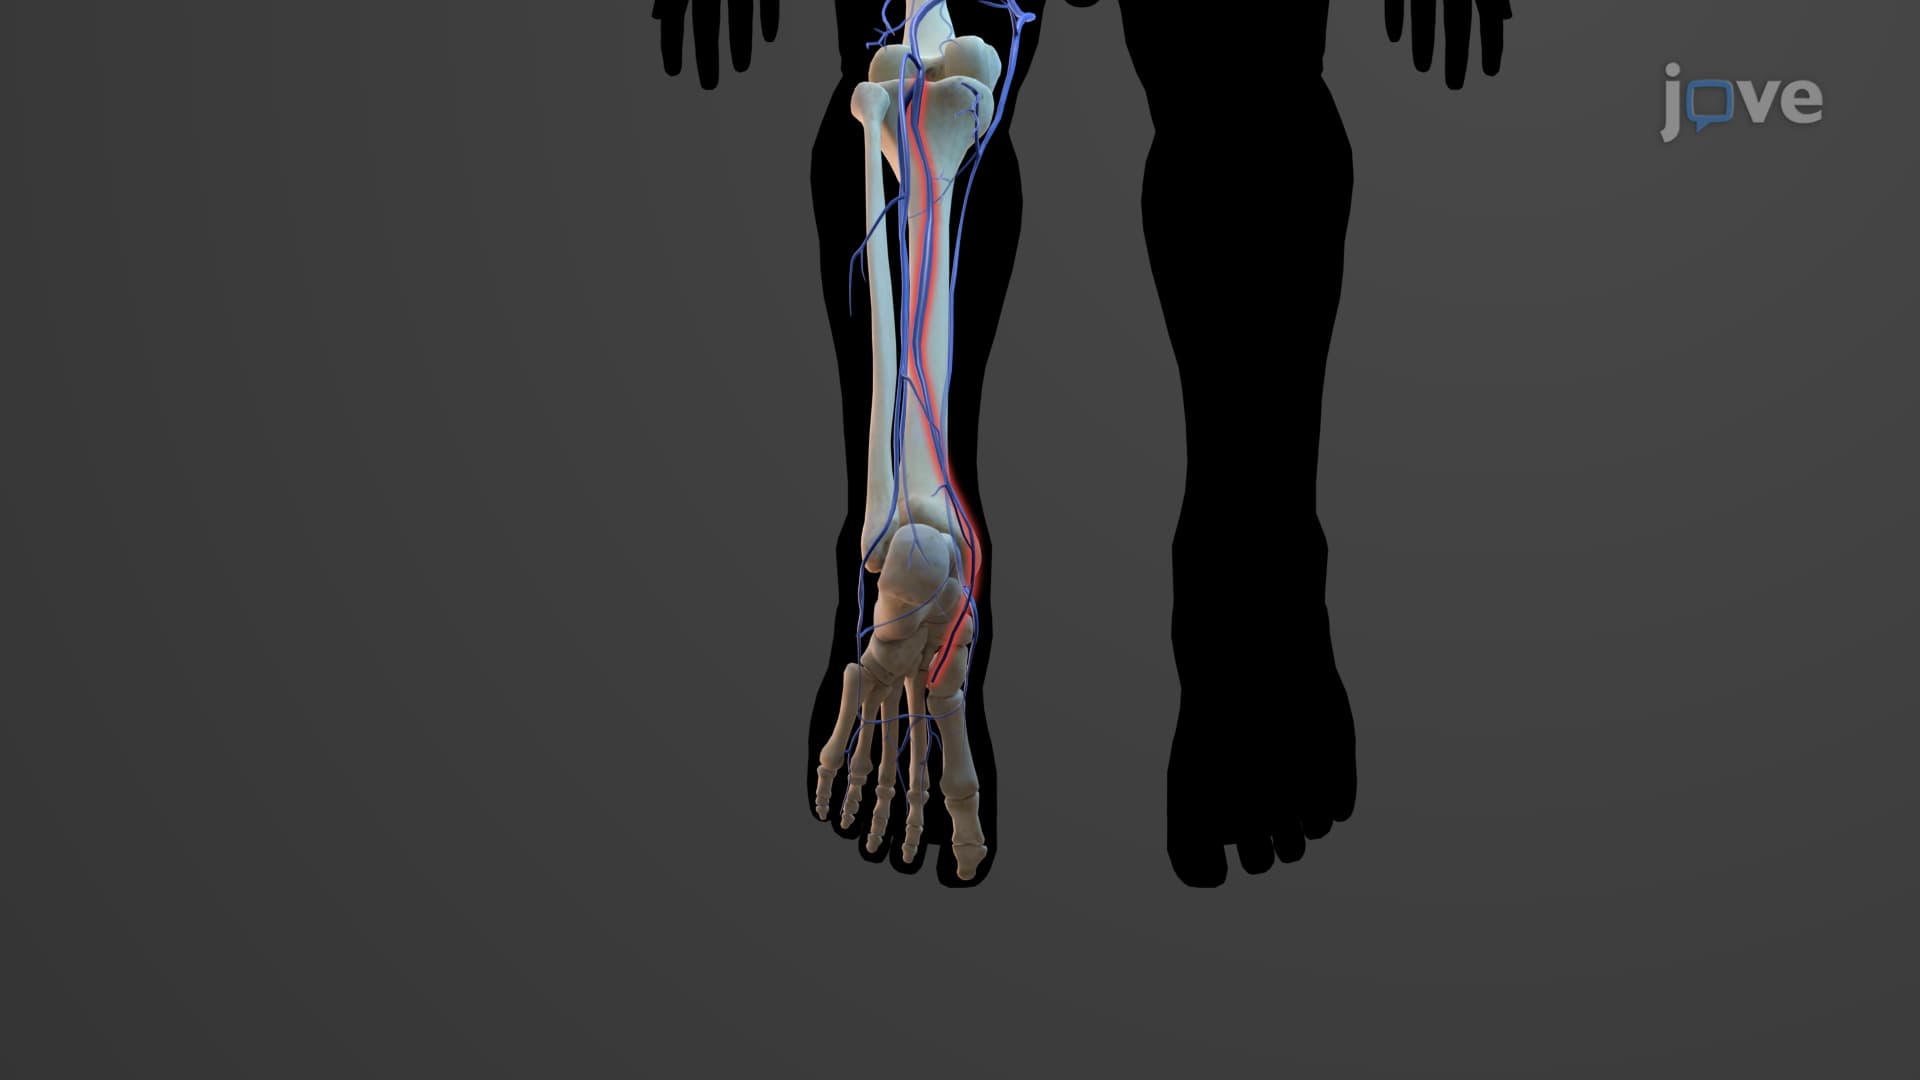
Formed by the union of the medial and lateral plantar veins, the posterior tibial vein, rising through the calf muscle, assimilates the fibular vein. The anterior tibial vein, a superior extension of the foot's dorsalis pedis vein, merges with the posterior tibial vein at the...
 01:29
Impression Management Techniques I: Managing Appearances
 01:10
Veins as Blood Reservoirs