Related Experiment Video
Updated: Jan 23, 2026


Robot-assisted Total Mesorectal Excision and Lateral Pelvic Lymph Node Dissection for Locally Advanced Middle-low Rectal Cancer
Published on: February 12, 2022
Transanal endoscopic microsurgery for rectal lesions in a specialist regional early rectal cancer centre: the Mersey
M Ondhia1, P Tamvakeras2, P O'Toole1
1Royal Liverpool and Broadgreen University Hospital NHS Trust, Liverpool, UK.

Aim:
Organ-preserving local excision by transanal endoscopic microsurgery (TEM) for early rectal cancer offers significantly lower morbidity as compared to formal rectal cancer resection with acceptable outcomes. This study presents our 6-year experience of TEM for rectal lesions referred to a specialist early rectal cancer centre in the UK.
Method:
Data were collected for all patients referred for TEM of suspected early rectal cancer to a regional specialist early rectal cancer multidisciplinary team (MDT) over a 6-year period.
Results:
One hundred and forty-one patients who underwent full-thickness TEM for suspected or confirmed early rectal cancer were included. Thirty patients were referred for TEM following incomplete endoscopic polypectomy. Final pathology was benign in 77 (54.6%) cases and malignant in 64 (45.4%). Of the 61 confirmed adenocarcinomas, TEM resections were pT0 in 17 (27.9%), pT1 in 32 (51.7%), pT2 in 11 (18.0%) and pT3 in 1 (1.6%). Thirty-eight of 61 patients (62.3%) had one or more poor histological prognostic features and these patients were offered further treatment. Twenty-three of 61 (37.7%) patients with rectal adenocarcinoma required no further treatment following TEM. Forty-three cases of rectal adenocarcinoma were available for establishing recurrence rates. Two of 43 patients (4.7%) developed a recurrence at a median follow-up of 28.7 months (12.1-66.5 months). The overall estimated 5-year overall survival rate was 87.9% and the disease-free survival rate was 82.9%.
Conclusion:
Acceptable outcomes are possible for TEM surgery with appropriate patient selection, effective technique, expert histopathology, appropriate referral for adjuvant treatment and meticulous follow-up. This can be achieved through an early rectal cancer MDT in a dedicated specialist regional centre.
More Related Videos
 07:22
Surgical Robot-Assisted Transanal Specimen Extraction Radical Sigmoidectomy Without an Auxiliary Abdominal Incision
Published on: June 13, 2025
 05:32
Povidone Iodine Rectal Preparation at Time of Prostate Needle Biopsy is a Simple and Reproducible Means to Reduce Risk of Procedural Infection
Published on: September 21, 2015
Related Concept Videos
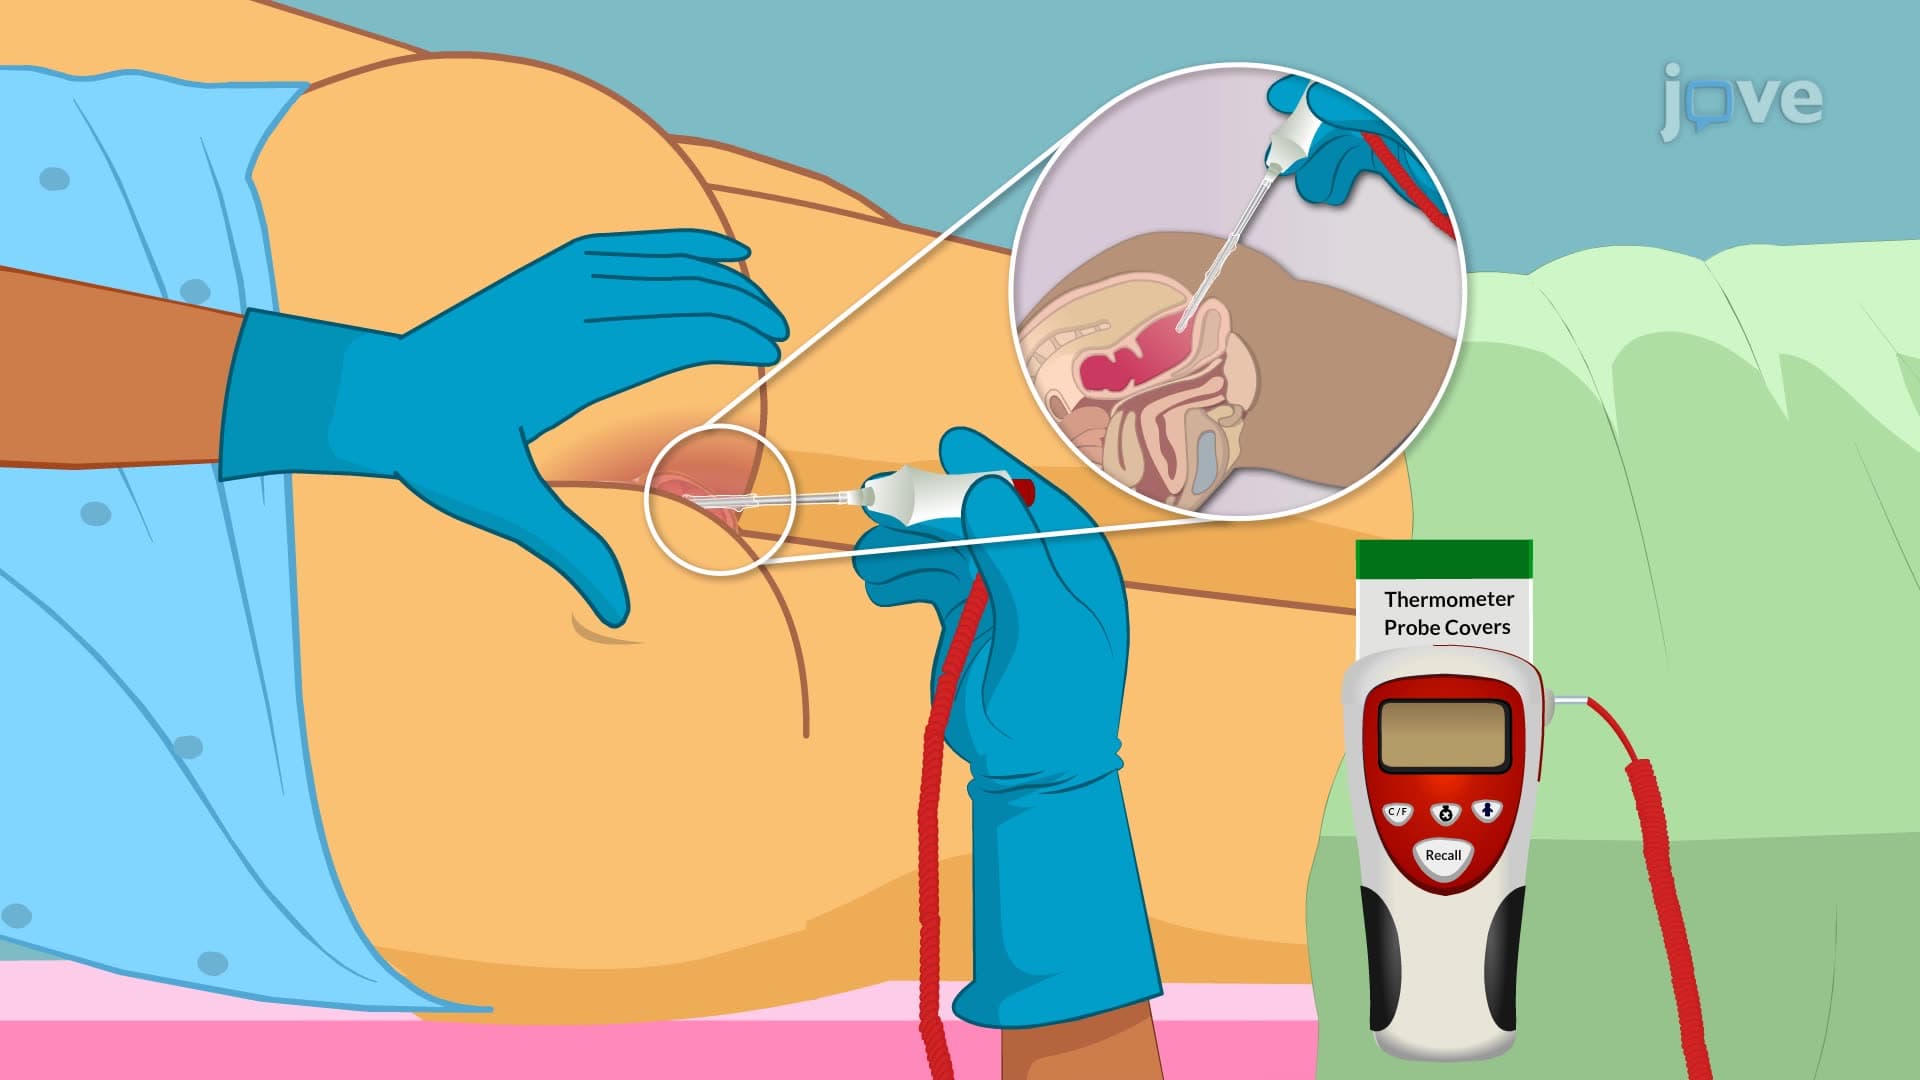 01:27
Assessing Body Temperature - Rectal
Follow these steps for rectal temperature assessment:
Step 1: Perform hand hygiene and don clean gloves to prevent cross-infection.
Step 2: Position the patient in a side-lying position to better visualize the rectal...
 01:03
IR Frequency Region: Fingerprint Region
 02:40
The Eukaryotic Promoter Region
 01:12
What is an Experiment?
 01:17
Region of Convergence
 01:12
Regional Terms
Primarily, the human body has two major regions, the axial and appendicular regions. The axial region comprises regions from the head to the abdomen and makes up the central body axis. In contrast,...