Related Experiment Video
Updated: Jan 23, 2026

Invasive Hemodynamic Characterization of the Portal-hypertensive Syndrome in Cirrhotic Rats
Published on: August 1, 2018
Performance of Controlled Attenuation Parameter in Patients with Advanced Chronic Liver Disease and Portal
Georg Semmler1,2, Judith Stift3, Bernhard Scheiner1,2
1Division of Gastroenterology and Hepatology, Department of Internal Medicine III, Medical University of Vienna, Vienna, Austria.

Background:
Liver stiffness (LS) measured by vibration-controlled transient elastography (VCTE) is influenced by liver fibrosis and hepatic perfusion pressure. VCTE-based controlled attenuation parameter (CAP) is a noninvasive marker for hepatic steatosis (HS).
Aims:
To investigate the diagnostic performance of CAP in patients with advanced chronic liver disease (ACLD)/portal hypertension (PHT: hepatic venous pressure gradient (HVPG) ≥ 6 mmHg).
Methods:
Eighty-eight patients with LS ≥ 10 kPa and/or HVPG ≥ 6 mmHg who underwent simultaneous liver biopsy, CAP, and HVPG measurement were included. HS was histologically graded according to the modified Brunt classification.
Results:
Patient characteristics: Mean MELD:11 (standard derivation [SD] ± 4), median HVPG:16 (interquartile range [IQR]10-19) mmHg, median LS:27.4 (IQR 16.2-48.9) kPa, and mean CAP:221 (SD ± 75) dB/m. According to histology, 47 (53.4%) patients had no HS (S0), 28 (31.8%) had S1, 11 (12.5%) had S2, and 2 (2.3%) had S3. The area under the receiver operating characteristic curve (AUROC) of CAP for diagnosing any HS (S0 vs. ≥ S1) was 0.692 (95% confidence interval [95% CI] 0.582-0.802) in the overall cohort, 0.830 (95% CI 0.637-1.0) in patients with HVPG < 10 mmHg, and 0.629 (95% CI 0.497-0.761) in patients with clinically significant portal hypertension (CSPH; HVPG ≥ 10 mmHg; n = 69). Using the established cutoff for any HS (248 dB/m), the sensitivity/specificity of CAP was only 48.8%/76.6%, respectively. In contrast, the AUROC and sensitivity/specificity (cutoff 268 dB/m) for diagnosing HS ≥ S2 were 0.842 (95% CI 0.747-0.936) and 84.6%/81.3%, respectively. CAP correlated with the percentage of steatotic hepatocytes (Spearman's ρ = 0.402; p ≤ 0.001) and showed a weak correlation with liver stiffness (ρ = 0.225; p = 0.035).
Conclusions:
The diagnostic performance of CAP for any HS seems to be limited in patients with ACLD, if CSPH is present.
More Related Videos
Related Concept Videos
 01:26
Diseases of the Liver and Gallbladder
Cirrhosis is characterized by the scarring of hepatic lobules in the liver, which are replaced by fibrous tissue, affecting the liver's normal functioning. NAFLD, on the other hand, is caused by an excessive build-up of fat in the liver, not...
 02:42
Transcription Attenuation in Prokaryotes
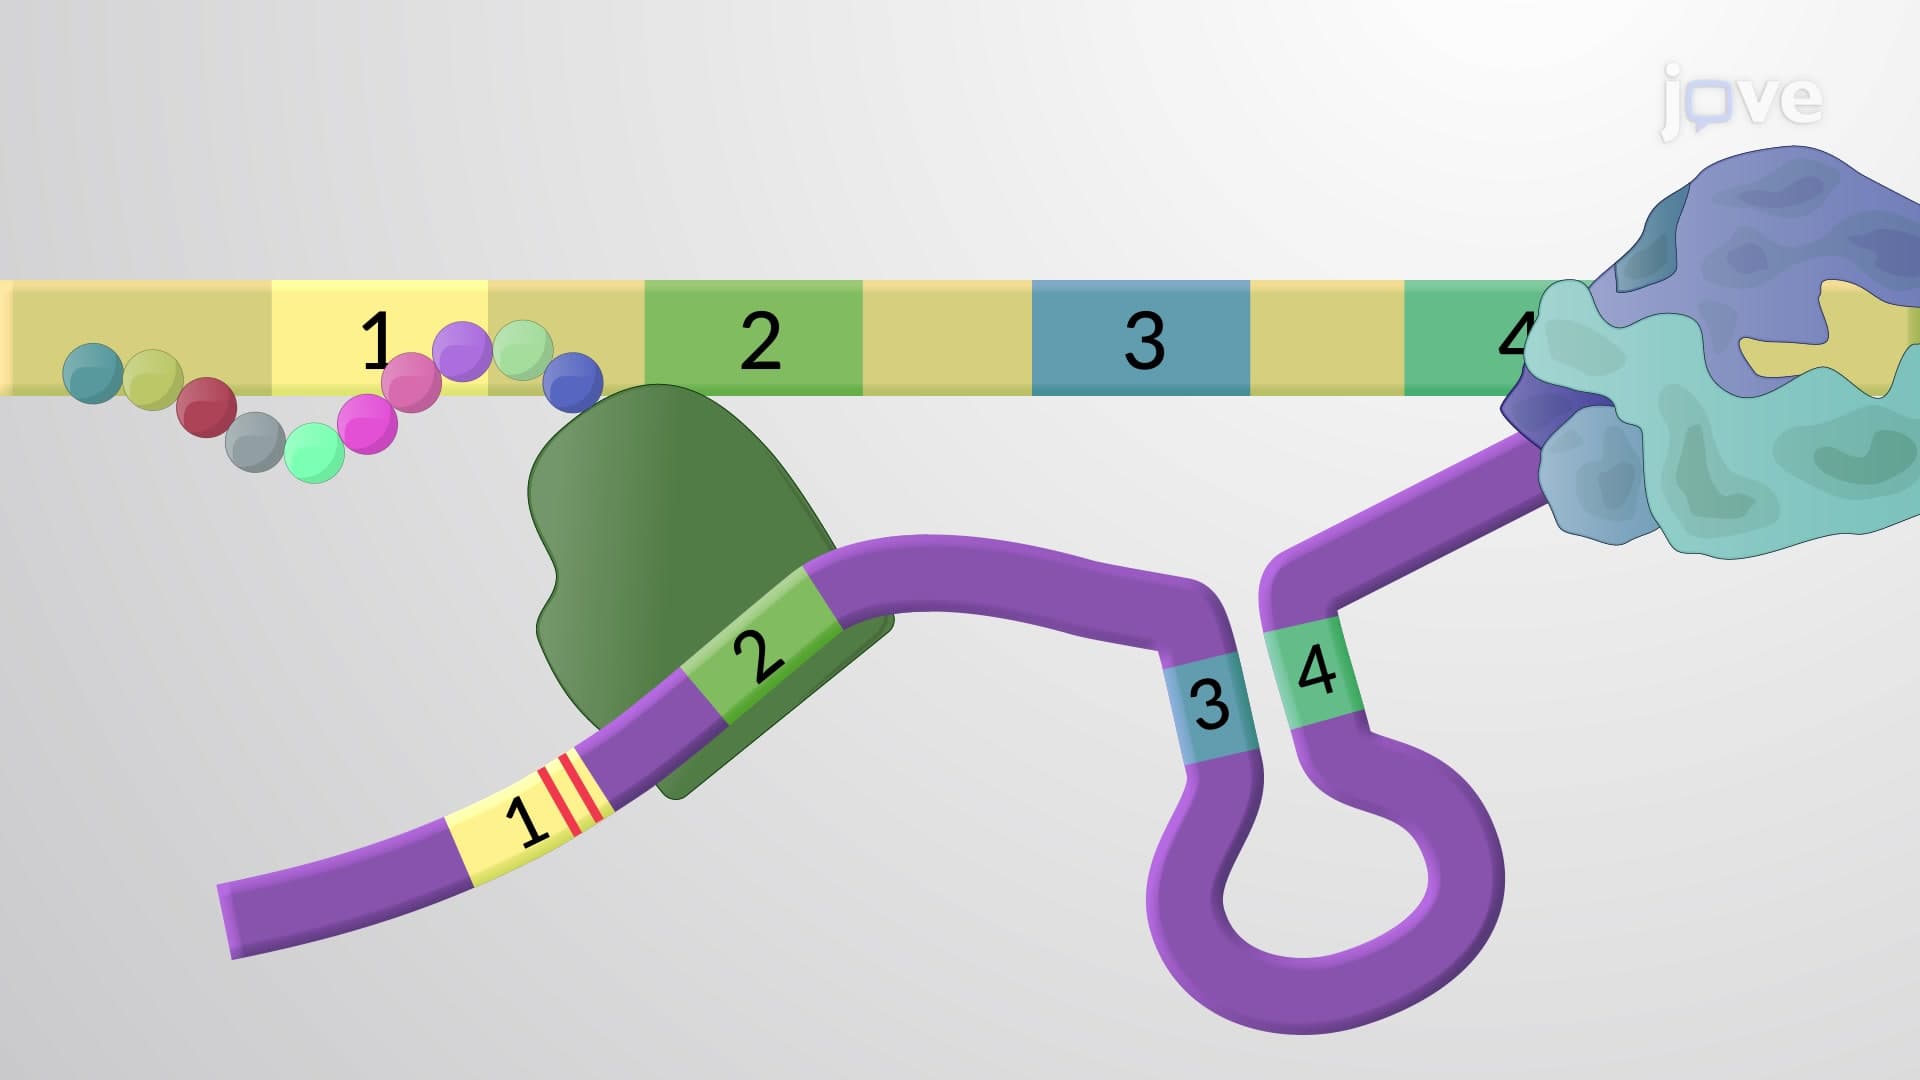
There are several different mechanisms used to attenuate transcription. In ribosome mediated...
 01:22
Chronic Obstructive Pulmonary Disease
Smoking is a primary risk factor for COPD, with over 80% of patients having a history of it. Patients typically experience progressive dyspnea or labored breathing, frequent coughing, and recurrent pulmonary infections. Many eventually succumb to respiratory failure, characterized by...
 01:25
Chronic Kidney Disease I: Introduction
 01:20
Chronic Obstructive Pulmonary Disease-I: Introduction
 01:29
Chronic Obstructive Pulmonary Disease-V: Management
Smoking Cessation