Related Experiment Video
Updated: Jan 23, 2026
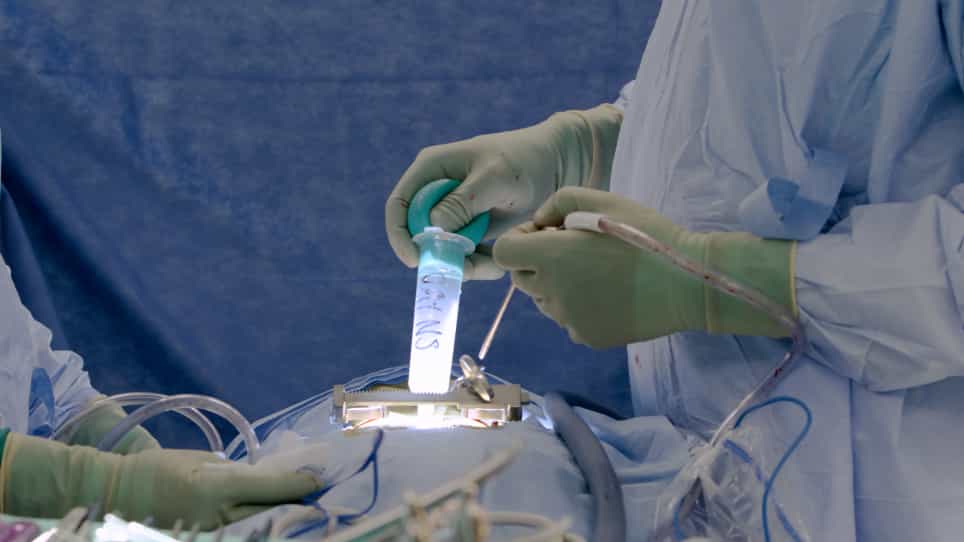

Intraoperative Ultrasound in Spinal Surgery
Published on: August 17, 2022
Spinal subependymoma surgery: do no harm. Little may be more!
Hamzah A Soleiman1, James Ironside2, Susan Kealey3
1Department of Clinical Neurosciences-Neurosurgery, Lothian University Hospitals NHS trust, Edinburgh, UK. h.a.soleiman@gmail.com.

Objective:
Outline the reported diagnostic and operative findings, and evaluate the surgical treatment outcome to clarify the best available recommendations.
Methods:
Ovid Medline, Embase and PubMed central databases were searched from inception until January 2019 using the terms (subependymoma and (spinal or cervical or thoracic)). The articles were reviewed for reported spinal subependymoma cases perioperative management and treatment outcomes.
Results:
A total of 49 papers provided data on 105 cases. 47 cases were reported in the last 5 years. The reported cases were two medullary-cervical, 35 cervical, 32 cervicothoracic, 21 thoracic, 12 thoracolumbar and three lumbar. Spinal subependymomas typically arise from within the central spinal canal, giving the appearance of an intramedullary mass, usually eccentric to one side. Symptoms at presentation ranged between 1 month to 17 years, (mean 3.5 years, median 2 years) and were over 3 years in 36, and over 8 years in 12 cases. Sensory symptoms are the most frequent 75(80%), followed by weakness in 60(64%), pain in 45(48%) and sphincter disturbance in 24(25%). Postoperative neurological function was reported in 78 cases, and worsening was reported in 40 cases (51%), of which, 29 (72%) had complete resection, 6 (15%) had subtotal resection and 5 (12%) had partial resection. Neurological status remained the same in 24 (30%) and improved in 14 (18%).
Conclusion:
The reviewed cases report a rate of 65% total resection of which 57% had worsened function after surgery. There were no reports of malignant transformation; therefore, long-term survival is expected, and surgical caution should be exercised where there is minimal symptom progression.
More Related Videos
 03:47
A Retrospective Study on Endoscopic Surgery for the Treatment of Paravertebral Abscess in Spinal Tuberculosis Patients
Published on: October 25, 2024
 11:38
High Content Screening Analysis to Evaluate the Toxicological Effects of Harmful and Potentially Harmful Constituents HPHC
Published on: May 10, 2016
Related Concept Videos
 01:26
Spinal Cord
 01:54
The Spinal Cord
 01:10
Spinal Cord: Information Processing
Sensory Information Processing
Sensory information processing begins at the sensory receptors located in the skin and other tissues, which detect somatic sensory stimuli such as touch, temperature, or pain. These receptors function as catalysts, initiating...
 01:21
Spinal Nerves: Plexus II
The Lumbar Plexus
The lumbar plexus is situated within the lumbar region of the back and is primarily formed by the first four lumbar spinal nerves (L1 to L4). This plexus extends its branches into several nerves, including the...
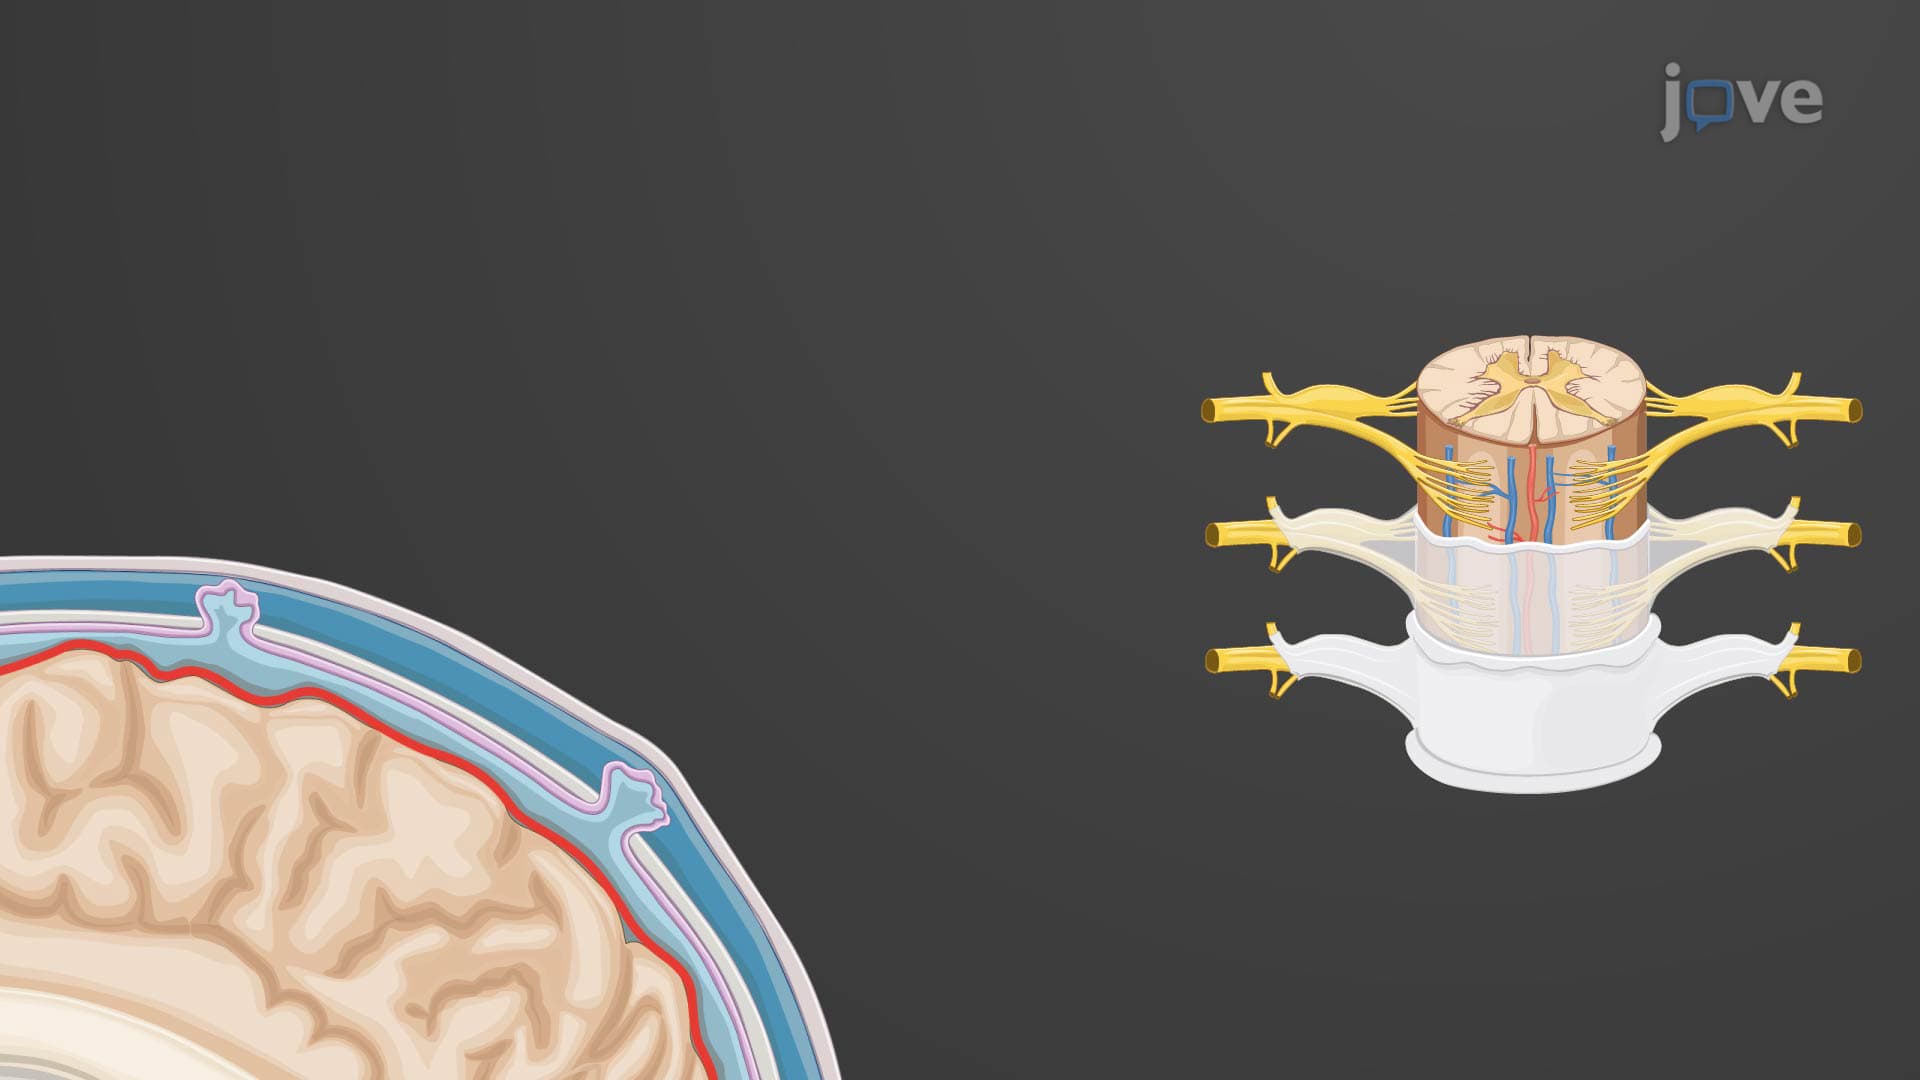 01:19
Cranial and Spinal Meninges
Cranial Meninges
These meningeal layers cover the cranium. The dura mater is the outermost layer of cranial meninges. It is a thick and durable membrane of dense...
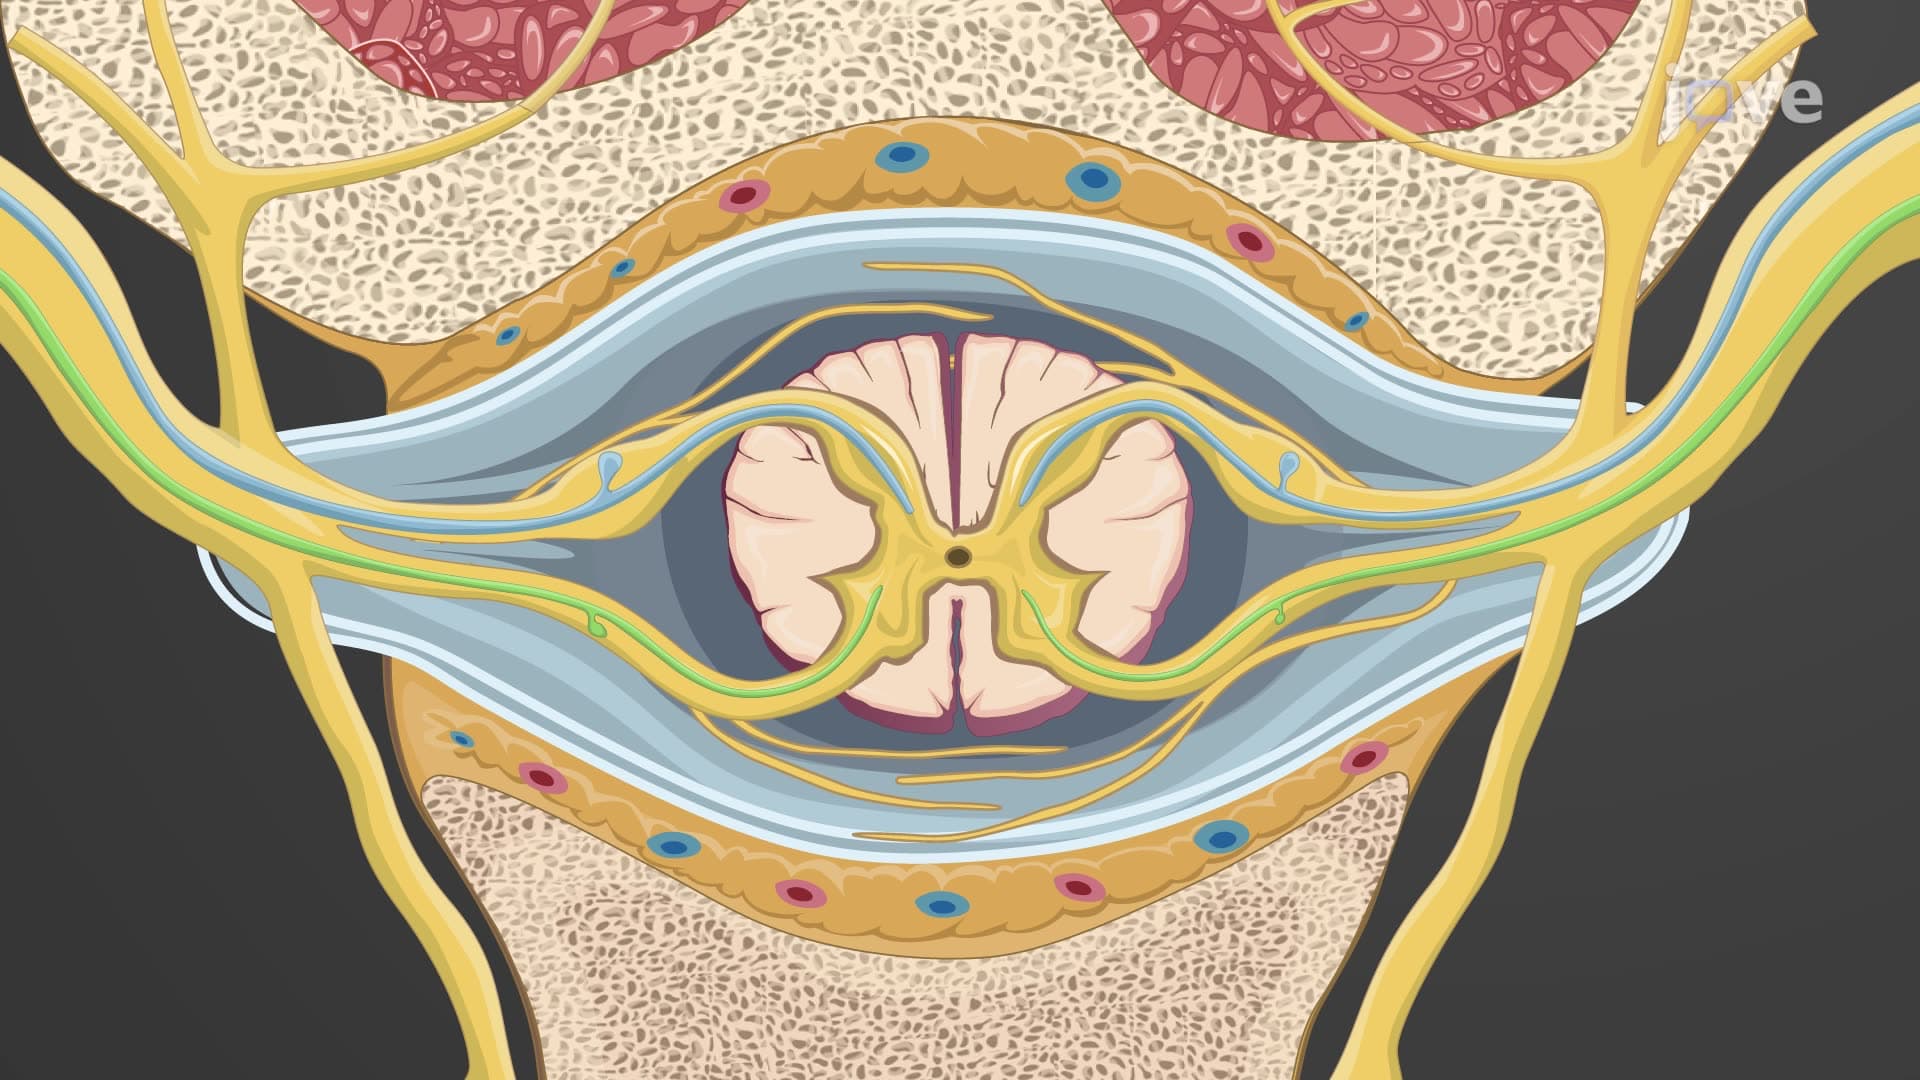 01:23
Spinal Nerves: Anatomy
There are 31 bilateral pairs of spinal nerves, each emerging from the spinal cord through the intervertebral foramina—openings between adjacent vertebrae. These nerves are...