Related Experiment Video
Updated: Jan 23, 2026

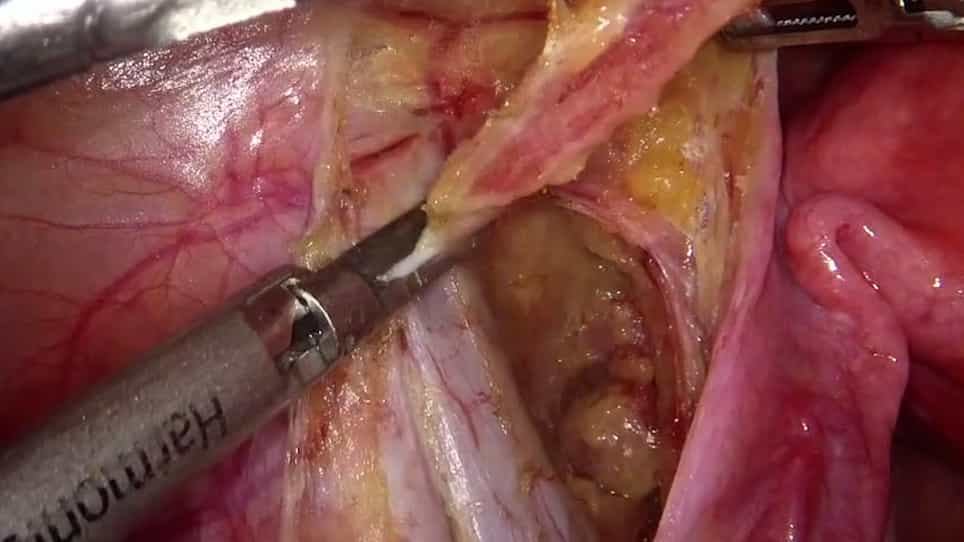
Robot-assisted Total Mesorectal Excision and Lateral Pelvic Lymph Node Dissection for Locally Advanced Middle-low Rectal Cancer
Published on: February 12, 2022
The adequacy of lymph node clearance in colon cancer surgery performed in a non-specialist centre; implications for
Patrick Higgins1, Tamas Nemeth2, Fadel Bennani2
1Department of Surgery, Mayo University Hospital, Saolta Health Care Group, Castlebar, Ireland. patrickphiliphiggins@gmail.com.

Background:
Despite recent medical advances, surgery remains the mainstay treatment in colon cancer. It is well established that better patient outcomes are achieved when complex surgery including pancreatic, oesophageal and rectal surgeries are carried out in high-volume centres. However, it is unclear as to whether or not colon cancer patients receive the same benefit. Lymph node adequacy is a key performance indicator of successful oncological colonic resection which impacts on patient outcome.
Aim:
To assess the adequacy of lymph node clearance during colonic resection performed with curative intent in a non-specialist centre post introduction of the National Cancer Strategy.
Methods:
Retrospective analysis was performed of a prospectively maintained database examining the lymph node clearance of all oncological resections for colon cancer over a 7-year period (Nov 2010-Dec 2017) at a satellite unit with links to a regional specialist centre. Primary outcome measured was the number of lymph nodes retrieved. Secondary outcomes included resection margins, 30-day complication rate and survival at 1 year. Statistical analysis was performed using SPSS Statistics for Windows, version 24.0 (IBM Corp, Armonk, N.Y., USA).
Results:
One hundred sixty-seven patients were included. Mean age was 71.0 ± 11.6 years. Majority were male (n = 90, 53.6%). The majority of resections was right sided (n = 112.66.7%) with 78.6% of all resections being undertaken electively. All margins were free of tumour. The average lymph node count was 19.93 ± 8.63 (4.62) with only 17 (10.2%) of specimens containing < 12 nodes. The anastomotic leak rate was 3.3%. There was no association between surgeon or pathologist volume, nor emergent status and achieving oncological lymph node count (p = 0.14, 0.29, 0.97). 90.5% of patients were alive at 1 year.
Conclusions:
This study demonstrates that colonic cancer surgery can be safely performed in a non- specialist centre with technical outcomes comparable to nationally reported figures.

Related Concept Videos
 01:23
Detailed Structure and Function of Lymph Nodes
From a histological perspective, lymph nodes can be split into two main areas: the superficial cortex and the deep medulla. The outer cortex is populated by dendritic cells, macrophages, and B lymphocytes, which are densely packed into follicles. When these B-lymphocytes are presented...
 01:09
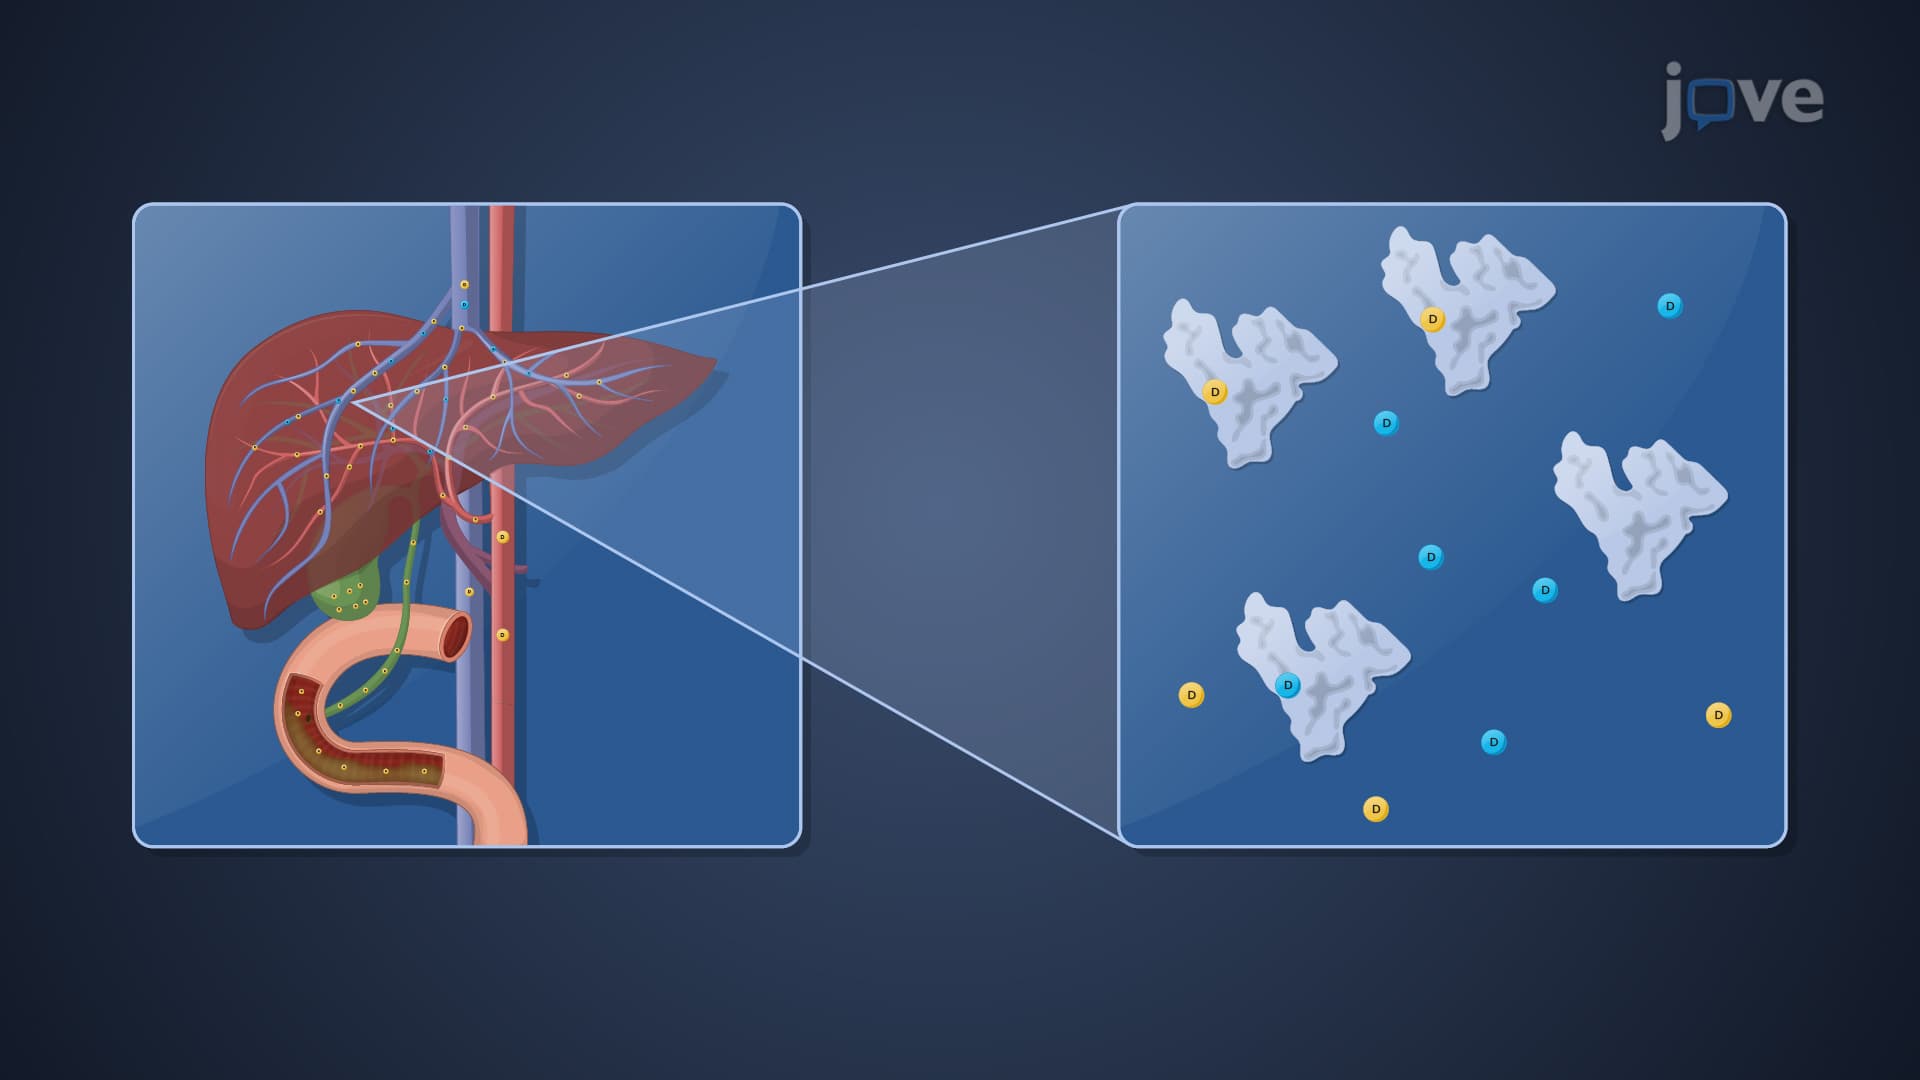
Hepatic Drug Clearance: Restrictive and Nonrestrictive Clearance
Most drugs undergo restrictive clearance, which is proportional to the...
 02:22
The Colonization of Land
 01:23
Renal Clearance
Renal clearance refers to the volume of plasma cleared of a specific substance, such as creatinine, per unit of time. To measure clearance, urine samples are collected over a 24-hour period during each bladder voiding, followed by a single blood sample at the...
 01:06
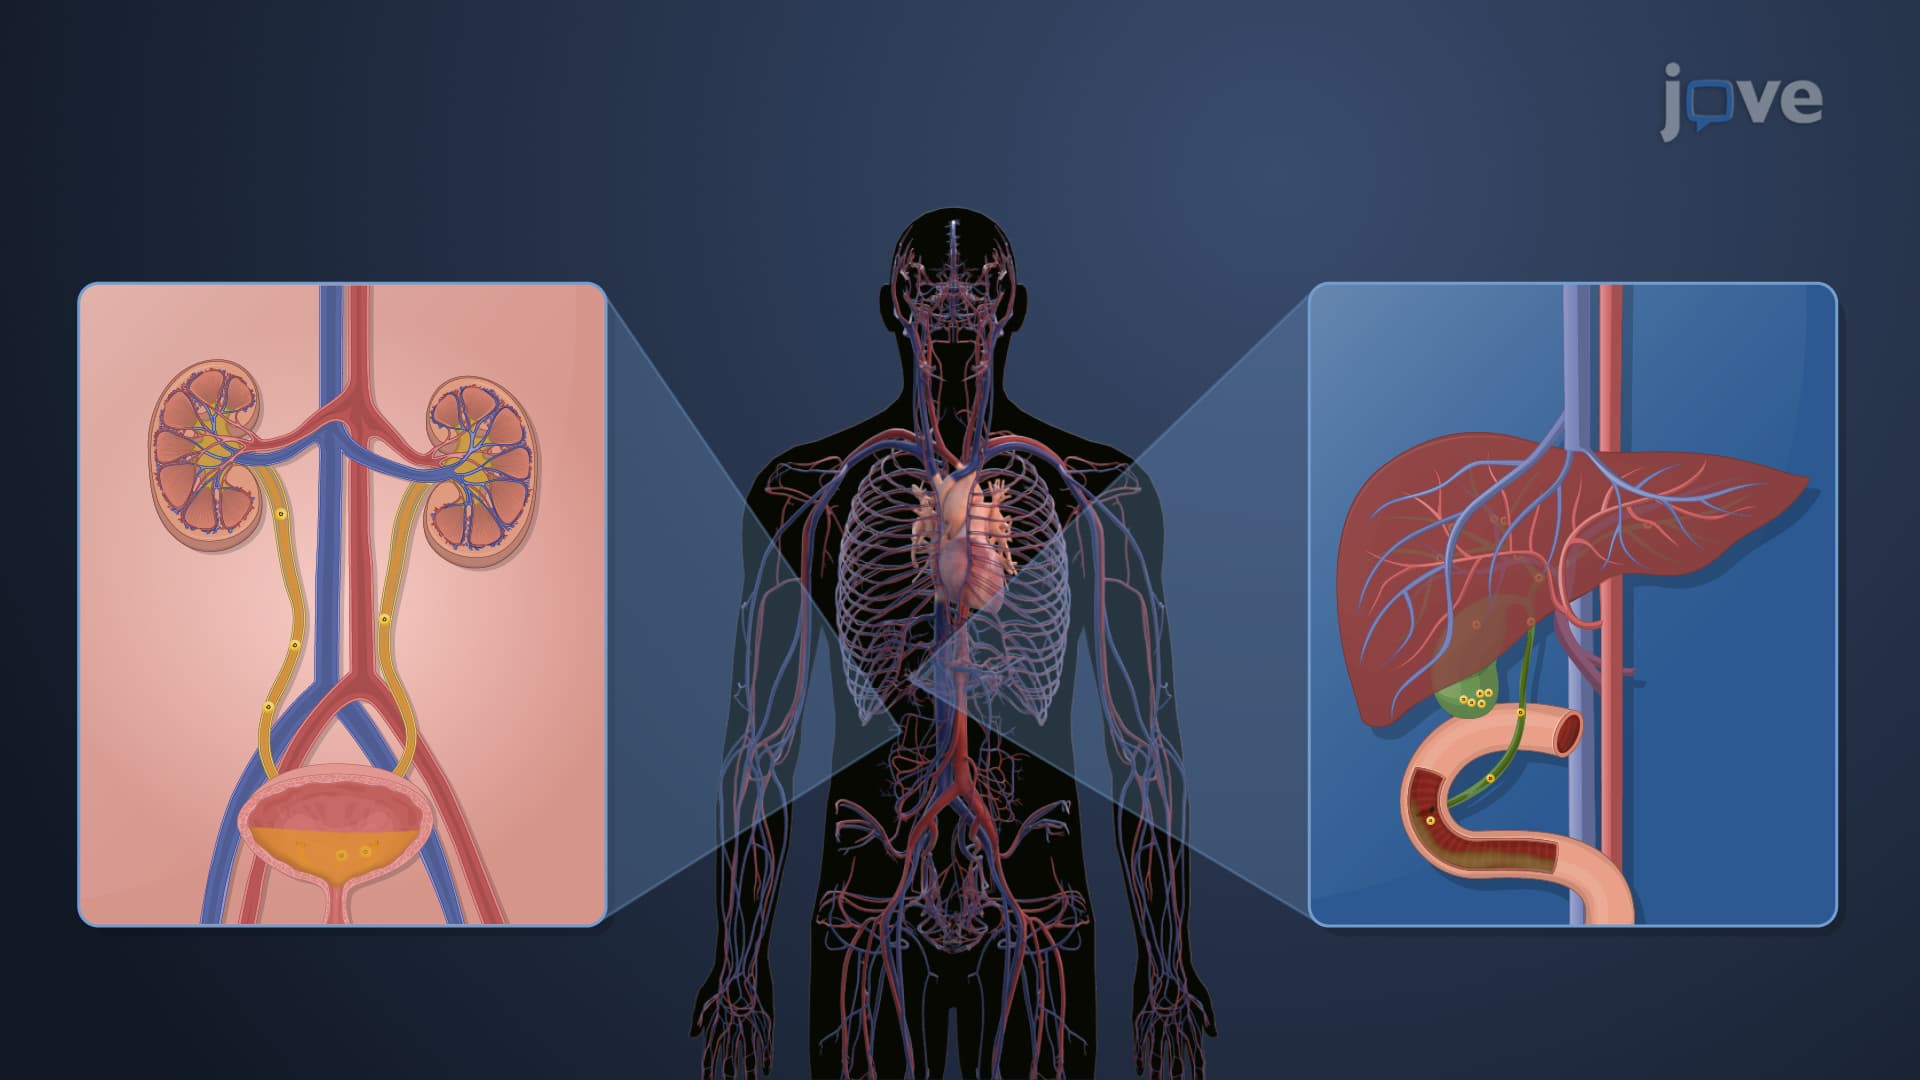
Drug Clearance: Overview
Drug clearance is not limited to renal excretion but encompasses all organs involved in drug elimination, including...
 01:17
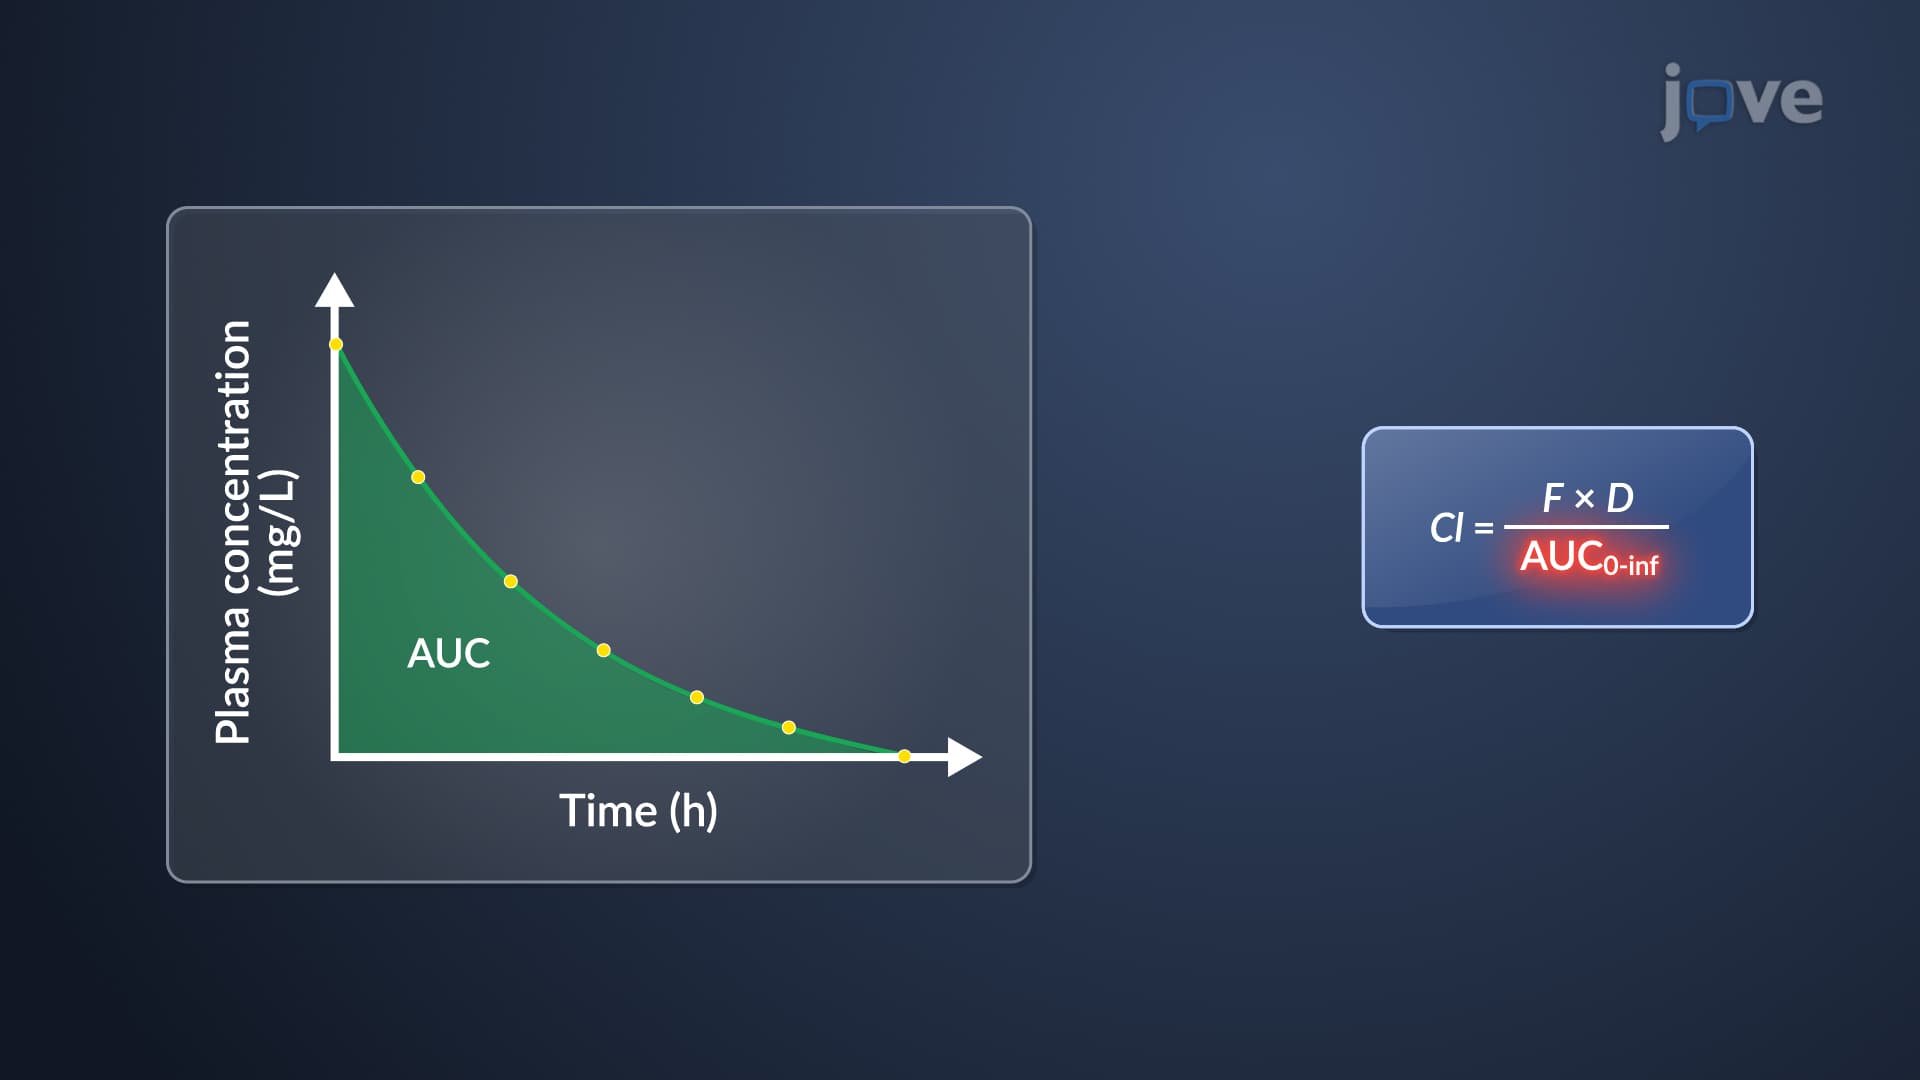
Clearance Models: Noncompartmental Models
The noncompartmental approach capitalizes on extensive sampling data, correlating the volume of distribution to systemic exposure and the administered dosage. This method enables...