Related Experiment Video
Updated: Jan 23, 2026
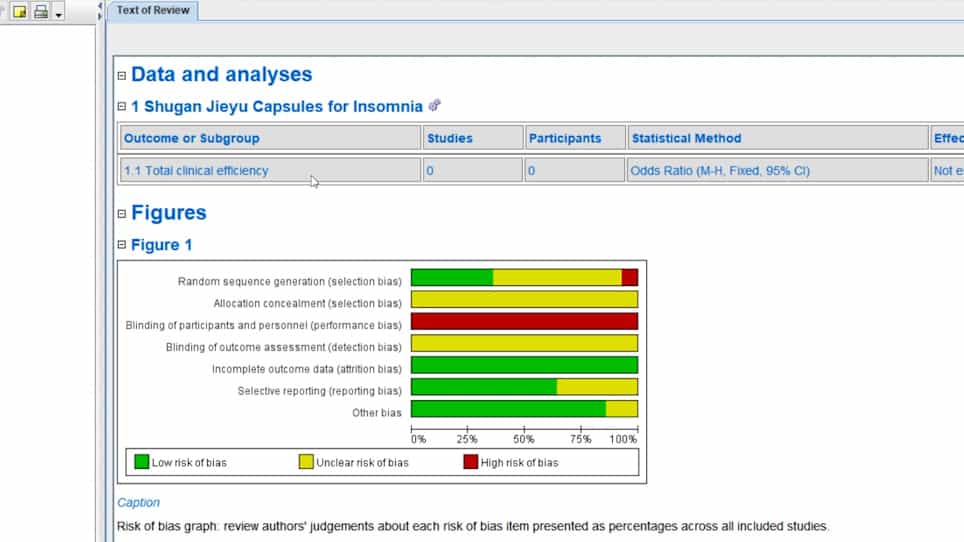
Meta-Analysis of the Effectiveness and Safety of Shugan Jieyu Capsules for the Treatment of Insomnia
Published on: February 17, 2023
A systematic review and meta-analysis of revascularization outcomes of infrainguinal chronic limb-threatening
Jehad Almasri1, Jayanth Adusumalli2, Noor Asi1
1Evidence-Based Practice Research Program, Mayo Clinic, Rochester, Minn; Robert D. and Patricia E. Kern Center for the Science of Health Care Delivery, Mayo Clinic, Rochester, Minn.

Insights
Optimal revascularization for chronic limb-threatening ischemia (CLTI) lacks high-quality evidence. Saphenous vein bypass offers superior patency, while prosthetic bypass is inferior for below-knee targets. Endovascular options show comparable results for focal disease.
Area of Science:
- Vascular Surgery
- Interventional Cardiology
- Health Services Research
Background:
- Optimal revascularization strategy for infrainguinal chronic limb-threatening ischemia (CLTI) is debated.
- Comparative trials are scarce, leading to reliance on low-quality evidence for clinical decisions.
Purpose of the Study:
- To systematically review and meta-analyze patient-relevant outcomes of infrainguinal revascularization procedures for CLTI.
- To compare the effectiveness of different revascularization modalities.
Main Methods:
- Systematic search of multiple databases for prospective studies with ≥1-year follow-up.
- Inclusion of studies evaluating infrainguinal revascularization in adult CLTI patients.
- Random-effects meta-analysis to pool outcomes.
Main Results:
- 44 studies with 8602 patients were included. Periprocedural outcomes were similar across modalities.
- Great saphenous vein grafts showed higher patency rates (1-year: 87%, 2-year: 78%) compared to other interventions.
- Prosthetic bypass had inferior amputation and patency outcomes, especially below the knee. Drug-eluting stents improved infrapopliteal patency versus bare-metal stents.
Conclusions:
- Current evidence for CLTI treatment is limited, especially for endovascular interventions in severe disease.
- Saphenous vein bypass offers the best patency; prosthetic bypass is inferior for below-knee targets.
- Percutaneous transluminal angioplasty and drug-eluting stents are comparable for focal infrapopliteal disease, but evidence for long tibial lesions is lacking.
Background:
The optimal strategy for revascularization in infrainguinal chronic limb-threatening ischemia (CLTI) remains debatable. Comparative trials are scarce, and daily decisions are often made using anecdotal or low-quality evidence.
Methods:
We searched multiple databases through May 7, 2017, for prospective studies with at least 1-year follow-up that evaluated patient-relevant outcomes of infrainguinal revascularization procedures in adults with CLTI. Independent pairs of reviewers selected articles and extracted data. Random-effects meta-analysis was used to pool outcomes across studies.
Results:
We included 44 studies that enrolled 8602 patients. Periprocedural outcomes (mortality, amputation, major adverse cardiac events) were similar across treatment modalities. Overall, patients with infrapopliteal disease had higher patency rates of great saphenous vein graft at 1 and 2 years (primary: 87%, 78%; secondary: 94%, 87%, respectively) compared with all other interventions. Prosthetic bypass outcomes were notably inferior to vein bypass in terms of amputation and patency outcomes, especially for below knee targets at 2 years and beyond. Drug-eluting stents demonstrated improved patency over bare-metal stents in infrapopliteal arteries (primary patency: 73% vs 50% at 1 year), and was at least comparable to balloon angioplasty (66% primary patency). Survival, major amputation, and amputation-free survival at 2 years were broadly similar between endovascular interventions and vein bypass, with prosthetic bypass having higher rates of limb loss. Overall, the included studies were at moderate to high risk of bias and the quality of evidence was low.
Conclusions:
There are major limitations in the current state of evidence guiding treatment decisions in CLTI, particularly for severe anatomic patterns of disease treated via endovascular means. Periprocedural (30-day) mortality, amputation, and major adverse cardiac events are broadly similar across modalities. Patency rates are highest for saphenous vein bypass, whereas both patency and limb salvage are markedly inferior for prosthetic grafting to below the knee targets. Among endovascular interventions, percutaneous transluminal angioplasty and drug-eluting stents appear comparable for focal infrapopliteal disease, although no studies included long segment tibial lesions. Heterogeneity in patient risk, severity of limb threat, and anatomy treated renders direct comparison of outcomes from the current literature challenging. Future studies should incorporate both limb severity and anatomic staging to best guide clinical decision making in CLTI.
Related Concept Videos
 01:10
Review and Preview
Percentiles are a type of fractile that partition data into...
 01:13
Review and Preview
 01:20
Random and Systematic Errors
 02:24
Predicting Reaction Outcomes
 01:09
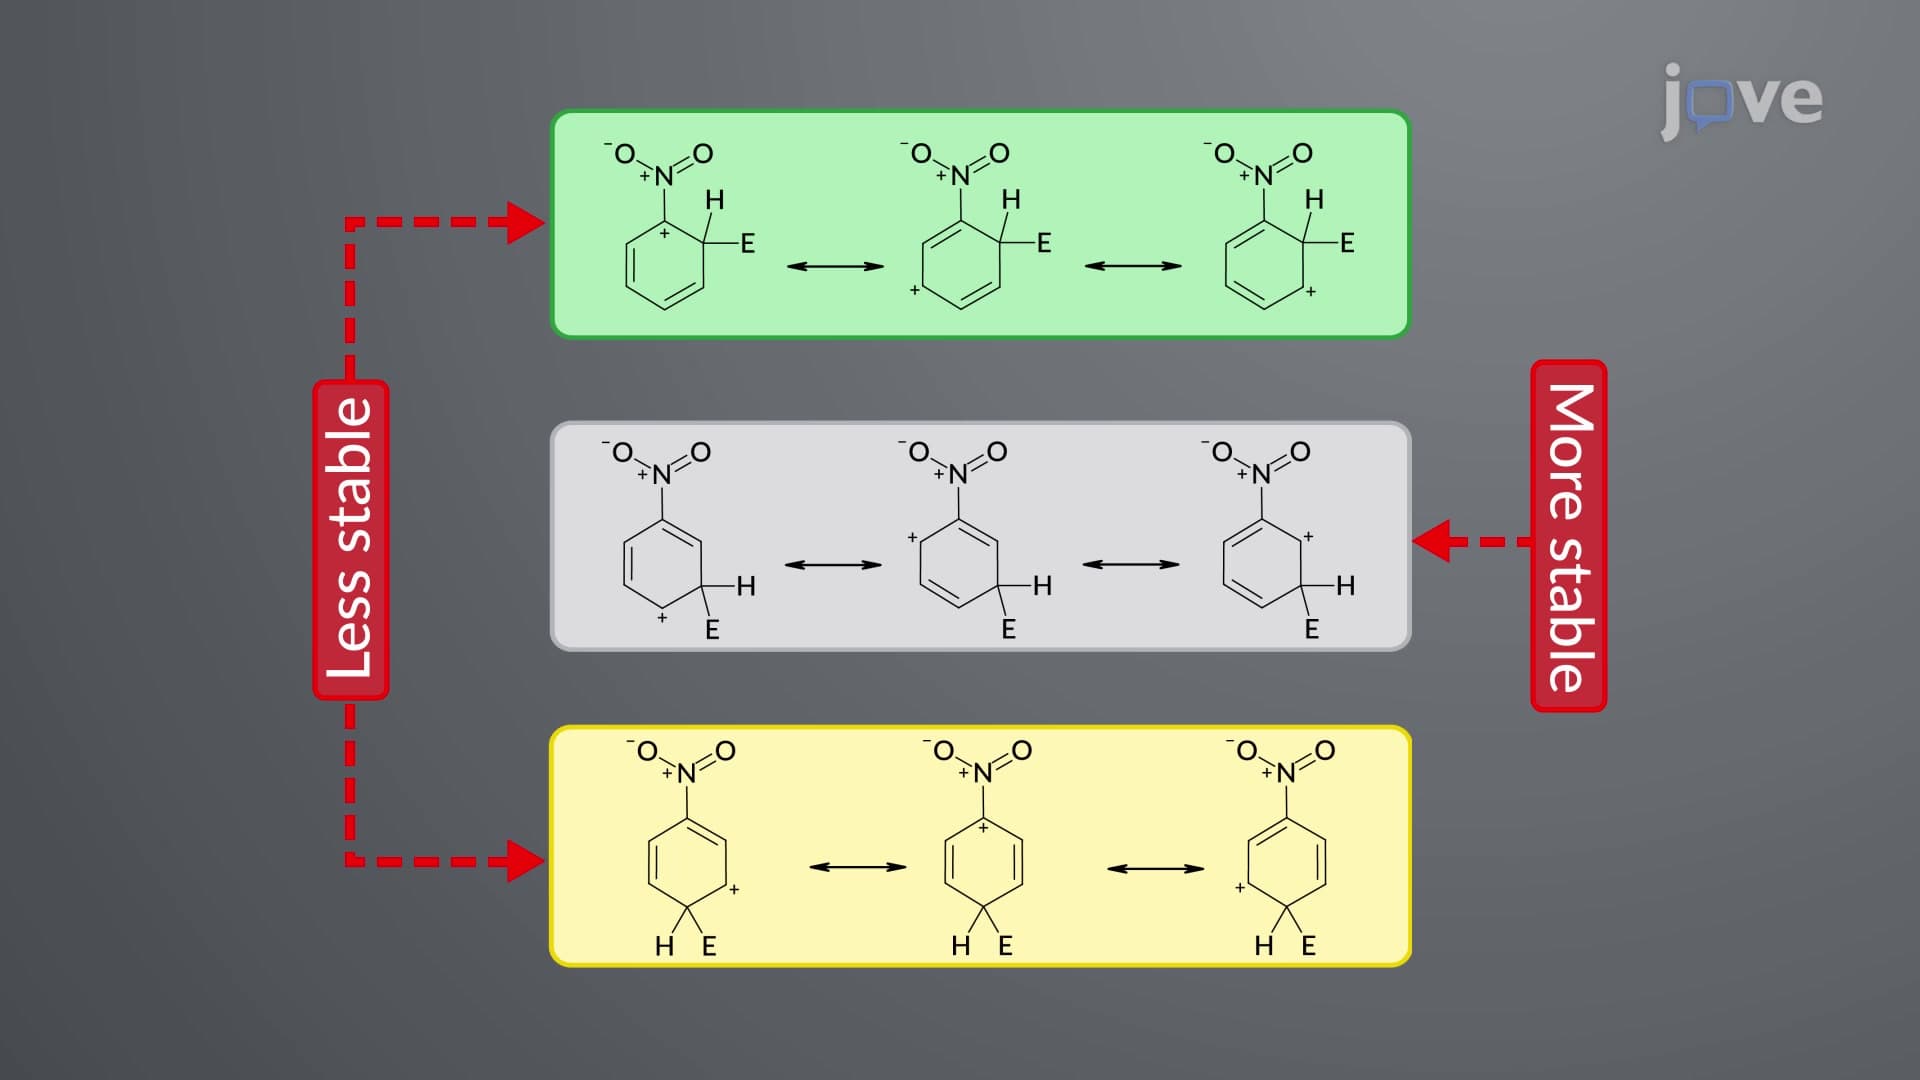
Directing Effect of Substituents: meta-Directing Groups
 01:17
Systematic Sampling Method
Systematic sampling is one of the simplest methods...