Related Experiment Video
Updated: Jan 23, 2026
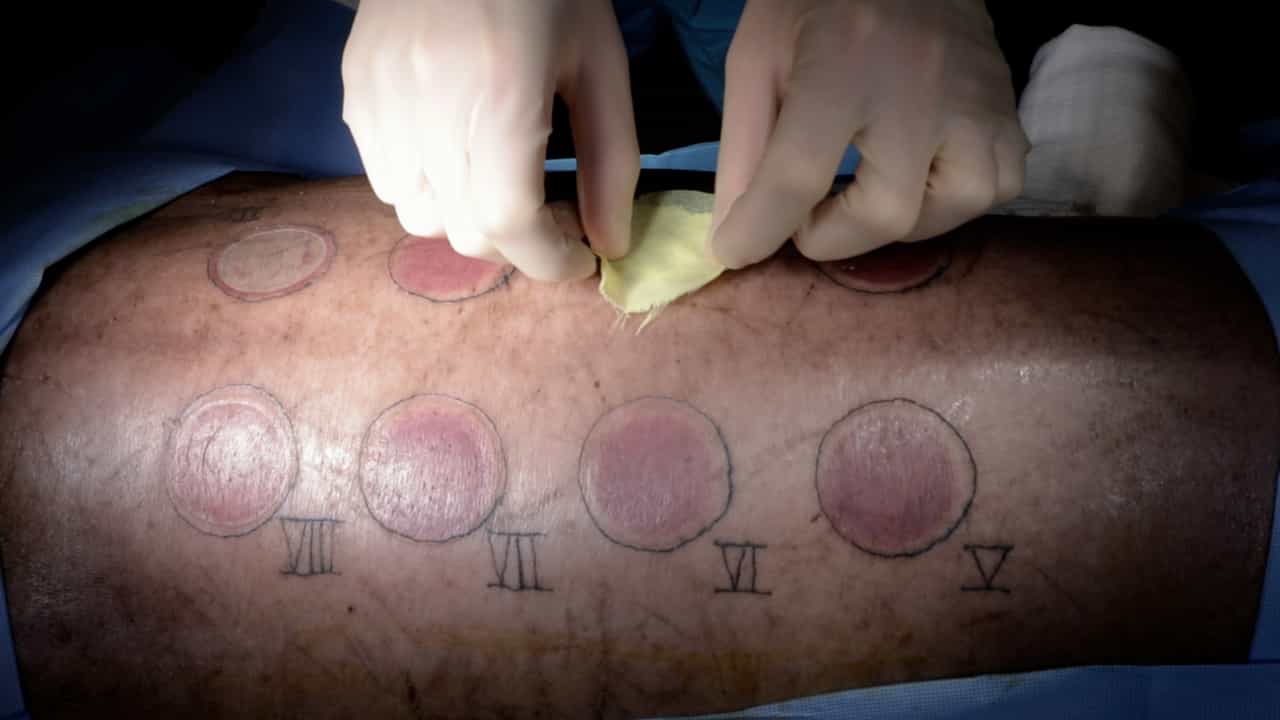

Author Spotlight: A Multi-Depth Porcine Model for Comprehensive Study of Burn Injuries and Healing Processes
Published on: February 23, 2024
Relationship Between Burn Wound Location and Outcomes in Severely Burned Patients: More Than Meets the Size
Nehemiah T Liu1, Julie A Rizzo1, Sarah K Shingleton1
1U.S. Army Institute of Surgical Research, JBSA Fort Sam Houston, Texas.

Abstract:
We hypothesized that burn location plays an important role in wound healing, mortality, and other outcomes and conducted the following study to test this multifold hypothesis. We conducted a study to retrospectively look at patients with burns ≥10% TBSA. Demographics, TBSA, partial/full thickness burns (PT/FT) in various wound locations, fluids, inhalation injury, mortality, ICU duration, and hospital duration were considered. Initial wound healing rates (%/d) were also calculated as a slope from the time of the first mapping of open wound size to the time of the third mapping of open wound size. Multivariate logistic regression and operating curves were used to measure mortality prediction performance. All values were expressed as median [interquartile range]. The mortality rate for 318 patients was 17% (54/318). In general, patients were 43 years [29, 58 years] old and had a TBSA of 25% [17, 39%], PT of 16% [10, 25%], and FT of 4% [0, 15%]. Between patients who lived and did not, age, TBSA, FT, 24-hour fluid, and ICU duration were statistically different (P < .001). Furthermore, there were statistically significant differences in FT head (0% [0, 0%] vs 0% [0, 1%], P = .048); FT anterior torso (0% [0, 1%] vs 1% [0, 4%], P < .001); FT posterior torso (0% [0, 0%] vs 0% [0, 4%], P < 0.001); FT upper extremities (0% [0, 3%] vs 2% [0, 11%], P < .001); FT lower extremities (0% [0, 2%] vs 6% [0, 17%], P < .001); and FT genitalia (0% [0, 0%] vs 0% [0, 2%], P < .001). Age, presence of inhalation injury, PT/FT upper extremities, and FT lower extremities were independent mortality predictors and per unit increases of these variables were associated with an increased risk for mortality (P < .05): odds ratio of 1.09 (95% confidence interval [CI] = 1.61-1.13; P < .001) for mean age; 2.69 (95% CI = 1.04-6.93; P = .041) for inhalation injury; 1.14 (95% CI = 1.01-1.27; P = .031) for mean PT upper extremities; 1.26 (95% CI = 1.11-1.42; P < .001) for mean FT upper extremities; and 1.07 (95% CI = 1.01-1.12; P = .012) for mean FT lower extremities. Prediction of mortality was better using specific wound locations (area under the curve [AUC], AUC of 0.896) rather than using TBSA and FT (AUC of 0.873). Graphs revealed that initial healing rates were statistically lower and 24-hour fluids and ICU length of stay were statistically higher in patients with FT upper extremities than in patients without FT extremities (P < .001). Burn wound location affects wound healing and helps predict mortality and ICU length of stay and should be incorporated into burn triage strategies to enhance resource allocation or stratify wound care.

Related Concept Videos
 01:22
Burn Injuries
The damage results in the death of skin cells, which can lead to a massive loss of fluid. Dehydration, electrolyte imbalance, and renal and circulatory failure follow, which can be fatal. Burn patients are treated with intravenous fluids to offset...
 02:12
Relationship Formation
 01:22
Cell Size
Surface Area
Cells can take in nutrients and water via diffusion through the plasma membrane itself or through specific channels in the membrane. The area of the membrane surrounding...
 01:28
Ending Relationships
 02:24
Predicting Reaction Outcomes
 01:13
Outcomes of Glycolysis
Cellular respiration can occur aerobically (with oxygen) or anaerobically (without oxygen). In the presence of oxygen, cellular respiration starts with glycolysis and continues with pyruvate...