Related Experiment Video
Updated: Aug 18, 2026
Two Techniques to Create Hypoparathyroid Mice: Parathyroidectomy Using GFP Glands and Diphtheria-Toxin-Mediated Parathyroid Ablation
Published on: March 14, 2017
Medical treatment of primary hyperparathyroidism: effects on parathormone and vitamin D metabolites
J Foldes1, Y Halperin, G Kidroni
1Department of Internal Medicine, Hadassah University Hospital, Mount Scopus, Jerusalem, Israel.

Abstract:
A 63-year-old woman was treated medically for primary hyperparathyroidism because of a recent myocardial infarction. She received propranolol alone or combined with either cimetidine, calcitonin or disodium etidronate (EHDP). The treatment did not affect the elevated serum parathormone or urinary cyclic AMP levels, nor did it correct the elevated serum 1,25(OH)2D and the decreased serum 24,25(OH)2D levels in this patient. Propranolol combined with either cimetidine or with EHDP (600 mg/day) caused a mild decrease in the serum calcium level which, however, remained within the hypercalcemic range. Following surgery all parameters returned to normal. We conclude that the above medical regimens were incapable of correcting the hyperparathyroid condition in this patient.

Related Concept Videos
 01:17
Hormones and Bone Tissue
Hormones That Influence Osteoblasts and/or Maintain the Matrix
Several hormones are necessary for controlling bone growth and maintaining the bone matrix. The pituitary gland secretes growth hormone (GH), which, as its name implies, controls bone growth. This happens in several ways: first, it triggers chondrocyte...
 01:21
Skeleton and Calcium Homeostasis
 00:51
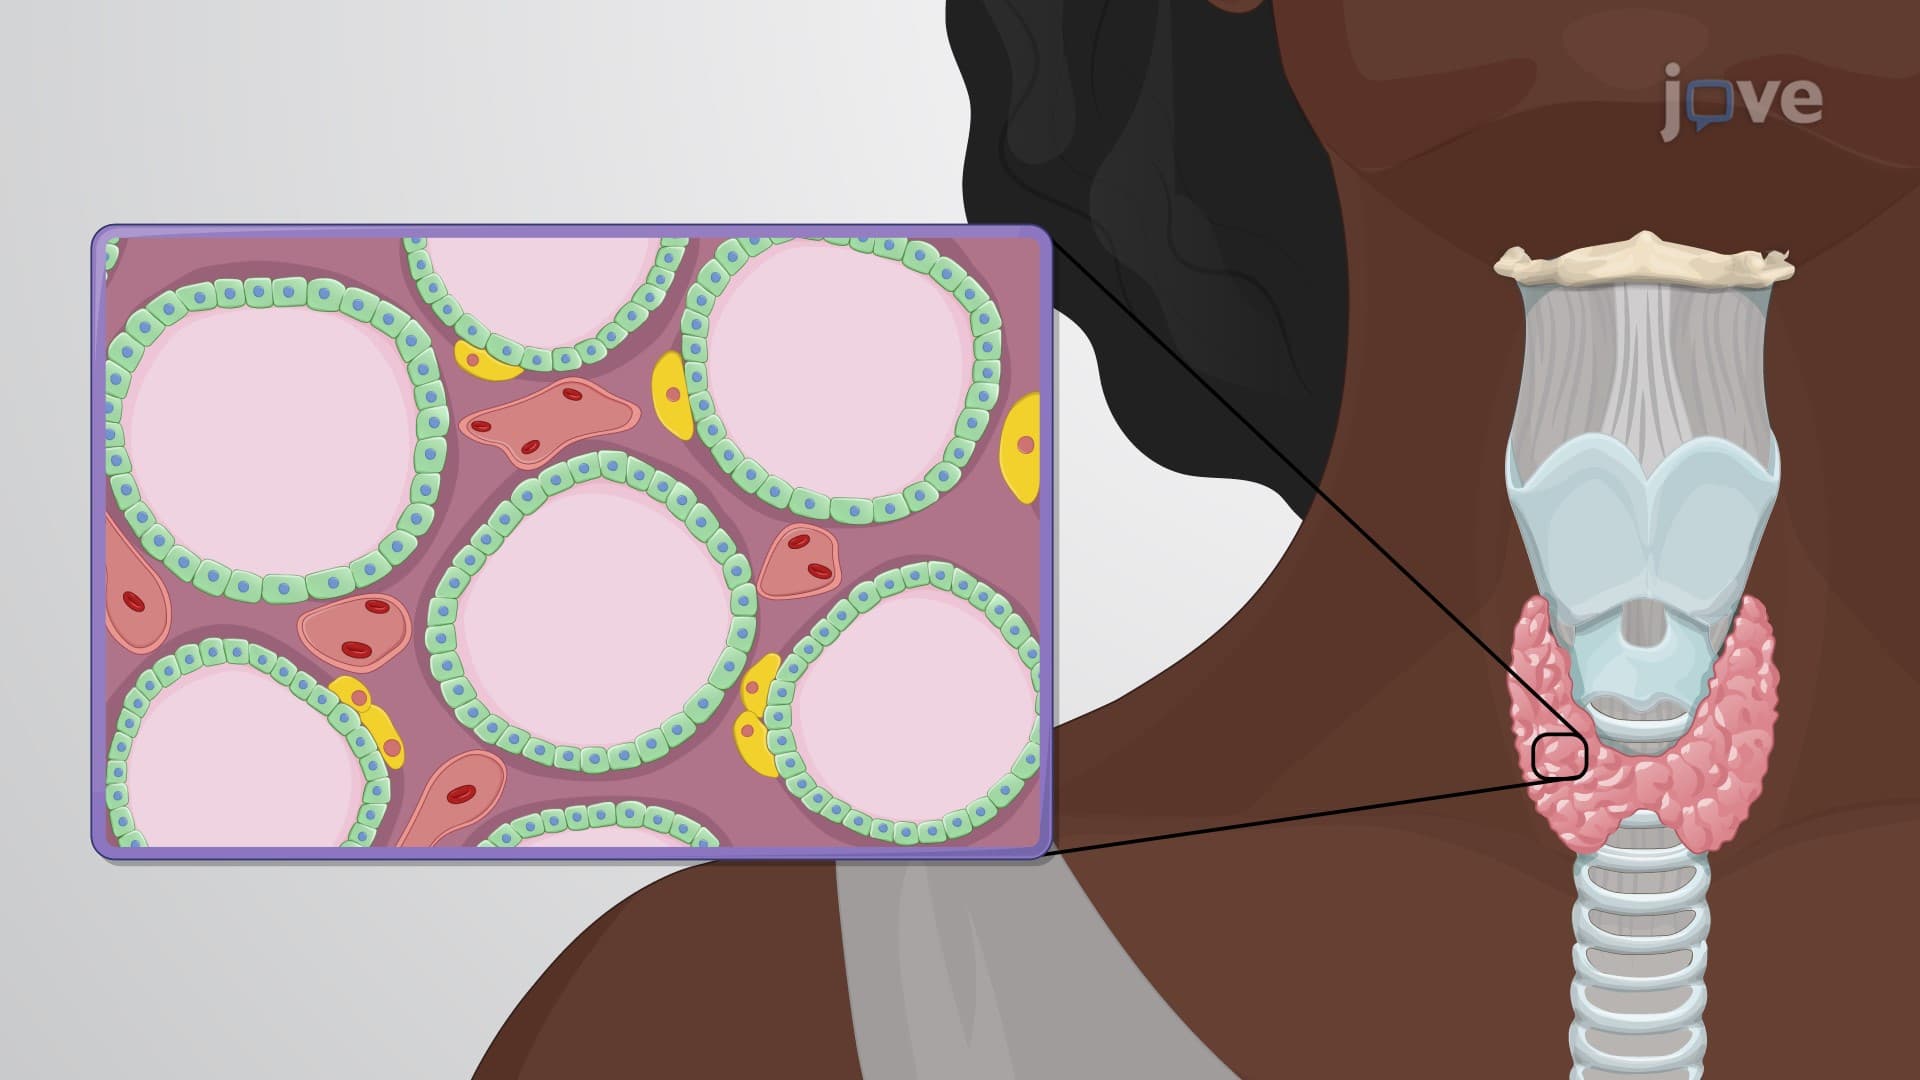
Synthesis and Functions of Calcitonin
The exact mechanisms by which calcitonin operates in calcium homeostasis remain elusive, but its significance is evident in several vital...
 00:59
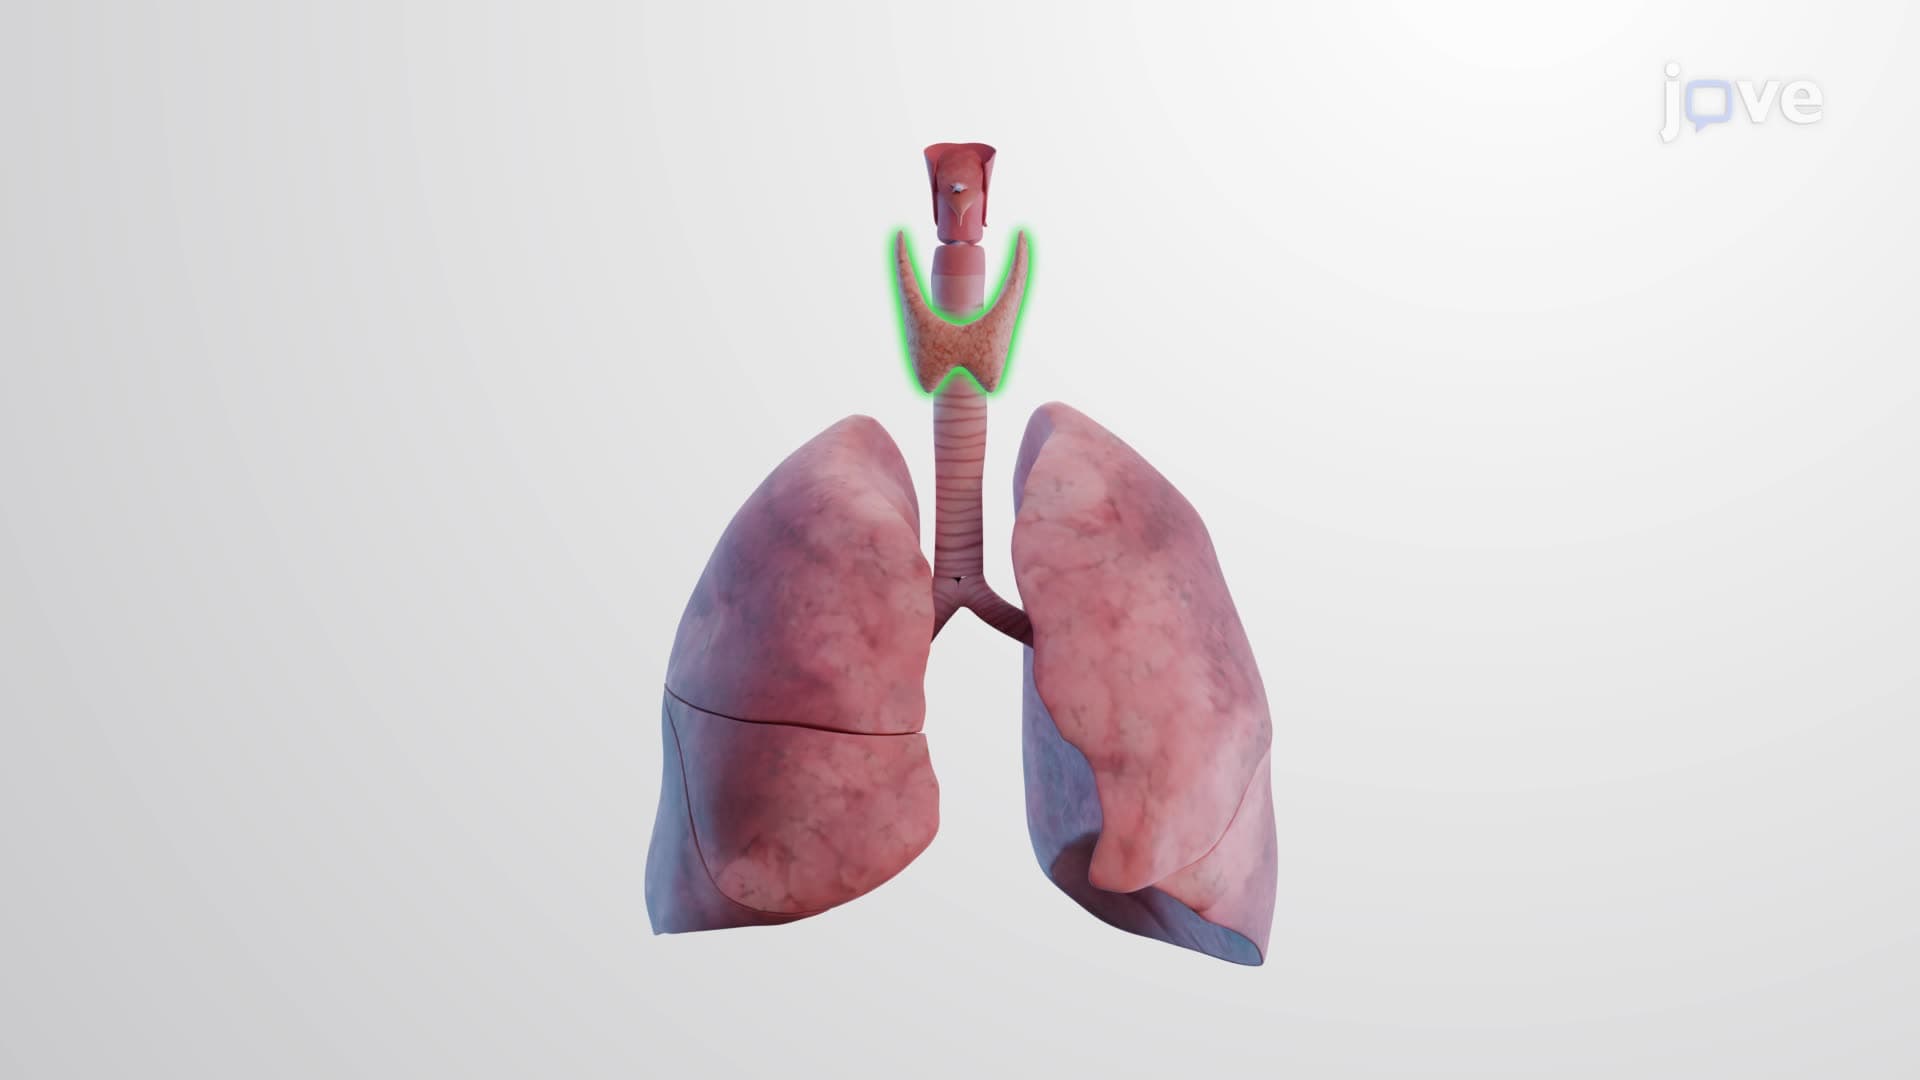
The Parathyroid Glands
Oxyphil cells, whose functions remain elusive, emerge during late puberty, adding a layer of complexity to the parathyroid gland's intricacies. In contrast, principal parathyroid cells undertake a vital role by producing...
 01:27
Hyperthyroidism II: Pathophysiology
 01:23
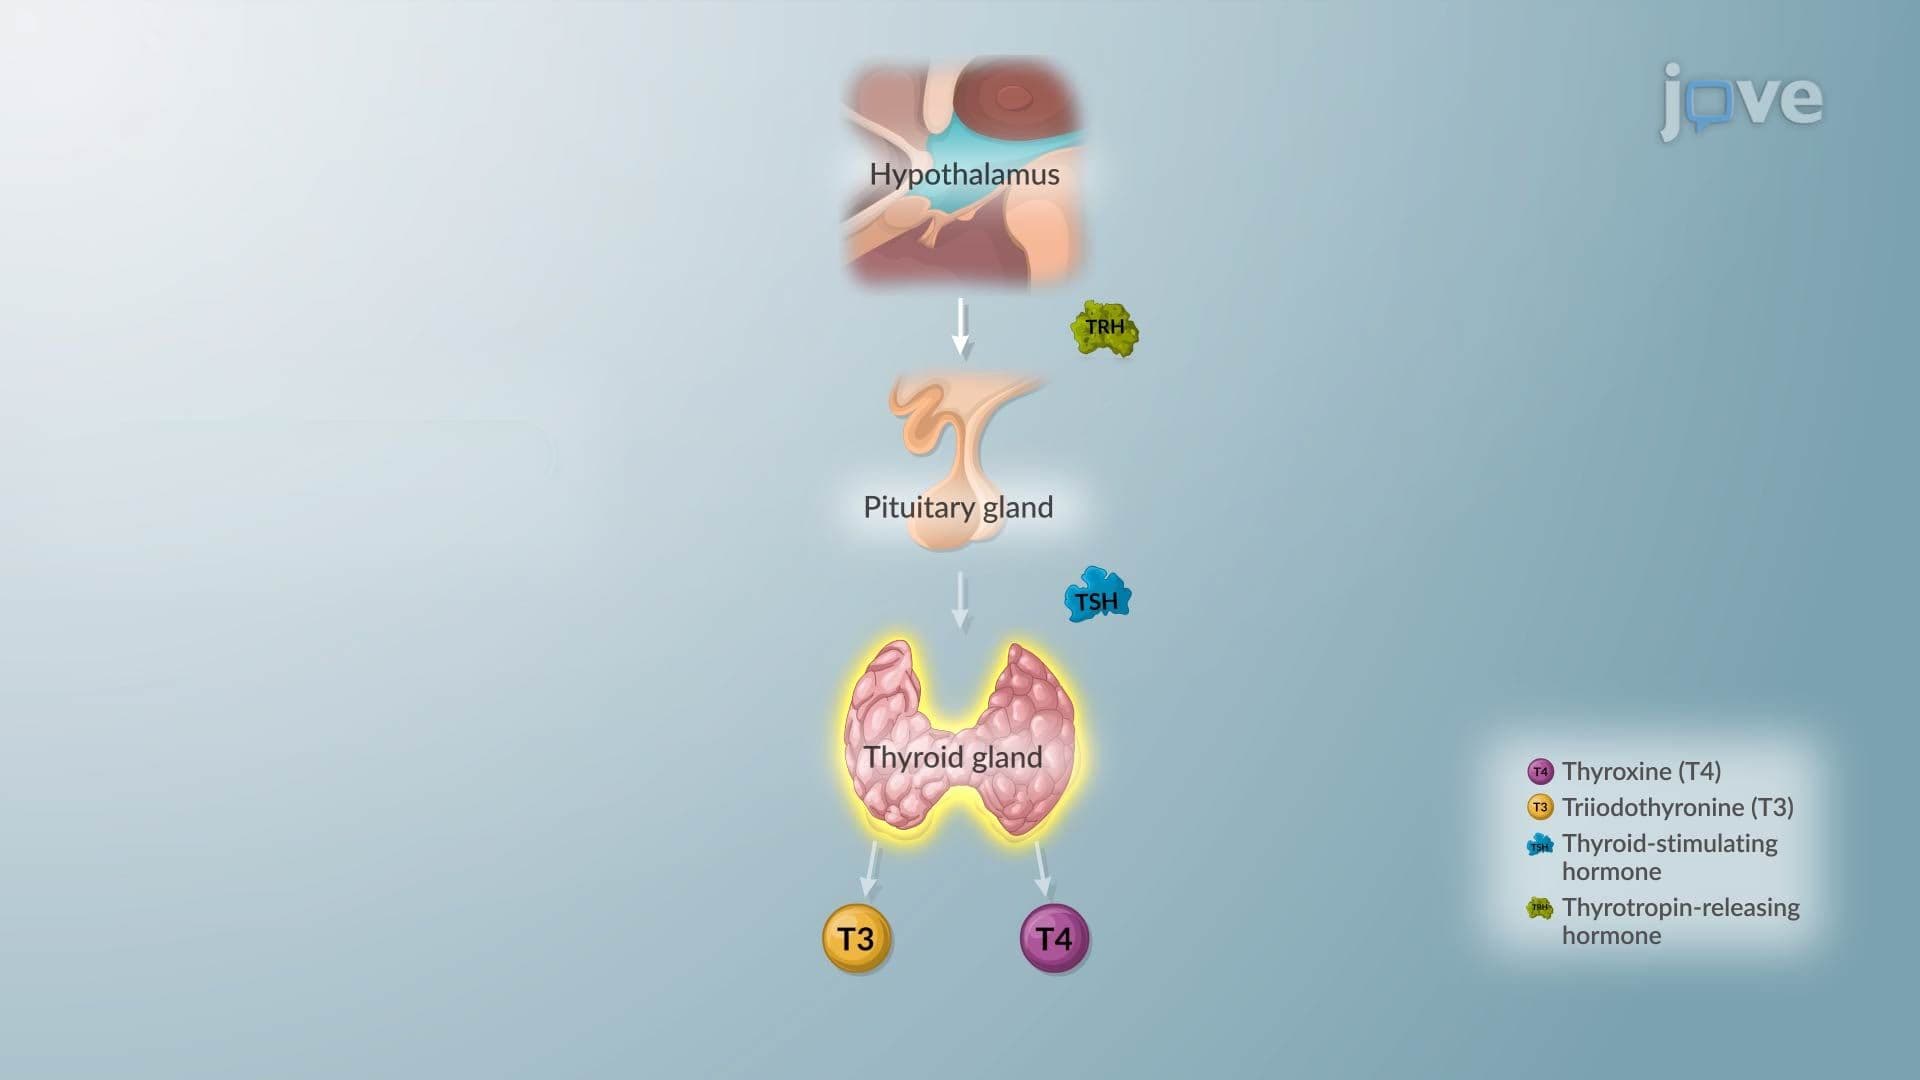
Hypothyroidism II: Pathophysiology