Related Experiment Video
Updated: Jan 22, 2026

A Quantitative Sensory Testing Paradigm to Obtain Measures of Pain Processing in Patients Undergoing Breast Cancer Surgery
Published on: January 18, 2018
Feasibility of closed-loop titration of norepinephrine infusion in patients undergoing moderate- and high-risk
Alexandre Joosten1, Brenton Alexander2, Jacques Duranteau3
1Department of Anesthesiology and Erasme Hospital, Université Libre de Bruxelles, Brussels, Belgium; Department of Anesthesiology and Intensive Care, Hôpitaux Universitaires Paris-Sud, Université Paris-Sud, Université Paris-Saclay, Hôpital De Bicêtre, Assistance Publique Hôpitaux de Paris (AP-HP), Le Kremlin-Bicêtre, France.

Background:
Vasopressor agents are used to prevent intraoperative hypotension and ensure adequate perfusion. Vasopressors are usually administered as intermittent boluses or manually adjusted infusions, but this practice requires considerable time and attention. We have developed a closed-loop vasopressor (CLV) controller to correct hypotension more efficiently. Here, we conducted a proof-of-concept study to assess the feasibility and performance of CLV control in surgical patients.
Methods:
Twenty patients scheduled for elective surgical procedures were included in this study. The goal of the CLV system was to maintain MAP within 5 mm Hg of the target MAP by automatically adjusting the rate of a norepinephrine infusion using MAP values recorded continuously from an arterial catheter. The primary outcome was the percentage of time that patients were hypotensive, as defined by a MAP of 5 mm Hg below the chosen target. Secondary outcomes included the total dose of norepinephrine, percentage of time with hypertension (MAP>5 mm Hg of the chosen target), raw percentage "time in target" and Varvel performance criteria.
Results:
The 20 subjects (median age: 64 years [52-71]; male (35%)) underwent elective surgery lasting 154 min [124-233]. CLV control maintained MAP within ±5 mm Hg of the target for 91.6% (85.6-93.3) of the intraoperative period. Subjects were hypotensive for 2.6% of the intraoperative period (range, 0-8.4%). Additional performance criteria for the controller included mean absolute performance error of 2.9 (0.8) and mean predictive error of 0.5 (1.0). No subjects experienced major complications.
Conclusions:
In this proof of concept study, CLV control minimised perioperative hypotension in subjects undergoing moderate- or high-risk surgery. Further studies to demonstrate efficacy are warranted.
Trial Registry Number:
NCT03515161 (ClinicalTrials.gov).
More Related Videos
 06:46
Competing-Risk Nomogram for Predicting Cancer-Specific Survival in Multiple Primary Colorectal Cancer Patients after Surgery
Published on: September 27, 2024
 07:37
Label-free Neutrophil Enrichment from Patient-derived Airway Secretion Using Closed-loop Inertial Microfluidics
Published on: June 7, 2018
Related Concept Videos
 01:17
Open and closed-loop control systems
An open-loop control system operates without feedback from the output. It consists of two primary elements: the controller and the controlled process. The controller receives an input signal...
 02:08
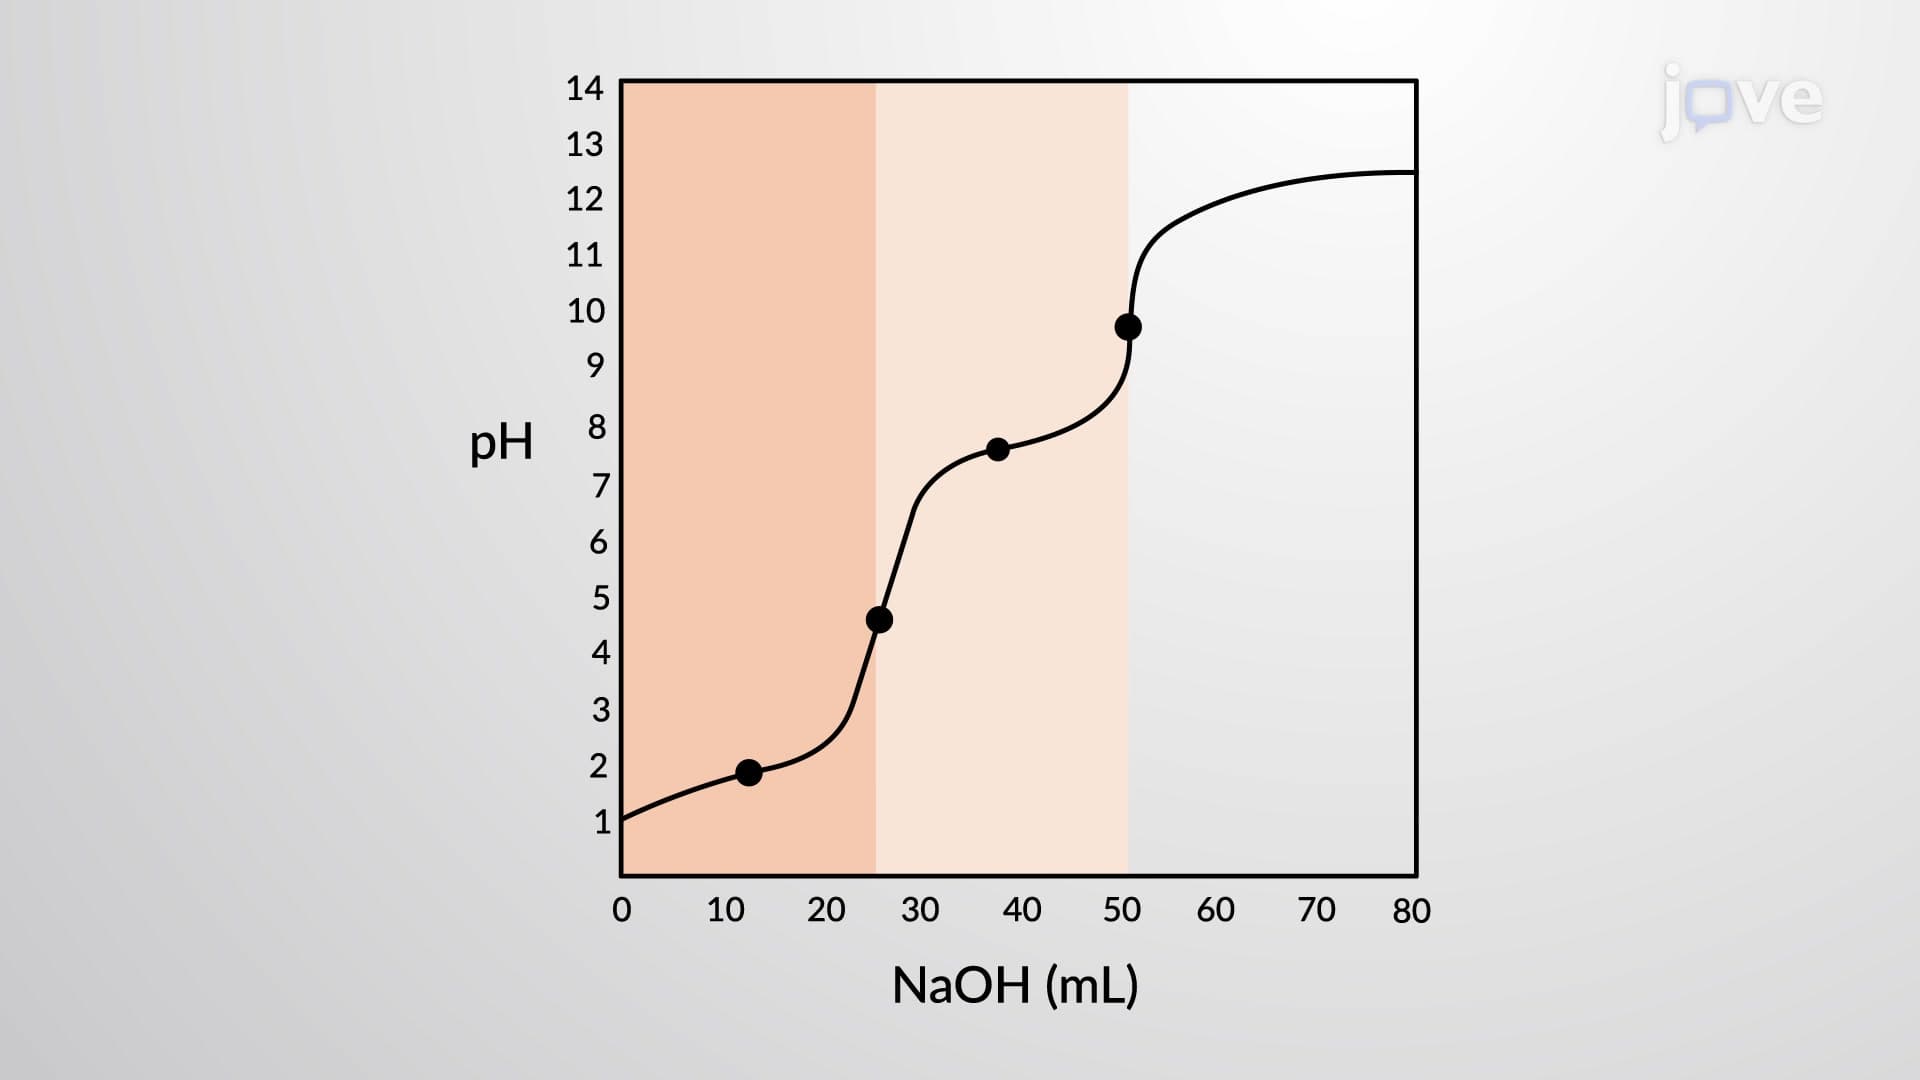
Titration of a Polyprotic Acid
 02:23
Acid-Base Titration Curves
For a titration carried out for 25.00 mL of...
 03:55
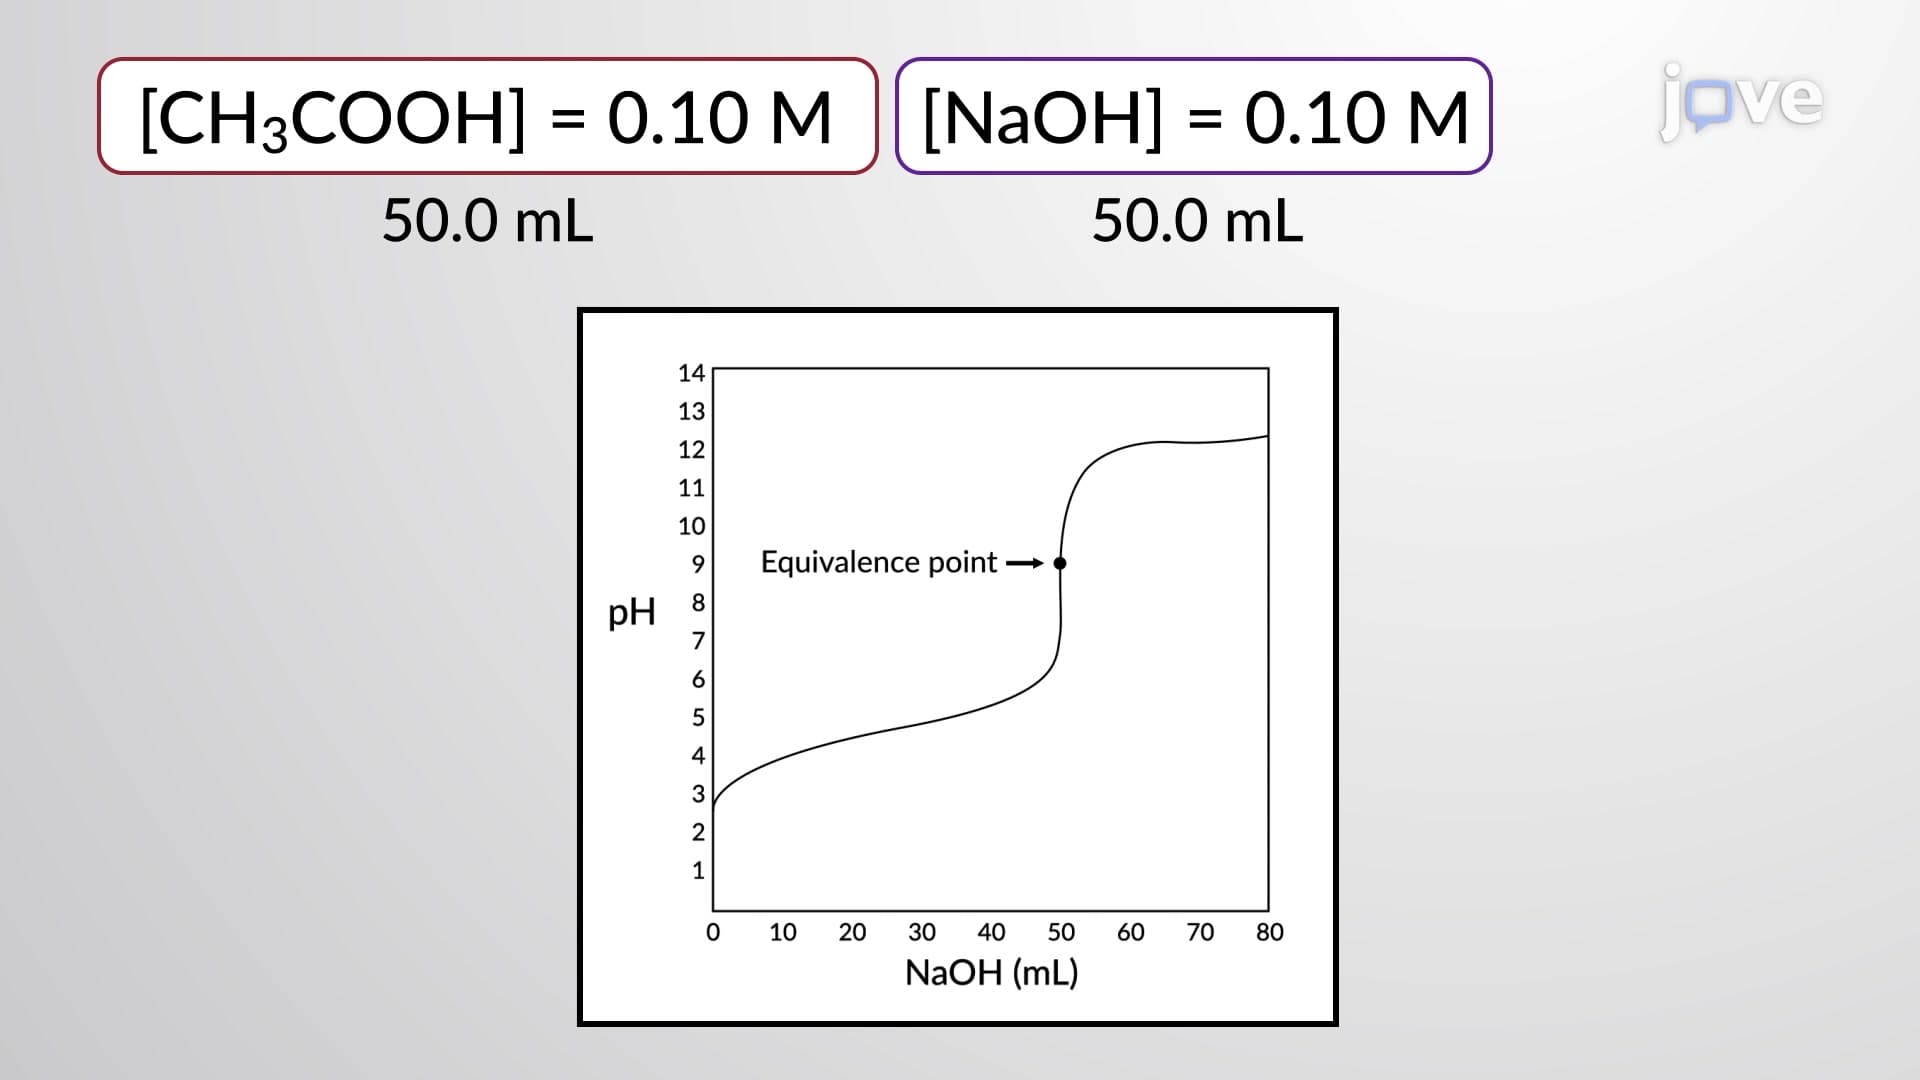
Titration Calculations: Weak Acid - Strong Base
For the titration of 25.00 mL of 0.100 M CH3CO2H with 0.100 M NaOH, the reaction can be represented as:
 02:28
Titration Calculations: Strong Acid - Strong Base
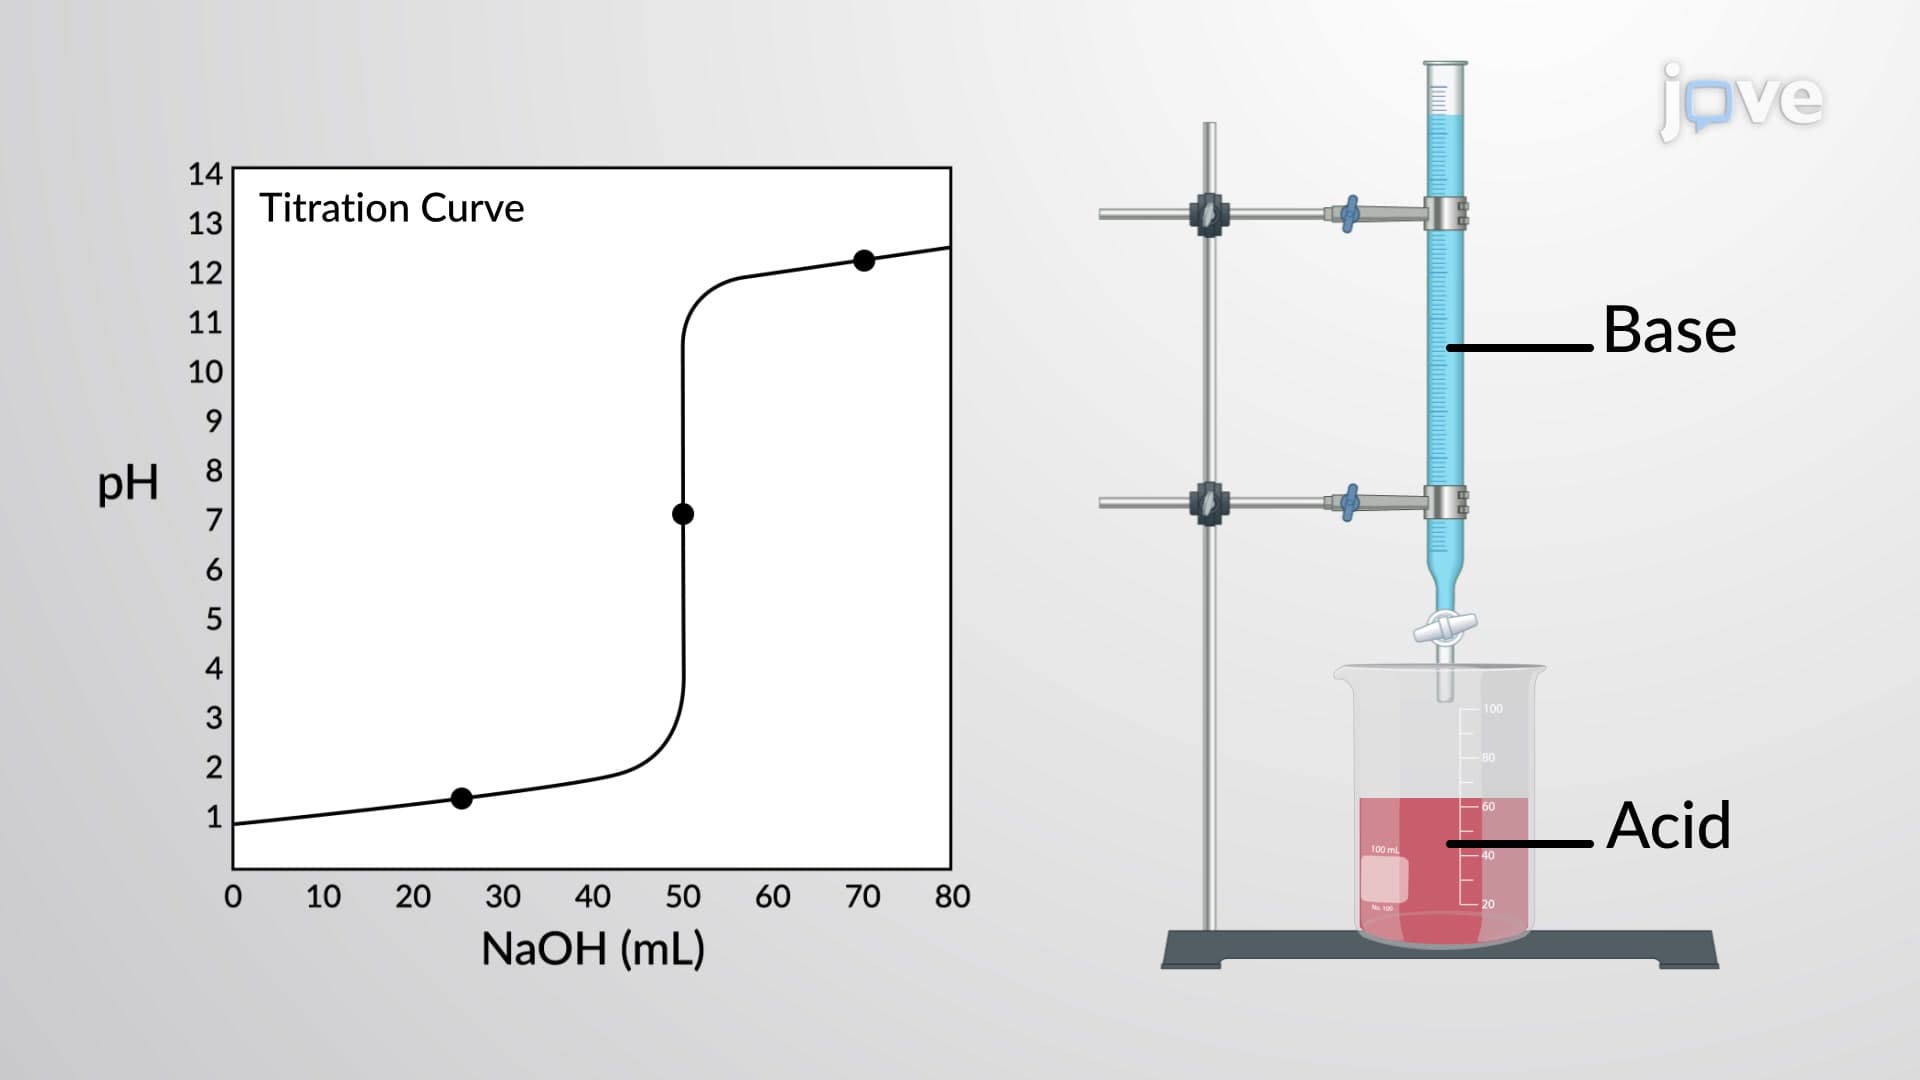
A titration is carried out for 25.00 mL of 0.100 M HCl (strong acid) with 0.100 M of a strong base NaOH. The pH at different volumes of added base solution can be calculated as follows:
(a) Titrant volume = 0 mL. The solution pH is due to the acid ionization of HCl. Because this is a strong acid, the ionization is complete and the hydronium ion molarity is 0.100 M. The pH of the solution is then:
 01:12
Relative Risk