Related Experiment Video
Updated: Jan 22, 2026
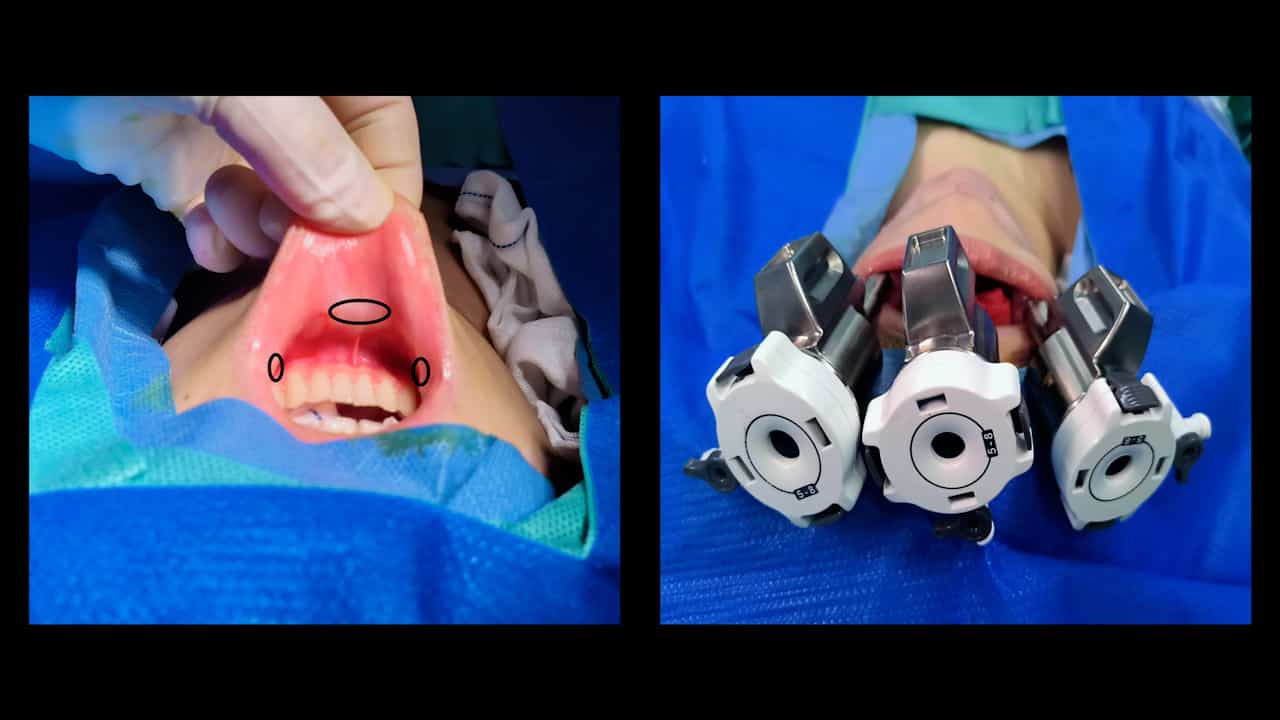
Identification and Protection of the Recurrent Laryngeal Nerve during Transoral Robotic Thyroidectomy
Published on: October 24, 2025
Complete and incomplete recurrent laryngeal nerve injury after thyroid and parathyroid surgery: Characterizing
Max Schneider1, Valerie Dahm2, Christian Passler1
1Surgical Department, Rudolfstiftung, Wien Kliniken, Rudolfstiftung, Vienna, Austria.

Background:
Injury of the recurrent laryngeal nerve and consequent disorder of vocal fold movement is a typical complication in thyroid and parathyroid surgery. During postoperative laryngoscopy we observed not only a complete standstill (vocal fold paralysis), but also a hypomobility (paresis). In this prospective study, we investigated the difference in incidence and prognosis as well as risk-factors, intraoperative neuromonitoring, and symptoms between vocal fold paralysis and vocal fold paresis.
Methods:
Data were prospectively collected and analyzed in a single high-volume thyroid center between 2012 and 2016. Vocal fold paresis was defined as hypomobility in abduction or adduction, a reduction in range and speed of vocal fold movement. Vocal fold paralysis was defined as asymmetry and missing purposeful vocal fold movement.
Results:
The study included 4,707 surgeries and 7,992 at-risk nerves at risk. Vocal fold paralysis was diagnosed in 374 patients (4.68% of 7,992 nerves at risk) and vocal fold paresis in 114 patients (1.43%). Exclusively in the paralysis group, 36 patients (0.45%) developed permanent loss of vocal fold function (P < .001). In follow-up, vocal fold paresis patients regain normal vocal fold function significantly earlier than vocal fold paralysis (mean duration: 6.96 ± 6.506 vs 10.77 ± 7,827 weeks) and presented with significantly less symptoms like hoarseness, diplophonia, dysphagia, and dyspnea (68.8% vs 95.9 %). In intraoperative neuromonitoring, vocal fold paresis showed a significantly higher postresectional N. vagus amplitude than vocal fold paralysis patients (0.349 mV vs 0.114 mV, P < .001).
Conclusion:
After thyroidectomy, vocal fold paresis must be distinguished from vocal fold paralysis and should be implemented as a separate outcome parameter in the postoperative quality assessment.
More Related Videos

Related Concept Videos
 01:43
Incomplete Dominance
 00:59
The Parathyroid Glands
Oxyphil cells, whose functions remain elusive, emerge during late puberty, adding a layer of complexity to the parathyroid gland's intricacies. In contrast, principal parathyroid cells undertake a vital role by...
 01:23
The Thyroid Gland
The follicles have a central cavity lined by simple cuboidal to squamous epithelial cells called follicular cells. These cells produce the glycoprotein...
 01:18
Functions of Thyroid Hormones
TH is indispensable for the normal development and maturation of the skeletal, muscular, and nervous systems during fetal and childhood growth. It facilitates bone mineral turnover and regulates protein synthesis in developing tissues, contributing significantly to overall growth and...
 01:20
Synthesis and Regulation of Thyroid Hormones
Upon reaching the thyroid gland, TSH stimulates the follicular cells' active uptake of iodide ions from the blood. The ions diffuse to the apical surface of the cells and are oxidized to iodine. The...
 01:27
Nerve Supply of the GI Tract
The enteric nervous system consists of two major plexuses: the myenteric plexus (Auerbach's plexus) and the submucosal plexus (Meissner's plexus). These plexuses are located within the layers of...