Related Experiment Video
Updated: Jan 22, 2026

Development of New Therapeutic Applications Using Microfluidics
Published on: October 1, 2007
Chenodeoxycholic Acid: An Update on Its Therapeutic Applications
Stefano Fiorucci1,2, Eleonora Distrutti3
1Section of Gastroenterology, Department of Surgical and Biomedical Sciences, University of Perugia, Perugia, Italy. Stefano.fiorucci@unipg.it.

Abstract:
Chenodeoxycholic acid (CDCA), 3α,7α-dihydroxy-5β-cholan-24-oic acid, is a primary bile acid generated in the liver from cholesterol. In liver cells CDCA is conjugated with glycine or taurine to form two bile salts, Glyco-CDCA and Tauro-CDCA, before being released into the bile ducts. In the intestine, CDCA is further metabolized to generate a 7β epimer, i.e., the ursodeoxycholic acid (UDCA), or dehydroxylate to generate lithocolic acid (LCA). In humans, CDCA is the physiological ligand for the bile acid sensor farnesoid X receptor (FXR), while LCA is a potent agonist for a G protein-coupled receptor, known as GPBAR1 (TGR5). Along with UDCA, CDCA has been clinically used for the dissolution of gallbladder stones at doses ranging from 375 to 750 mg/day, with a success rate of 8 to 18%. Because the efficacy of CDCA was significantly lower than that of UDCA and 18-30% of patients developed significant side effects, the most frequent being diarrhea and a reversible increase in aminotransferases plasma levels, this application has lost its therapeutic relevance. Additionally, the combination of CDCA with UDCA, generally at doses of 5-10 mg/kg each, has failed to provide significant advantages over UDCA alone. In 2017, CDCA has been approved as an orphan indication for the treatment of patients with cerebrotendinous xanthomatosis (CTX), a rare autosomal recessive disorder caused by mutations of sterol 27-hydroxylase (CYP27A1) gene. Since CYP27A1 is essential for cholesterol breakdown, CTX patients develop abnormal lipid storage with increased plasma and tissue levels of cholestanol and very low/absent production of CDCA. CDCA is a potent inhibitor of CYP27A1, and early initiation of CDCA therapy, at doses up to 750 mg/day, is considered the standard medical therapy for CTX resulting in decreased plasma levels of cholestanol and stabilization of neurologic symptoms. Studies in CTX patients have also shown that CDCA might suppress the activity of 3-hydroxy-3-methylglutaryl coenzyme A (HMG CoA) reductase in the liver. Furthermore, CDCA promotes the release of glucagon-like peptide-1 (GLP-1) in diabetic patients, likely by activating GPBAR1.

Related Concept Videos
 01:13
Therapeutic Index
 01:30
Therapeutic Communication
Verbal communication depends on language or a prescribed way of using words so that people can share information effectively. The critical aspects of verbal...
 03:42
Amino acids
 03:27
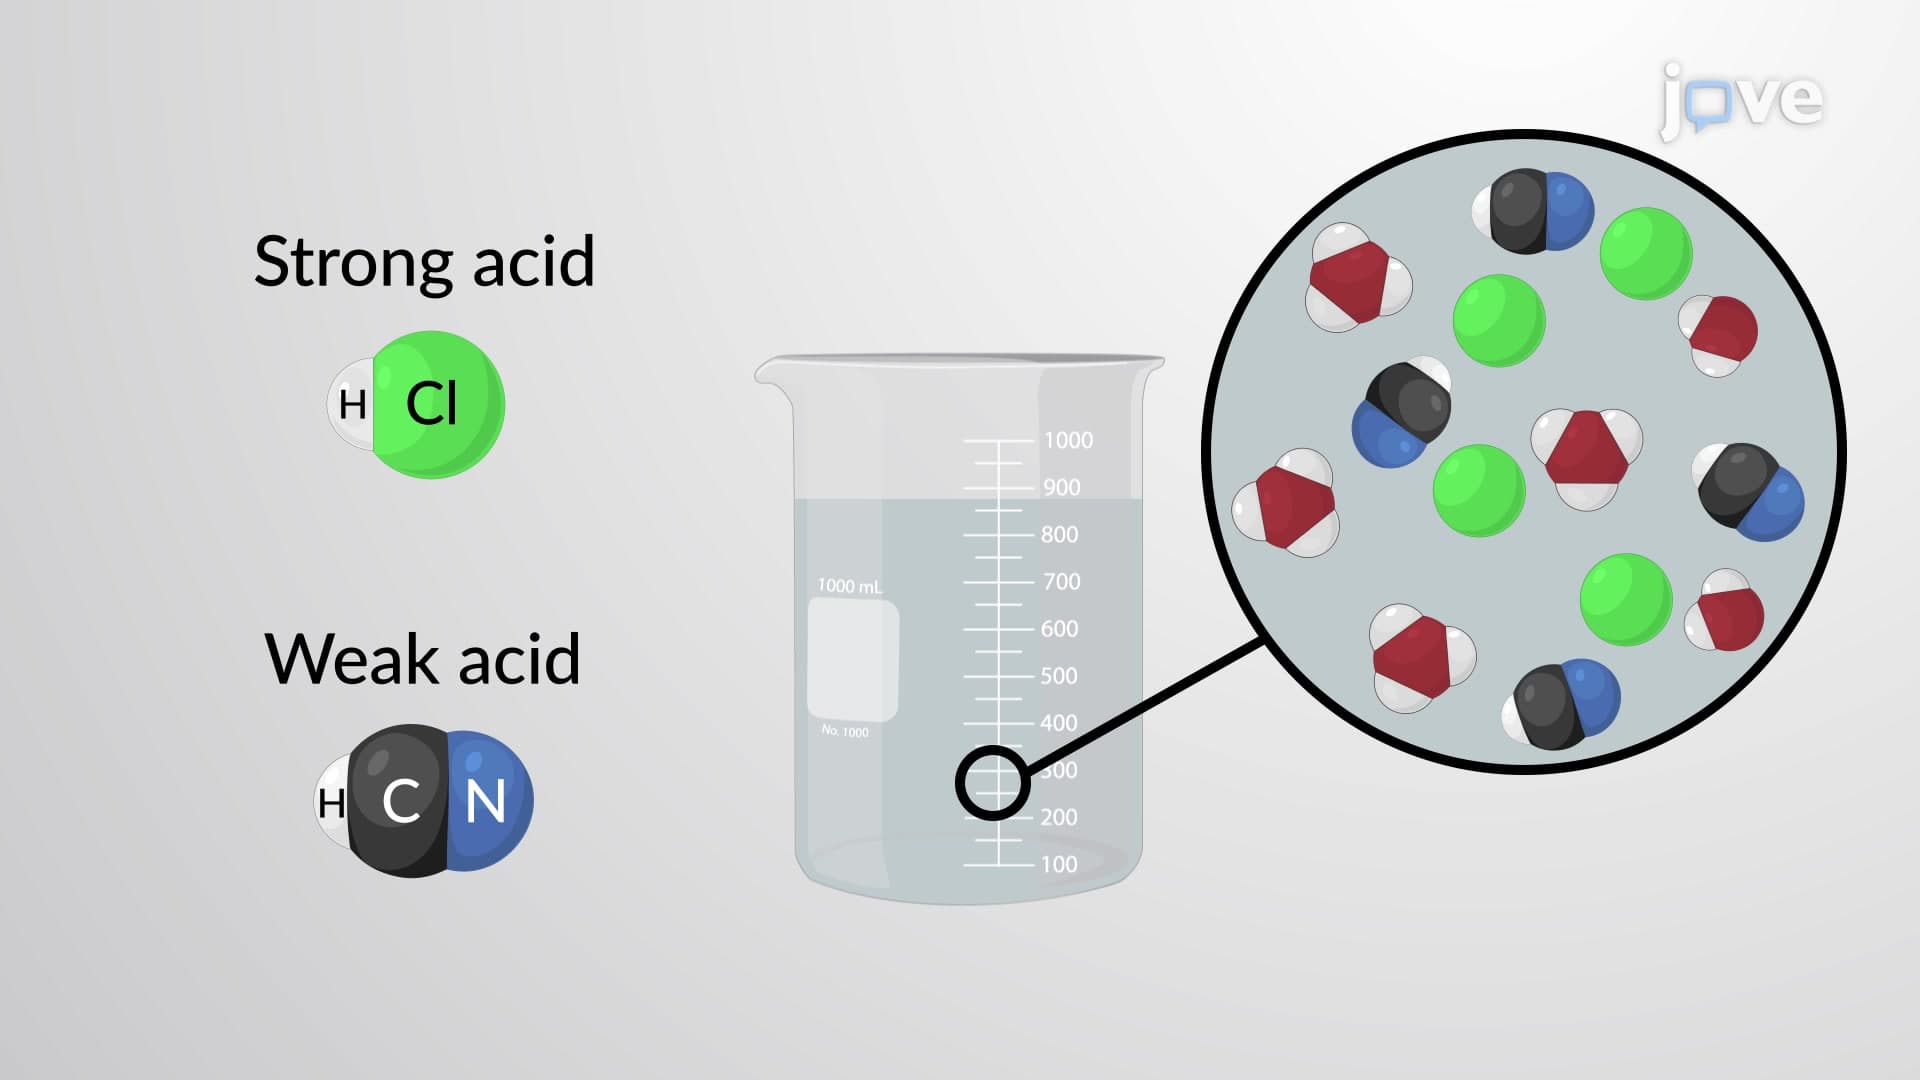
Mixtures of Acids
A Mixture of a Strong Acid and a Weak Acid
In a mixture of a strong acid and a weak acid, the strong acid dissociates completely and becomes a source of almost all the hydronium ions...
 03:38
Polyprotic Acids
 02:43
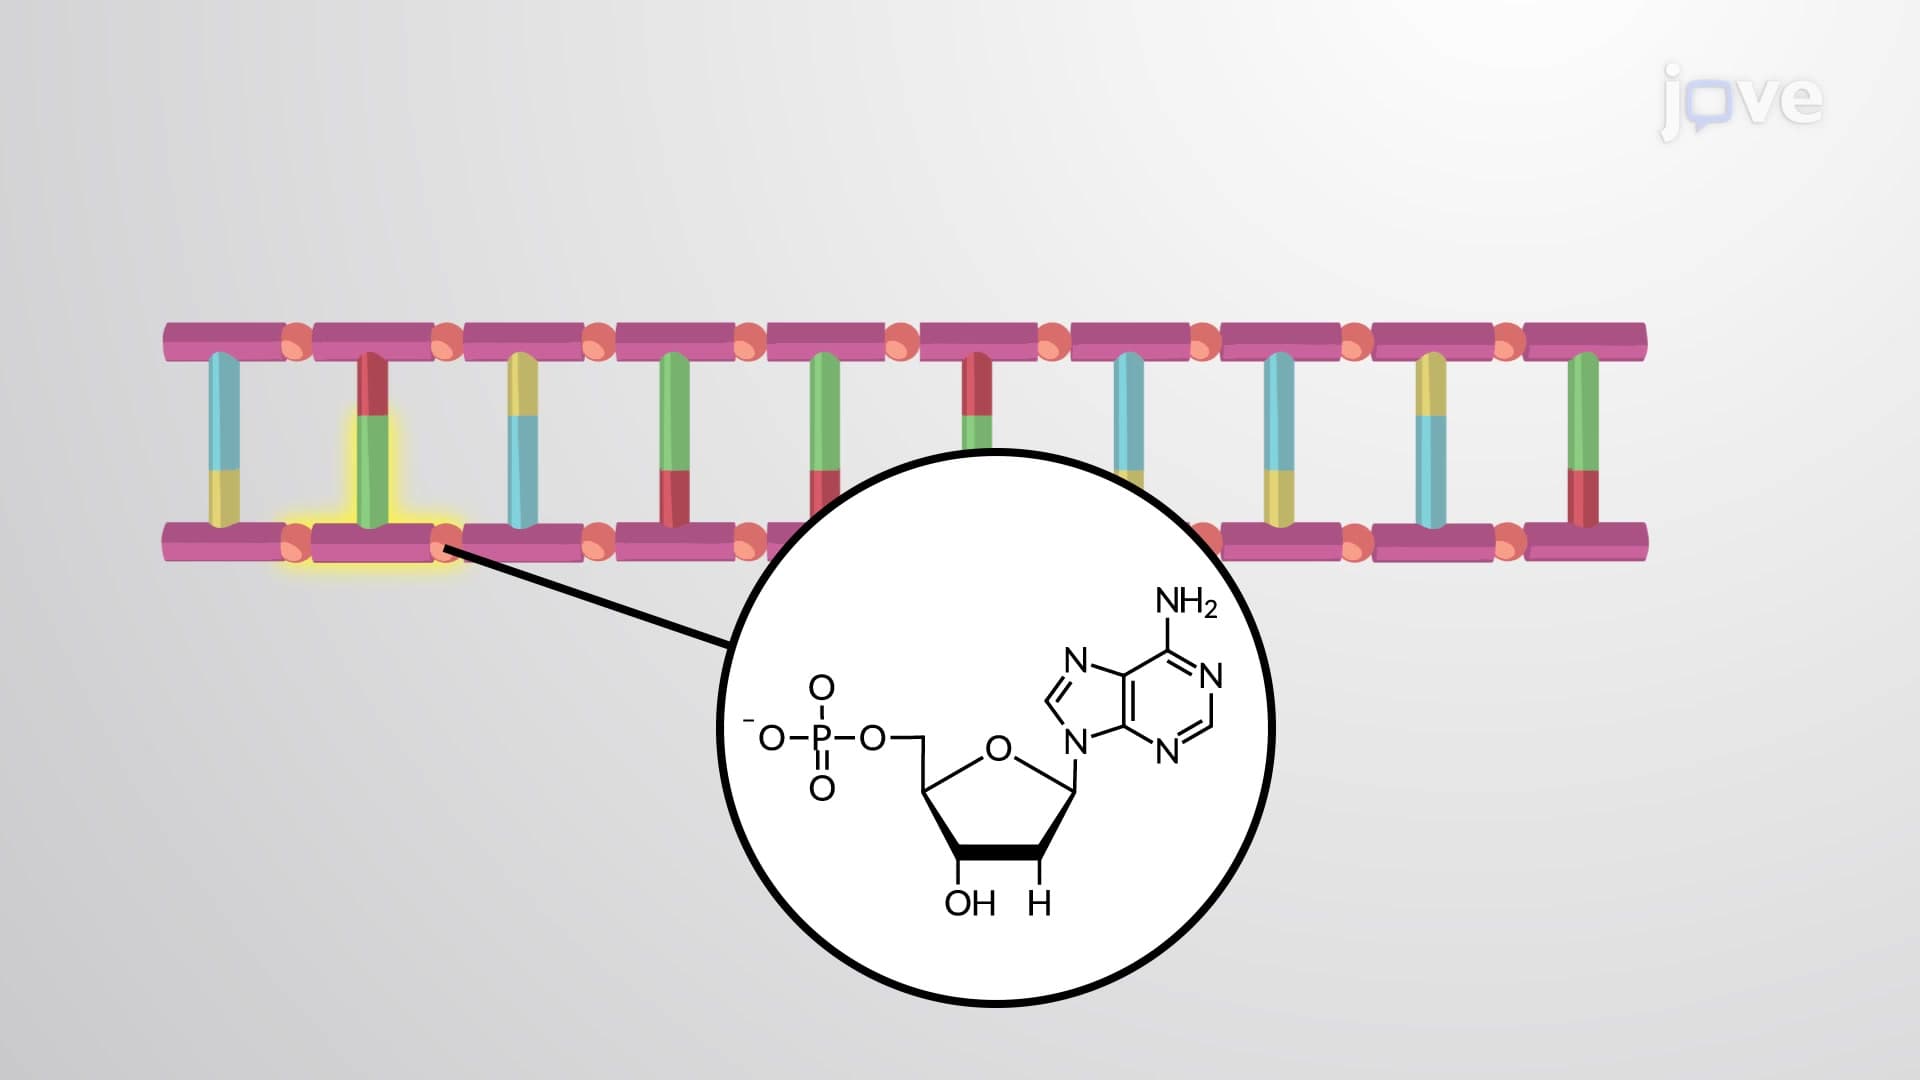
Nucleic acids
DNA and RNA
The two main types of nucleic acids are deoxyribonucleic acid (DNA) and ribonucleic acid (RNA). DNA is the genetic material in all living organisms, ranging from single-celled bacteria to multicellular mammals. It is in the nucleus of eukaryotes and in the organelles, chloroplasts, and mitochondria. In prokaryotes,...