Related Experiment Video
Updated: Jan 22, 2026

Spinal Cord Electrophysiology
Published on: January 18, 2010
Impact of spinal needle design and approach to postdural puncture headache and spinal anesthesia failure in
Roumiana Batova1, Silvi Georgiev1
1Department of Anesthesiology and Intensive Care, University Hospital of Obstetrics and Gynecology 'Maichin Dom', Medical University, Sofia, Bulgaria.

Background:
Concern has been raised that Sprotte needles predispose to spinal anes-thesia failure. Nevertheless, these needles are associated with a low incidence of postdural puncture headache. The impact of the paramedian approach to postdural puncture headache remains controversial. The objective of this prospective randomized study was to compare Sprotte, Quincke and Atraucan needles as well as the midline and the paramedian approach in terms of postdural puncture headache and spinal anesthesia failure in patients undergoing Caesarean section.
Methods:
655 patients were randomized to 5 groups. A midline approach was used in four groups. The spinal needles were the 25G Sprotte, 27G Sprotte, 26G Atraucan and 25G Quincke. In the fifth group a 25G Quincke needle was used by the paramedian approach.
Results:
The incidence of postdural puncture headache was 0% in both 25G and 27G Sprotte groups, 2.5% in the 26G Atraucan group, and 7.2% and 2.7% in the 25G Quincke midline and paramedian approach respectively. A significant difference in terms of postdural puncture headache was found between 25G Sprotte and 25G Quincke needles (P = 0.004), while the failure rate was similar between these two needles. A significant difference in spinal anesthesia failure rate was observed between midline and paramedian approaches (P = 0.041).
Conclusions:
Sprotte but not Atraucan needle design correlates with lower incidence of postdural puncture headache compared to Quincke design. Sprotte needles are not associated with a higher spinal anesthesia failure compared to Quincke needles. The incidence of postdural puncture headache by the paramedian approach is not significantly reduced whereas the spinal anesthesia failure rate is increased in comparison to the midline approach.
Related Concept Videos
 01:11
Local Anesthetics: Clinical Application as Spinal Anesthesia
 01:26
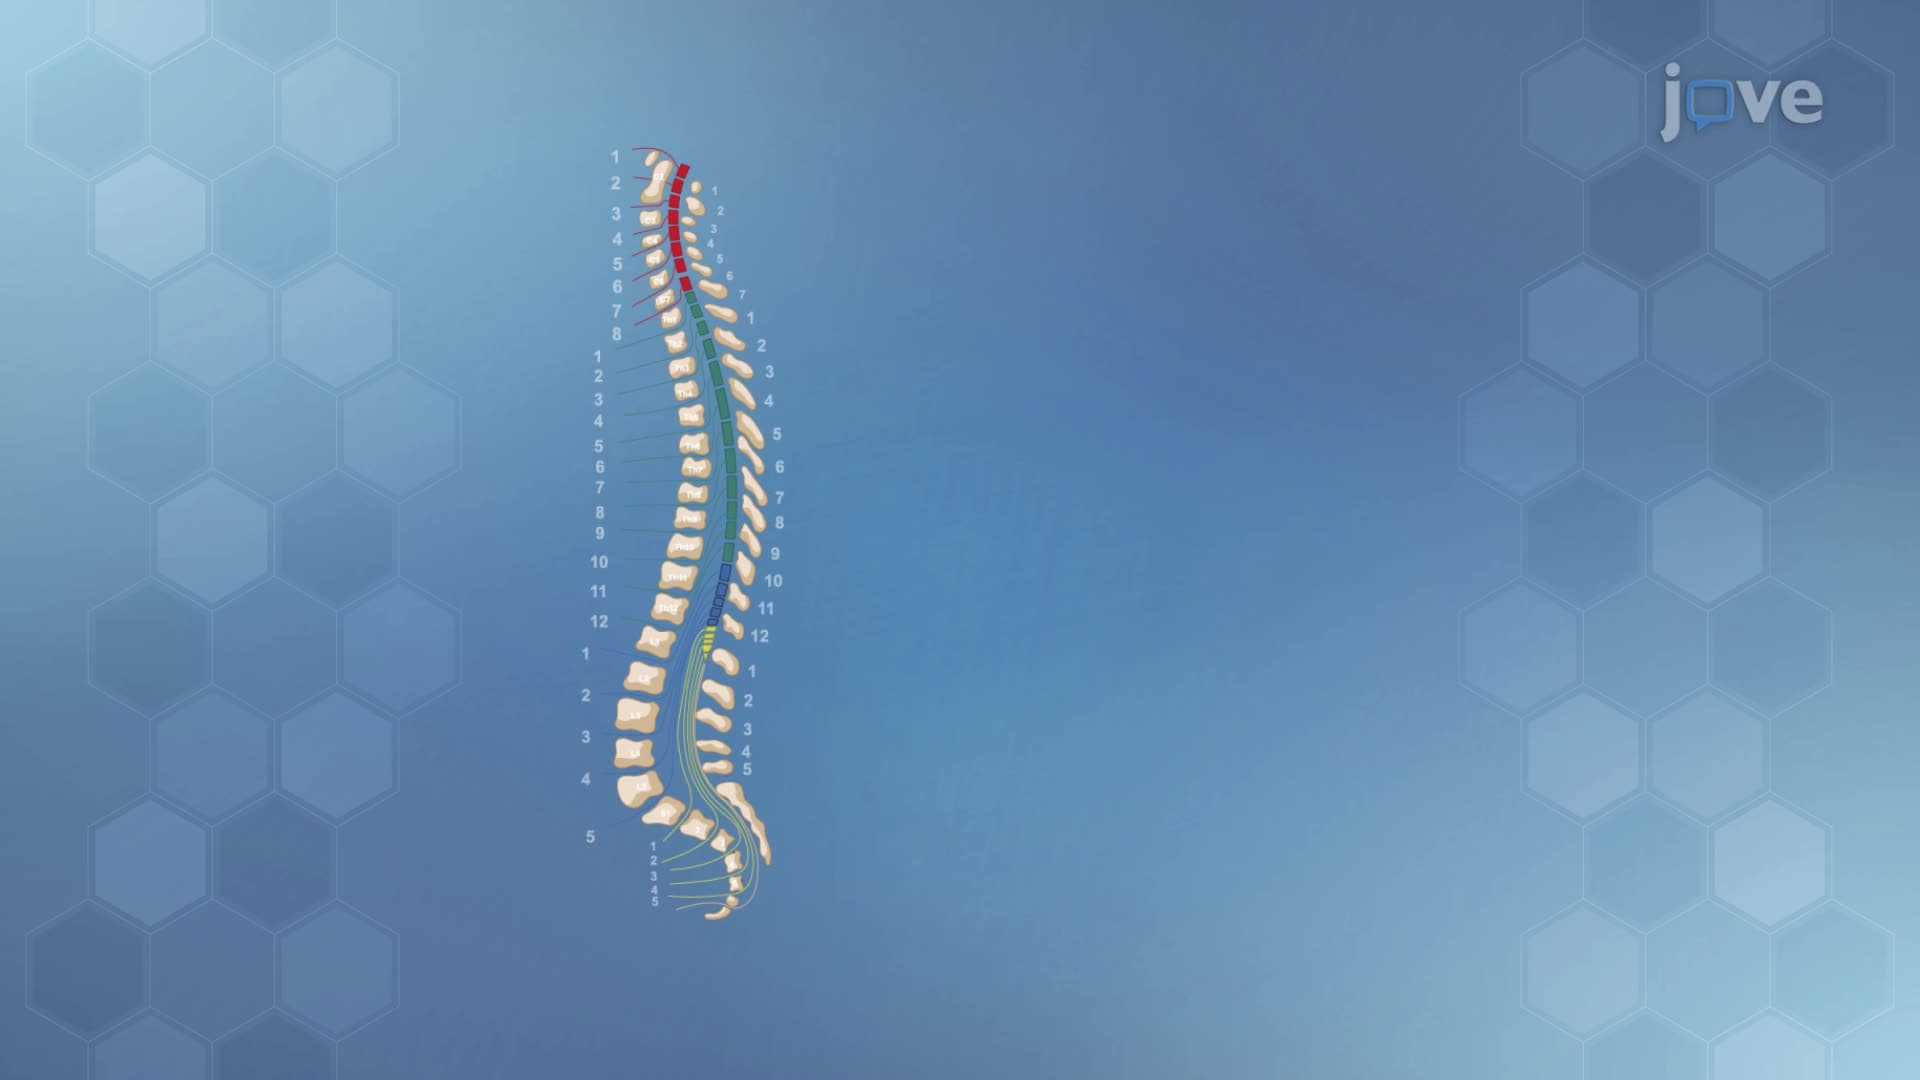
Spinal Cord
 01:54
The Spinal Cord
 01:10
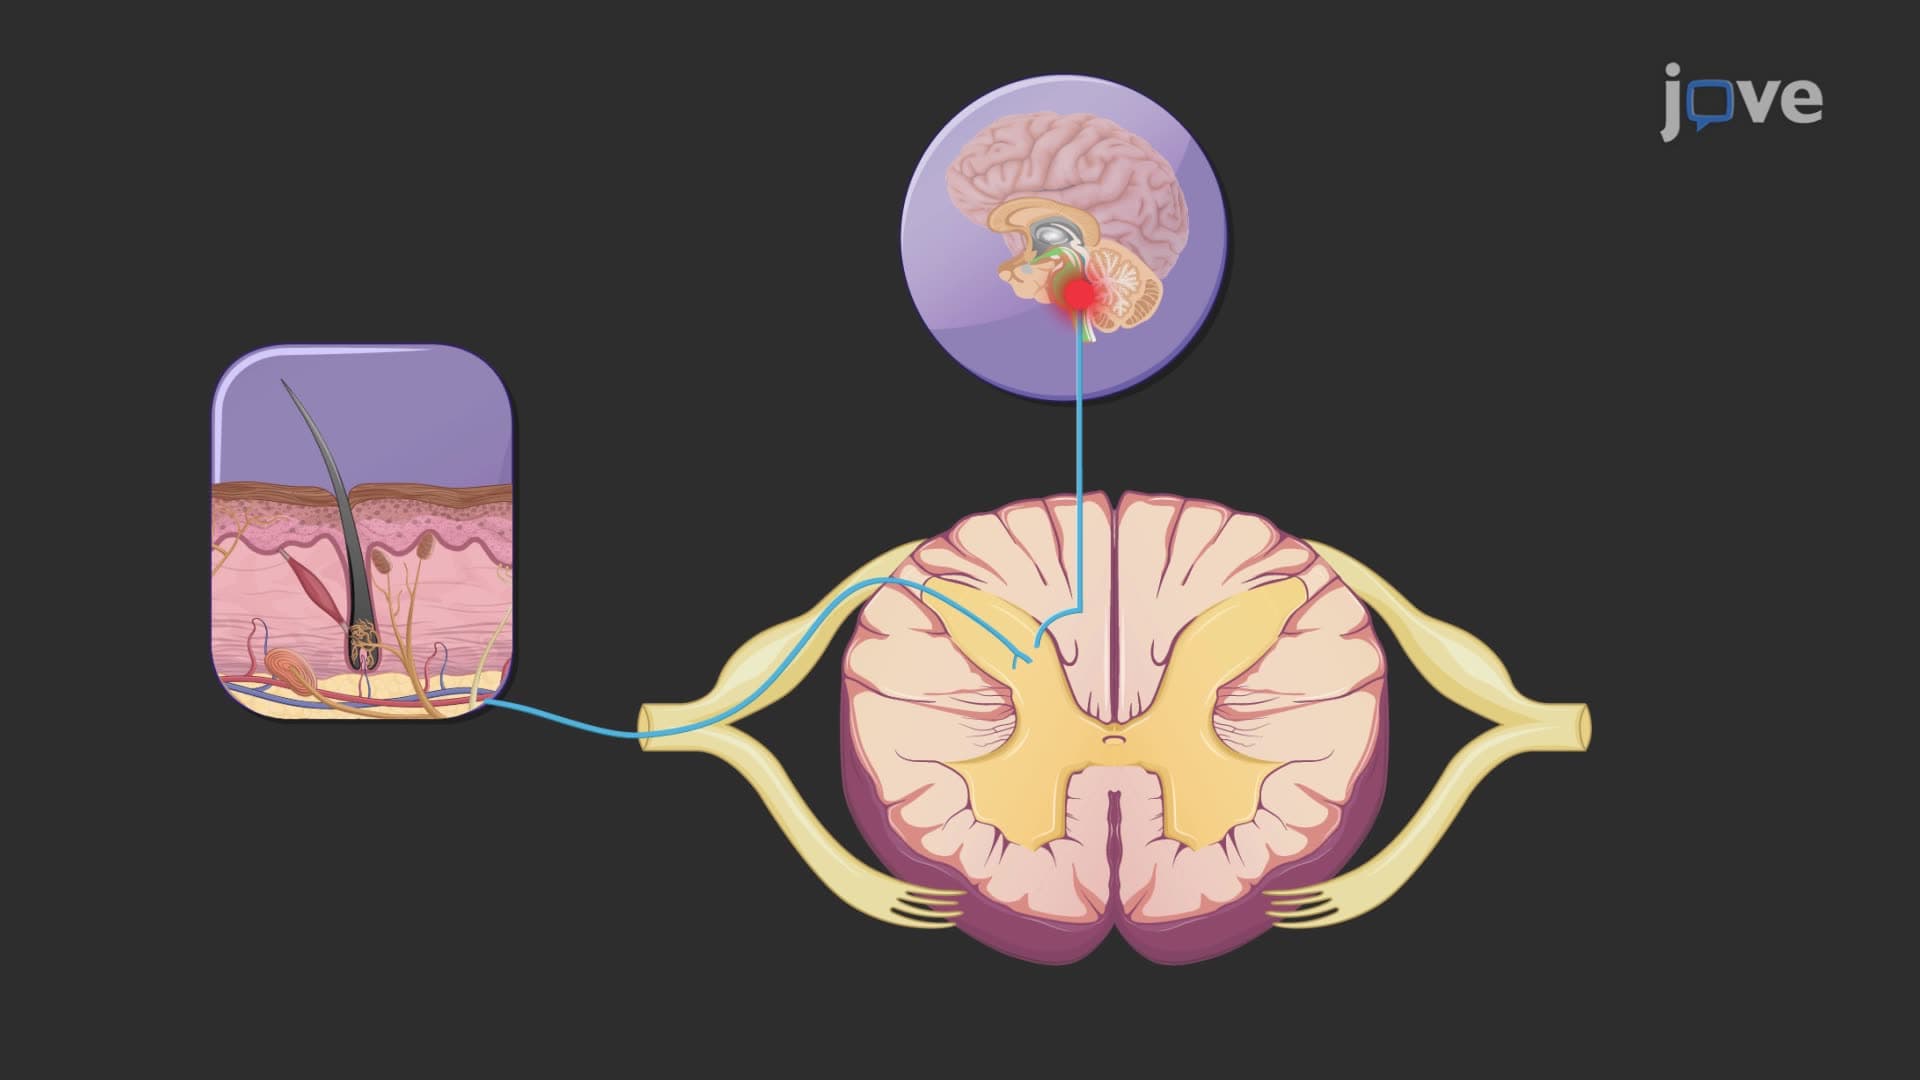
Spinal Cord: Information Processing
Sensory Information Processing
Sensory information processing begins at the sensory receptors located in the skin and other tissues, which detect somatic sensory stimuli such as touch, temperature, or pain. These receptors function as catalysts, initiating...
 01:21
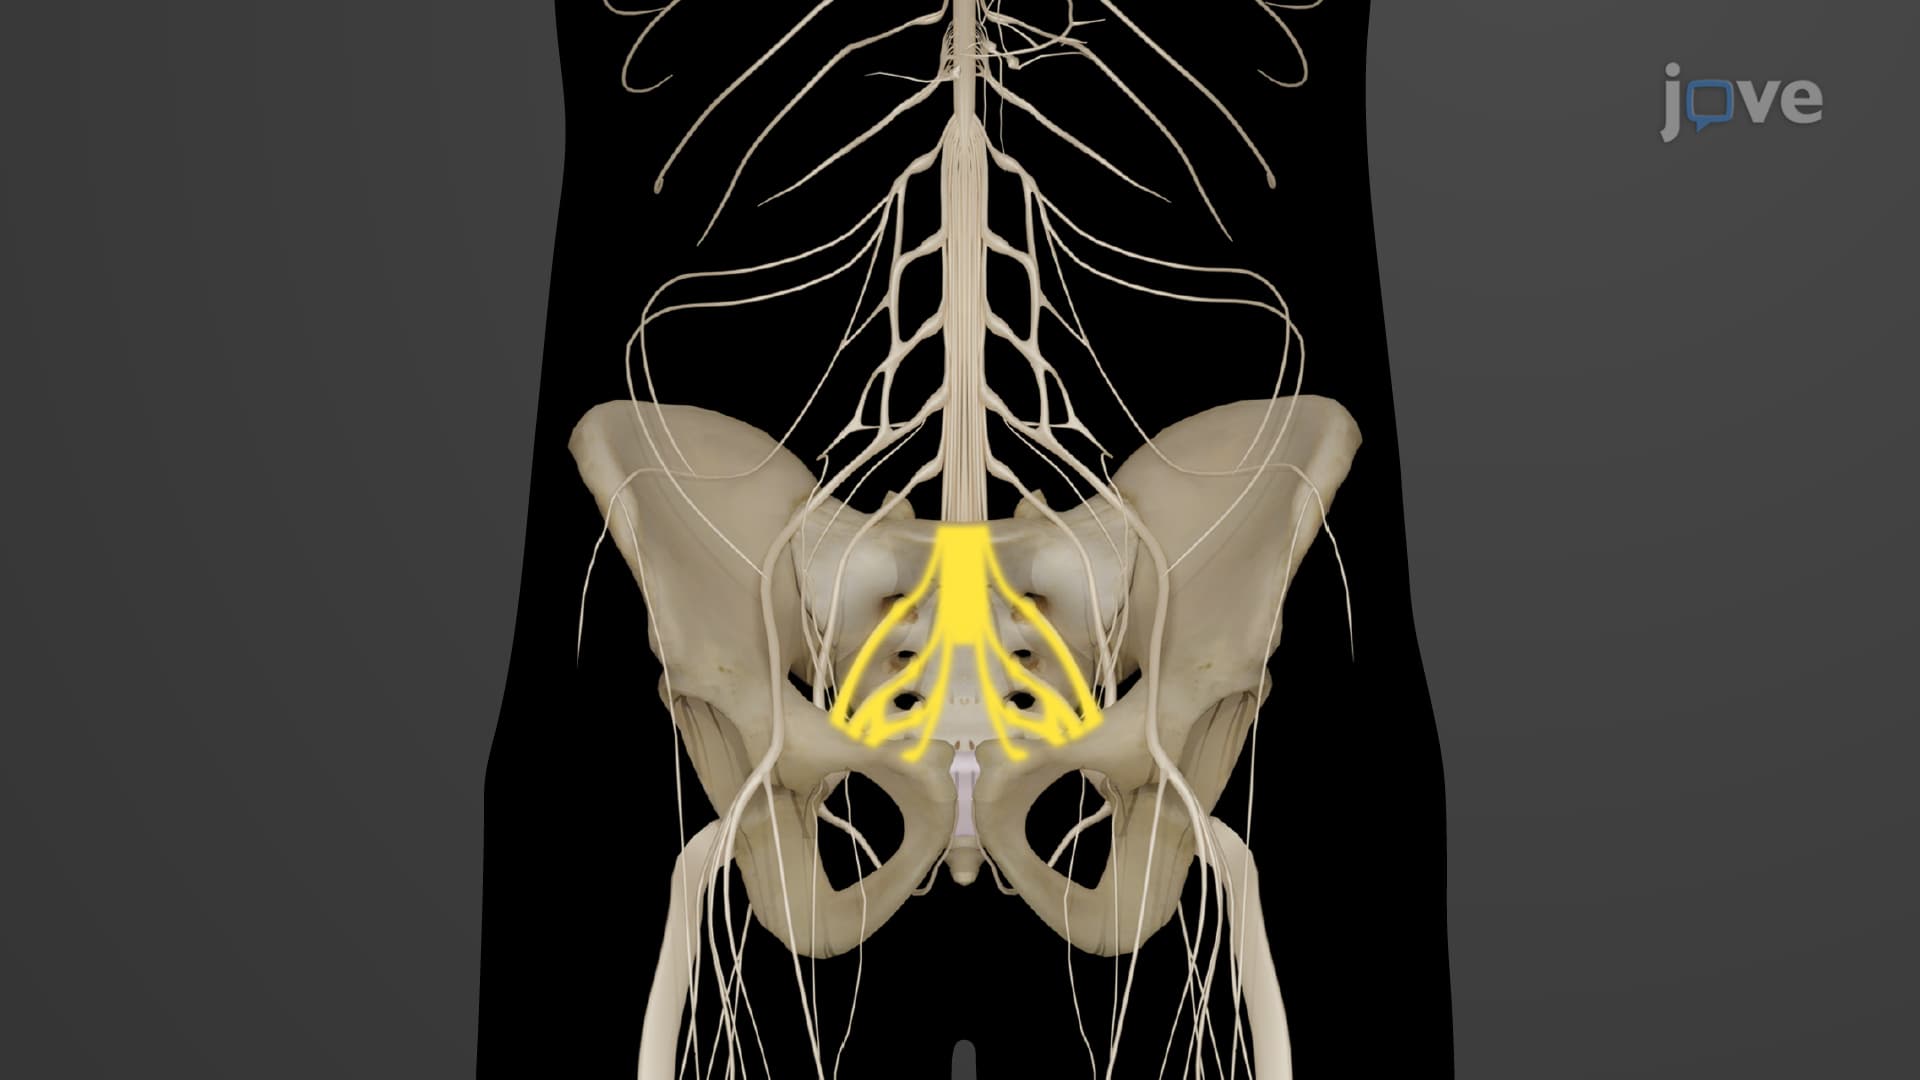
Spinal Nerves: Plexus II
The Lumbar Plexus
The lumbar plexus is situated within the lumbar region of the back and is primarily formed by the first four lumbar spinal nerves (L1 to L4). This plexus extends its branches into several nerves, including the...
 01:19
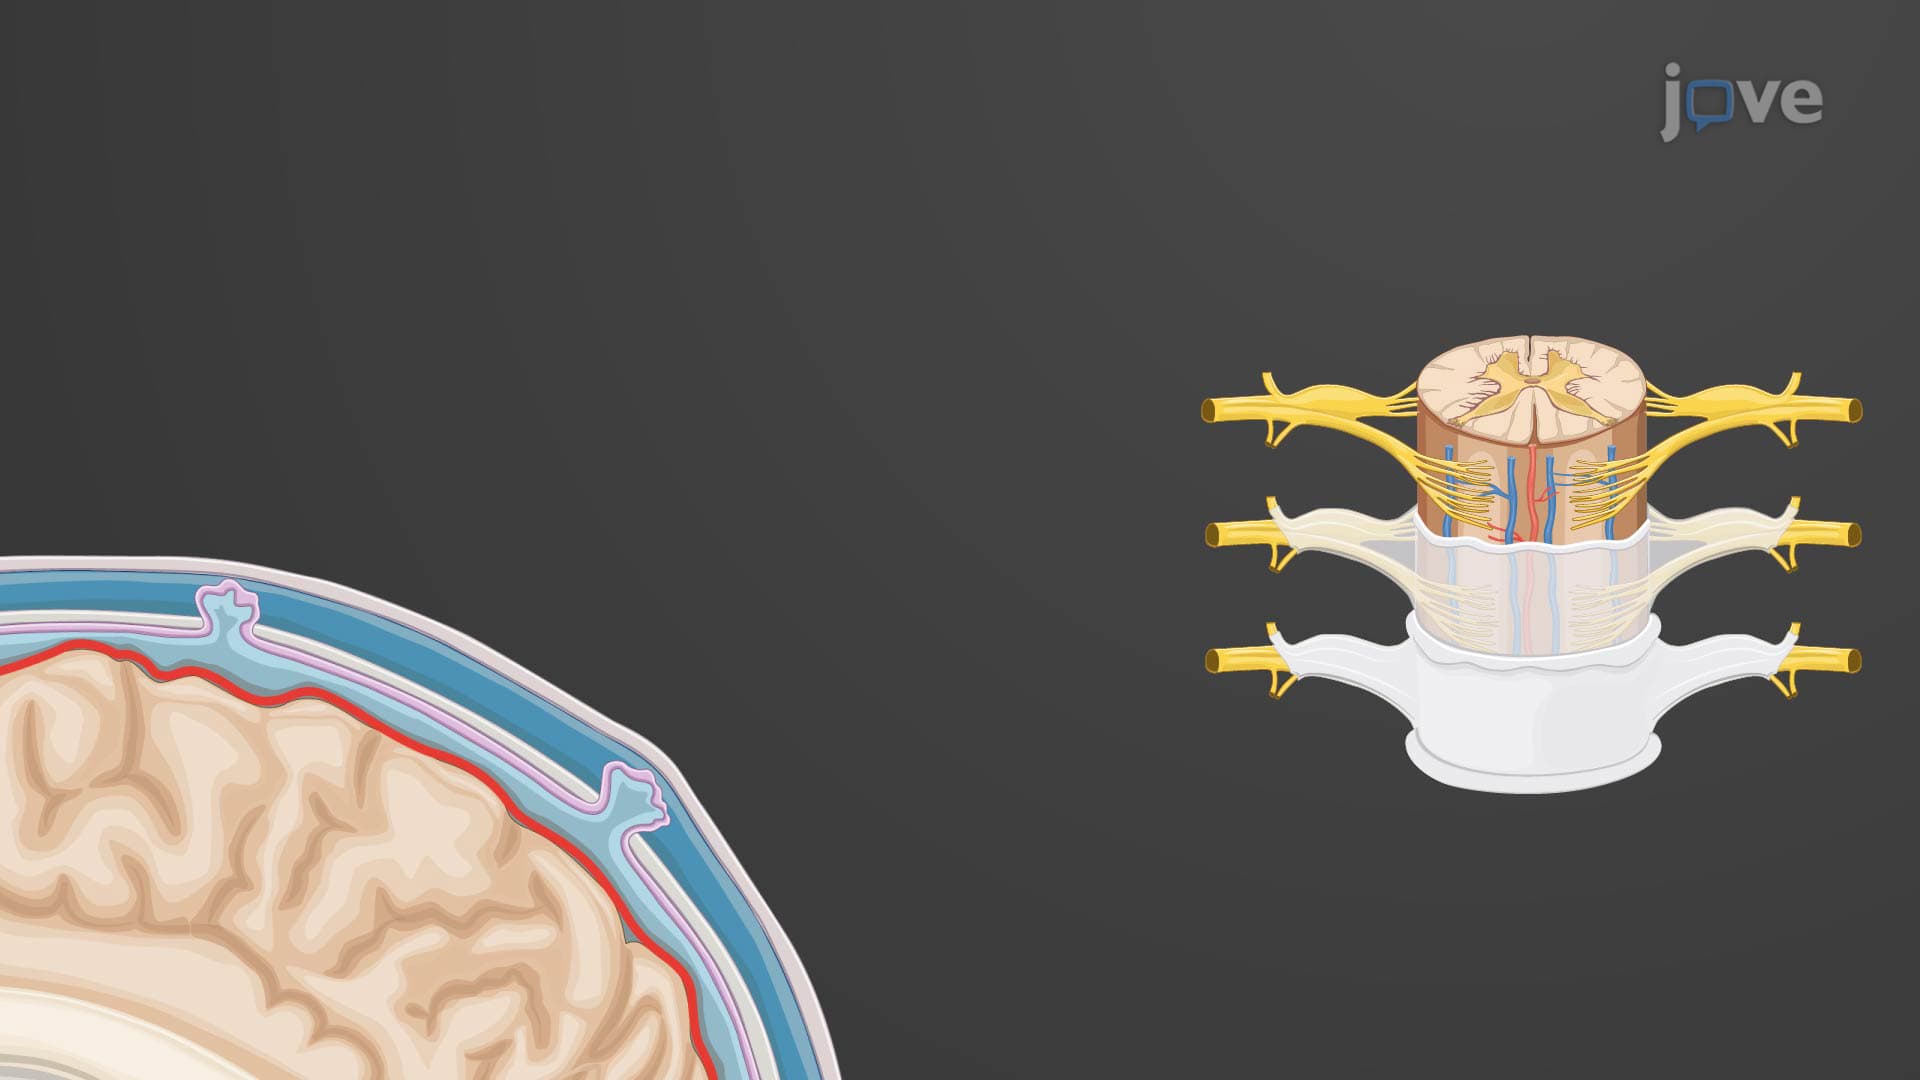
Cranial and Spinal Meninges
Cranial Meninges
These meningeal layers cover the cranium. The dura mater is the outermost layer of cranial meninges. It is a thick and durable membrane of dense...