Related Experiment Video
Updated: Jan 22, 2026

Treatment with Vancomycin Loaded Calcium Sulphate and Autogenous Bone in an Improved Rabbit Model of Bone Infection
Published on: March 14, 2019
Treatment of Human Immunodeficiency Virus Infection With Tenofovir Disoproxil Fumarate-Containing Antiretrovirals
Janaina Ramalho1, Carolina Steller Wagner Martins1, Juliana Galvão2
1Department of Nephrology, Laboratório de Investigação Médica 16, Hospital das Clinicas da Faculdade de Medicina da Universidade de Sao Paulo, SP, Brazil.

Abstract:
Bone mineral density (BMD) loss is a known complication of human immunodeficiency virus (HIV) infection and its treatment, particularly with tenofovir disoproxil fumarate (TDF)-containing antiretroviral regimens. Although renal proximal tubular dysfunction and phosphaturia is common with TDF, it is unknown whether BMD loss results from inadequate mineralization. We evaluated change in BMD by dual-energy X-ray absorptiometry (DXA) and bone histomorphometry by tetracycline double-labeled transiliac crest biopsies in young men living with HIV before (n = 20) and 12 months after (n = 16) initiating TDF/lamivudine/efavirenz. We examined relationships between calciotropic hormones, urinary phosphate excretion, pro-inflammatory and pro-resorptive cytokines, and bone remodeling-related proteins with changes in BMD and histomorphometry. Mean age was 29.6 ± 5.5 years, with mean CD4 + T cell count of 473 ± 196 cells/mm3 . At baseline, decreased bone formation rate and increased mineralization lag time were identified in 16 (80%) and 12 (60%) patients, respectively. After 12 months, we detected a 2% to 3% decrease in lumbar spine and hip BMD by DXA. By histomorphometry, we observed no change in bone volume/total volume (BV/TV) and trabecular parameters, but rather, increases in cortical thickness, osteoid volume, and osteoblast and osteoclast surfaces. We did not observe significant worsening of renal phosphate excretion or mineralization parameters. Increases in PTH correlated with decreased BMD but not histomorphometric parameters. Overall, these data suggest abnormalities in bone formation and mineralization occur with HIV infection and are evident at early stages. With TDF-containing antiretroviral therapy (ART), there is an increase in bone remodeling, reflected by increased osteoblast and osteoclast surfaces, but a persistence in mineralization defect, resulting in increased osteoid volume. © 2019 American Society for Bone and Mineral Research.
Related Concept Videos
 01:25
Role of Vitamins in Maintaining Bone Health
Vitamin A
Vitamin A is involved in the process of bone remodeling. Retinoic acid, the active metabolite of Vitamin A, has nuclear receptors in osteoblasts and osteoclasts, which are involved in bone remodeling.
Vitamin B12
Vitamin B12 acts as a cofactor during the formation of osteoblast-related proteins, such as osteocalcin. Vitamin B12 plays a role...
 01:29
Bone Formation by Intramembranous Ossification
The process begins when mesenchymal cells in the embryonic skeleton gather together and differentiate into osteogenic cells, which then develop into ...
 01:24
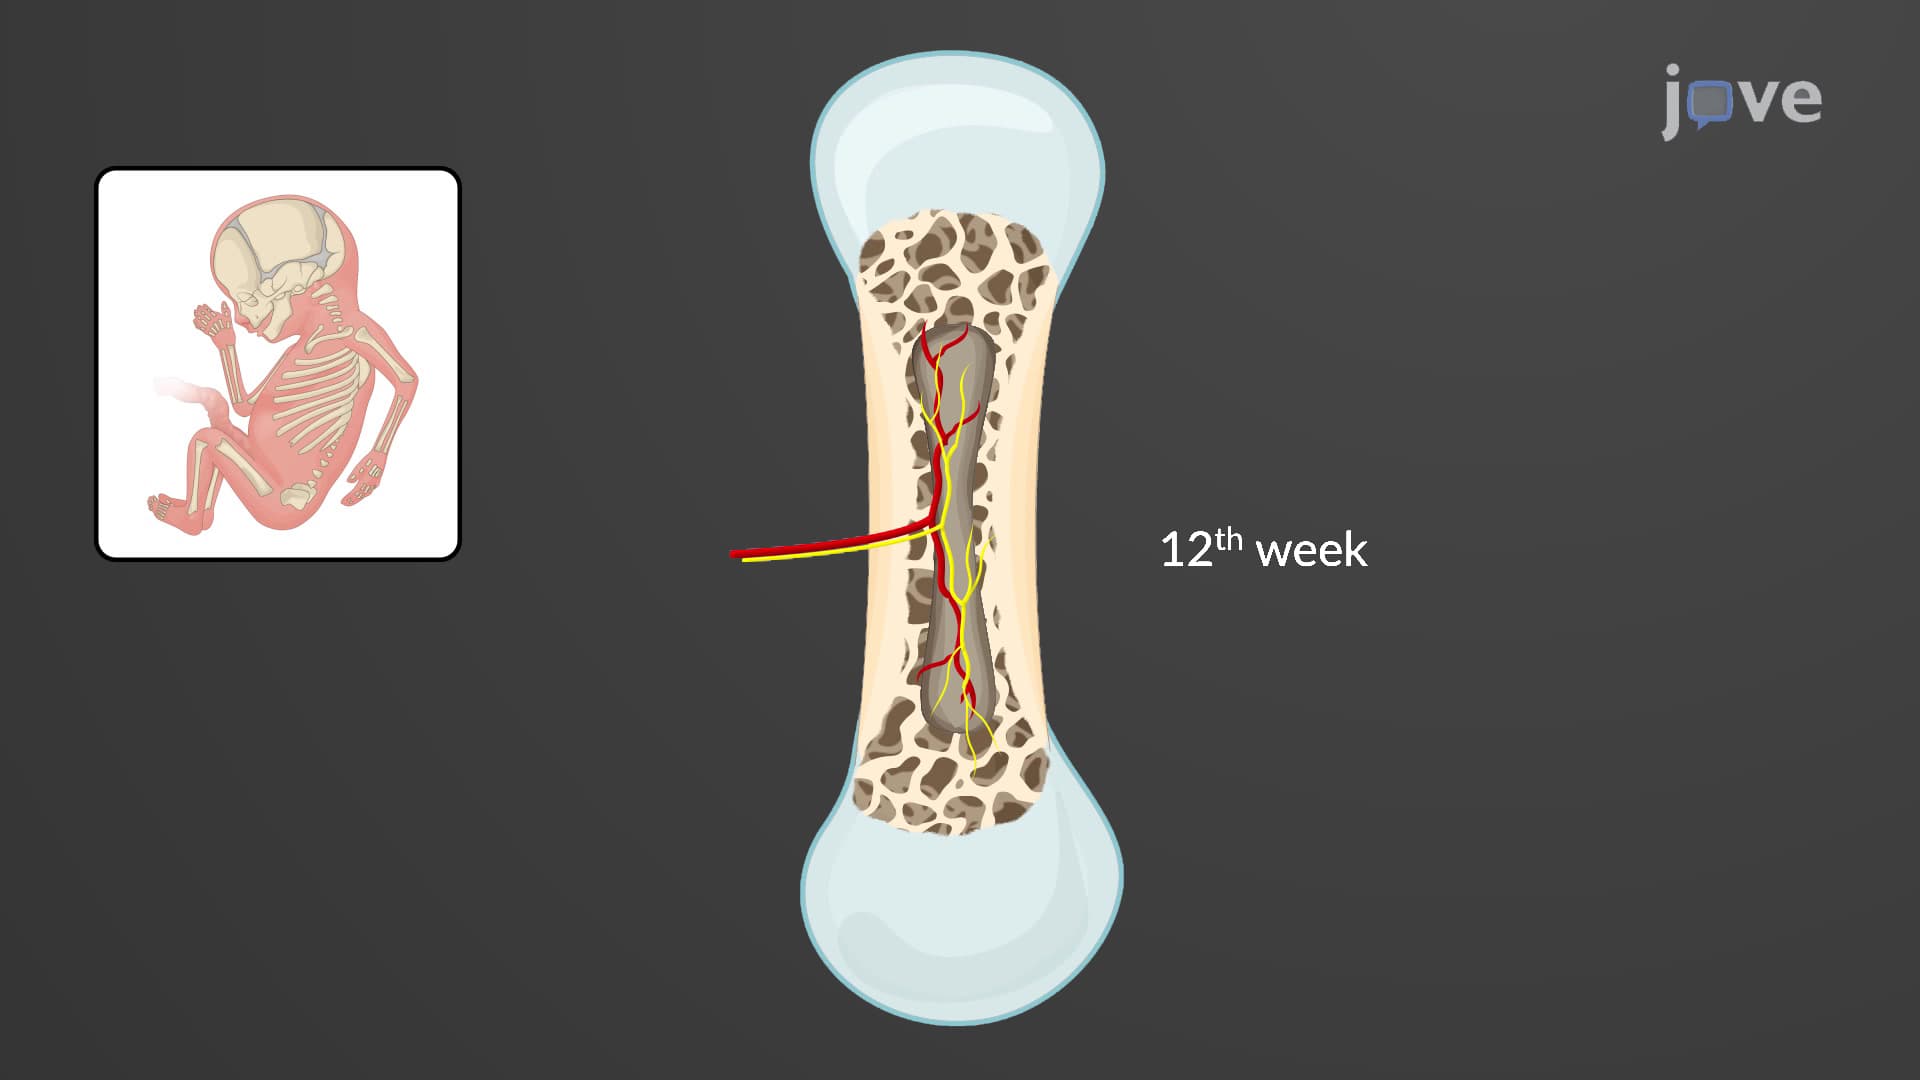
Bone Formation by Endochondral Ossification
 01:17
Increased pulse rate
Many factors can elevate the risk of developing tachycardia. These include advanced age, a family history of arrhythmias, and an...
 01:09
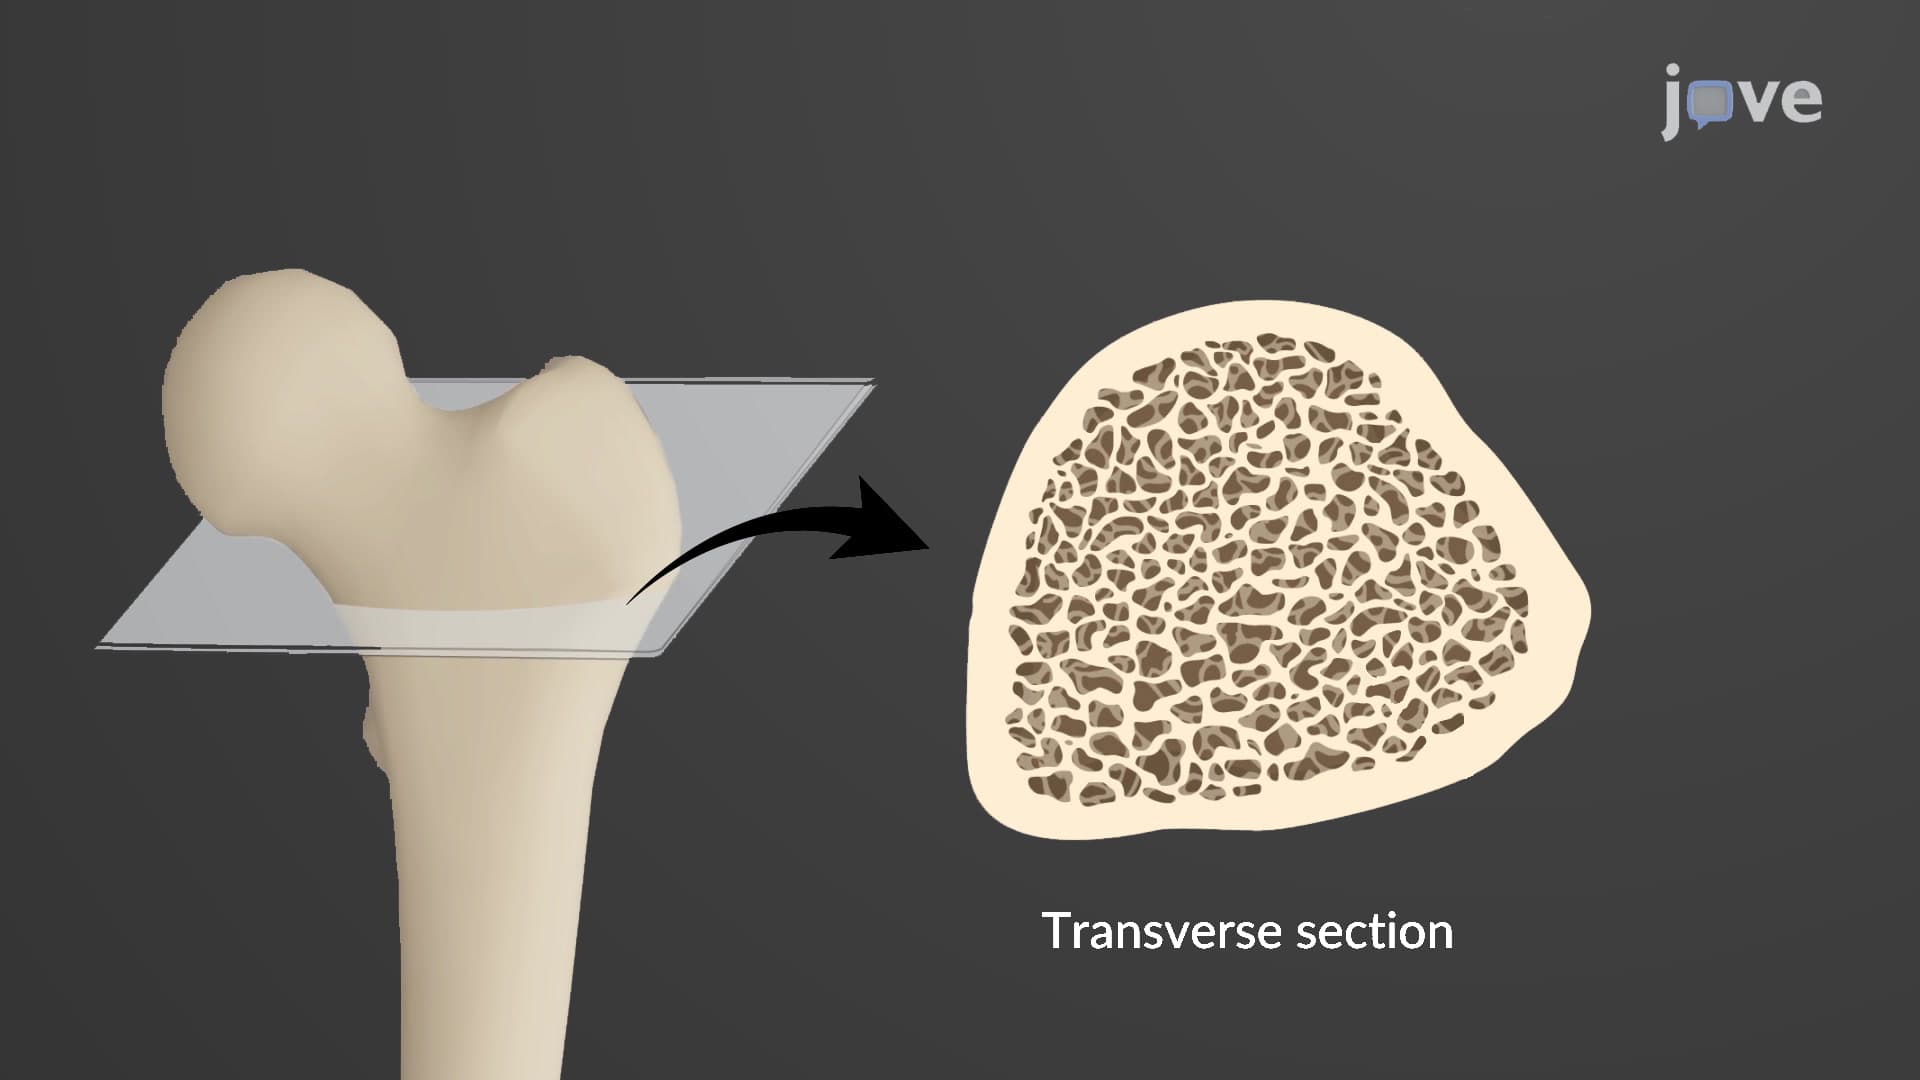
Spongy Bone
Spongy bone is more porous, and less dense compared to compact bone. It is composed of concentric lamellae that are arranged irregularly to form the trabecular network. In some bones, the spaces between trabeculae contain red marrow, where...
 01:27
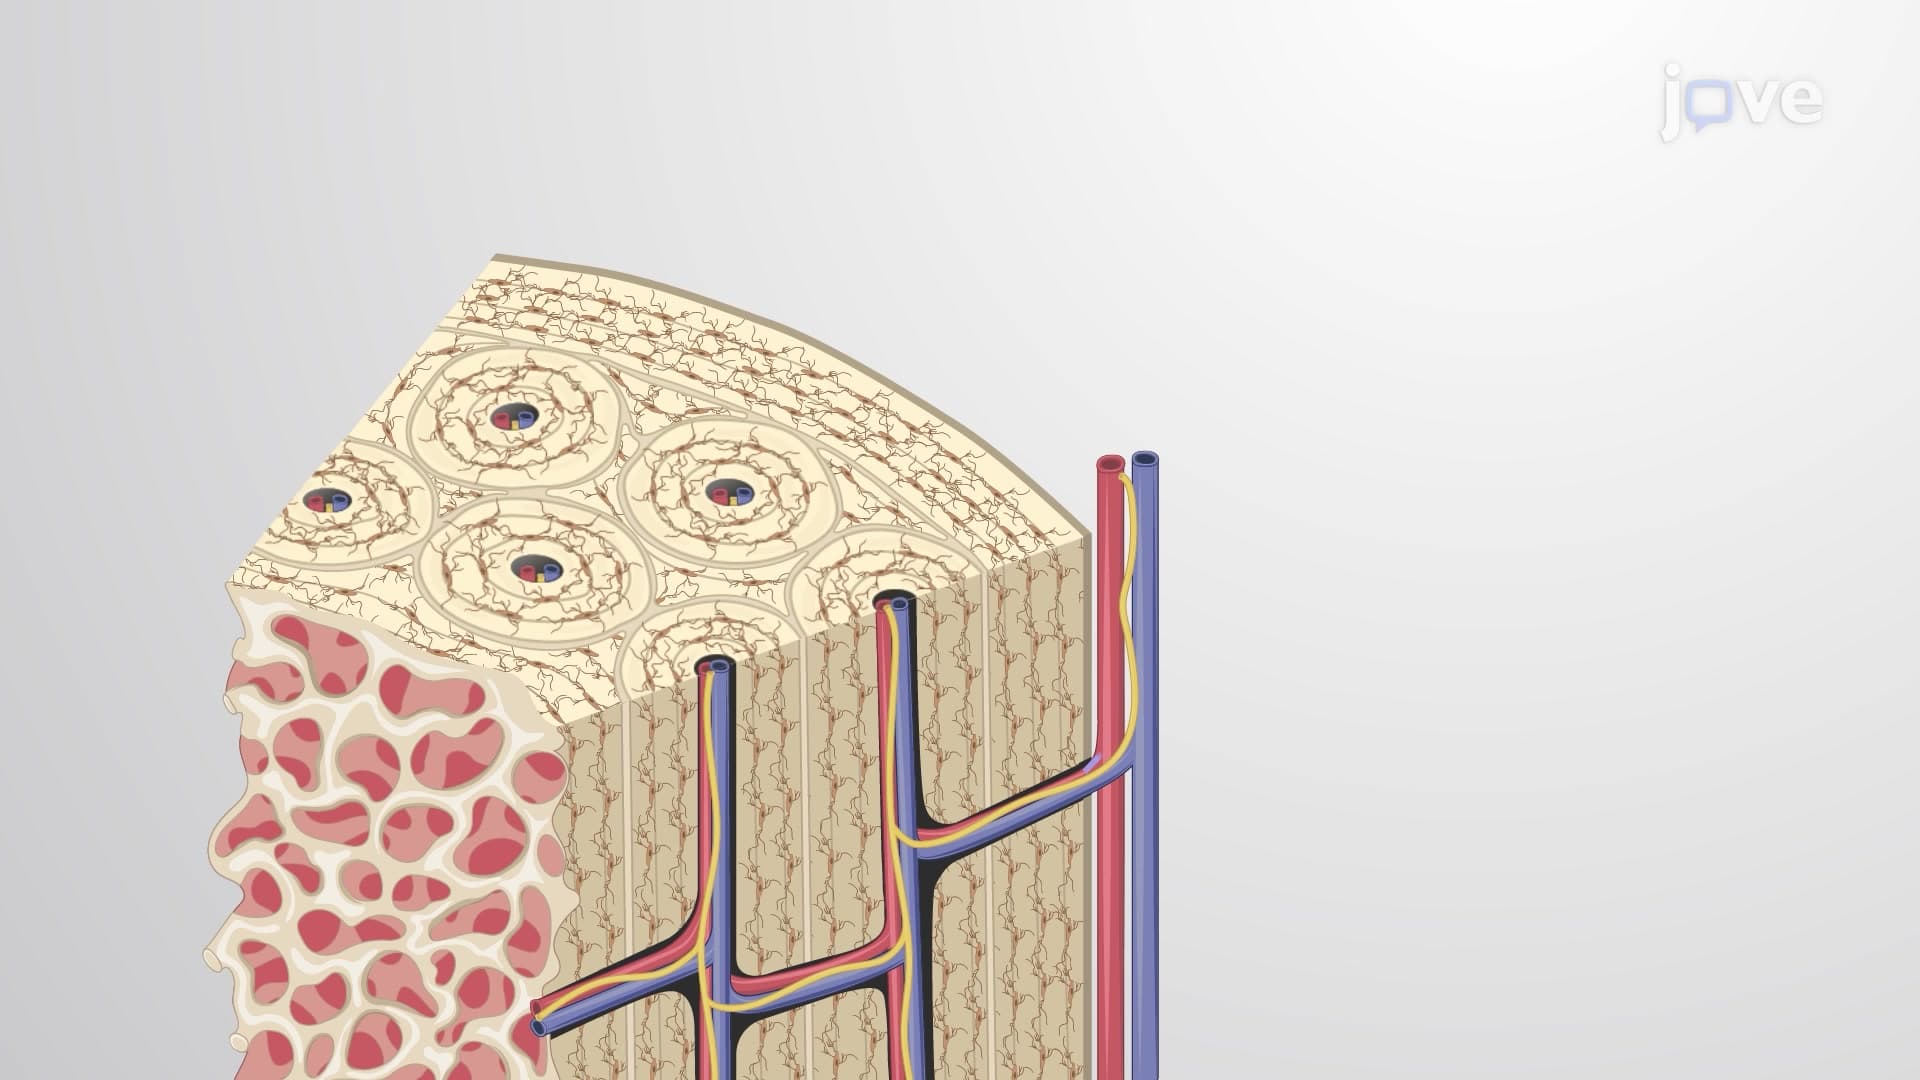
Compact Bone
Compact bone, also called cortical bone, is the denser, stronger of the two types of bone tissue. It is found under the periosteum and in the diaphyses of long bones, where it provides support and protection. The microscopic structural unit of compact bone is called an osteon, or haversian system. Each osteon is composed of concentric rings of calcified...