Related Experiment Video
Updated: Jan 22, 2026
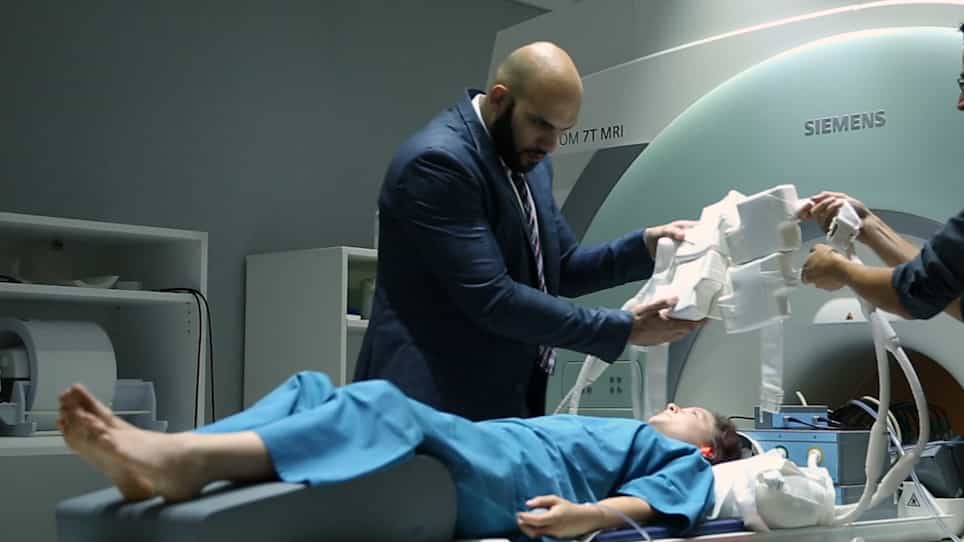
Cardiac Magnetic Resonance Imaging at 7 Tesla
Published on: January 6, 2019
Early effects of kidney transplantation on the heart - A cardiac magnetic resonance multi-parametric study
Manvir K Hayer1, Ashwin Radhakrishnan1, Anna M Price1
1Birmingham Cardiorenal Group, Institute of Cardiovascular Sciences, University of Birmingham, United Kingdom of Great Britain and Northern Ireland.

Insights
Native myocardial T1 times are elevated in end-stage kidney disease (ESKD) and remain stable after kidney transplantation, suggesting they are a reliable marker for diffuse interstitial myocardial fibrosis (DIF) in chronic kidney disease (CKD).
Area of Science:
- Cardiovascular Imaging
- Nephrology
- Radiology
Background:
- Elevated native myocardial T1 times in chronic kidney disease (CKD) may indicate diffuse interstitial myocardial fibrosis (DIF) or edema/inflammation.
- Gadolinium-based contrast agents (GBCA) use is limited in end-stage kidney disease (ESKD) due to nephrogenic systemic fibrosis concerns, hindering extracellular volume (ECV) measurement.
- Kidney transplantation offers a unique window to assess myocardial changes as volume status normalizes.
Purpose of the Study:
- To evaluate the stability of myocardial T1 and T2 times before and after kidney transplantation.
- To compare pre- and post-transplant myocardial T1/T2 times with ECV measurements.
- To determine if native T1 times can reliably assess diffuse interstitial myocardial fibrosis (DIF) in CKD patients.
Main Methods:
- Serial cardiovascular magnetic resonance imaging (CMR) including T1 and T2 mapping was performed on 24 ESKD patients.
- ECV was measured using GBCA post-transplantation in patients with eGFR >30 ml/min/1.73 m².
- Eighteen age- and sex-matched healthy controls underwent single-timepoint CMR for comparison.
Main Results:
- ESKD patients exhibited higher ECV and T2 times compared to controls.
- Post-transplantation, septal T1 times increased, and left ventricular (LV) volumes decreased, while LV mass remained unchanged.
- Myocardial T2 times showed no significant change after transplantation.
Conclusions:
- Elevated ECV and myocardial T1 times in ESKD support DIF as the primary cause, though myocardial edema may contribute.
- The lack of change in T1 and T2 times post-transplantation indicates that native myocardial T1 times are a stable and reliable measure of DIF in CKD.
- This finding supports the use of native T1 mapping for assessing myocardial fibrosis in CKD patients, circumventing GBCA risks.
Abstract:
Increased native myocardial T1 times in chronic kidney disease (CKD) may be due to diffuse interstitial myocardial fibrosis (DIF) or due to interstitial edema/inflammation. Concerns relating to nephrogenic systemic fibrosis with gadolinium-based contrast agents (GBCA) limit their use in end-stage kidney disease (ESKD) to measure extracellular volume (ECV) and characterise myocardial fibrosis. This study aimed to examine stability of myocardial T1 and T2 times before, and within 2 months after kidney transplantation; a time frame when volume status normalises but myocardial remodelling is unlikely to have occurred, and to compare these with ECV using GBCA after transplantation. Twenty-four patients with ESKD underwent serial cardiovascular magnetic resonance imaging, including T1 and T2 mapping. GBCA was administered on follow-up provided eGFR was >30 ml/min/1.73 m2. Eighteen age- and sex-matched controls were studied at one timepoint. ECV (ECV 28 ± 2% vs. 24 ± 2%, p = 0.001) and T2 times were higher in ESKD compared to controls. After transplantation, septal T1 times increased (MOLLI 985 ms ± 25 vs. 1002 ms ± 30, p = 0.014; ShMOLLI 974 ms ± 39 vs. 992 ms ± 33, p = 0.113), LV volumes reduced (LVEDvol indexed 79 ± 24 vs. 63 ± 20 ml/m2, p = 0.005) but LV mass was unchanged (LV mass index 89 g/m2 ± 38 to 83 g/m2 ± 23, p = 0.141). T2 times did not change after transplantation. Both ECV and myocardial T1 times are elevated in ESKD, supporting the theory that elevated T1 times are due to DIF, although a contribution from myocardial edema cannot be fully excluded. The lack of any fall in T1 or T2 times after transplantation suggests that myocardial T1 times are a stable measure of DIF in CKD.
Related Concept Videos
 01:28
Kidney Transplant I: Introduction
 01:27
Imaging Studies IV: Magnetic Resonance Imaging
 01:24
Magnetic Resonance Imaging
 01:26
Kidney Transplant II: Surgical Procedure
 01:18
Physiology of the Heart: The Cardiac Cycle
Diastole: The Relaxation Phase
During diastole, all four heart chambers relax. The atrioventricular (AV) valves open, and the semilunar valves close. This phase sees the lowest chamber pressures, promoting ventricular filling. Venous blood enters the heart through the...
 01:19
Cardiac Output I:Effect of Heart Rate on Cardiac Output
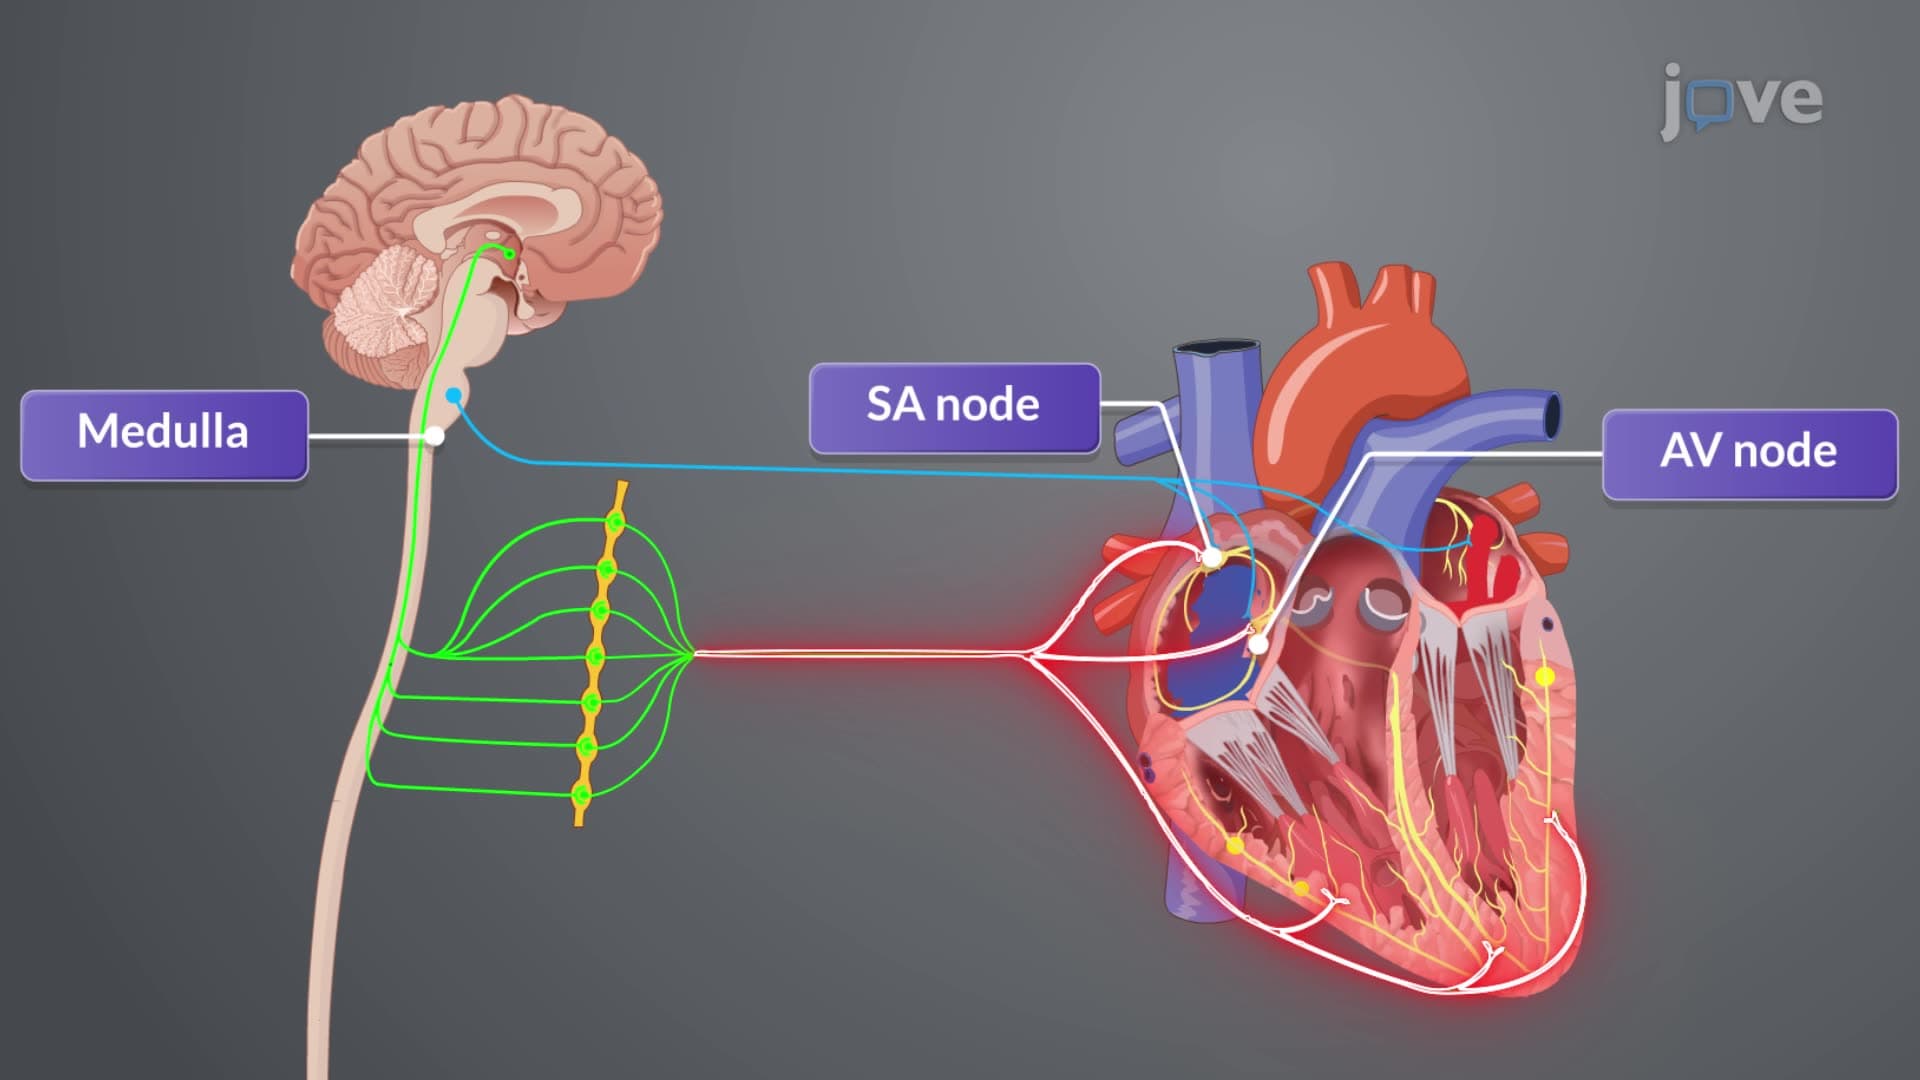
Cardiac output (CO) refers to the total amount of blood ejected by one of the ventricles in liters per minute (L/min). In a resting adult, CO ranges from 5 to 6 L/min, adjusting according to the body's metabolic requirements.
Effect of Heart Rate on Cardiac Output
Cardiac output adapts to metabolic demands during stress, physical activity, or illness. The autonomic nervous system regulates heart rate via the sinoatrial node. The parasympathetic nervous system decreases heart...