Related Experiment Video
Updated: Jan 22, 2026

Transradial Access Chemoembolization for Hepatocellular Carcinoma Patients
Published on: September 20, 2020
Dose escalation in radiotherapy for incomplete transarterial chemoembolization of hepatocellular carcinoma
Hwa Kyung Byun1, Hyun Ju Kim2, Yoo Ri Im1
1Department of Radiation Oncology, Yonsei Cancer Center, Yonsei University College of Medicine, 50-1 Yonsei-ro, Seodaemun-gu, 03722, Seoul, Korea (Republic of).

Purpose:
To investigate the efficacy of radiation dose escalation in patients with hepatocellular carcinoma (HCC) after incomplete transarterial chemoembolization (TACE).
Methods:
This study evaluated retrospective data of 323 HCC patients who received radiotherapy after incomplete TACE from 2001-2016. Radiation dose in biologically effective dose (BED) (α/β = 10) was categorized as <72 Gy (261 patients) and ≥72 Gy (62 patients). Simultaneous integrated boost-intensity modulated radiation therapy (SIB-IMRT) was used significantly more frequently in the high-dose group (64.5% vs. 12.9%; P < 0.001). Local failure-free rate (LFFR), progression-free rate (PFR), and toxicities were compared between the two groups. Additionally, propensity score matching was performed.
Results:
Median follow-up time for patients who were alive at the time of analysis was 47 months (range 18-189 months). Median overall survival after radiotherapy was 14 months. In multivariate analysis, BED ≥72 Gy was an independent predictor of favorable LFFR (hazard ratio [HR] 0.32; 95% confidence interval [CI] 0.14-0.72; P = 0.006) and PFR (HR 0.67; 95% CI 0.45-0.98; P = 0.04). In the propensity score-matched cohort (62 pairs), 1‑year LFFR (94% vs. 81%; P = 0.002), and 1‑year PFR (49% vs. 42%; P = 0.01) were significantly higher in the high-dose group. Treatment-related toxicities were comparable between the high-dose and low-dose groups (classic radiation-induced liver disease: 5.3% [3/57] vs. 13.8% [29/210], P = 0.08; grade 2-4 gastrointestinal bleeding: 3.2% [2/62] vs. 7.3% [19/261], P = 0.39).
Conclusion:
Radiation dose with BED ≥72 Gy improved LFFR and PFR without increasing toxicity. In radiotherapy for incomplete TACE of HCC, dose escalation using SIB-IMRT should be actively considered to improve oncologic outcome.
More Related Videos
 11:38
Voluntary Breath-hold Technique for Reducing Heart Dose in Left Breast Radiotherapy
Published on: July 3, 2014
 09:49
Dual-phase Cone-beam Computed Tomography to See, Reach, and Treat Hepatocellular Carcinoma during Drug-eluting Beads Transarterial Chemo-embolization
Published on: December 2, 2013
Related Concept Videos
 01:43
Incomplete Dominance
 01:21
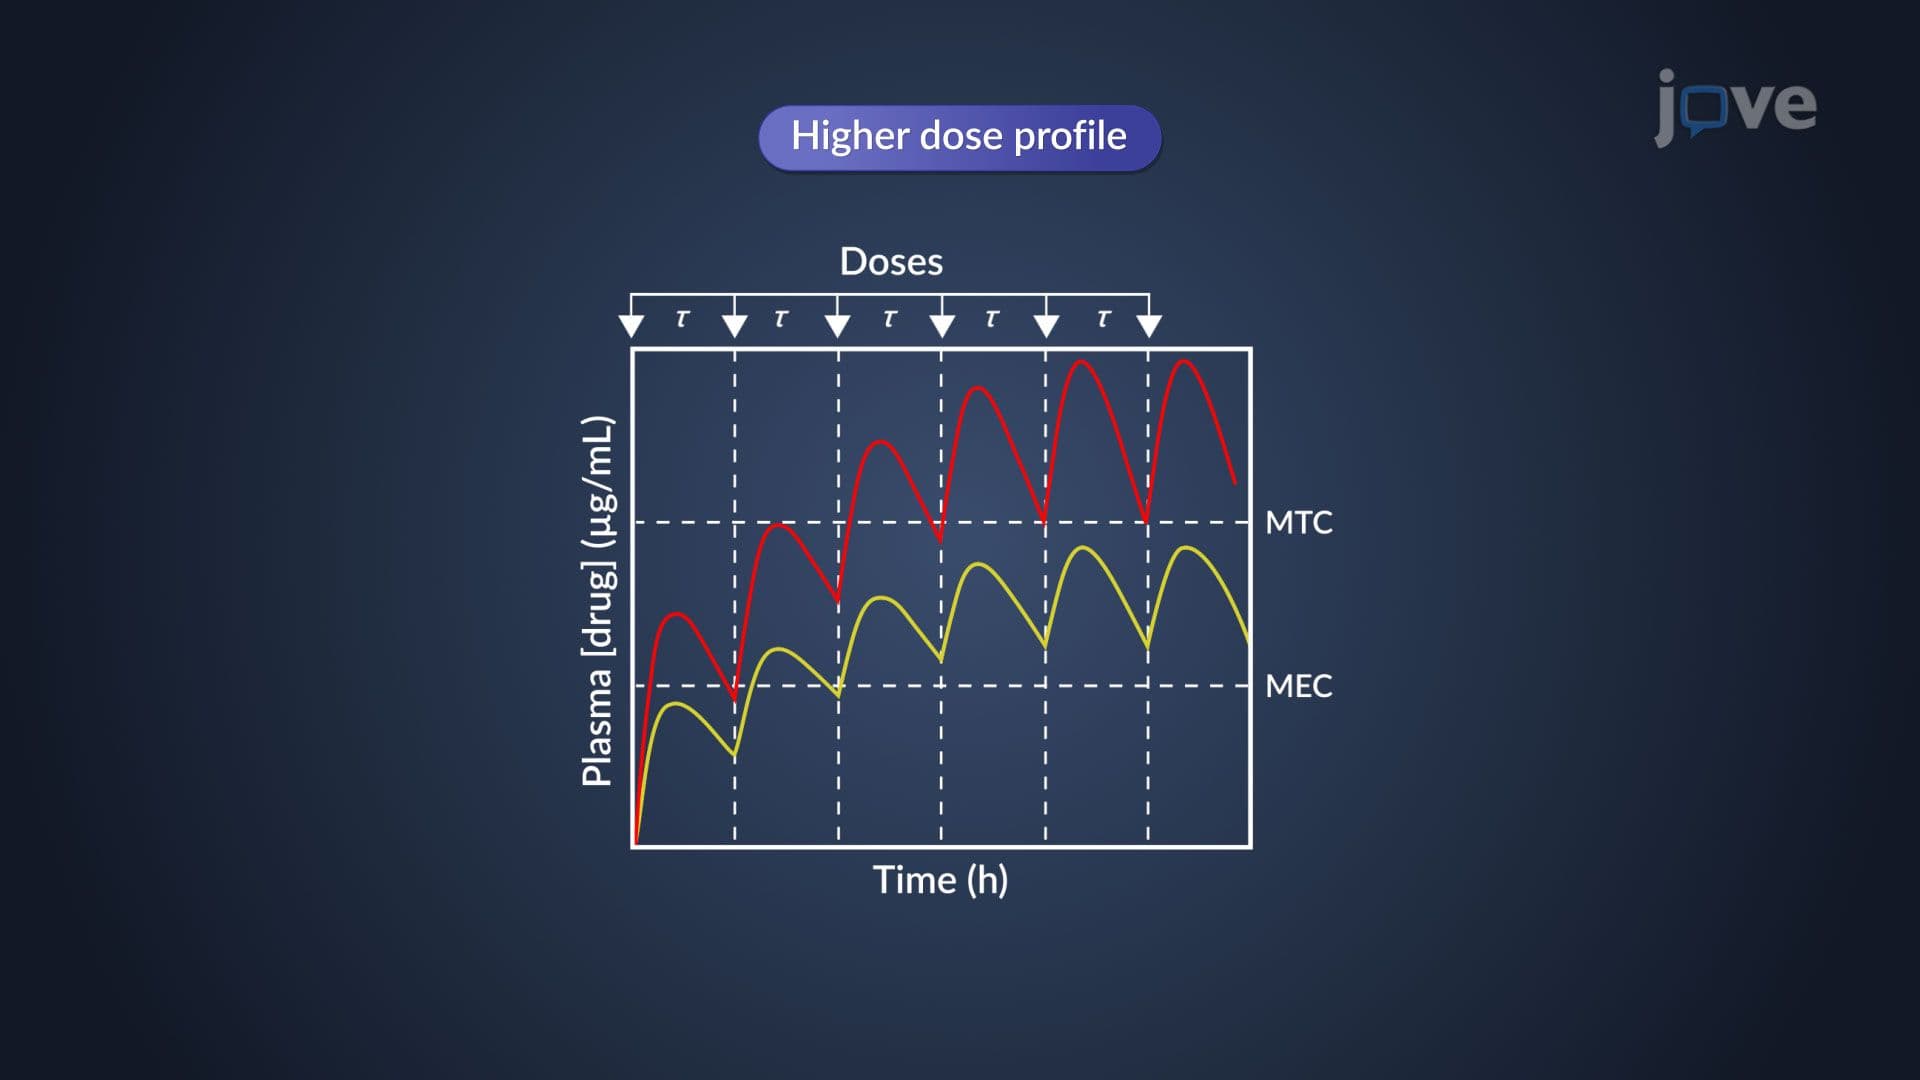
Dose Size and Dosing Frequency: Determination Methods
 01:25
Determination of Multiple Dosing Parameters: Loading and Maintenance Doses
 01:24
Rational Dosage Regimen: Maintenance Dose and Loading Dose
In most cases, drugs are administered repetitively or infused continuously to maintain a steady-state concentration in the body. At a steady...
 01:03
Dose-Response Relationship: Overview
 01:29
Drug Dosing: Infants and Children