Related Experiment Video
Updated: Jan 22, 2026
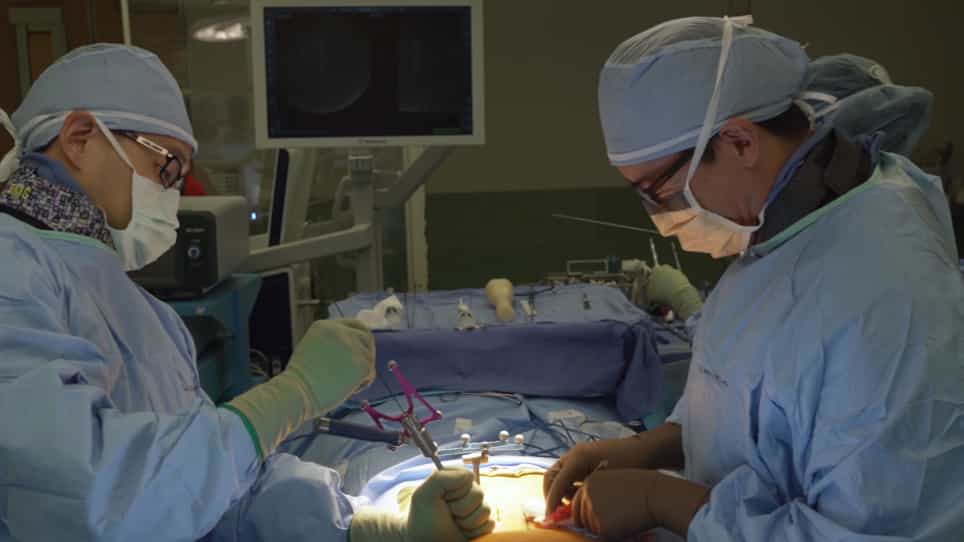

Cone Beam Intraoperative Computed Tomography-based Image Guidance for Minimally Invasive Transforaminal Interbody Fusion
Published on: August 6, 2019
Near-infrared intraoperative imaging for minimally invasive pulmonary metastasectomy for sarcomas
Jarrod D Predina1, Andrew D Newton2, Christopher Corbett1
1Center for Precision Surgery, Perelman School of Medicine at the University of Pennsylvania, Philadelphia, Pa; Division of Thoracic Surgery, Department of Surgery, Perelman School of Medicine at the University of Pennsylvania, Philadelphia, Pa.

Background:
Complete pulmonary metastasectomy for sarcoma metastases provides patients an opportunity for long-term survival and possible cure. Intraoperative localization of preoperatively identified metastases and identification of occult lesions can be challenging. In this trial, we evaluated the efficacy of near-infrared (NIR) intraoperative imaging using second window indocyanine green during metastasectomy to identify known metastases and to detect occult nodules.
Methods:
Thirty patients with pulmonary nodules suspicious for sarcoma metastases were enrolled in an open-label, feasibility study (NCT02280954). All patients received intravenous indocyanine green (5 mg/kg) 24 hours before metastasectomy. Patients 1 through 10 (cohort 1) underwent metastasectomy via thoracotomy to assess fluorescence patterns of nodules detected by traditional methods (preoperative imaging and intraoperative visualization/bimanual palpation). After confirming reliability within cohort 1, patients 11 through 30 (cohort 2) underwent video-assisted thoracic surgery metastasectomy with NIR imaging.
Results:
In cohort 1, 14 out of 16 preoperatively identified pulmonary metastases (87.5%) displayed tumor fluorescence. Nonfluorescent metastases were deeper than fluorescent metastases (2.1 cm vs 1.3 cm; P = .03). Five out of 5 metastases identified during thoracotomy displayed fluorescence. NIR imaging identified 3 additional occult lesions in this cohort. In cohort 2, 33 out of 37 known pulmonary metastases (89.1%) displayed fluorescence. Nonfluorescent tumors were deeper than 2.0 cm (P = .007). NIR imaging identified 24 additional occult lesions. Of 24 occult lesions, 21 (87.5%) were confirmed metastases and the remaining 3 nodules were lymphoid aggregates.
Conclusions:
NIR intraoperative imaging with indocyanine green (5 mg/kg and 24 hours before surgery) localizes known sarcoma pulmonary metastases and identifies otherwise occult lesions. This approach may be a useful intraoperative adjunct to improve metastasectomy.
More Related Videos


Related Concept Videos
 01:03
Rous Sarcoma Virus (RSV) and Cancer
RSV is a retrovirus that contains two copies of a plus-strand RNA genome. Its genome consists of four main open...
 01:29
Pulmonary Tuberculosis I
Causative Organism
The primary infectious agent causing tuberculosis is Mycobacterium tuberculosis, a slow-growing, acid-fast, aerobic rod that exhibits sensitivity to heat and ultraviolet light. Instances of Mycobacterium bovis and Mycobacterium avium contributing to the development of TB infection are rare.
Mode of...
 01:28
Pulmonary Tuberculosis II
Here is a detailed explanation of its pathophysiology:
Transmission: The process begins when a person inhales droplet nuclei containing M. tuberculosis. These are typically released into the air when an individual with pulmonary or...
 01:28
Pulmonary Tuberculosis V
Latent tuberculosis infection occurs when TB bacteria are present in a person's body, but are not causing illness or symptoms. It is not contagious, and preventive treatment is crucial to avoid the...
 01:09
Infrared (IR) Spectroscopy: Overview
Different compounds display unique properties due to their...
 01:17
Other Pulmonary Disorders