Related Experiment Video
Updated: Jan 22, 2026


Measuring the Functional Abilities of Children Aged 3-6 Years Old with Observational Methods and Computer Tools
Published on: June 20, 2020
Comparison of 3 Methods to Assess Occupational Sevoflurane Exposure in Abdominal Surgeons: A Single-Center
Jennifer Herzog-Niescery1, Hans-Martin Seipp2, Martin Bellgardt1
1From the Department of Anesthesiology, Ruhr-University Bochum, St Josef Hospital, Bochum, Germany.

Background:
Studies demonstrated that operating room personnel are exposed to anesthetic gases such as sevoflurane (SEVO). Measuring the gas burden is essential to assess the exposure objectively. Air pollution measurements and the biological monitoring of urinary SEVO and its metabolite hexafluoroisopropanol (HFIP) are possible approaches. Calculating the mass of inhaled SEVO is an alternative, but its predictive power has not been evaluated. We investigated the SEVO burdens of abdominal surgeons and hypothesized that inhaled mass calculations would be better suited than pollution measurements in their breathing zones (25 cm around nose and mouth) to estimate urinary SEVO and HFIP concentrations. The effects of potentially influencing factors were considered.
Methods:
SEVO pollution was continuously measured by photoacoustic gas monitoring. Urinary SEVO and HFIP samples, which were collected before and after surgery, were analyzed by a blinded environmental toxicologist using the headspace gas chromatography-mass spectrometry method. The mass of inhaled SEVO was calculated according to the formula mVA = cVA·(Equation is included in full-text article.)·t·ρ VA aer. (mVA: inhaled mass; cVA: volume concentration; (Equation is included in full-text article.): respiratory minute volume; t: exposure time; and ρ VA aer.: gaseous density of SEVO). A linear multilevel mixed model was used for data analysis and comparisons of the different approaches.
Results:
Eight surgeons performed 22 pancreatic resections. Mean (standard deviation [SD]) SEVO pollution was 0.32 ppm (0.09 ppm). Urinary SEVO concentrations were below the detection limit in all samples, whereas HFIP was detectable in 82% of the preoperative samples in a mean (SD) concentration of 8.53 µg·L (15.53 µg·L; median: 2.11 µg·L, interquartile range [IQR]: 4.58 µg·L) and in all postoperative samples (25.42 µg·L [21.39 µg·L]). The mean (SD) inhaled SEVO mass was 5.67 mg (2.55 mg). The postoperative HFIP concentrations correlated linearly to the SEVO concentrations in the surgeons' breathing zones (β = 216.89; P < .001) and to the calculated masses of inhaled SEVO (β = 4.17; P = .018). The surgeon's body mass index (BMI), age, and the frequency of surgeries within the last 24 hours before study entry did not influence the relation between HFIP concentration and air pollution or inhaled mass, respectively.
Conclusions:
The biological SEVO burden, expressed as urinary HFIP concentration, can be estimated by monitoring SEVO pollution in the personnel's individual breathing zone. Urinary SEVO was not an appropriate biomarker in this setting.
More Related Videos


Related Concept Videos
 01:11
Observational Studies
There are three types of observational studies – Prospective, retrospective, and cross-sectional.
Prospective Study
Prospective studies, also known as longitudinal or cohort studies, are carried out by collecting future data from groups sharing similar characteristics. One...
 01:21
Pilot and Numeric Relaying
 02:57
The Sense of Self: Reflected Self-Appraisal and Social Comparison
 02:33
Lattice Centering and Coordination Number
Types of Unit Cells
Imagine taking a large number of identical...
 01:08
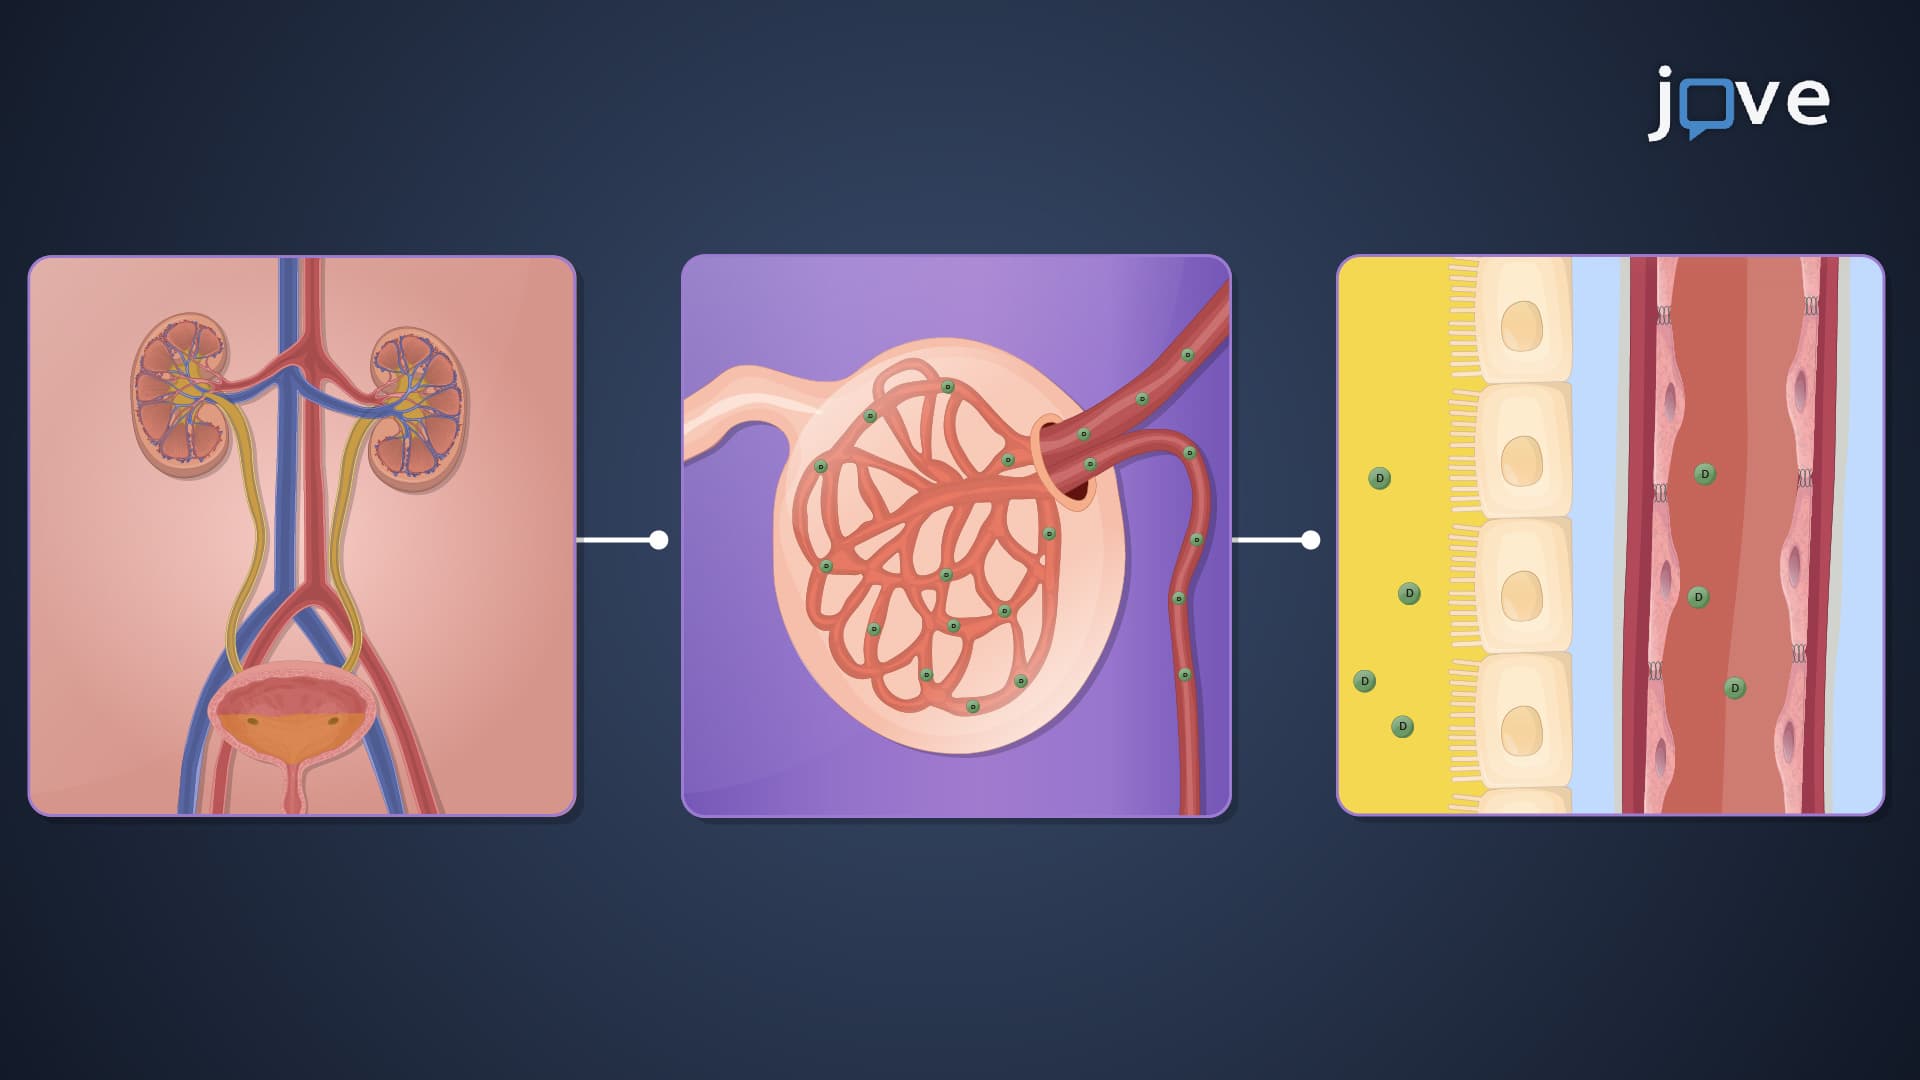
Renal Drug Clearance: Comparison Between Renal Excretion Methods
Renal clearance is often associated with the renal glomerular filtration rate (GFR), which represents the rate at which plasma is filtered through the glomeruli in the kidney. When drug reabsorption is minimal and there is no active secretion, renal clearance is closely related to the...
 02:30
Naturalistic Observations