Related Experiment Video
Updated: Jan 22, 2026

The Bionic Clicker Mark I & II
Published on: August 14, 2017
Four Extremity Amputation and Bionic Prosthesis Supply after Disseminated Intravascular Coagulation: A Follow-Up on
Dennis Werner1, Seyed Arash Alawi1
1Department of Plastic, Aesthetic, Hand and Reconstructive Surgery, Hannover Medical School, Hannover, Germany.

Background:
Disseminated intravascular coagulopathy (DIC) is a rare symptom complex that causes embolisms within the microvasculature and extensive necrosis of the skin and the acres. During surgical decision-making, preserving functionally important structures must be weighed against radical debridement. The aim was to analyze functional recovery and quality of life of patients sustaining amputations from disseminated intravascular coagulopathy and supplied with bionic prostheses.
Methods:
A monocentric, retrospective review of patients with disseminated intravascular coagulopathy after sepsis was conducted from 2016 to 2018. After initial reconstruction and intensive care treatment, patients were provided with bionic prosthetic devices. A follow-up survey measuring function and quality of life was performed.
Results:
Three patients (mean: 45 years; median: 50 years) were analyzed. The first necrectomy and amputation were performed, on average, after >4 weeks post-symptom onset. All patients required re-amputation, averaging two or one re-amputations in the right or left upper extremity, respectively, and one in the lower extremities. On average, 12 operations for reconstruction of skin defects were required (x͂=8). On average, patients tolerated their prostheses for 5.67 h per day. Satisfaction metrics were either sufficient (SF-36, x̅=69) or moderate (TAPES-R, x̅=4.7). Physical skills were rated poor to fair (average TAPES-R=2.67).
Conclusion:
Supplying bionic prostheses after DIC yielded sufficient to moderate results. However, prothesis weight, signal transmission disorders, and repeated functional failures were suboptimal. For extensive stump scarring, implantable signal electrodes may improve signal transmission.
More Related Videos
 09:14
Surface Electromyographic Biofeedback as a Rehabilitation Tool for Patients with Global Brachial Plexus Injury Receiving Bionic Reconstruction
Published on: September 28, 2019
 12:01
Techniques for Processing Eyes Implanted With a Retinal Prosthesis for Localized Histopathological Analysis
Published on: August 2, 2013
Related Concept Videos
 01:27
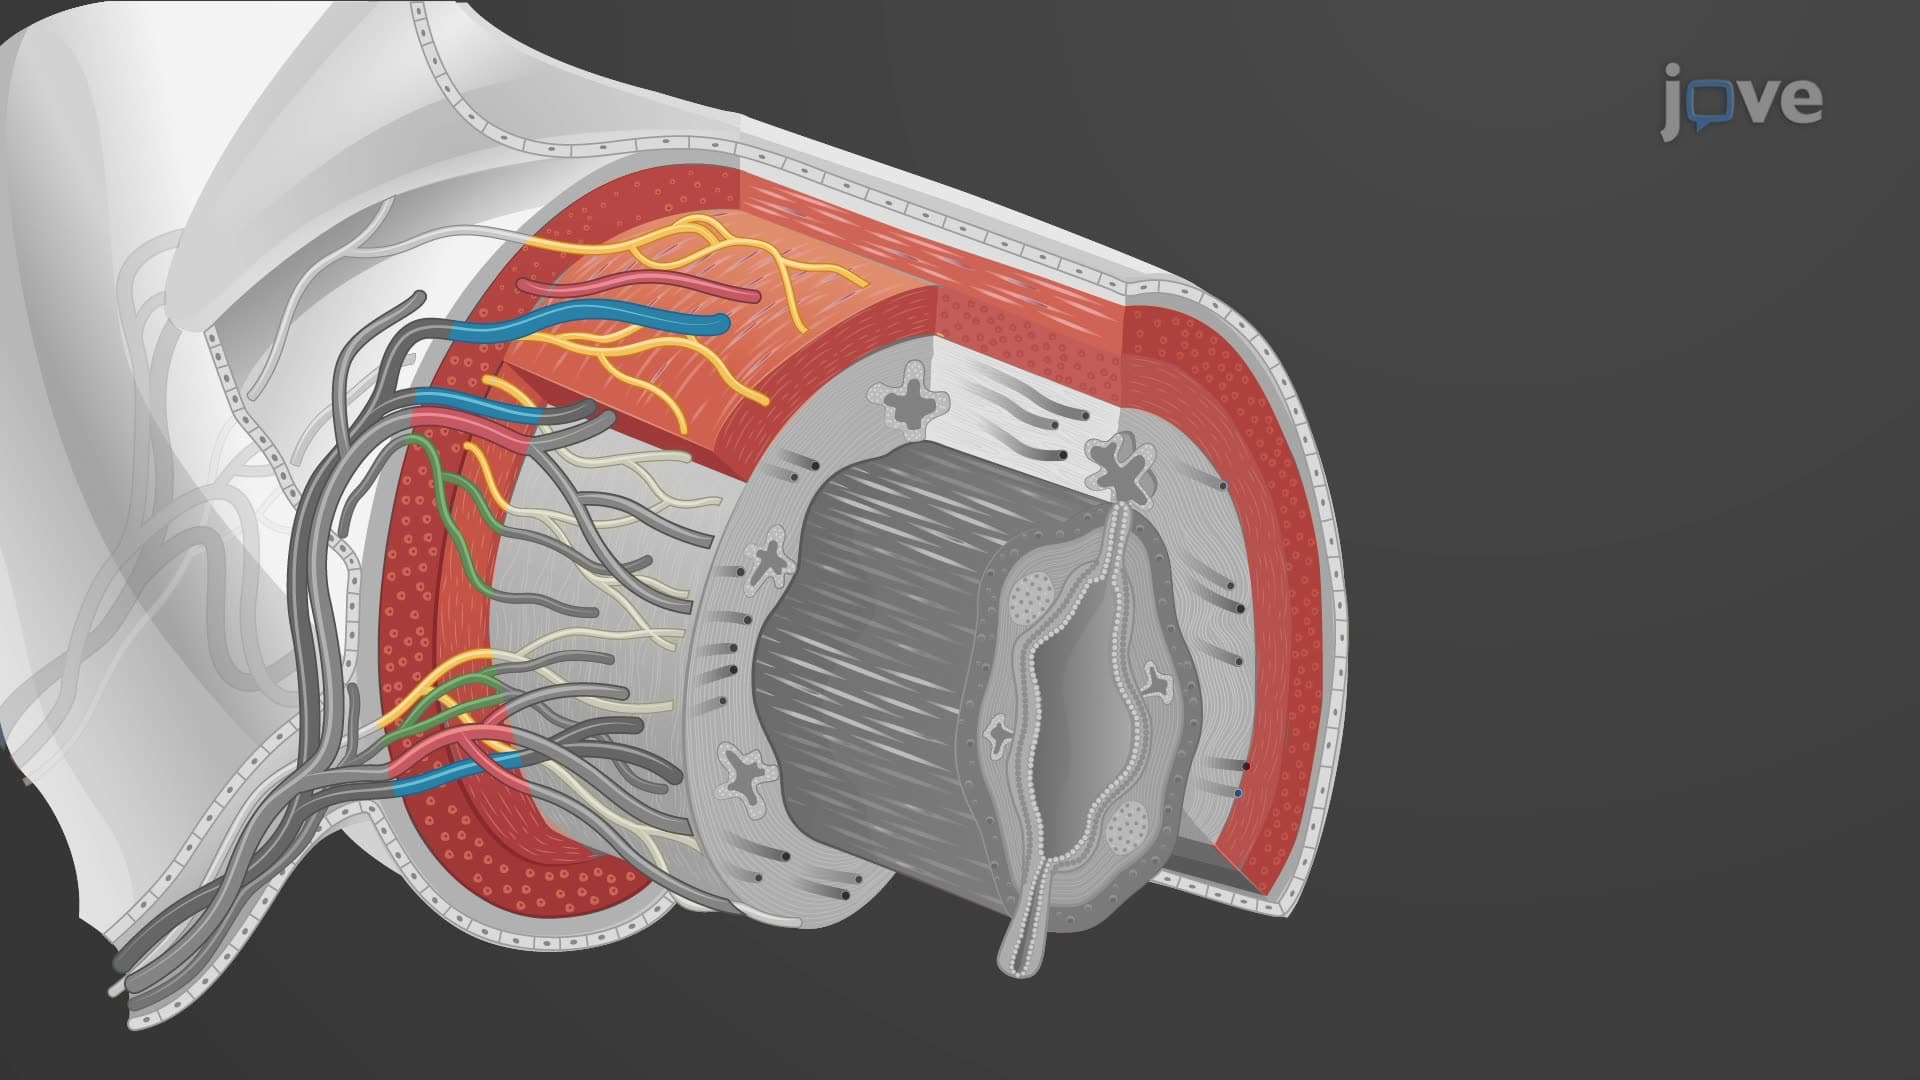
Nerve Supply of the GI Tract
The enteric nervous system consists of two major plexuses: the myenteric plexus (Auerbach's plexus) and the submucosal plexus (Meissner's plexus). These plexuses are located within the layers of...
 01:16
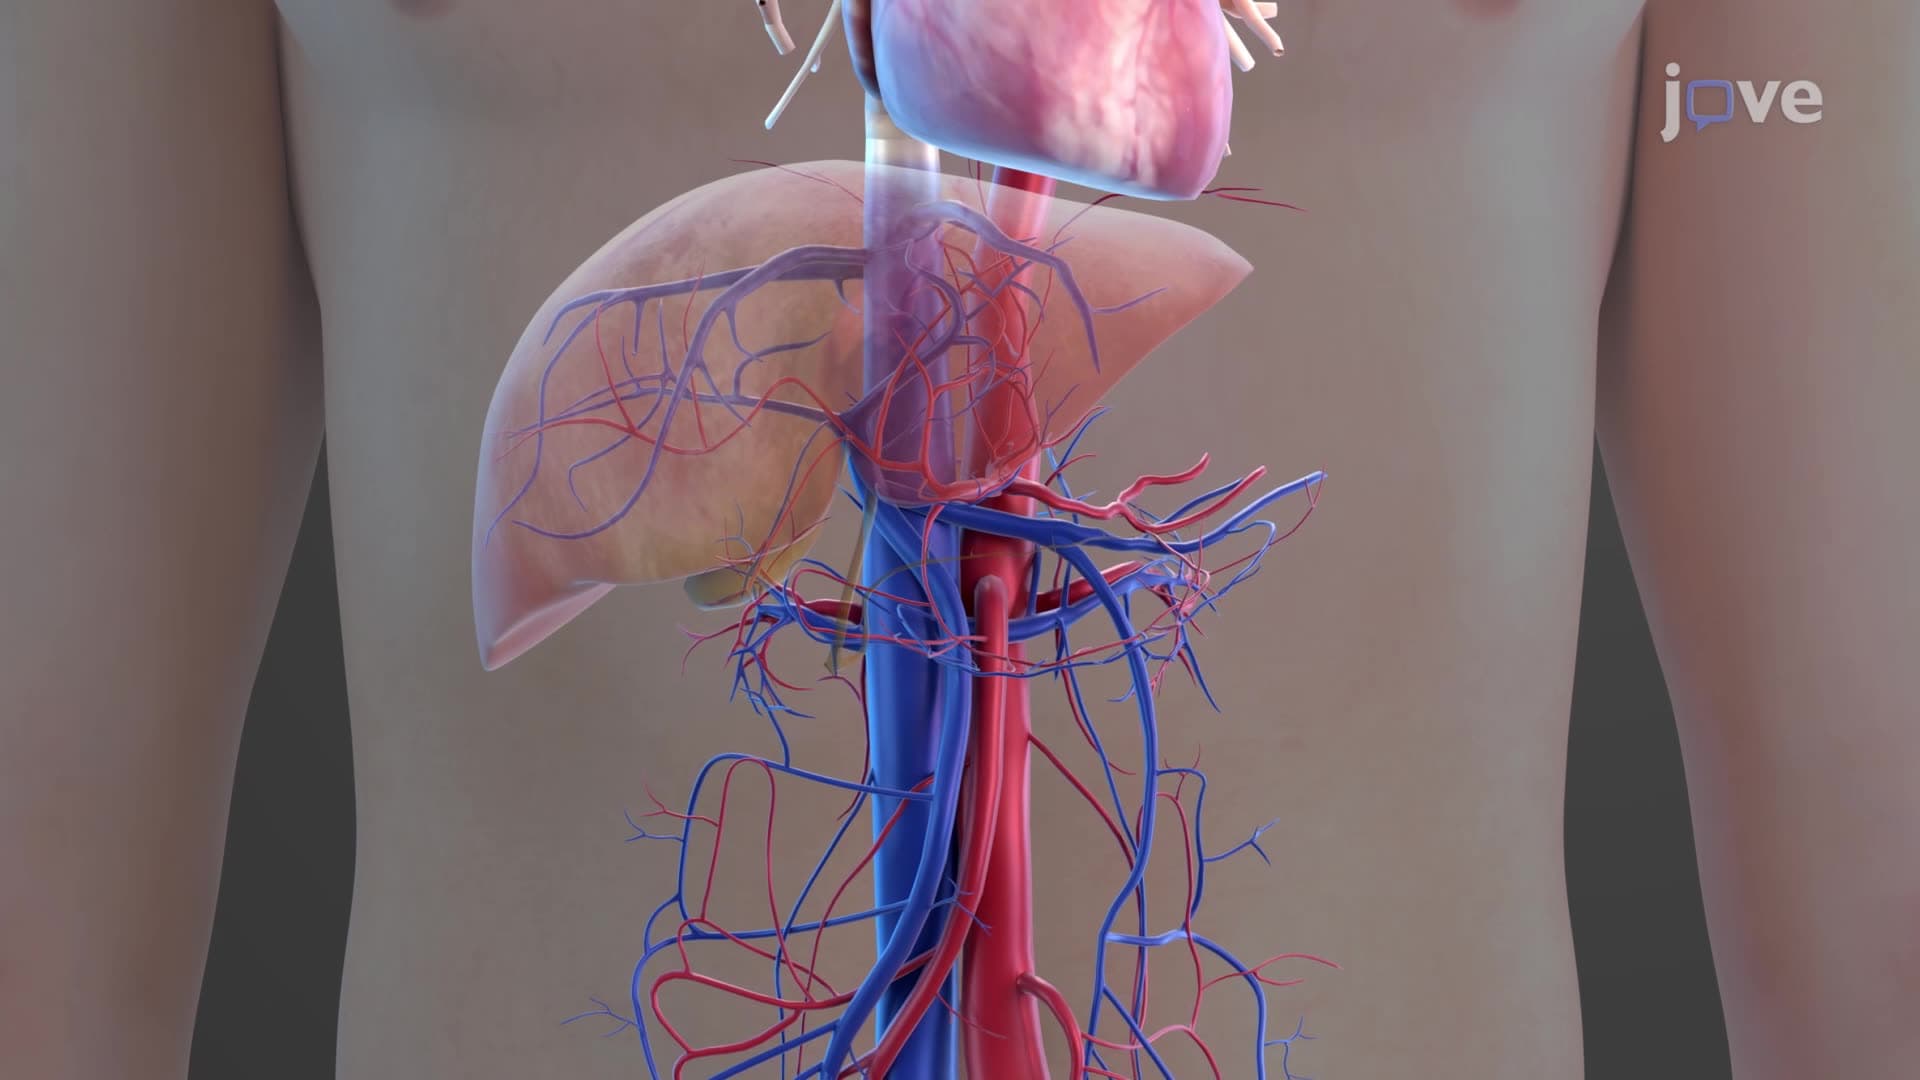
Blood Supply to the Digestive System
Blood Supply to the Digestive System: The splanchnic circulation involves three main arteries: the celiac artery (also known as the celiac trunk) and the superior and inferior mesenteric...
 01:25
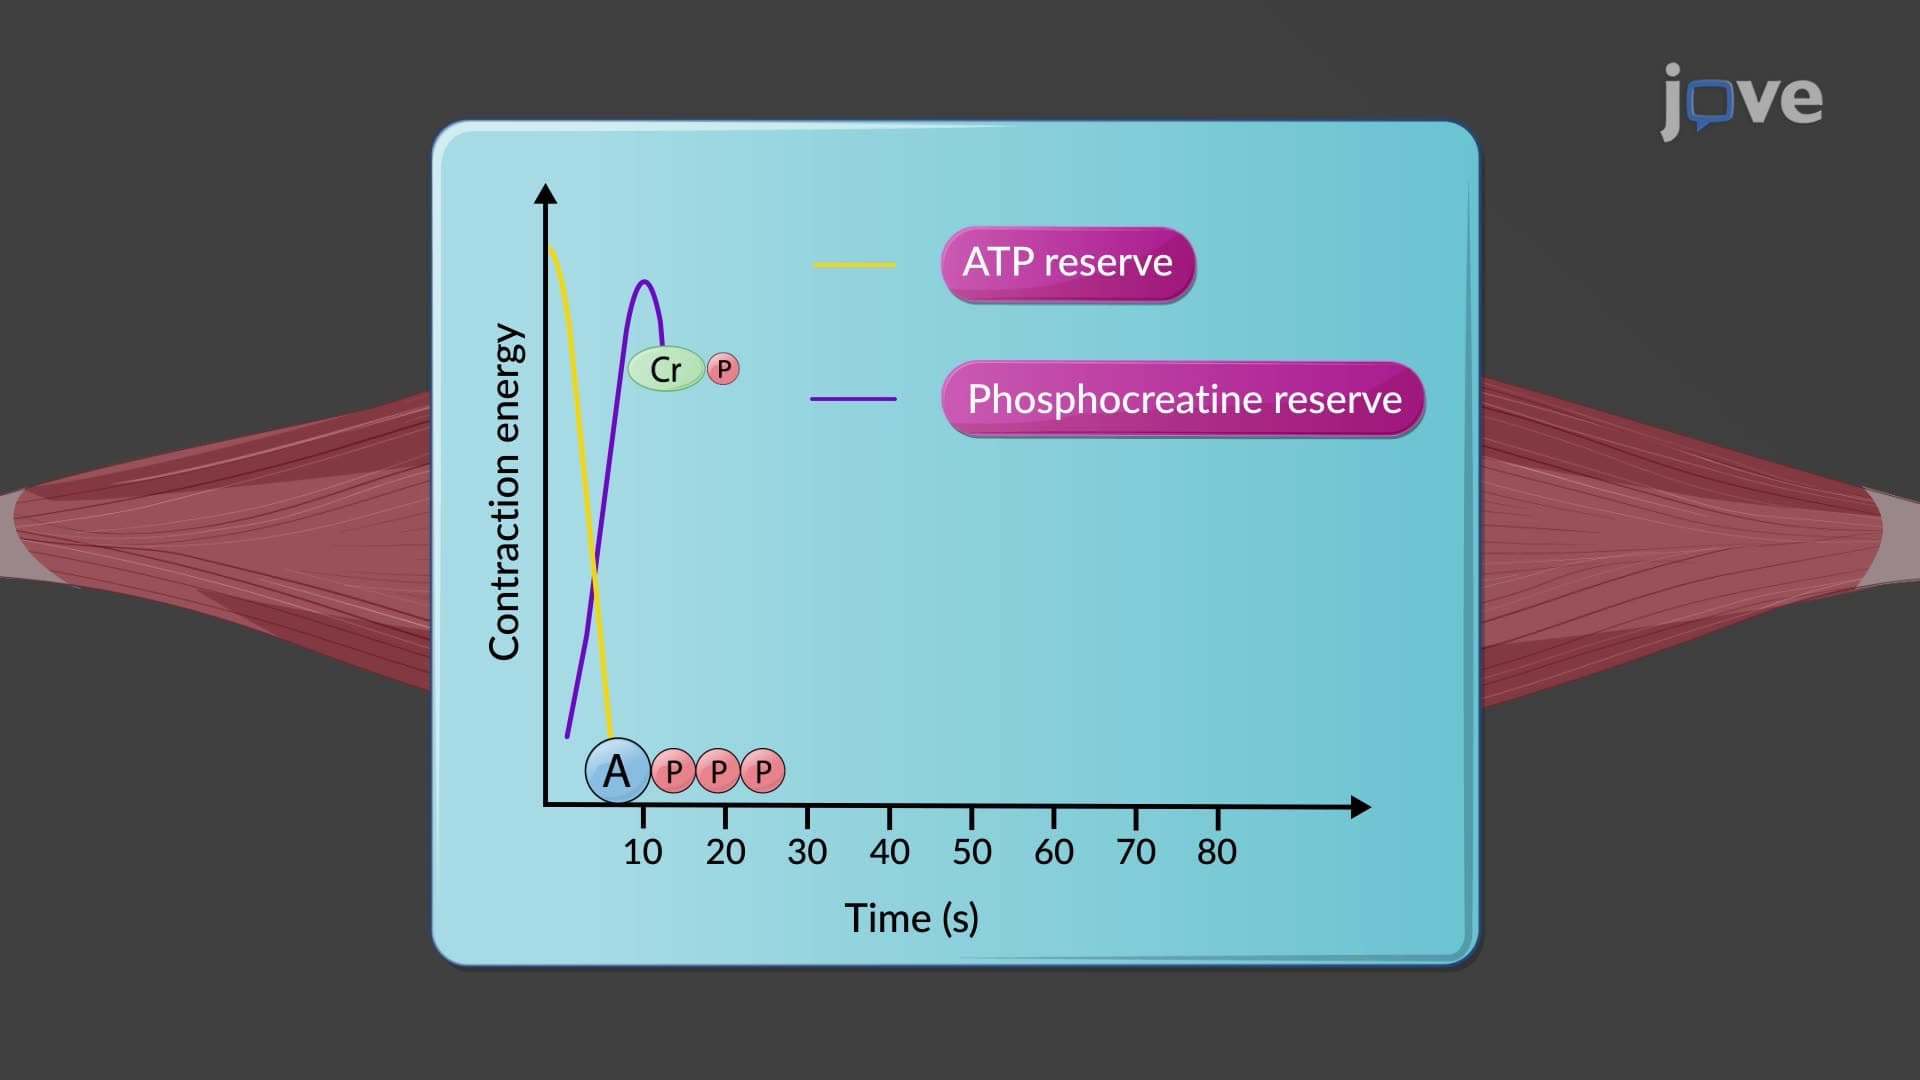
Energy Supply for Muscle Contraction
 01:29
Blood and Nerve Supply to the Bones
Nutrient Artery
The nutrient artery is the main blood vessel that enters the diaphysis via the nutrient foramen. While most long bones have only one nutrient foramen, large bones, such as the femur, may have two. This...
 01:18
Blood and Nerve Supply to the Kidney
Bloody Supply to the Kidneys:
The kidneys receive their blood supply from the renal arteries, which branch off from the abdominal aorta—the main artery supplying the abdomen and lower body. The renal arteries enter the kidneys at the hilum, a notch on the medial side of...
 01:24
Regulation of Angiogenesis and Blood Supply