Related Experiment Video
Updated: Jan 22, 2026
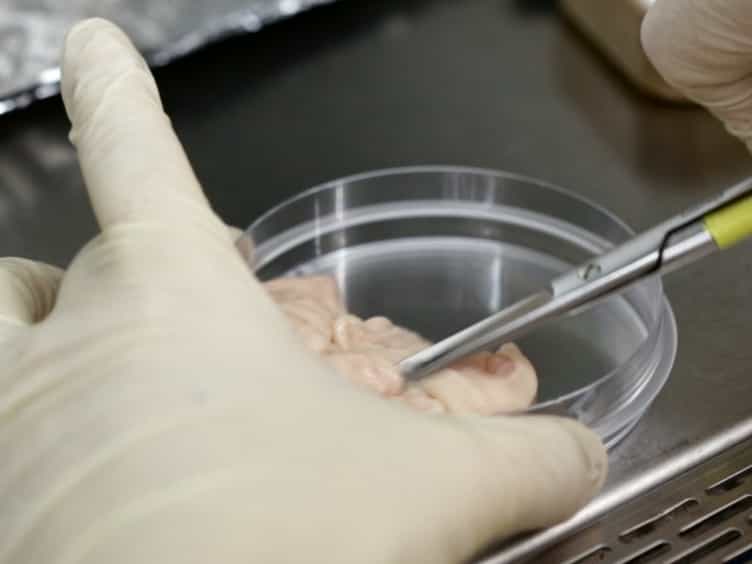

Isolation and Differentiation of Adipose-Derived Stem Cells from Porcine Subcutaneous Adipose Tissues
Published on: March 31, 2016
Differentiating characteristics and evaluating intravenous and subcutaneous immunoglobulin
1Senior Director, Specialty Clinical Services, Managed Health Care Associates, Inc, Florham Park, NJ; President, Immune Globulin National Society.

Clinicians have a range of options for treating patients with disease states that require the use of immunoglobulin (Ig). Traditionally, intravenous immunoglobulin (IVIG) administration has provided effective therapy for a variety of disease states. More recently, subcutaneous immunoglobulin (SCIG) administration has become available for patients with primary immunodeficiencies and chronic inflammatory demyelinating polyneuropathy (CIDP). Ig is used as replacement therapy in patients with primary or secondary immunodeficiencies and has been shown to reduce morbidity due to bacterial infections associated with antibody deficiency. The mechanism of action for use of Ig in the treatment of autoimmune disorders is complex and partially understood, but immunomodulatory effects have been suggested in CIDP and multifocal motor neuropathy. The available IVIG and SCIG products differ in their pharmaceutical properties (eg, pH, osmolality, IgA content, sodium content, and stabilizer), which can affect safety and tolerability in some patients. The pharmacokinetics of Ig also differ based on the route of administration. With IVIG administration every 3 or 4 weeks, peak concentrations are greater and trough concentrations are lower, which can increase the propensity of systemic adverse effects (AEs) and impact tolerability of therapy. SCIG infusions are typically administered more frequently (ie, biweekly, weekly, and even daily based on patient need), resulting in steady state concentrations with fewer fluctuations in Ig plasma levels. The route of administration plays a major role in the types of AEs seen in patients receiving Ig therapy, with systemic AEs associated with IV administration and local reactions more commonly seen with SC administration. By understanding the differences in IVIG and SCIG products, which are not interchangeable, and the patient characteristics that guide product selection, clinicians and managed care providers can better serve patients with immunodeficiency disorders and other disease states.
Clinicians have a range of options for treating patients with disease states that require the use of immunoglobulin (Ig). Traditionally, intravenous immunoglobulin (IVIG) administration has provided effective therapy for a variety of disease states. More recently, subcutaneous immunoglobulin (SCIG) administration has become available for patients with primary immunodeficiencies and chronic inflammatory demyelinating polyneuropathy (CIDP). Ig is used as replacement therapy in patients with primary or secondary immunodeficiencies and has been shown to reduce morbidity due to bacterial infections associated with antibody deficiency. The mechanism of action for use of Ig in the treatment of autoimmune disorders is complex and partially understood, but immunomodulatory effects have been suggested in CIDP and multifocal motor neuropathy. The available IVIG and SCIG products differ in their pharmaceutical properties (eg, pH, osmolality, IgA content, sodium content, and stabilizer), which can affect safety and tolerability in some patients. The pharmacokinetics of Ig also differ based on the route of administration. With IVIG administration every 3 or 4 weeks, peak concentrations are greater and trough concentrations are lower, which can increase the propensity of systemic adverse effects (AEs) and impact tolerability of therapy. SCIG infusions are typically administered more frequently (ie, biweekly, weekly, and even daily based on patient need), resulting in steady state concentrations with fewer fluctuations in Ig plasma levels. The route of administration plays a major role in the types of AEs seen in patients receiving Ig therapy, with systemic AEs associated with IV administration and local reactions more commonly seen with SC administration. By understanding the differences in IVIG and SCIG products, which are not interchangeable, and the patient characteristics that guide product selection, clinicians and managed care providers can better serve patients with immunodeficiency disorders and other disease states.

Related Concept Videos
 01:23
Characteristics of Life
 01:31
Immunoglobulin-like Cell Adhesion Molecules
Ig-CAMs exhibit either homophilic binding (to other Ig-CAMs) or heterophilic binding (to other ligands such as integrins). While most Ig-CAMs...
 01:20
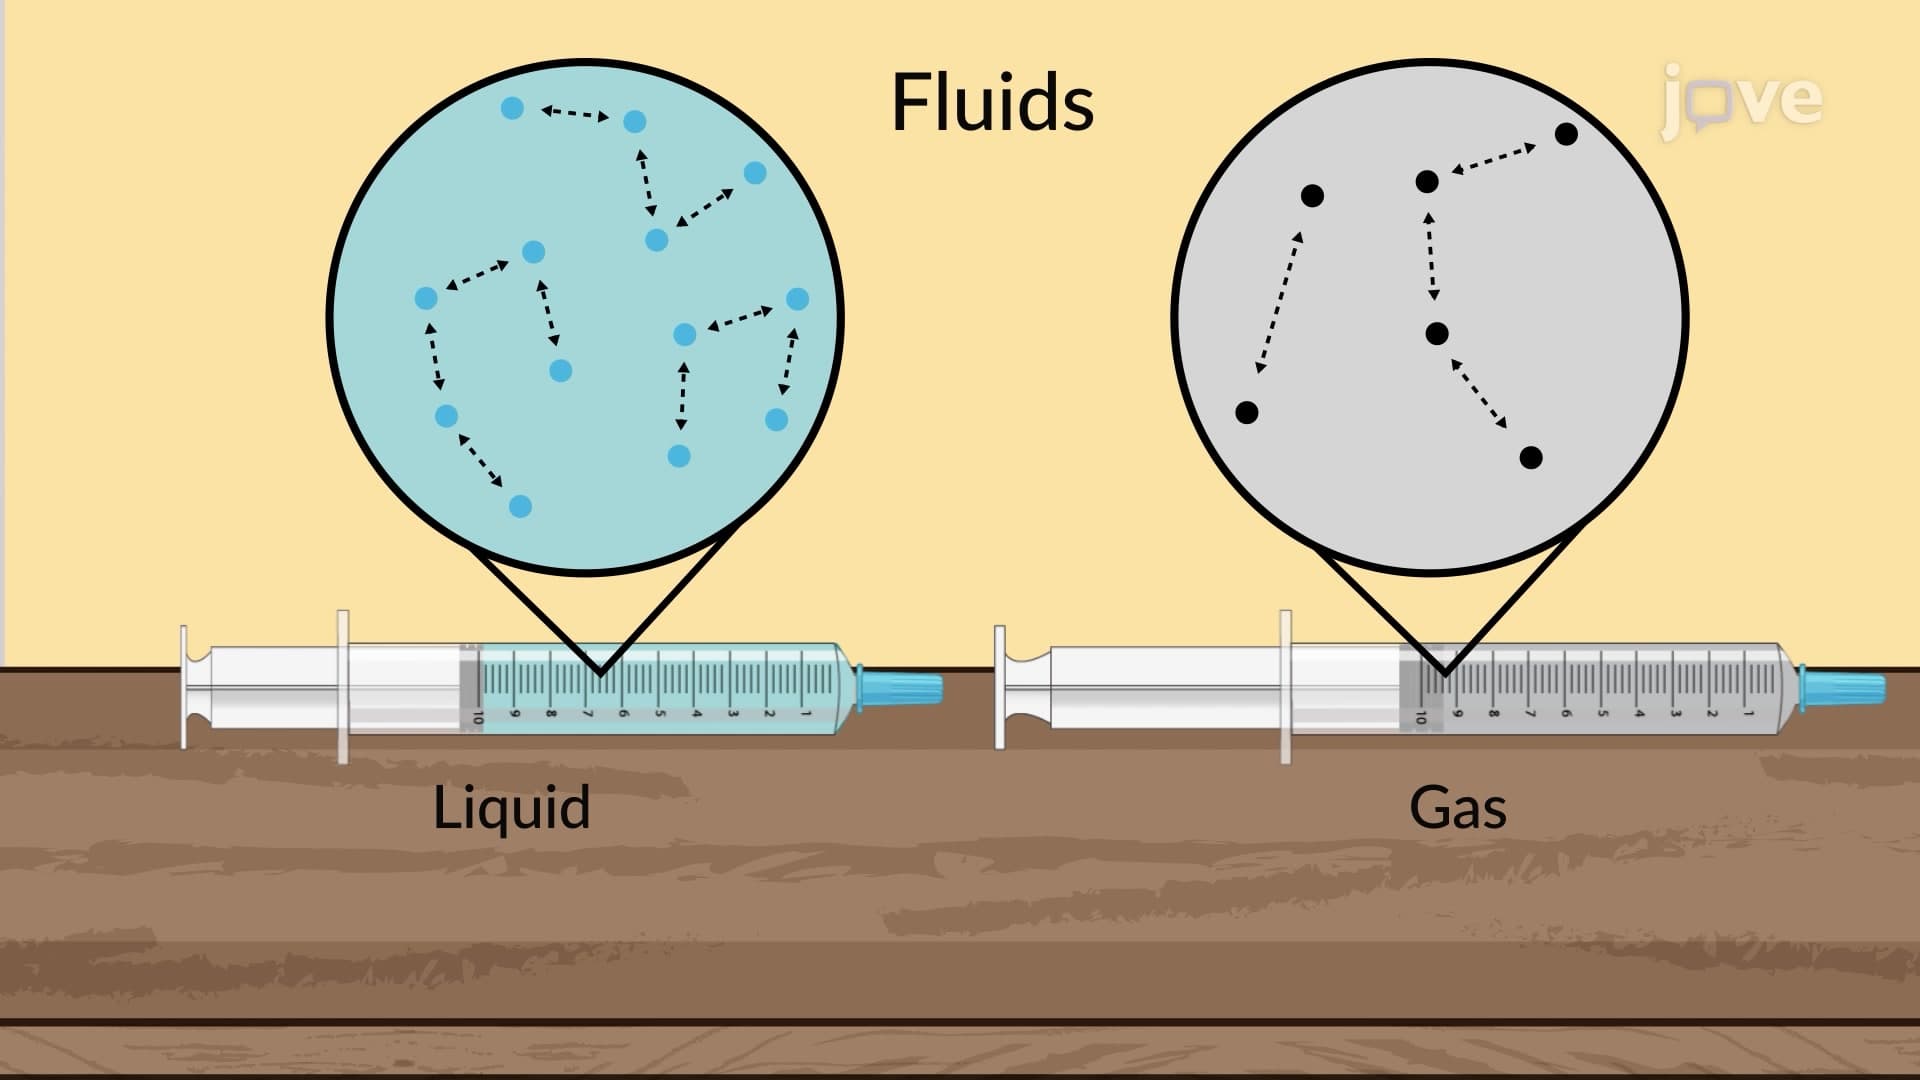
Characteristics of Fluids
 01:31
Characteristics of Fluids
Fluids, which include both liquids and gases, are substances that deform continuously under shearing stress. For example, water and oil are liquids with molecules that can...
 01:17
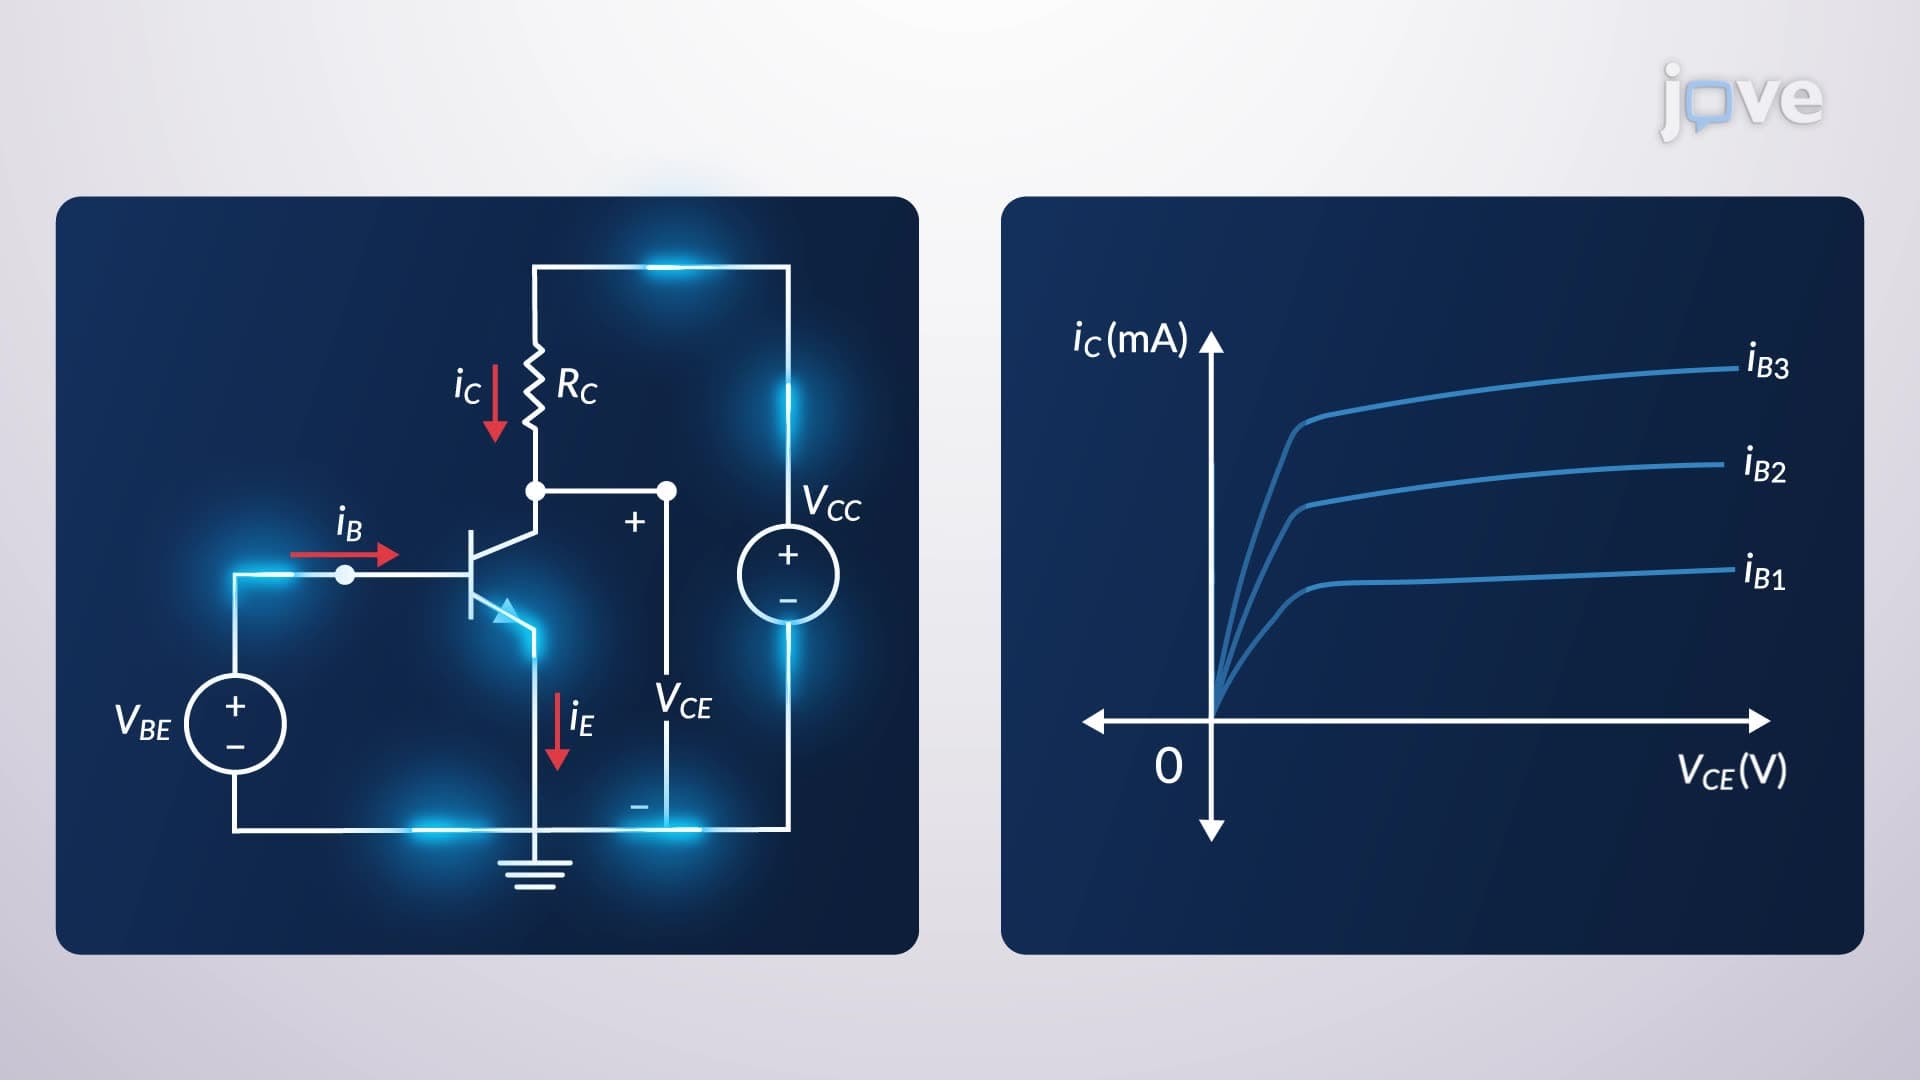
Characteristics of BJT
For input characteristics, the base-emitter voltage is varied, maintaining a constant collector-emitter voltage. This setup reveals a Shockley-type dependence of the collector current on...
 01:21
Characteristics of JFET
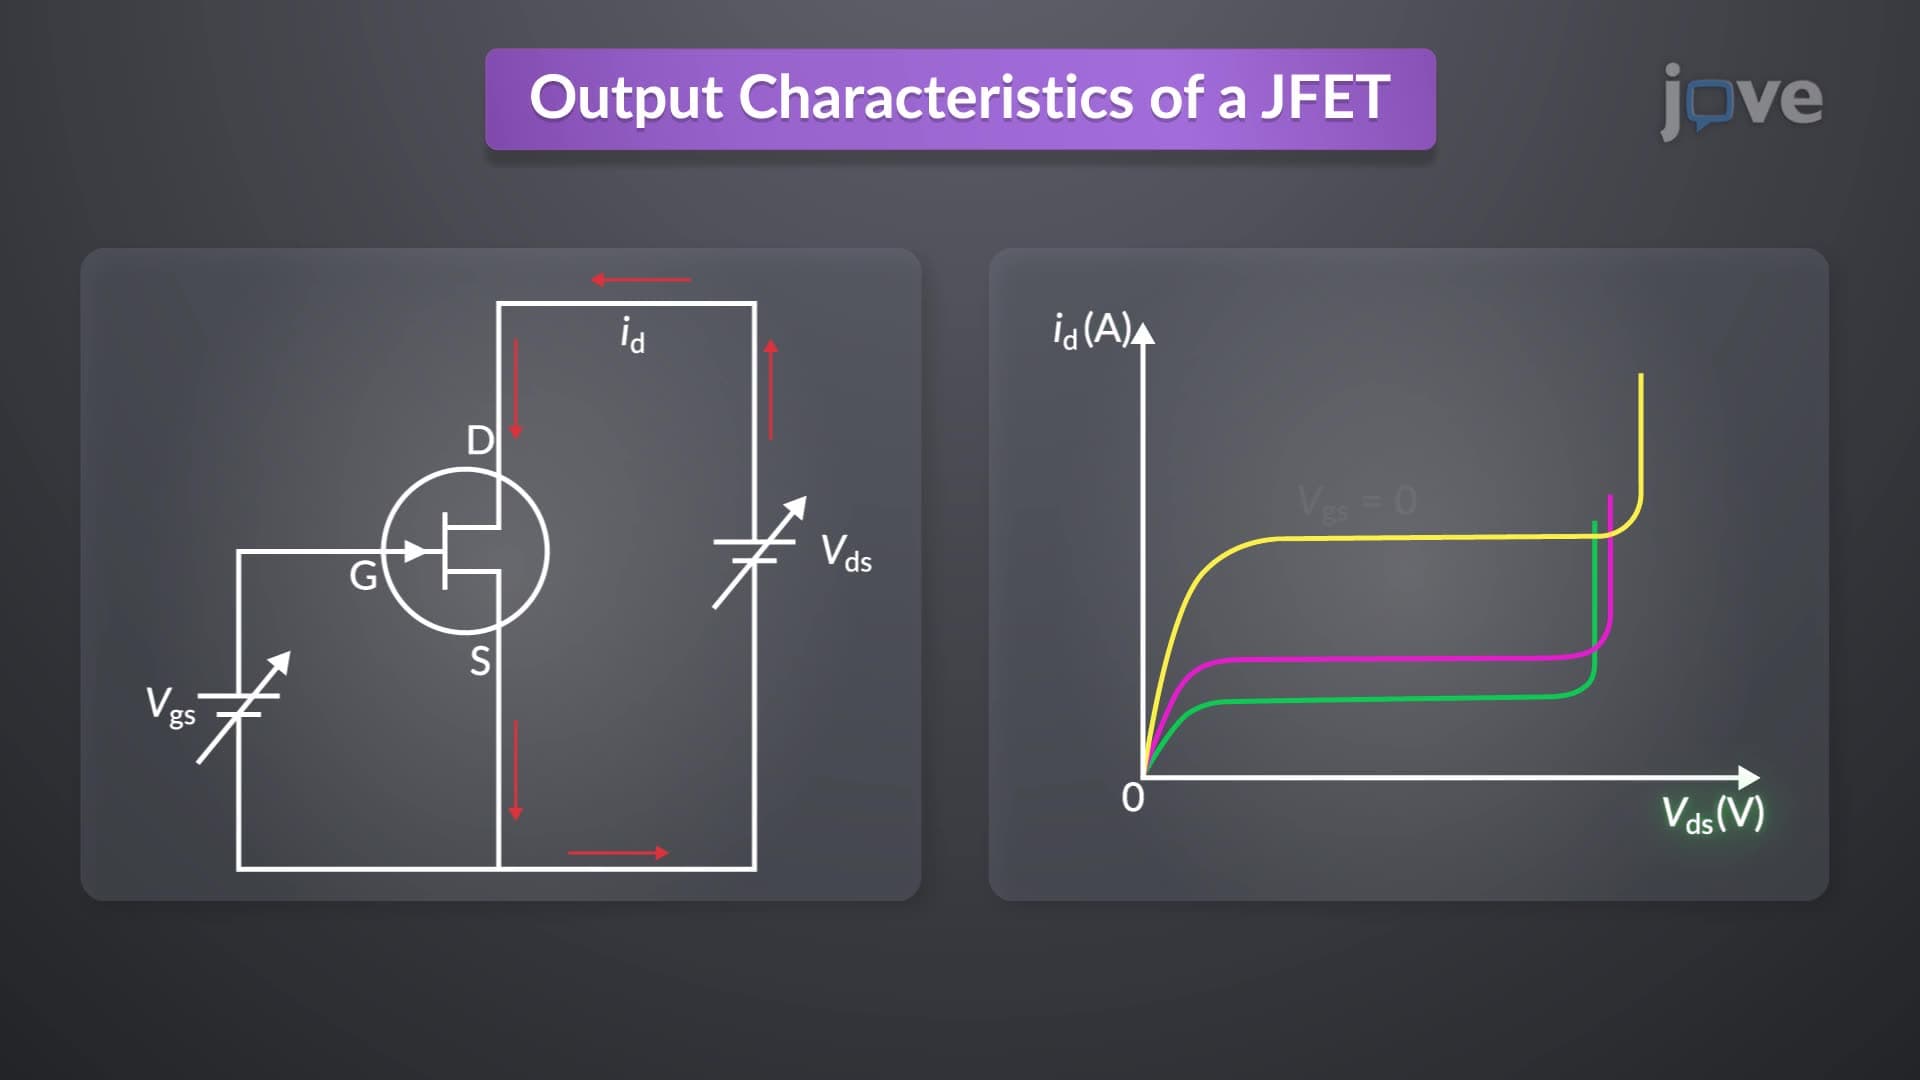
The core of a JFET's operation is controlling drain current by modulating the gate-source voltage. When the drain and gate voltage are set to zero, the JFET exhibits no net current flow, representing a state of equilibrium. The drain current increases linearly as the...