Related Experiment Video
Updated: Jan 22, 2026


Role of Diffusion MRI Tractography in Endoscopic Endonasal Skull Base Surgery
Published on: July 5, 2021
Safety and Feasibility of Transanal Endoscopic Surgery for Diffuse Cavernous Hemangioma of the Rectum
Ziwei Zeng1,2,3, Xianrui Wu1,2,3, Junji Chen1,2,3
1Department of Colorectal Surgery, The Sixth Affiliated Hospital, Sun Yat-sen University, Guangzhou, China.

Insights
Transanal endoscopic surgery is a safe and feasible treatment for diffuse cavernous hemangioma of the rectum (DCHR). This minimally invasive approach offers a high potential for treating rectal diseases with no reported complications.
Area of Science:
- Gastroenterology
- Surgical Oncology
- Minimally Invasive Surgery
Background:
- Diffuse cavernous hemangioma of the rectum (DCHR) is a rare vascular malformation.
- Painless rectal bleeding is the primary symptom, often leading to anemia.
- Accurate diagnosis of DCHR can be challenging, requiring advanced imaging.
Purpose of the Study:
- To evaluate the safety and feasibility of transanal endoscopic surgery for DCHR.
- To assess the efficacy of this minimally invasive technique in treating DCHR.
- To explore the potential of transanal endoscopic surgery for other rectal conditions.
Main Methods:
- Retrospective review of 7 DCHR patients who underwent transanal endoscopic surgery (January 2014 - June 2018).
- Diagnosis confirmed using colonoscopy, CT, and MRI.
- Surgical procedure involved transanal endoscopic surgery, with some patients requiring loop ileostomy.
Main Results:
- Seven patients (4 male, 3 female) with DCHR underwent transanal endoscopic surgery.
- Mean age was 32 years; median symptom duration was 10 years.
- No intraoperative or postoperative complications were reported; all patients recovered well without transfusions.
Conclusions:
- Transanal endoscopic surgery is a safe and feasible treatment option for DCHR.
- Preoperative MRI and CT are crucial for definitive diagnosis and staging.
- This technique shows significant potential for treating various rectal diseases.
Purpose:
To evaluate the safety and feasibility of transanal endoscopic surgery for diffuse cavernous hemangioma of the rectum (DCHR).
Methods:
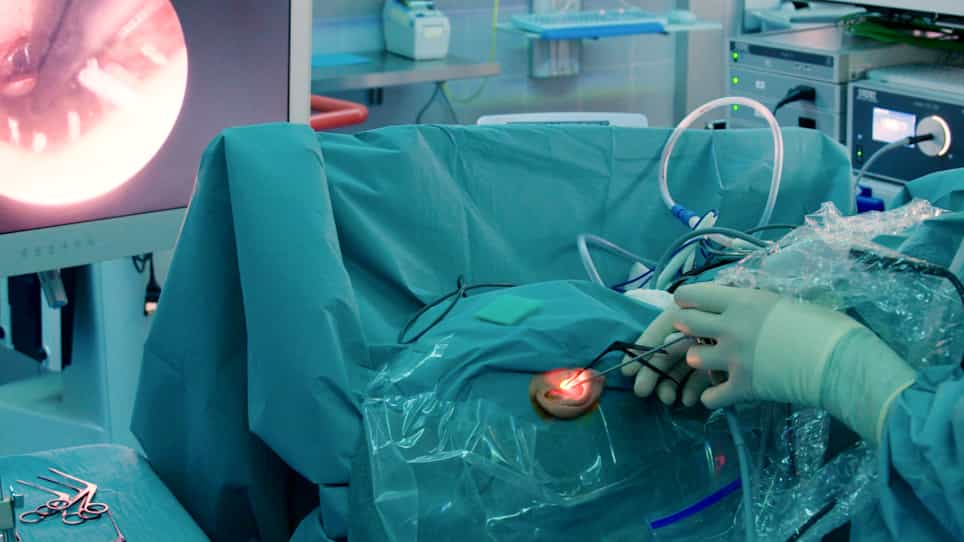
All DCHR patients who underwent transanal endoscopic surgery in our hospital between January 2014 and June 2018 were reviewed.
Results:
A total of 7 patients with a diagnosis of DCHR underwent transanal endoscopic surgery during the study period. Four patients (57.1%) were male, with a mean age at surgery of 34.5 ± 7.7 years, and three patients (42.9%) were female, with a mean age at surgery of 29.9 ± 3.8 years. Recurrent painless rectal bleeding was the main symptom in all patients. The mean age was 32 years old (range 21-54 years). The median duration of symptoms was 10 years (range 1 month-50 years). The level of hemoglobin at admission ranged from 59.0 to 148.0 g/l (mean 106.6 g/l), and the level of mean corpuscular volume (MCV) ranged from 75.1 fl to 93.5 fl (mean 83.7 fl). Colonoscopy, computed tomography (CT), and magnetic resonance imaging (MRI) were important in the diagnosis of DCHR because of their high positive rates and accurate features. All of the lesions are between the anal canal and the descending colon. Two patients could be found with some enlarged serpentine vessels in the cervix, vagina, or corpus cavernosum by MRI. After admission, all the patients underwent transanal endoscopic surgery and four patients had simultaneous loop ileostomy. The mean operative time was 278 min (range 168-400 min). The median amount of intraoperative blood loss was 50 ml (range 10-300 ml). The mean distance from anal verge to anastomosis was 2.2 ± 0.2 cm. The anastomosis was fashioned with a stapler in two patients (28.6%). There were no intraoperative and postoperative complications. All the patients continued to recover well from the surgery, and nobody needed postoperative blood transfusions.
Conclusions:
The specific diagnosis rate of DCHR is low. Preoperative MRI and CT examination can make a definitive diagnosis and determine the extent of the lesions. DCHR is mostly restricted to the rectum, sigmoid colon, anal wall, and mesorectum. The best treatment for DCHR is complete lesion resection. It is safe and feasible to treat DCHR using transanal endoscopic surgery. Moreover, transanal endoscopic surgery might have a huge potential when used to treat other rectal diseases.

Related Concept Videos
 01:25
Assessment of the Rectum and Anus
Rectal Inspection
Begin by inspecting the perianal and anal areas for color, texture, rashes,...
 01:12
Diffusion
 01:21
Diffusion
 01:28
Survey Safety
 01:13
Household Wiring And Electrical Safety
 01:16
Facilitated Diffusion
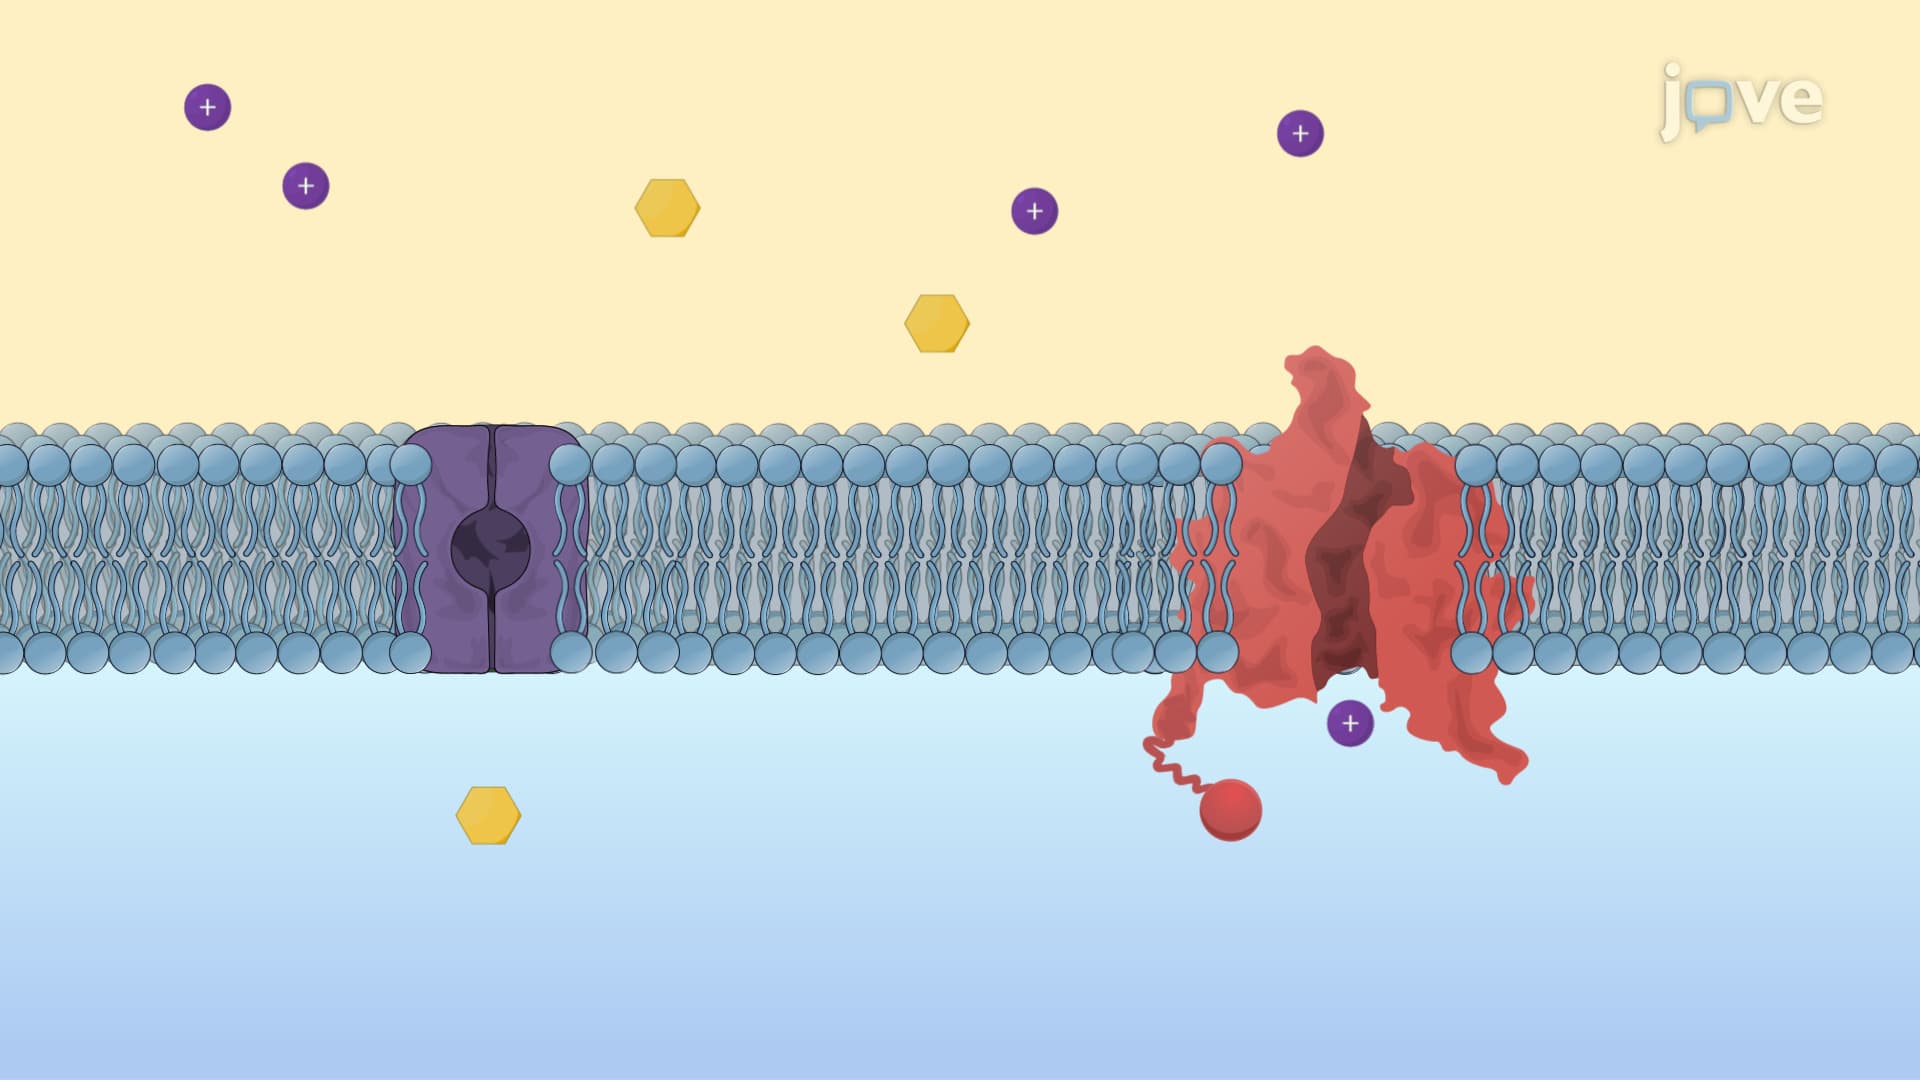
In this process, substrates such as organic compounds and ions interact with a transporter on one side, triggering conformational changes in proteins that enable...