Related Experiment Video
Updated: Jan 21, 2026
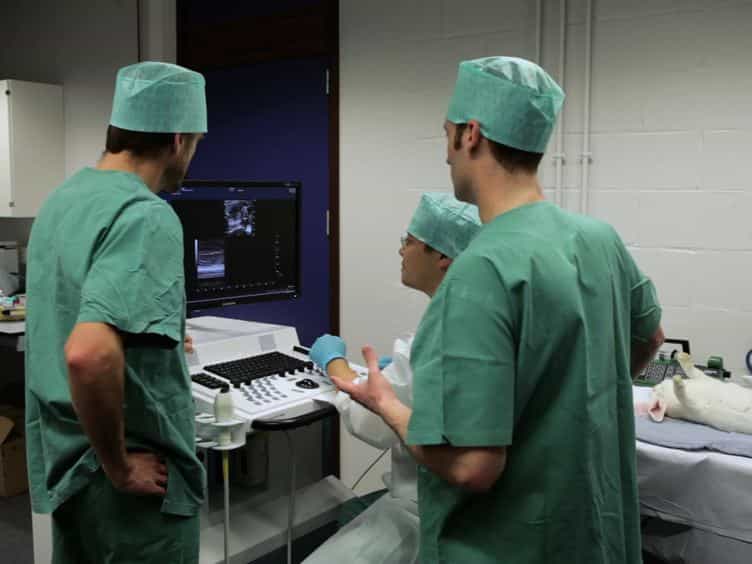
Fetal Echocardiography and Pulsed-wave Doppler Ultrasound in a Rabbit Model of Intrauterine Growth Restriction
Published on: June 29, 2013
The association of stillbirth with placental abnormalities in growth-restricted and normally grown fetuses
Alexa A Freedman1, Robert M Silver2, Karen J Gibbins2
1Department of Epidemiology, Rollins School of Public Health, Emory University, Atlanta, Georgia.

Background:
Stillbirth, defined as foetal death ≥20 weeks' gestation, is associated with poor foetal growth and is often attributed to placental abnormalities, which are also associated with poor foetal growth. Evaluating inter-relationships between placental abnormalities, poor foetal growth, and stillbirth may improve our understanding of the underlying mechanisms for some causes of stillbirth.
Objective:
Our primary objective was to determine whether poor foetal growth, operationalised as small for gestational age (SGA), mediates the relationship between placental abnormalities and stillbirth.
Methods:
We used data from the Stillbirth Collaborative Research Network study, a population-based case-control study conducted from 2006-2008. Our analysis included 266 stillbirths and 1135 livebirths. We evaluated associations of stillbirth with five types of placental characteristics (developmental disorders, maternal and foetal inflammatory responses, and maternal and foetal circulatory disorders) and examined mediation of these relationships by SGA. We also assessed exposure-mediator interaction. Models were adjusted for maternal age, race/ethnicity, education, body mass index, parity, and smoking status.
Results:
All five placental abnormalities were more prevalent in cases than controls. After adjustment for potential confounders, maternal inflammatory response (odds ratio [OR] 2.58, 95% confidence interval [CI] 1.77, 3.75), maternal circulatory disorders OR 4.14, 95% CI 2.93, 5.84, and foetal circulatory disorders OR 4.58, 95% CI 3.11, 6.74 were strongly associated with stillbirth, and the relationships did not appear to be mediated by SGA status. Associations for developmental disorders and foetal inflammatory response diverged for SGA and non-SGA births, and strong associations were only observed when SGA was not present.
Conclusions:
Foetal growth did not mediate the relationships between placental abnormalities and stillbirth. The relationships of stillbirth with maternal and foetal circulatory disorders and maternal inflammatory response appear to be independent of poor foetal growth, while developmental disorders and foetal inflammatory response likely interact with foetal growth to affect stillbirth risk.

Related Concept Videos
 02:23
Abnormal Proliferation
 01:24
Gonadal and Placental Hormones
In males, testosterone is the primary gonadal androgen. It plays a central role in the maturation of male reproductive organs — the penis and testes. Additionally, testosterone is instrumental in the development of secondary sexual characteristics — a deep voice as well as facial and pubic hair...
 01:15
Development of the Sexual Organs in the Embryo and Fetus
Near the gonadal ridges, two duct systems are present: the mesonephric ducts (Wolffian ducts) and paramesonephric ducts (Müllerian ducts). These ducts form the basis for the...
 01:11
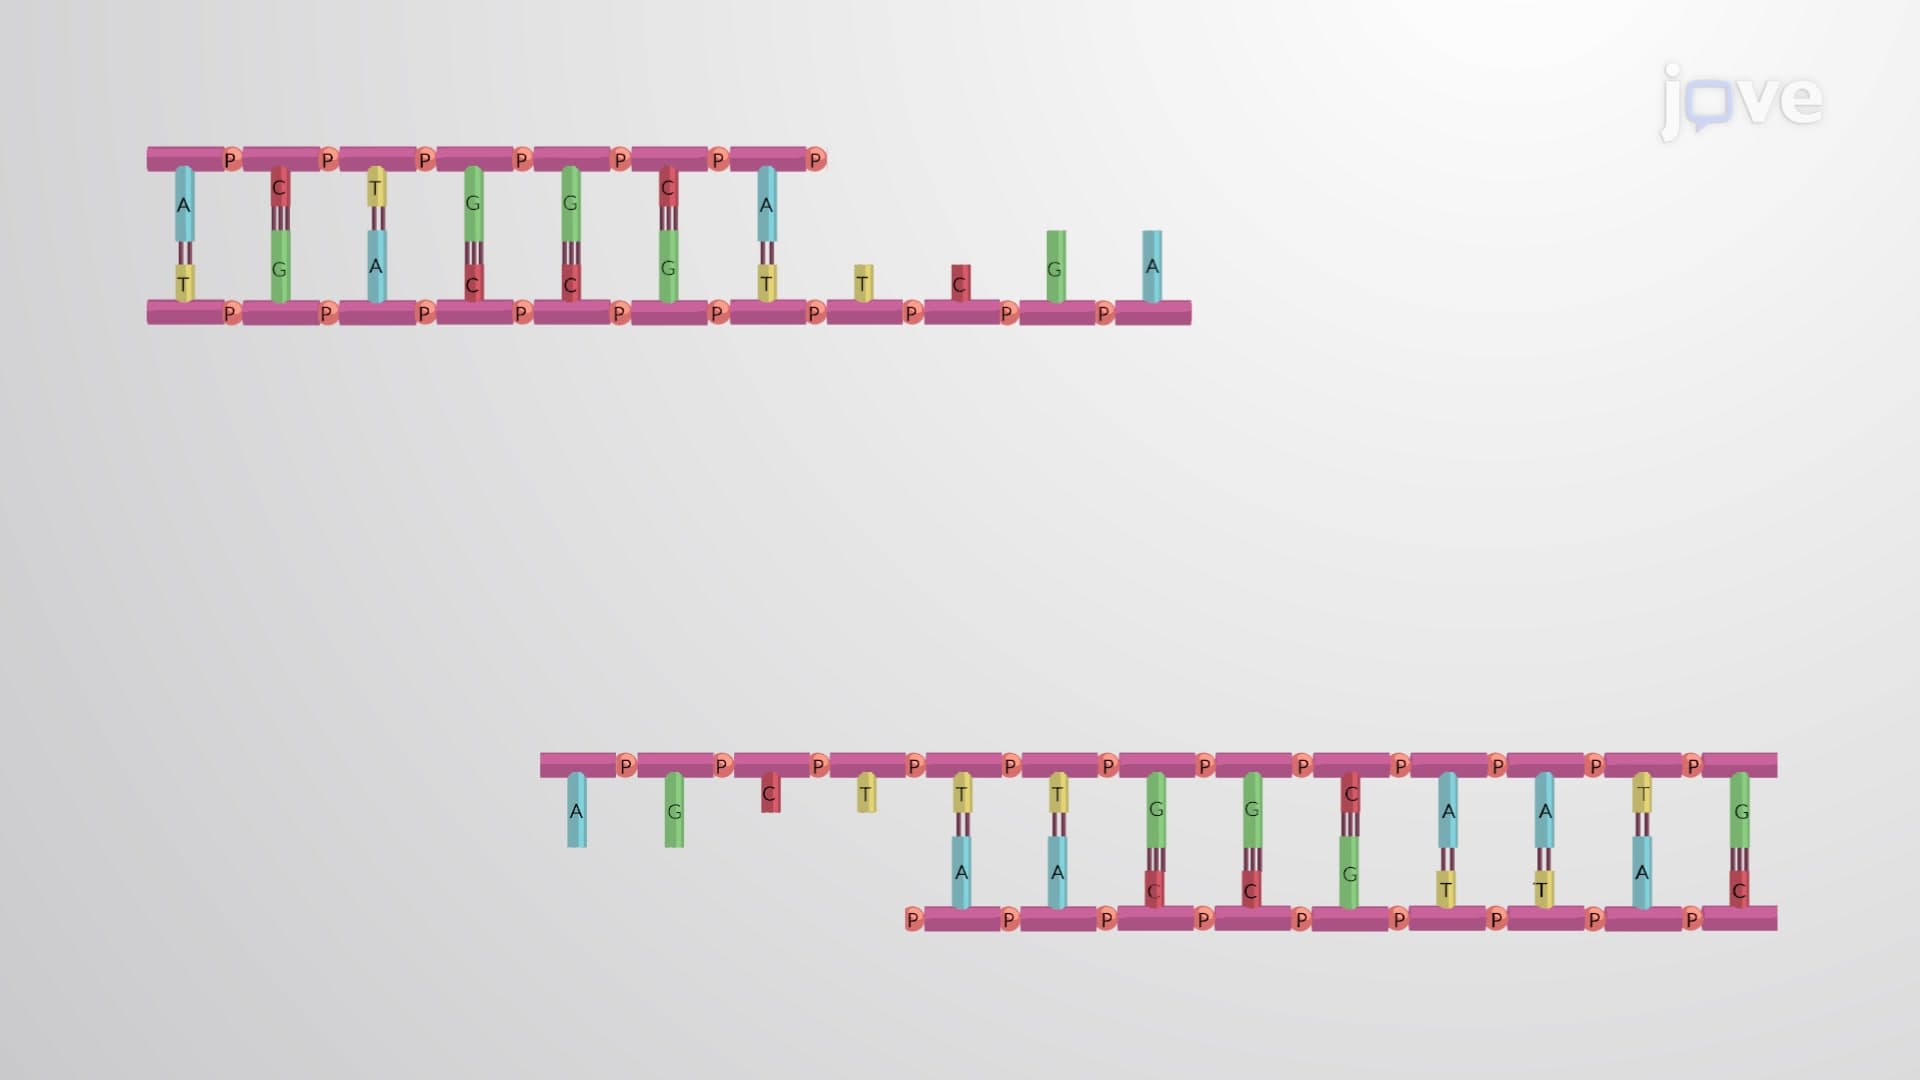
Restriction Enzymes
The host bacteria protect their own genomic DNA from these enzymes by methylating these sites. Some...
 02:36
Meristems and Plant Growth
 01:30
Respiratory System Abnormal Finding I: Inspection and Percussion
Inspection Findings
During an inspection, several findings may suggest the presence of respiratory distress or disease. Pursed-lip breathing, where exhalation is slowed by...