Related Experiment Video
Updated: Jan 21, 2026

Analysis of Cardiac Contractile Dysfunction and Ca2+ Transients in Rodent Myocytes
Published on: May 25, 2022
Debunking the July Effect in Cardiac Surgery: A National Analysis of More Than 470,000 Procedures
Rohan M Shah1, Sameer A Hirji1, Spencer Kiehm1
1Division of Cardiac Surgery, Brigham and Women's Hospital, Harvard Medical School, Boston, Massachusetts.

Background:
Recent studies in noncardiac surgery have described worse outcomes in the first month of training. However, the "July effect" in the context of cardiac surgery outcomes is not well understood. We examined whether patient outcomes after cardiac surgery were affected by procedure month or academic year quartile.
Methods:
Using the National Inpatient Sample, we isolated all coronary artery bypass grafting (CABG), surgical aortic valve replacement (AVR), mitral valve repair or replacement (MV), and isolated thoracic aortic aneurysm (TAA) replacement procedures between 2012 and 2014. For each procedure, overall trends in in-hospital mortality and hospital complications were compared by academic year quartiles (ie, between the first academic year quartile vs the fourth quartile) and by procedure month. Outcomes between teaching and nonteaching hospitals were also compared.
Results:
Overall, 301,105 CABG, 111,260 AVR, 54,985 MV, and 2,655 TAA procedures met inclusion criteria. In-hospital mortality for each procedure did not vary by procedure month or academic year quartile, even after risk adjustment (all P > .05). Teaching status did not influence risk-adjusted mortality for CABG and isolated TAA replacement (both P > .05). However, teaching hospitals had significantly lower adjusted mortality than nonteaching hospitals for AVR and MV surgery (both P < .01).
Conclusions:
The July effect is not evident for cardiac surgery despite preexisting notions. Teaching hospitals performed at least equivalent, if not better, for major cardiac surgery procedures. These findings highlight the pivotal role of hospital support systems to ensure the safe transition of resident classes without compromising on patient outcomes.
More Related Videos
 09:12
Surgical Swine Model of Chronic Cardiac Ischemia Treated by Off-Pump Coronary Artery Bypass Graft Surgery
Published on: March 27, 2018
 08:43
Isolation of Endothelial Progenitor Cells from Healthy Volunteers and Their Migratory Potential Influenced by Serum Samples After Cardiac Surgery
Published on: February 14, 2017
Related Concept Videos
 01:26
National Nursing Organizations I
 01:28
Cardiac Catheterization I: Pre-Procedure Overview
 01:30
National Nursing Organizations II
The AACN emphasizes a healthy work environment through six standards to achieve an optimal patient outcome. The standards are appropriate staffing, meaningful recognition, collaboration, authentic leadership, effective communication, and decision-making. In addition, AACN provides certification programs, webinars, journals, and...
 01:22
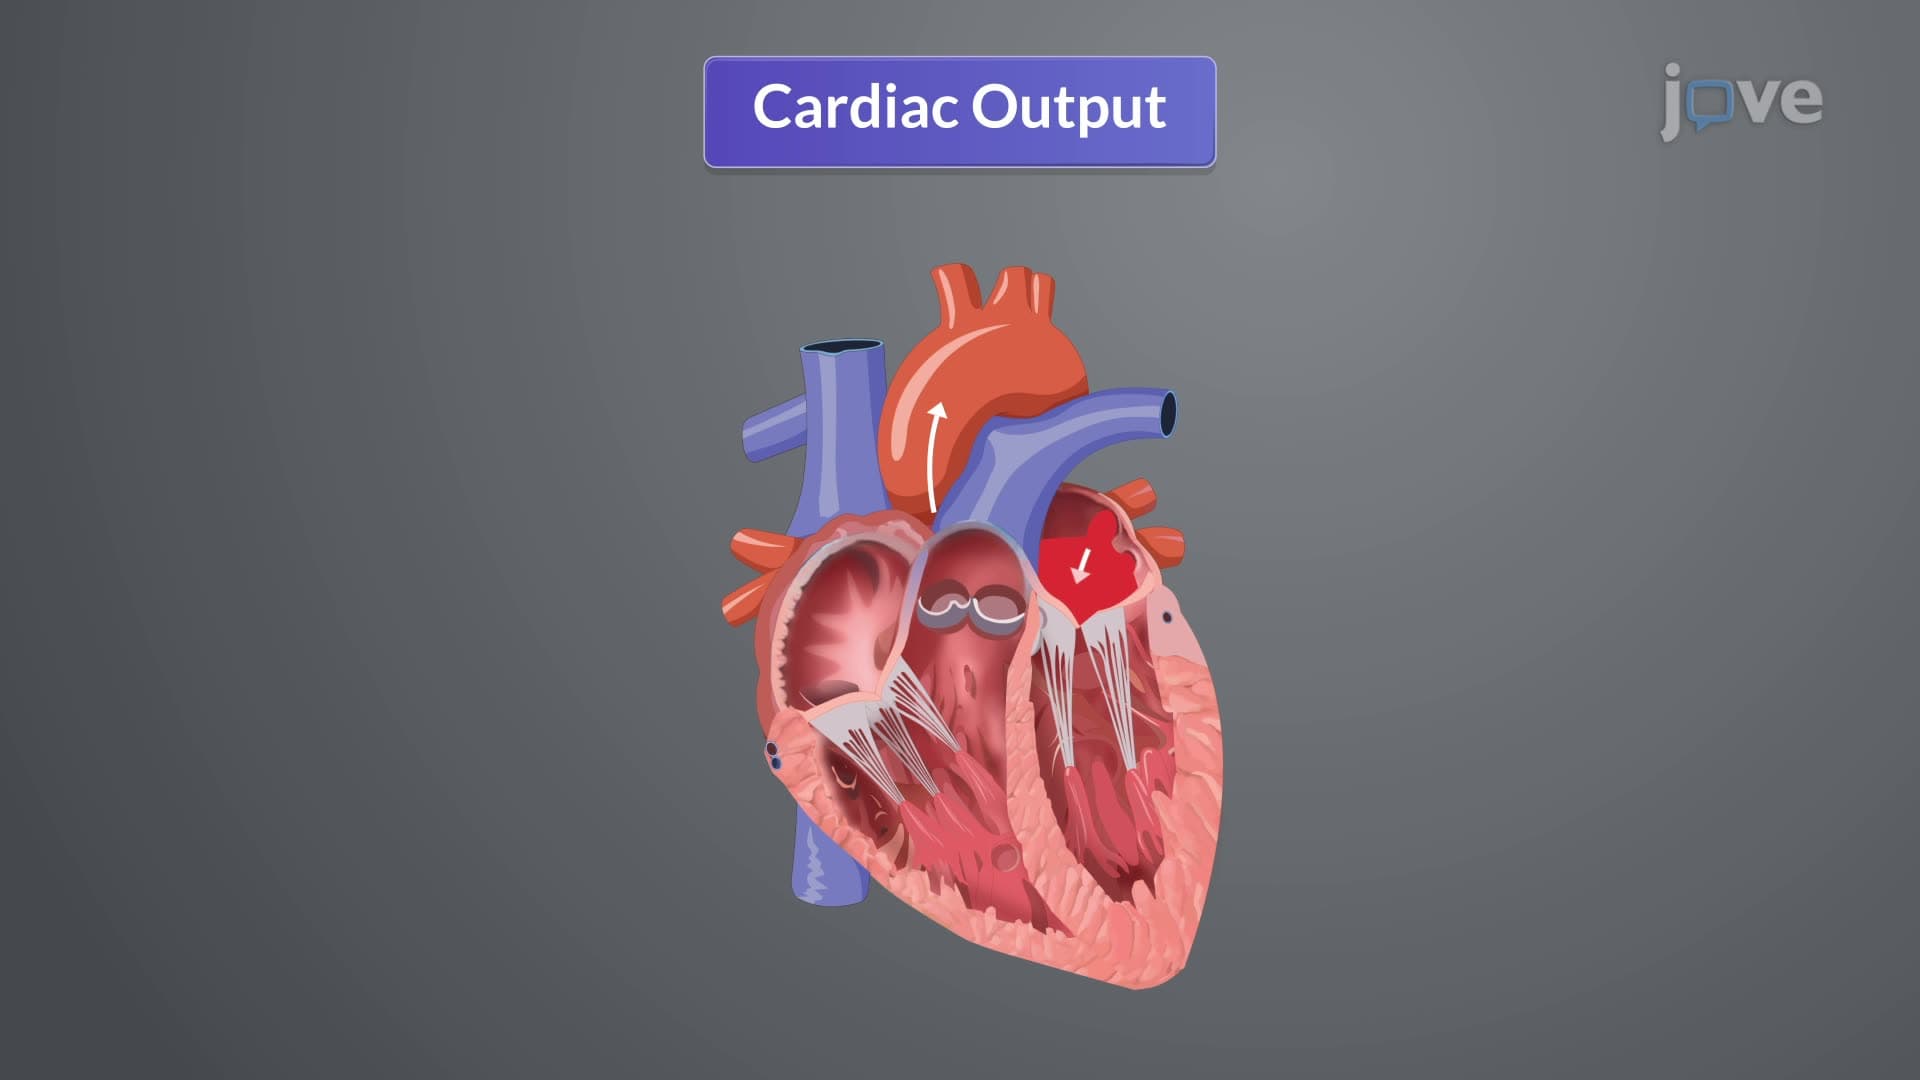
Cardiac Output II: Effect of Stroke Volume on Cardiac Output
Preload
Preload refers to the initial elongation of the cardiac myocytes before contraction and is related to the volume of blood filling the heart at the end of diastole, or end-diastolic volume. The...
 02:07
Blind Procedures
 01:19
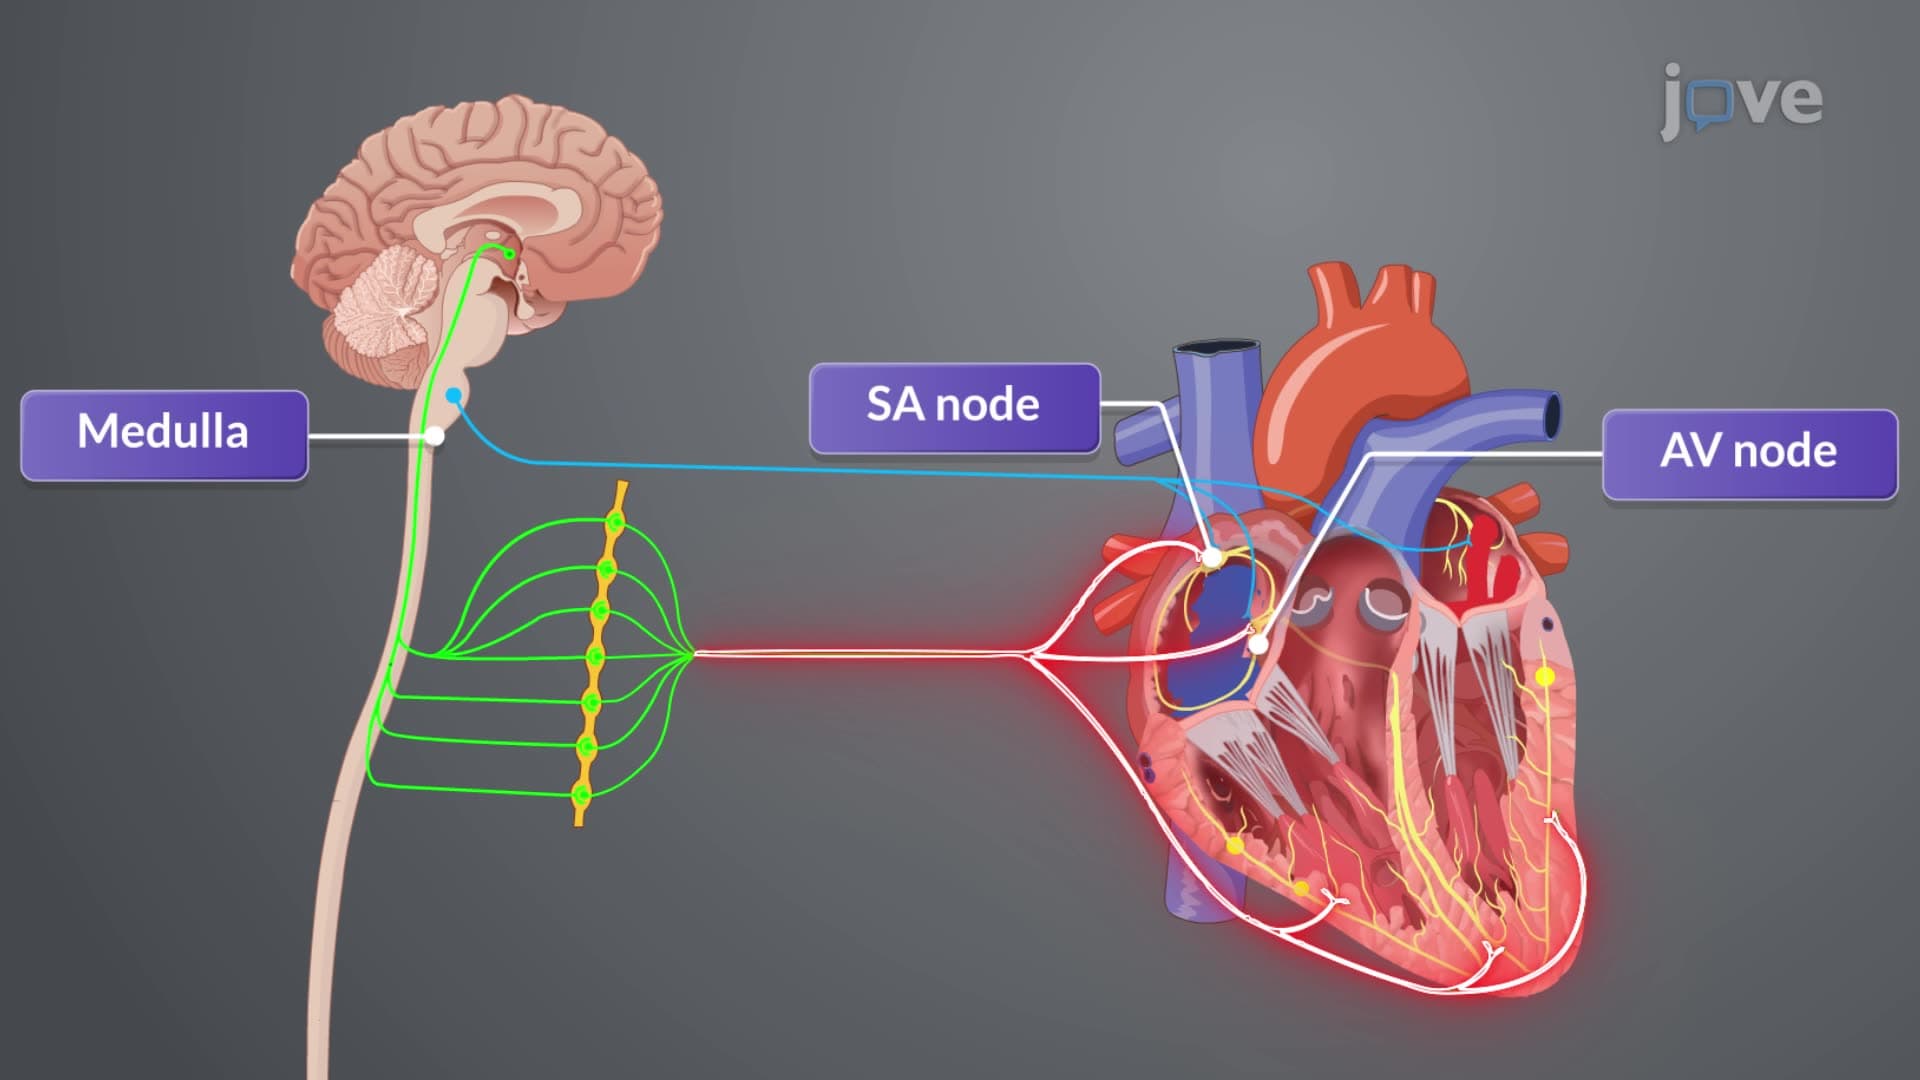
Cardiac Output I:Effect of Heart Rate on Cardiac Output
Cardiac output (CO) refers to the total amount of blood ejected by one of the ventricles in liters per minute (L/min). In a resting adult, CO ranges from 5 to 6 L/min, adjusting according to the body's metabolic requirements.
Effect of Heart Rate on Cardiac Output
Cardiac output adapts to metabolic demands during stress, physical activity, or illness. The autonomic nervous system regulates heart rate via the sinoatrial node. The parasympathetic nervous system decreases heart...