Related Experiment Video
Updated: Jan 21, 2026
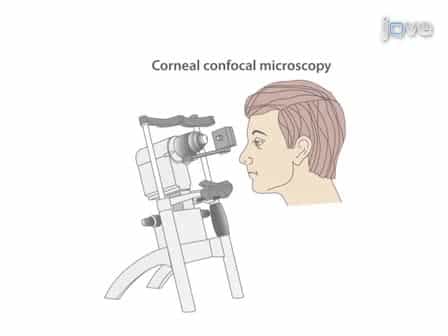

Corneal Confocal Microscopy: A Novel Non-invasive Technique to Quantify Small Fibre Pathology in Peripheral Neuropathies
Published on: January 3, 2011
Optimizing Clinical Screening for Chemotherapy-Induced Peripheral Neuropathy
J Matt McCrary1, David Goldstein2, Terry Trinh1
1Prince of Wales Clinical School, University of New South Wales, Kensington, Australia.

Context:
Efficient and accurate clinical screening for treatment-related toxicities is a critical component of optimal patient management. A number of alternate screening tools for chemotherapy-induced peripheral neuropathy (CIPN) have been proposed in response to demonstrated limitations with standard clinical screening, although their relative diagnostic value is unclear.
Objectives:
The aim of this study is to evaluate the relative construct validity and discriminant properties of available CIPN screening tools.
Methods:
Patients treated with known potentially neurotoxic therapies underwent CIPN evaluation at one or multiple timepoints (N = 316 patients; age = 56 ± 13 years). At each testing session (N = 644 testing sessions), patients were evaluated using screening tools and comprehensive CIPN assessments. Comprehensive assessments were clinician-rated (Total Neuropathy Score, reduced) or patient-reported outcome (PRO; Functional Assessment of Cancer Therapy-Gynecologic Oncology Group/Neurotoxicity questionnaire). Similarly, screening tools were clinician-rated (National Cancer Institute Common Terminology Criteria for Adverse Events [NCI-CTCAE]) or PRO (Patient Neurotoxicity Questionnaire, PRO-CTCAE).
Results:
Analyses revealed moderate-to-high correlations between screening tools and comprehensive assessments (0.55 ≤ rho ≤ 0.75; P < 0.001) and similar discriminant properties across screening tools (P > 0.01). Screening tool grading corresponding to clinically significant (grade 2/3) vs. low-grade (grade 0/1) CIPN would correspond to greater ratings of CIPN severity by more comprehensive assessments in a predicted 77%-91% of cases (c-statistic = 0.77-0.91; P < 0.01).
Conclusions:
PRO screening tools provide adequate CIPN screening while avoiding potential biases demonstrated to limit currently used clinician-rated screening tools. Addition of a brief objective test did not add value to PRO screening. Up to 23% of patients would be misidentified through screening, providing quantitative evidence of the limitations of available screening tools. More extensive CIPN evaluations are critical in patients at risk of serious neurotoxicity.
Related Concept Videos
 01:21
Chemotherapy-Induced Nausea and Vomiting: Cannabinoids
Two synthetic agonists of THC,...
 01:29
Chemotherapy-Induced Nausea and Vomiting: Dopamine Receptor Antagonists
Phenothiazines, such as prochlorperazine...
 01:27
Chemotherapy-Induced Nausea and Vomiting: 5-HT3 Receptor Antagonists
 01:28
Chemotherapy-Induced Nausea and Vomiting: Neurokinin-1 Receptor Antagonists
 01:21
Peripheral Arterial Disease II: Clinical Manifestations and Diagnostic Evaluation
 00:48
Optimal Foraging