Related Experiment Video
Updated: Jan 21, 2026


Protocol and Guidelines for Point-of-Care Lung Ultrasound in Diagnosing Neonatal Pulmonary Diseases Based on International Expert Consensus
Published on: March 6, 2019
Diagnostic Performance of 6-Point Lung Ultrasound in ICU Patients: A Comparison with Chest X-Ray and CT Thorax
Mohammad Danish1, Aarti Agarwal1, Puneet Goyal1
1Department of Anaesthesiology and Intensive Care, Sanjay Gandhi Post Graduate Institute of Medical Sciences, Lucknow, UP, India.

Objective:
To evaluate the diagnostic performance of a rapid bedside 6-point lung ultrasonography (LUS) performed by an intensive care unit (ICU) physician for detection of four common pathological conditions of the lung, such as alveolar consolidation, pleural effusion, interstitial syndrome and pneumothorax, in critically ill patients and its comparison with bedside chest X-ray (CXR) and high-resolution computed tomography (CT) scan of the thorax. Volume of pleural effusion measured by LUS and CT thorax was also compared.
Methods:
This was a cross-sectional, observational study of 90 adult patients with an acute lung injury score of ≥1 admitted to the medical-surgical ICU. They were examined by CXR and 6-point LUS as per BLUE protocol at bedside, followed by CT thorax in the radiology department.
Results:
The sensitivity of 6-point LUS for detecting alveolar consolidation, pleural effusion, interstitial syndrome and pneumothorax was 76%, 88%, 83% and 89%, respectively, which was remarkably higher than that of CXR. The specificity of LUS was 100% for all pathologies, which was again notably higher than that of CXR except for interstitial syndrome for which it was 88.5%. Measurement of volume of pleural effusion by LUS was comparable and had a strong absolute agreement with CT thorax.
Conclusion:
6-Point LUS can be a useful diagnostic tool and is better than CXR in diagnosing respiratory pathologies in critically ill patients. Owing to the comparable diagnostic performance of LUS and CT scan and with increasing evidence in favour of LUS, the requirement of CT thorax can be reduced. Radiation hazards associated with CXR and CT, as well as potentially risky transfer of patients to CT room, can also be minimised.
More Related Videos
 08:05
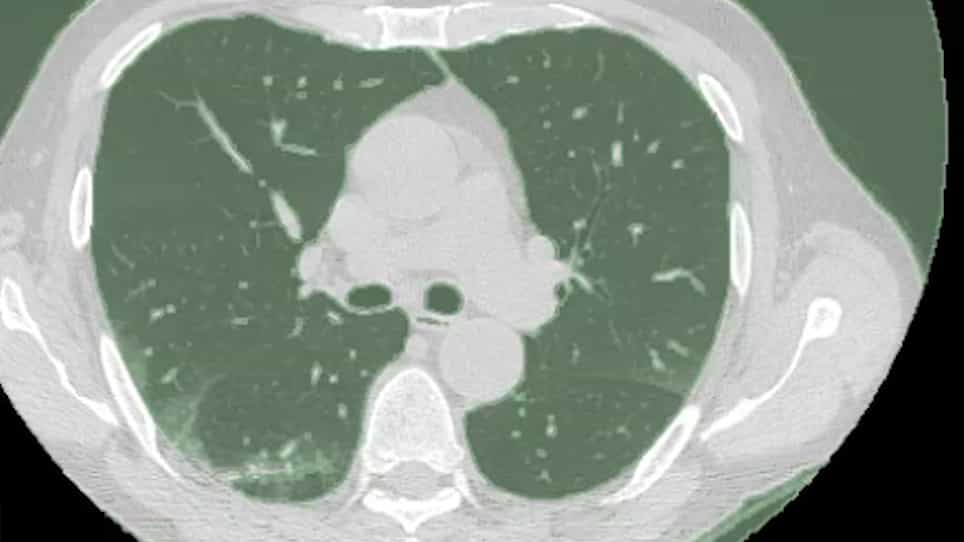
Lung CT Segmentation to Identify Consolidations and Ground Glass Areas for Quantitative Assesment of SARS-CoV Pneumonia
Published on: December 19, 2020
 08:41
Patient-Specific Polyvinyl Alcohol Phantom Fabrication with Ultrasound and X-Ray Contrast for Brain Tumor Surgery Planning
Published on: July 14, 2020
Related Concept Videos
 01:30
Radiological Investigation I: X-ray and CT
 01:25
Muscles of the Thorax
The diaphragm is at the core of thoracic musculature, the primary muscle involved in breathing. This expansive, dome-shaped muscle marks the division between the thoracic and abdominal cavities. It...
 01:19
Veins of Thorax
The azygos vein, positioned just right of the midline and anterior to the vertebral column, begins at the junction of the right ascending lumbar and subcostal veins, terminating in the superior vena cava. This vein drains blood from the right side of the thoracic wall, thoracic viscera, and posterior abdominal wall.
The...
 01:24
Flail Chest-I
Flail chest is a severe and potentially life-threatening condition characterized by the fracture of three or more adjacent ribs in multiple places. It is most commonly caused by direct impacts and trauma, such as motor vehicle accidents or injuries from a steering wheel impact. It can also occur due to falls in elderly individuals with osteoporosis, or assaults involving sharp objects.
Pathophysiology
The pathophysiology of flail chest is complex, involving fractures of...
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History:
 01:24
Chest Physiotherapy
Purpose
CPT is primarily used for patients with excessive bronchial secretions who have difficulty clearing...