Related Experiment Video
Updated: Jan 21, 2026
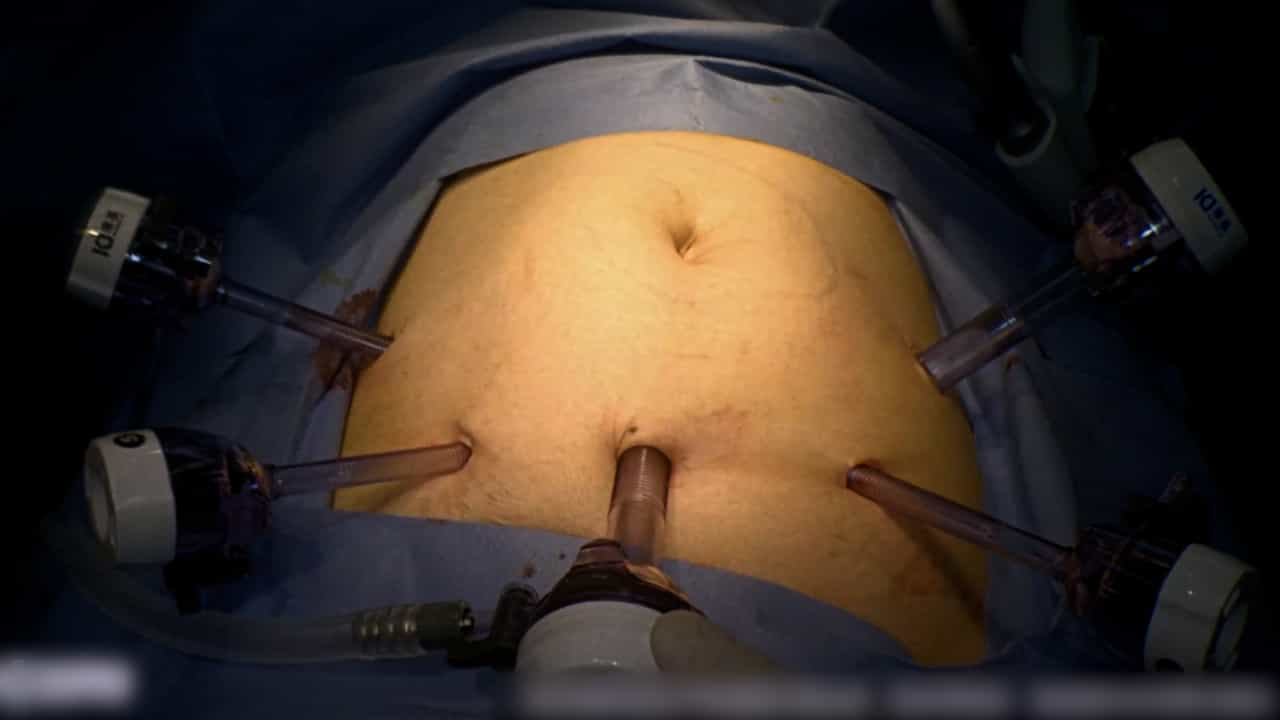

Surgical Trunk Oriented Laparoscopic Right Hemicolectomy (ST-LRH) for Right-Sided Colon Cancer
Published on: July 25, 2025
Successful patient-oriented surgical outcomes in robotic vs laparoscopic right hemicolectomy for cancer - a
P S Waters1, F P Cheung1, O Peacock1
1Colorectal Surgery Unit, Peter MacCallum Cancer Centre, Melbourne, Victoria, Australia.

Aim:
Minimally invasive surgical approaches for cancer of the right colon have been well described with significant patient and equivalent oncological benefits. Robotic surgery has advanced in its ability to provide multi-quadrant abdominal access, leading the surgical community to widen its application outside of the pelvis to other abdominal compartments. Globally it is being realized that a patient's surgical episode of care is becoming the epicentre of cancer treatment. In order to establish the role of robotic surgery in a patient's episode of care, 'successful patient-oriented surgical' parameters in right hemicolectomy for malignancy were measured. The objective was to examine the rates of successful patient-oriented surgical outcomes in robotic right hemicolectomy (RRH) compared to laparoscopic right hemicolectomy (LRH) for cancer.
Methods:
A systematic search of MEDLINE (Ovid: 1946-present), PubMed (NCBI), Embase (Ovid: 1966-present) and Cochrane Library was conducted using PRISMA for parameters of successful patient-oriented surgical outcomes in RRH and LRH for malignancy alone. The parameters measured included postoperative ileus, anastomotic complication, surgical wound infection, length of stay (LOS), incisional hernia rate, conversion to open, margin status, lymph node harvest and overall morbidity and mortality.
Results:
There were 15 studies which included 831 RRH patients and 3241 LRH patients, with a median age of 62-74 years. No study analysed the concept of successful patient-oriented surgical outcomes. There was no significant difference in the incidence of postoperative ileus, with less time to first flatus in RRH (2.0-2.7 days, compared with 2.5-4.0 days, P < 0.05). Anastomotic leak rate in one study reported a significant increase in LRH compared to RRH (P < 0.05, 0% vs 8.3%). Significantly decreased LOS following RRH was outlined in six studies. One study reported a significantly higher rate of incisional hernias following LRH with extracorporeal anastomoses compared to RRH with intracorporeal anastomoses. Overall rates of conversion to open surgery were less with RRH (0%-3.9% vs 0%-18%, P < 0.001, 0.05). One study outlined significantly higher rates of incomplete resection with an open right hemicolectomy compared with minimally invasive laparoscopic and robotic resections, with positive margin rates of 2.3%, 0.9% and 0% respectively (P < 0.001). Two studies reported significantly higher lymph node harvest in RRH (P < 0.05). Overall morbidity and 30-day mortality were comparable in both approaches.
Conclusion:
Thirty-day morbidity and mortality were comparable between the two approaches, with patients undergoing RRH having lower anastomotic complications, increased lymph node harvest, and reduced LOS, conversion to open and incisional hernia rates in a number of studies. There are limited data on surgical approach and impact on quality of life and what patients deem successful surgical outcomes. There is a further need for a randomized controlled trial examining successful patient-oriented outcomes in right hemicolectomy for malignancy.

Related Concept Videos
 02:17
Ecological Succession
 01:10
Review and Preview
Percentiles are a type of fractile that partition data into...
 01:13
Review and Preview
 01:20
Random and Systematic Errors
 02:24
Predicting Reaction Outcomes
 01:13
Location and Orientation of the Heart