Adult Congenital Heart Disease: Current Early Expectations After Cardiac Transplantation
Related Experiment Video
Updated: Jan 21, 2026

Implantation of Total Artificial Heart in Congenital Heart Disease
Published on: July 18, 2014
Kyle W Riggs1, Farhan Zafar1, Yasmin Radzi1
1Department of Cardiothoracic Surgery, Heart Institute, Cincinnati Children's Hospital, Cincinnati, Ohio.

Insights
Improved perioperative care has enhanced outcomes for heart transplantation in adult congenital heart disease (ACHD) patients. Patients without key risk factors, like obesity or organ dysfunction, now show survival rates comparable to those without ACHD.
Area of Science:
- Cardiology
- Transplantation Medicine
- Congenital Heart Disease
Background:
- Early mortality remains a challenge in heart transplantation for adult congenital heart disease (ACHD).
- Perioperative care advancements are improving outcomes for ACHD patients undergoing heart transplants.
- This study identifies current risk factors for 1-year mortality in ACHD heart transplant recipients.
Purpose of the Study:
- To identify current risk factors for 1-year mortality in adult congenital heart disease (ACHD) patients post-heart transplantation.
- To compare the outcomes of ACHD patients without identified risk factors against non-ACHD recipients.
- To evaluate the impact of improved perioperative care on survival rates in ACHD heart transplantation.
Main Methods:
- Utilized the United Network of Organ Sharing database for adult heart transplant recipients (2000-2018).
- Divided patients into early (2000-2008) and late (2009-2018) eras for comparative analysis.
- Performed multivariate analysis to identify risk factors for 1-year mortality in the late era and Kaplan-Meier analysis for survival comparisons.
Main Results:
- The recent era (2009-2018) showed significantly better 1-year and overall survival for ACHD patients compared to the early era.
- Identified risk factors for early mortality in ACHD patients: BMI > 25 kg/m², renal dysfunction, liver dysfunction, and longer ischemic times.
- ACHD patients with only one of the first three risk factors (BMI, renal/liver dysfunction) had 1-year survival comparable to non-ACHD recipients.
Conclusions:
- Heart transplantation outcomes for ACHD patients have improved in the recent era.
- Presence of only one pre-transplant risk factor (BMI, renal/liver dysfunction) in ACHD patients leads to survival rates similar to non-ACHD recipients.
- Further research may reveal even better long-term survival for ACHD patients with optimized pre-transplant conditions.
Background:
Early mortality has plagued the otherwise good outcomes of heart transplantation in patients with adult congenital heart disease (ACHD), but perioperative care is improving. This study sought to identify risk factors for 1-year mortality currently and examine the results of patients without those risk factors compared with patients who did not have ACHD (nACHD).
Methods:
The United Network of Organ Sharing database was searched for all adult (>17 years of age) heart transplant recipients from 2000 to 2018. They were divided into an early era and a late era. A multivariate analysis identified risk factors for 1-year mortality in the late era. Patients without these risk factors were compared with the nACHD group by Kaplan-Meier analysis.
Results:
A total of 495 patients with ACHD were identified from 2000 to 2008, and 666 were identified from 2009 to 2018. The recent era had better 1-year survival (P <.001) and overall survival (P = .003) than did the era from 2000 to 2008. Patients with ACHD were different from the nACHD population in age (37 years vs 57 years), body mass index greater than 25 kg/m2 (45% vs 66%), incidence of renal dysfunction (23% vs 28%) and liver dysfunction (29% vs 23%), sensitization (38% vs 29%), and ischemic times (3.5 hours vs 3.1 hours). Multivariate analysis identified body mass index greater than 25 kg/m2 (hazard ratio [HR], 1.79), renal dysfunction (HR, 1.85), liver dysfunction (HR, 1.69), and longer ischemic time (HR, 1.46) as risk factors for early mortality. Patients with only 1 of the first 3 categorical risk factors had 1-year survival comparable to that reported in patients with nACHD.
Conclusions:
Patients with ACHD had better early and long-term outcomes in the recent era. When only 1 of 3 pretransplant risk factors for early mortality was present, patients had survival equal to that of nACHD patients and perhaps better long-term survival.

Related Concept Videos
 01:15
Expected Value
 01:18
Physiology of the Heart: The Cardiac Cycle
Diastole: The Relaxation Phase
During diastole, all four heart chambers relax. The atrioventricular (AV) valves open, and the semilunar valves close. This phase sees the lowest chamber pressures, promoting ventricular filling. Venous blood enters the heart through the...
 01:19
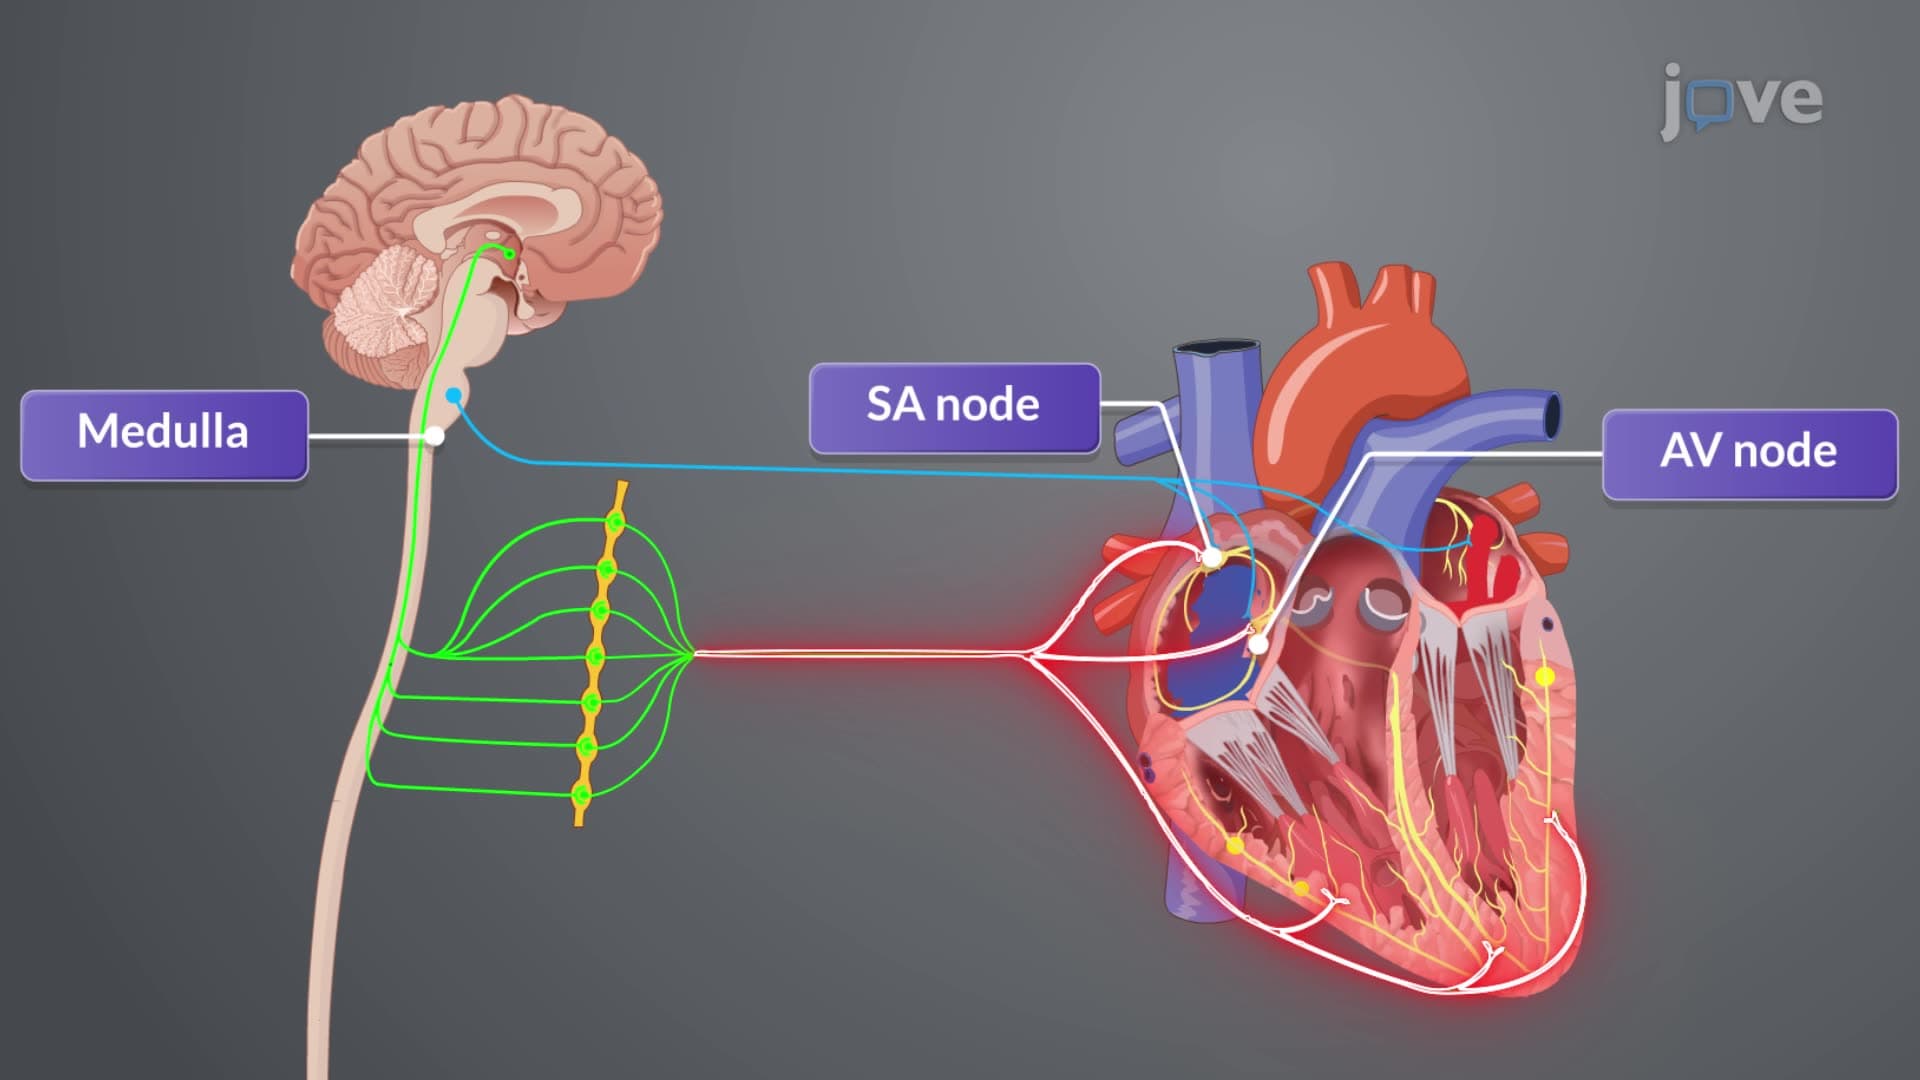
Cardiac Output I:Effect of Heart Rate on Cardiac Output
Cardiac output (CO) refers to the total amount of blood ejected by one of the ventricles in liters per minute (L/min). In a resting adult, CO ranges from 5 to 6 L/min, adjusting according to the body's metabolic requirements.
Effect of Heart Rate on Cardiac Output
Cardiac output adapts to metabolic demands during stress, physical activity, or illness. The autonomic nervous system regulates heart rate via the sinoatrial node. The parasympathetic nervous system decreases heart...
 01:21
Cardiac Catheterization II: Right Heart Catheterization
 01:23
Rheumatic Heart Disease I: Introduction
 01:17
Ischemic Heart Disease: Overview
Atherosclerosis, the primary malefactor, orchestrates this dangerous condition. It manifests as the accumulation of fatty deposits, akin to insidious plaques, within arterial walls. As time elapses, these plaques metamorphose, hardening and...