Related Experiment Video
Updated: Jan 20, 2026

Surgical Model for Single-Staged Tissue-Engineered Urothelial Tubes in Minipigs
Published on: July 5, 2024
Development and Validation of an Improved Pathological Nodal Staging System for Urothelial Carcinoma of the Bladder
Devin N Patel1, Michael Luu2, Zachary S Zumsteg3
1Department of Surgery, Division of Urology, Cedars-Sinai Medical Center, Los Angeles, CA, USA.

Background:
Current pathological nodal staging for bladder cancer is based on lymph node (LN) location but not on the number of positive LNs.
Objective:
We sought to improve prognostic classification by creating a novel staging system incorporating positive LN burden.
Design, Setting, And Participants:
We sampled 12515 patients with muscle-invasive bladder cancer (MIBC) from the National Cancer Database (NCDB) and 5928 MIBC patients from the Surveillance, Epidemiology, and End Results (SEER) database for our development and validation cohorts, respectively.
Outcome Measurements And Statistical Analysis:
Multivariable Cox proportional hazards analysis with restricted cubic splines was used to assess the association between the number of metastatic LNs and overall mortality (OM). A novel staging system was derived by recursive partitioning analysis (RPA) in NCDB and was validated in SEER by assessing discrimination (Harrel's c-index) and calibration (mean absolute prediction error).
Results And Limitations:
Mortality risk increased continuously with more metastatic LNs; the effect was most pronounced up to four LNs (hazard ratio [HR] 1.17, 95% confidence interval [CI] 1.12-1.22) and attenuated beyond four nodes (HR 1.03, 95% CI 1.02-1.05). RPA generated a novel staging system predicting mortality by metastatic nodal number with cutpoints at zero (reference), one (HR 1.57, 95% CI 1.46-1.69), two to three (HR 2.03, 95% CI 1.88-2.19), four to seven (HR 2.46, 95% CI 2.25-2.70), and more than seven (HR 3.83, 95% CI 3.38-4.33) positive LNs. Location of LN involvement was not a significant predictor of OM. In external validation, the novel staging system showed good risk discrimination (optimism corrected c-index 0.677, 95% CI 0.672-0.682) and calibration (mean absolute prediction error 0.011 for 5-yr OM). Results are limited by development and validation using secondary data.
Conclusions:
The number of metastatic LNs predicts mortality better than LN location and may improve pathological nodal staging in MIBC.
Patient Summary:
This retrospective study found that the number of metastatic lymph nodes more accurately predicts survival than the location of metastatic lymph nodes in patients with muscle-invasive bladder cancer. This finding argues for change to the current bladder cancer staging system.
More Related Videos
 11:02
Induction of Invasive Transitional Cell Bladder Carcinoma in Immune Intact Human MUC1 Transgenic Mice: A Model for Immunotherapy Development
Published on: October 30, 2013
 09:28
Patient-derived Orthotopic Xenograft Models for Human Urothelial Cell Carcinoma and Colorectal Cancer Tumor Growth and Spontaneous Metastasis
Published on: May 12, 2019
Related Concept Videos
 01:10
Nodal Analysis
Consider, for instance, a simple circuit composed of three nodes and three resistors, as shown in...
 01:14
Piaget's Stage 1 of Cognitive Development
Exploration...
 01:14
Piaget's Stage 2 of Cognitive Development
 01:19
Piaget's Stage 4 of Cognitive Development
Abstract Reasoning and Hypothetical-Deductive Thinking
Unlike the concrete operational...
 01:17
Piaget's Stage 3 of Cognitive Development
Conservation and Constancy of Quantity
A significant cognitive milestone in the...
 01:11
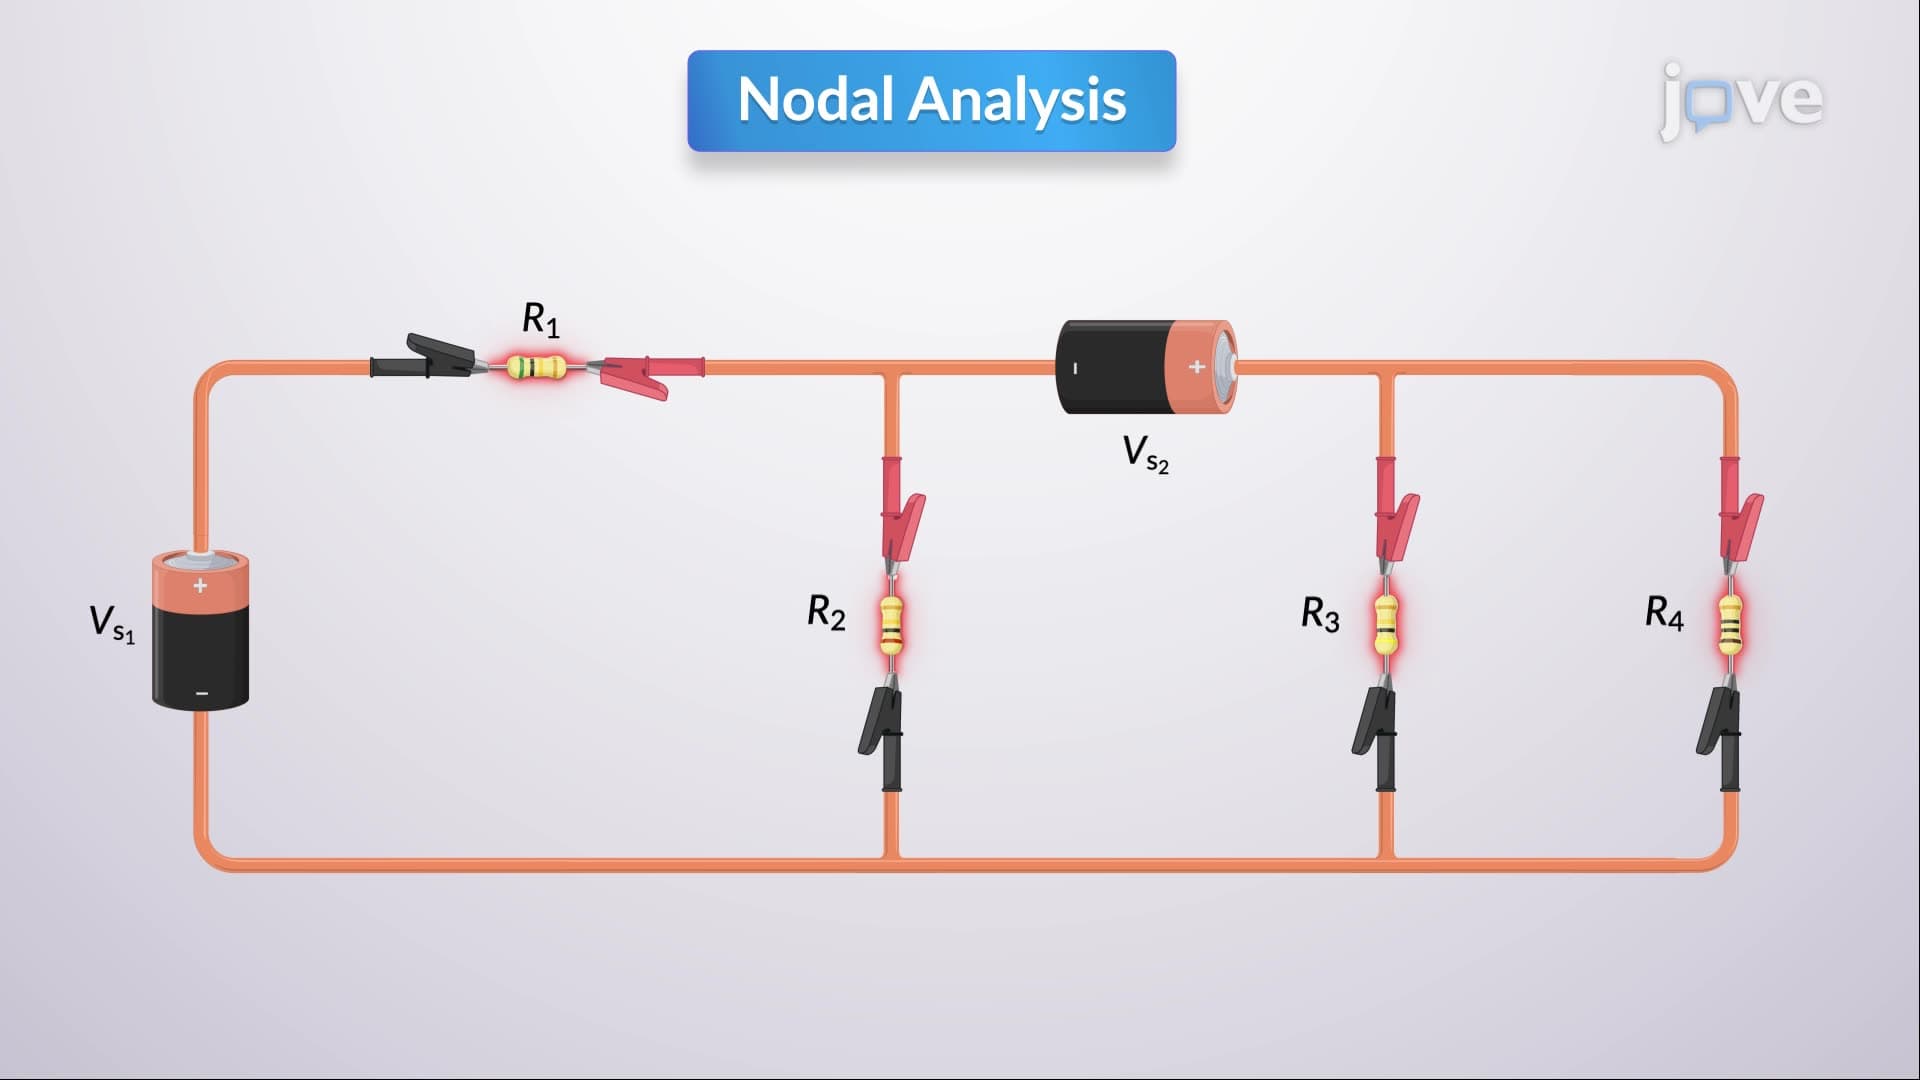
Nodal Analysis with Voltage Sources
Consider a circuit that contains four resistors and two voltage sources, as shown in Figure 1. One of these voltage sources is connected between a...