Related Experiment Video
Updated: Jan 20, 2026


Radiation Planning Assistant - A Streamlined, Fully Automated Radiotherapy Treatment Planning System
Published on: April 11, 2018
Radiation treatment planning with embedded dose escalation
William T Hrinivich1, Todd R McNutt2, Jeffrey J Meyer2
1Dept. of Radiation Oncology and Molecular Radiation Sciences, Johns Hopkins University School of Medicine, 401 N Broadway St. Weinberg Suite 1440, Baltimore, MD, 21231, USA. whriniv1@jhmi.edu.

Background:
Heterogeneous target doses are a common by-product from attempts to improve normal tissue sparing in radiosurgery treatment planning. These regions of escalated dose within the target may increase tumor control probability (TCP). Purposely embedding hot spots within tumors during optimization may also increase the TCP. This study discusses and compares five optimization approaches that not only eliminate homogeneity constraints, but also maximize heterogeneity and internal dose escalation.
Methods:
Co-planar volumetric modulated arc therapy (VMAT) plans were produced for virtual spherical targets with 2-8 cm diameters, minimum target dose objectives of 25 Gy, and objectives to minimize normal tissue dose. Five other sets of plans were produced with additional target dose objectives: 1) minimum dose-volume histogram (DVH) objective on 10% of the target 2) minimum dose objective on a sub-structure within the target, and 3-5) minimum generalized equivalent uniform dose (gEUD) objectives assuming three different volume-effect parameters. Plans were normalized to provide equivalent maximum OAR dose and were compared in terms of target D0.1 cc, ratio of V12.5 Gy to PTV volume (R50%), monitor units per 5 Gy fraction (MU), and mean multi-leaf collimator (MLC) segment size. All planning approaches were also applied to a clinical patient dataset and compared.
Results:
Mean ± standard deviation metrics achievable using the baseline and experimental approaches 1-5) included D0.1 cc: 27.7 ± 0.8, 64.6 ± 10.5, 56.5 ± 10.3, 48.9 ± 5.7, 44.8 ± 5.0, and 37.4 ± 4.5 Gy. R50%: 4.64 ± 3.27, 5.15 ± 2.32, 4.83 ± 2.64, 4.42 ± 1.83, 4.45 ± 1.88, and 4.21 ± 1.75. MU: 795 ± 27, 1988 ± 222, 1766 ± 259, 1612 ± 112, 1524 ± 90, and 1362 ± 146. MLC segment size: 4.7 ± 1.6, 2.3 ± 0.7, 2.6 ± 0.8, 2.7 ± 0.7, 2.7 ± 0.8, and 2.8 ± 0.8 cm.
Conclusions:
The DVH-based approach provided the highest embedded doses for all target diameters and patient example with modest increases in R50%, achieved by decreasing MLC segment size while increasing MU. These results suggest that embedding doses > 220% of tumor margin dose is feasible, potentially improving TCP for solid tumors.
More Related Videos
 07:57
Positron Emission Tomography-based Dose Painting Radiation Therapy in a Glioblastoma Rat Model using the Small Animal Radiation Research Platform
Published on: March 24, 2022
 06:20
Irradiator Commissioning and Dosimetry for Assessment of LQ α and β Parameters, Radiation Dosing Schema, and in vivo Dose Deposition
Published on: March 11, 2021
Related Concept Videos
 02:59
Biological Effects of Radiation
 01:23
Sampling Plans
Random sampling is a method where each member of the population has an equal chance of being selected for the sample. It involves selecting individuals randomly, often using random number generators or lottery-type methods. For example, when analyzing the properties of a...
 01:17
Radiation: Applications
The average...
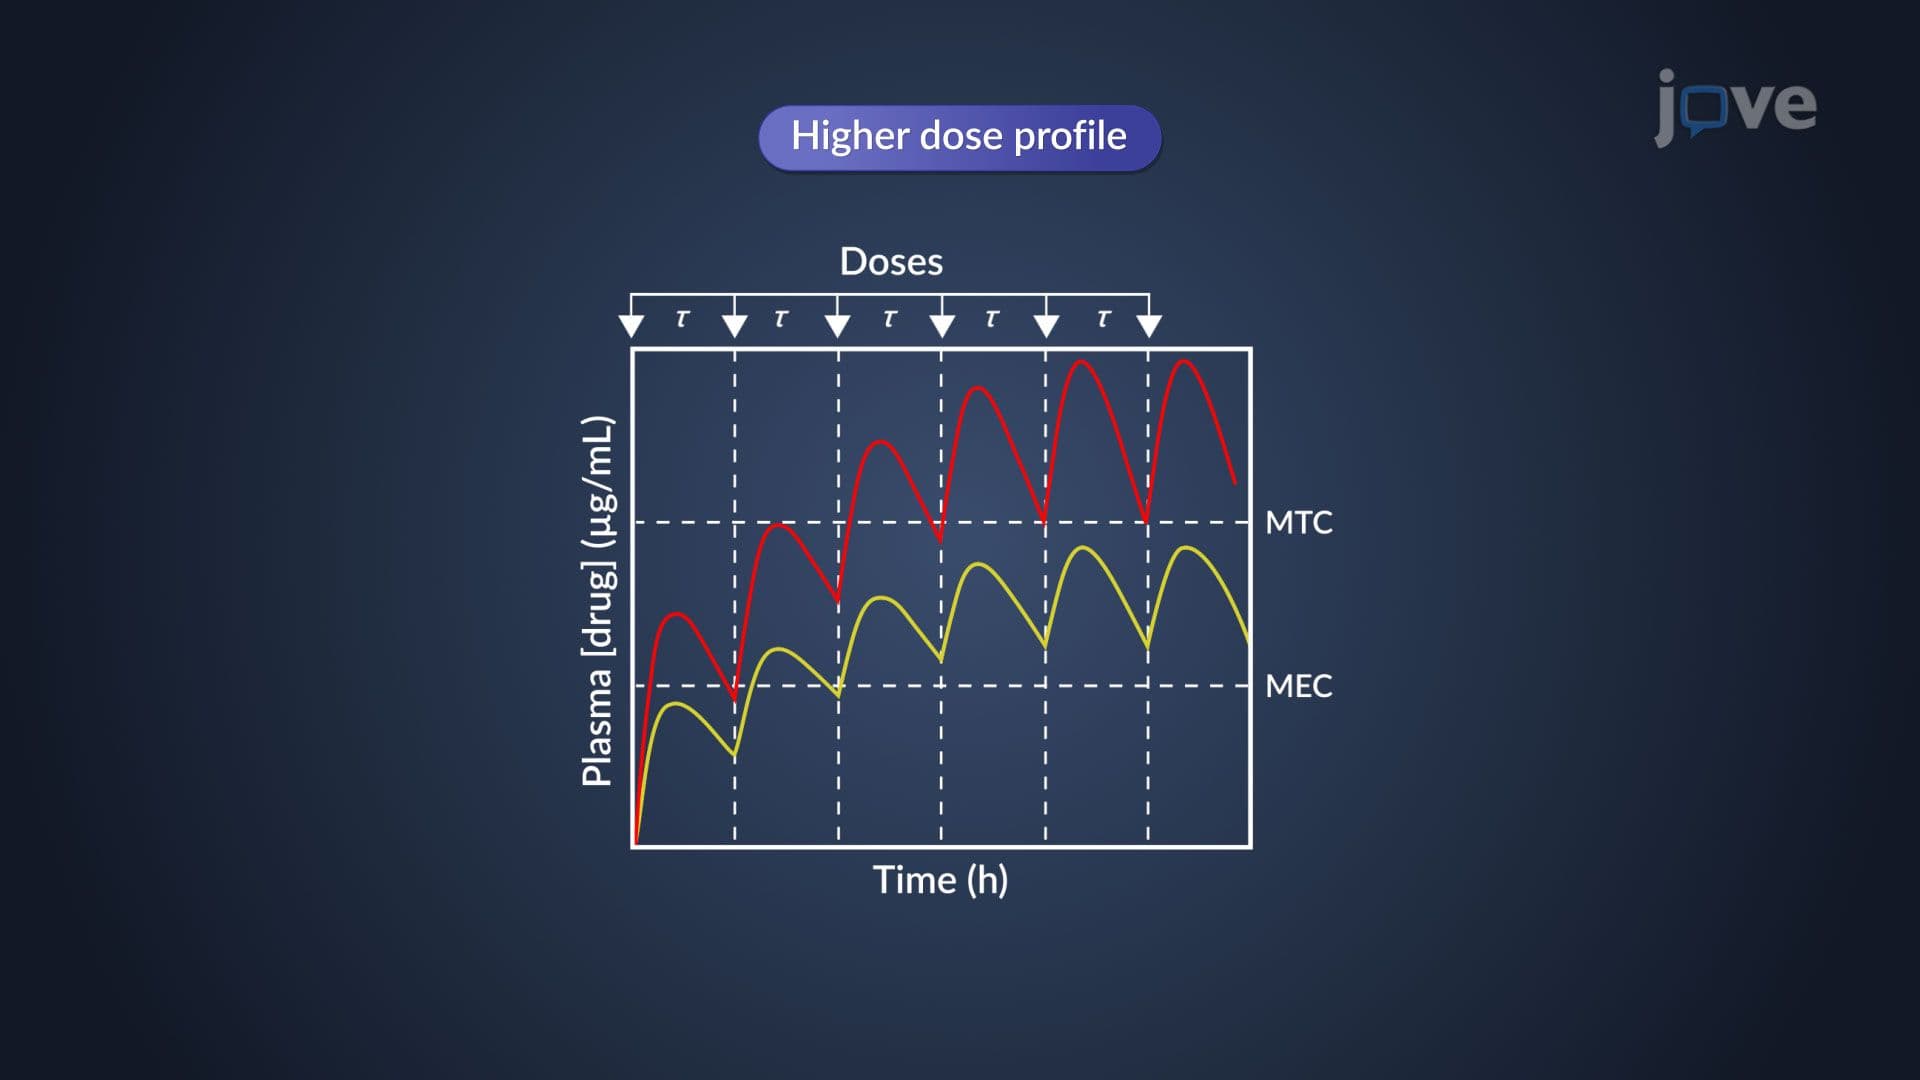 01:21
Dose Size and Dosing Frequency: Determination Methods
 01:25
Determination of Multiple Dosing Parameters: Loading and Maintenance Doses
 01:05
Absorption of Radiation