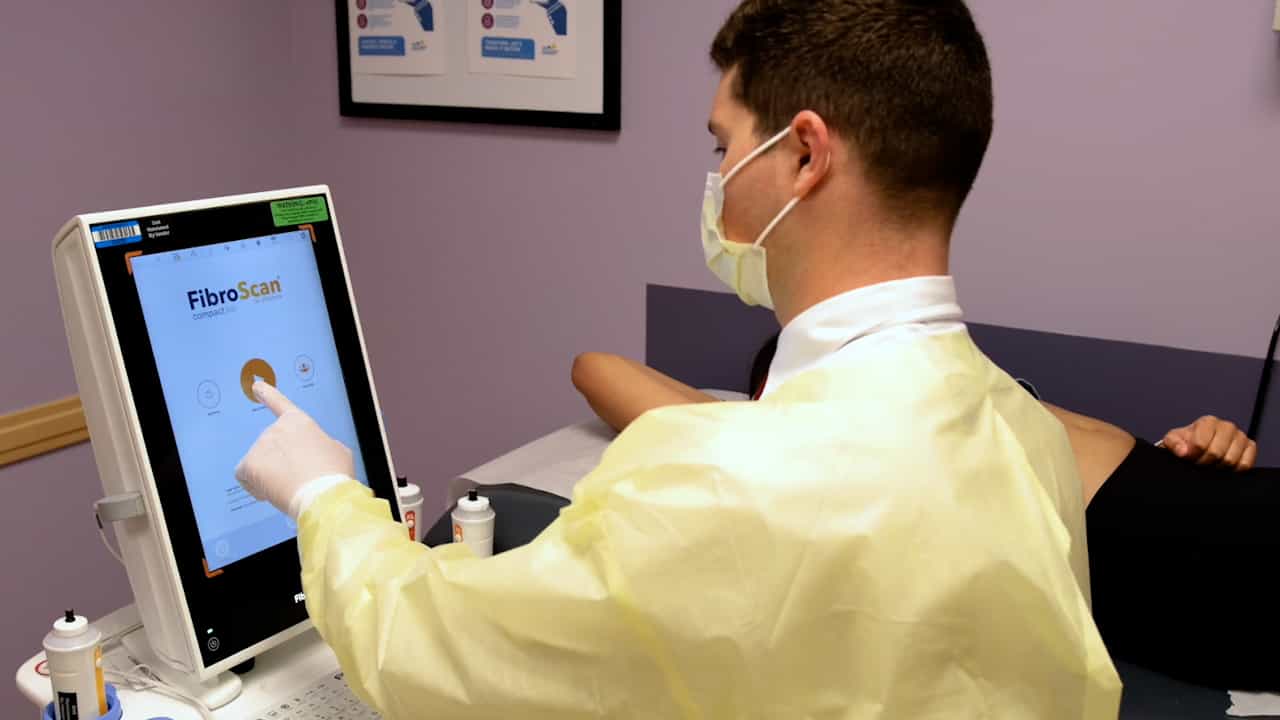

Shear wave elastography correlates with liver fibrosis scores in pediatric patients with liver disease
Shannon G Farmakis1, Paula M Buchanan2, Miguel A Guzman3
1Department of Radiology, SSM Health Cardinal Glennon Children's Hospital and St. Louis University School of Medicine, 3635 Vista Avenue at Grand Boulevard, St. Louis, MO, 63110, USA. shannon.farmakis@health.slu.edu.

Background:
While liver biopsy remains the gold standard, given the procedure risks and sampling errors, there is a need for reliable noninvasive biomarkers of hepatic fibrosis.
Objective:
Determine the accuracy of two-dimensional shear wave elastography (2-D SWE) in predicting the histological severity of liver fibrosis in pediatric patients with known or suspected liver disease.
Materials And Methods:
Subjects 0-18 years old with known or suspected liver disease and liver biopsy within 30 days (n=70) were included. Comparisons by 2-D SWE were made to a control group (n=79). Two-dimensional SWE was performed using the GE LOGIQ E9 system. Liver biopsy specimens were scored according to METAVIR and Ishak scoring systems using Spearman's Rho correlation. Receiver operator characteristic (ROC) analysis, Kruskal-Wallis and Mann-Whitney U tests were conducted.
Results:
Control group median 2-D SWE measurements were lower than in subjects with any degree of liver fibrosis (P<0.001). Those with METAVIR F0 and Ishak 0 scores had significantly lower median 2-D SWE measurements (1.35 m/s; 1.36 m/s) than those with more advanced liver disease (F1-F3: 1.49-1.62 m/s; 1-4: 1.45-1.63 m/s) (P<0.05 for all), whereas the 2-D SWE in the higher scores were similar. Results did not differ between METAVIR and Ishak scores for any degree of fibrosis. Fibrosis scores moderately correlated with median 2-D SWE measurements (rs=0.43). The area under the curve for F1 compared to combined control/F0 was 0.89 (95% confidence interval [CI] 0.83-0.95; P<0.001) with sensitivity of 94.6% and specificity of 78.6%. Results for Ishak score 1 were similar. The ideal cutoff value for identifying fibrosis was determined to be 1.29 m/s.
Conclusion:
The liver 2-D SWE measurements correlated with the histological liver fibrosis scores, regardless of the histopathological scoring system, although 2-D SWE was better at identifying patients with early fibrosis, not at distinguishing among the individual fibrosis levels. Two-dimensional SWE using the GE LOGIQ US system is useful for identifying pediatric patients at risk for liver fibrosis.

Related Concept Videos
 01:26
Diseases of the Liver and Gallbladder
Cirrhosis is characterized by the scarring of hepatic lobules in the liver, which are replaced by fibrous tissue, affecting the liver's normal functioning. NAFLD, on the other hand, is caused by an excessive build-up of fat in the liver, not...
 01:22
Effect of Hepatic Disease on Pharmacokinetics: Pathophysiologic Assessment and Liver Function Test
 01:27
Liver Histology
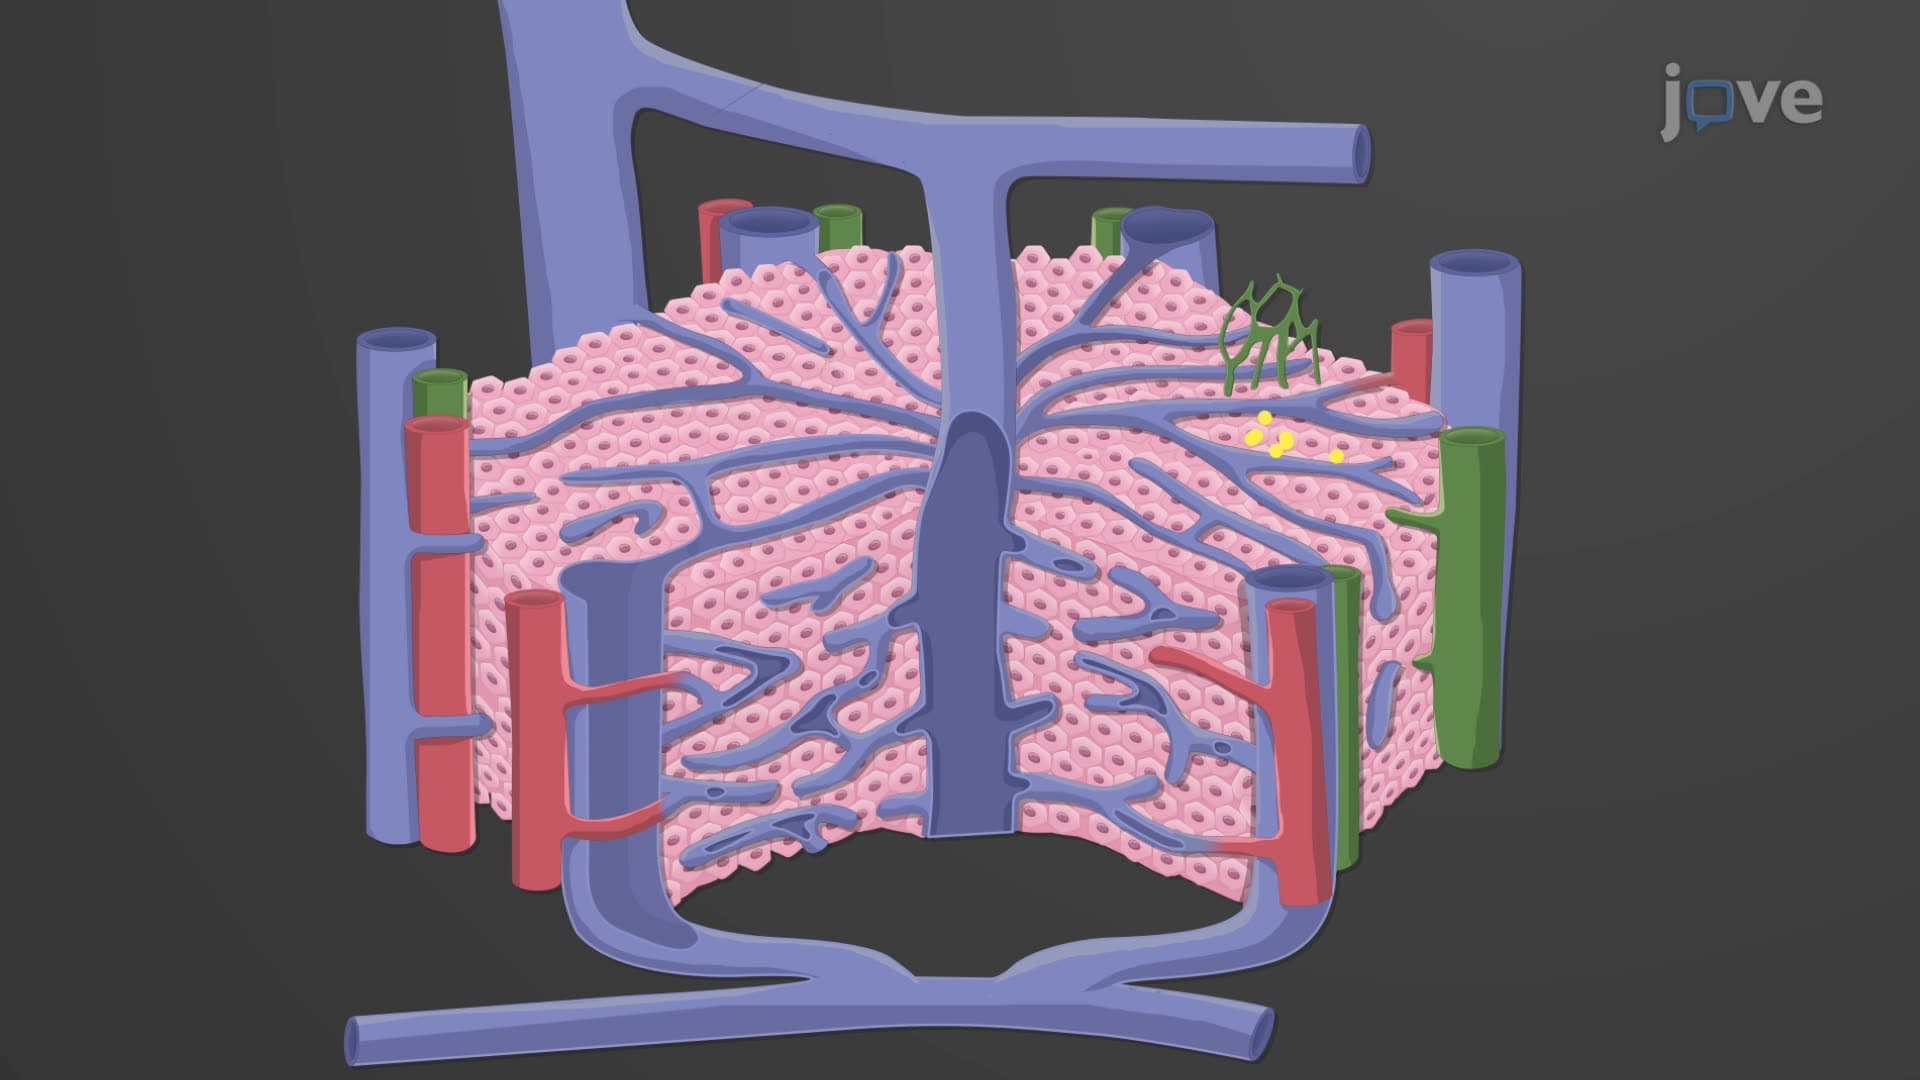
Hepatocytes perform a variety of essential functions. They secrete...
 01:30
Liver Physiology
Metabolic Regulation:
The liver is the central organ involved in regulating blood composition. It stabilizes blood glucose levels, maintaining them within the range of 70–110 mg/dL. When these levels drop, the liver breaks down glycogen reserves and releases glucose into the bloodstream. It can...
 01:24
Liver Regeneration
Cells of Liver
The liver comprises four major types of cells— hepatocytes, stellate, Kupffer, and sinusoidal endothelial cells. The hepatocytes are...
 01:17
Gross Anatomy of the Liver
Located under the diaphragm, the liver is almost entirely ensconced within the rib cage, providing it with substantial protection. Except for the superior most bare area, the liver's surface is...