Related Experiment Video
Updated: Jan 20, 2026

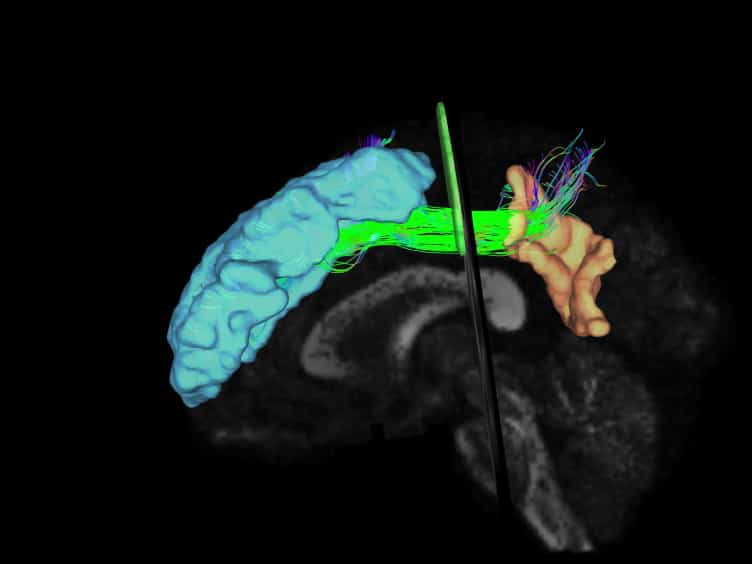
DTI of the Visual Pathway - White Matter Tracts and Cerebral Lesions
Published on: August 26, 2014
Intraoperative acquisition of DTI in cranial neurosurgery: readout-segmented DTI versus standard single-shot DTI
Cameron A Elliott1, Hayden Danyluk2, Keith E Aronyk1
11Division of Neurosurgery.

Objective:
Diffusion tensor imaging (DTI) tractography is commonly used in neurosurgical practice but is largely limited to the preoperative setting. This is due primarily to image degradation caused by susceptibility artifact when conventional single-shot (SS) echo-planar imaging (EPI) DTI (SS-DTI) is acquired for open cranial, surgical position intraoperative DTI (iDTI). Readout-segmented (RS) EPI DTI (RS-DTI) has been reported to reduce such artifact but has not yet been evaluated in the intraoperative MRI (iMRI) environment. The authors evaluated the performance of RS versus SS EPI for DTI of the human brain in the iMRI setting.
Methods:
Pre- and intraoperative 3-T 3D T1-weighted and 2D multislice RS-iDTI (called RESOLVE [readout segmentation of long variable echo-trains] on the Siemens platform) and SS-iDTI images were acquired in 22 adult patients undergoing intraaxial iMRI resections for suspected low-grade glioma (14; 64%), high-grade glioma (7; 32%), or focal cortical dysplasia. Regional susceptibility artifact, anatomical deviation relative to T1-weighted imaging, and tractographic output for surgically relevant tracts were compared between iDTI sequences as well as the intraoperative tract shifts from preoperative DTI.
Results:
RS-iDTI resulted in qualitatively less regional susceptibility artifact (resection cavity, orbitofrontal and anterior temporal cortices) and mean anatomical deviation in regions most prone to susceptibility artifact (RS-iDTI 2.7 ± 0.2 vs SS-iDTI 7.5 ± 0.4 mm) compared to SS-iDTI. Although tract reconstruction success did not significantly differ by DTI method, susceptibility artifact-related tractography failure (of at least 1 surgically relevant tract) occurred for SS-iDTI in 8/22 (36%) patients, and in 5 of these 8 patients RS-iDTI permitted successful reconstruction. Among cases with successful tractography for both sequences, maximal intersequence differences were substantial (mean 9.5 ± 5.7 mm, range -27.1 to 18.7 mm).
Conclusions:
RS EPI enables higher quality and more accurate DTI for surgically relevant tractography of major white matter tracts in intraoperative, open cranium neurosurgical applications at 3 T.
Related Concept Videos
 01:19
Cranial and Spinal Meninges
Cranial Meninges
These meningeal layers cover the cranium. The dura mater is the outermost layer of cranial meninges. It is a thick and durable membrane of dense...
 02:16
Light Acquisition
 01:14
Cranial Nerves: Types Part I
Olfactory Nerve (Cranial Nerve I)
The olfactory nerve, or cranial nerve I, is unique as it is purely sensory and dedicated to the sense of smell. This nerve originates in the olfactory epithelium of the...
 01:22
Cranial Nerves: Types Part II
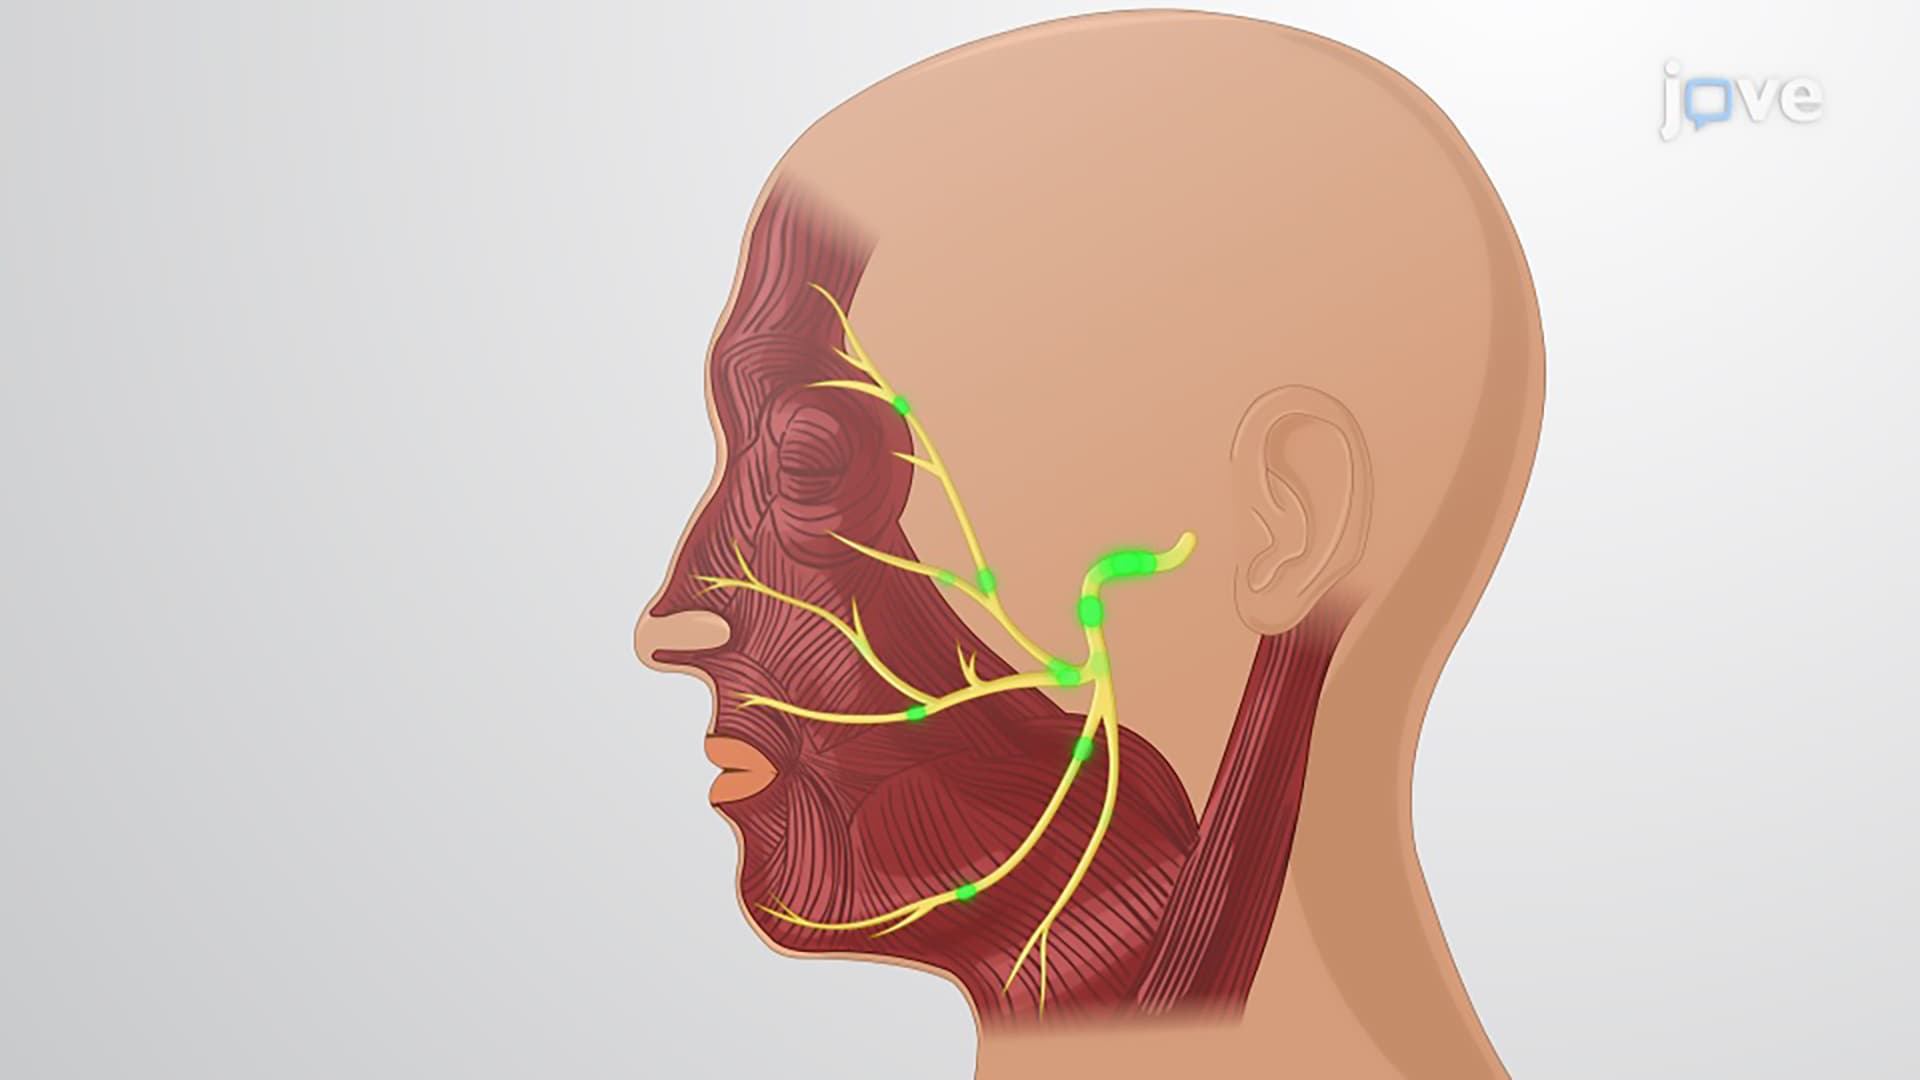
Facial Nerve (Cranial Nerve VII)
Cranial nerve VII, or the facial nerve,...
 01:18
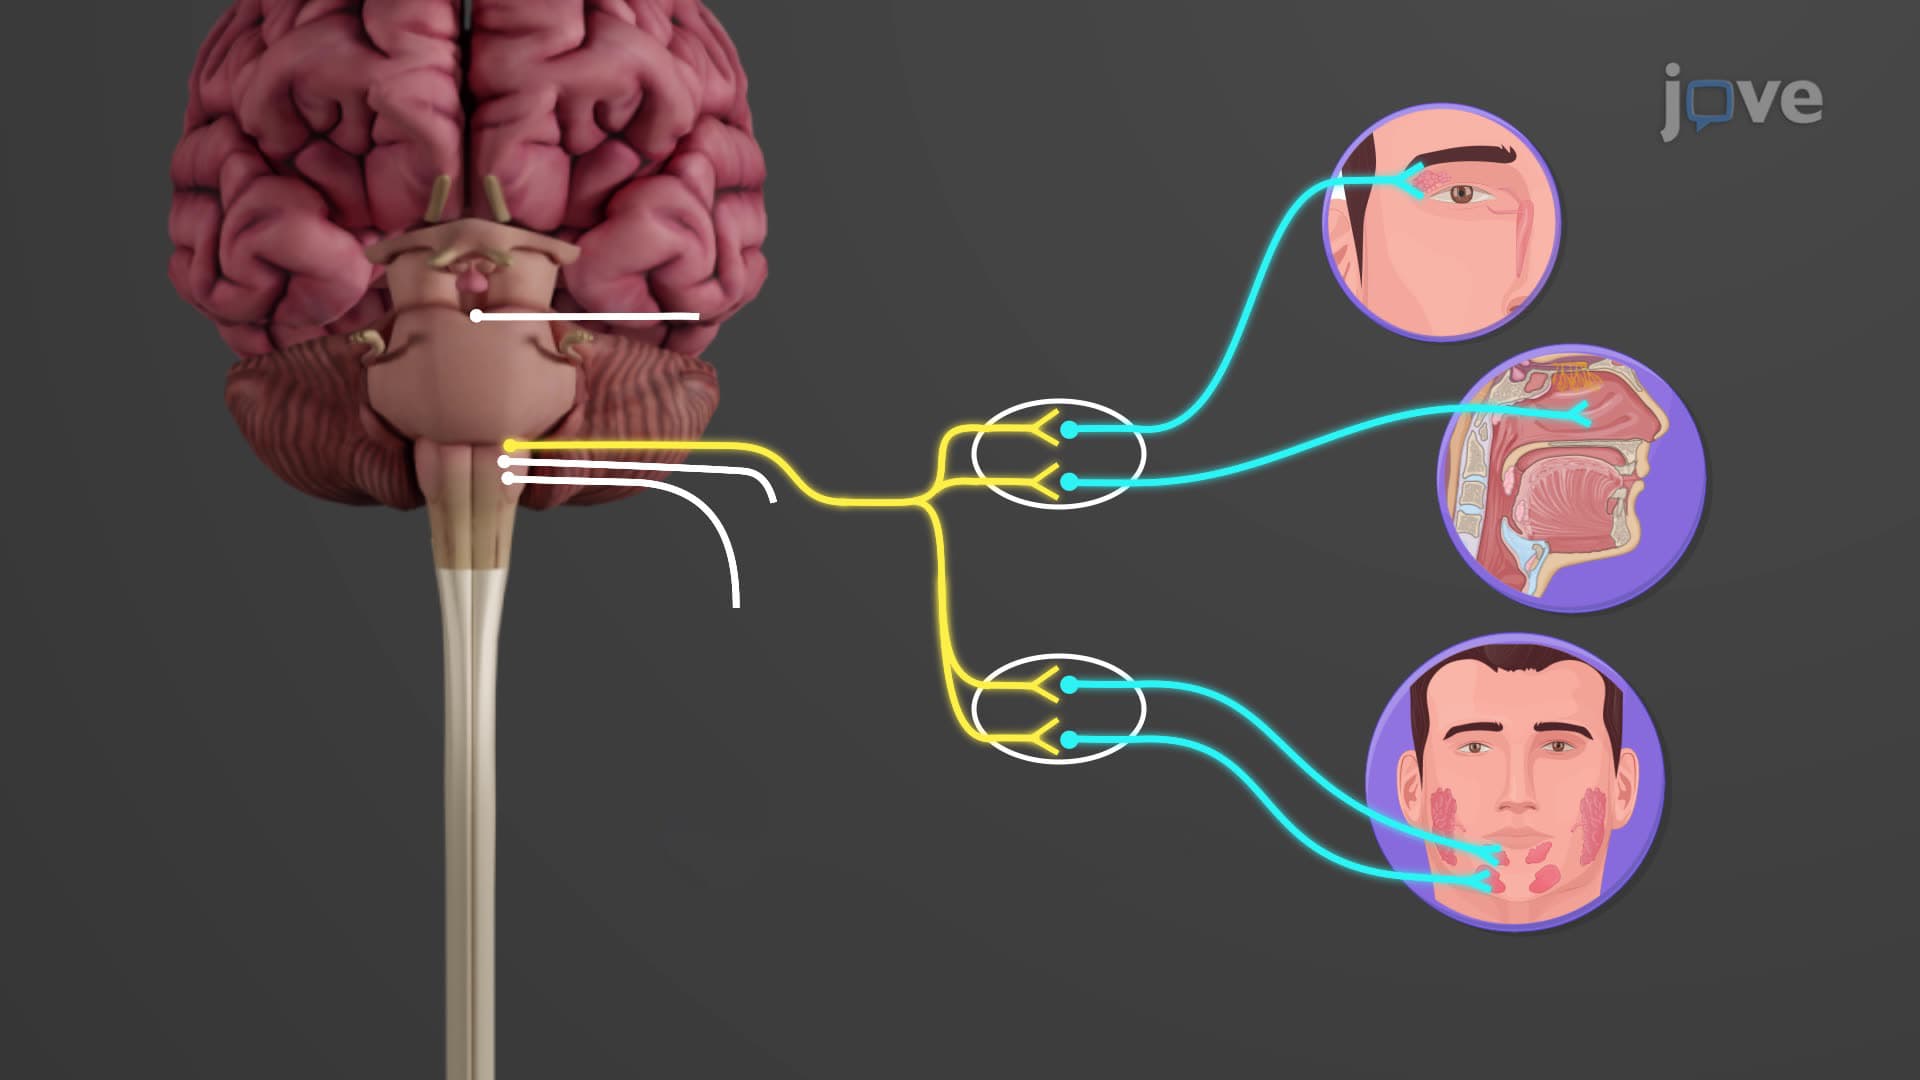
Cranial Part of Parasympathetic Division
The vagus nerve (cranial nerve X) alone accounts for approximately 75...
 02:37
Standard Enthalpy of Formation