Related Experiment Video
Updated: Jan 20, 2026
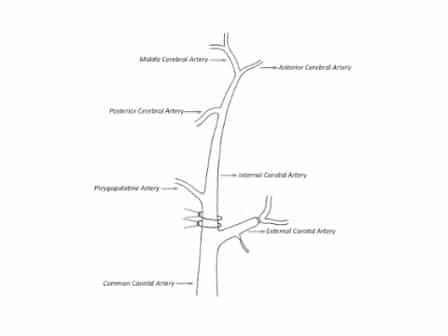
Intraluminal Middle Cerebral Artery Occlusion MCAO Model for Ischemic Stroke with Laser Doppler Flowmetry Guidance in Mice
Published on: May 8, 2011
Risk of Serious Bleeding with Antiplatelet Therapy for Secondary Prevention Post Ischemic Stroke in Middle East
Zeinab Awada1, Rim Abboud2, Samer Nasr3
1Internal Medicine, Lebanese American University-Medical Center, Beirut, LBN.

Insights
Dual antiplatelet therapy (DAPT) and high-dose aspirin increase stroke patients' bleeding risk, particularly between three months and one year. Advanced age and smoking further elevate this risk.
Area of Science:
- Neurology
- Cardiology
- Pharmacology
Background:
- Stroke is a leading cause of mortality and disability globally.
- Atherothrombosis is a primary cause of ischemic stroke, necessitating antiplatelet therapy for secondary prevention.
- Existing antiplatelet therapies like aspirin and clopidogrel monotherapy reduce recurrent stroke risk, but safety concerns persist, especially regarding bleeding complications in stroke patients.
Purpose of the Study:
- To assess the risk of serious bleeding in adult stroke patients undergoing antiplatelet therapy for secondary prevention.
- To evaluate the impact of different antiplatelet therapies, including dosage and combinations, on bleeding risk.
- To identify patient-related factors contributing to increased bleeding risk.
Main Methods:
- A retrospective monocentric study involving 454 patients admitted for ischemic cerebrovascular accident (CVA) between 2010 and 2015.
- Patients were discharged on antiplatelet therapy for secondary stroke prevention.
- Patient records were analyzed to determine the incidence of major bleeding events post-therapy initiation.
Main Results:
- The highest risk of serious bleeding was observed with aspirin 100 mg monotherapy and dual antiplatelet therapy (DAPT) (Aspirin 100 mg + Clopidogrel 75 mg).
- Bleeding risk was elevated within the first three months of therapy, with the highest incidence occurring between three months and one year.
- Advanced age and smoking were identified as significant patient-related factors increasing bleeding risk.
Conclusions:
- Aspirin 100 mg monotherapy and DAPT are associated with the highest bleeding risk in stroke patients.
- This elevated bleeding risk persists throughout antiplatelet therapy but is most pronounced between three months and one year post-initiation.
- Patient factors such as advanced age and smoking significantly contribute to the risk of bleeding complications.
Abstract:
Introduction Stroke is a devastating disease, causing significant mortality and long-term disability worldwide. Since the bulk of ischemic strokes is attributed to atherothrombosis, secondary prevention with antiplatelet agents is essential to decrease the recurrence of stroke. Aspirin, as well as clopidogrel monotherapy, has been shown to reduce the relative risk of recurrent stroke. However, concerns regarding the efficacy and safety of dual antiplatelet approach still exist. Stroke patients are particularly susceptible to bleeding complications, which might be due to advanced age and comorbidities. Our study assessed the risk of serious bleeding among adult patients on antiplatelet therapy for secondary prevention after stroke who were admitted to Mount Lebanon Hospital (MLH) between 2010 and 2015. It also studied the effect of the antiplatelet therapy, including dose and combination in increasing the risk of bleed. Methods A retrospective monocentric study included 454 patients who were admitted for ischemic cerebrovascular accident (CVA) between 2010 and 2015, and discharged on antiplatelet therapy for secondary prevention. Those patients' records were followed to assess the percentage of patients who developed a major bleed after initiation of antiplatelet therapy. Results The risk of serious bleed was highest with aspirin 100 mg monotherapy and dual antiplatelet therapy (DAPT) (Aspirin 100 mg + Clopidogrel 75 mg). Bleeding risk was high during the first three months of therapy. However, the highest risk of bleed exists during the duration extending between three months and one year for both aspirin 100 mg monotherapy and DAPT. Moreover, there was an established relation between patients' related factors and bleeding risk. Advanced age and smoking were found to contribute to increasing this risk. Conclusion Aspirin 100 mg monotherapy and DAPT are associated with the highest risk of bleeding. Although this exists regardless of the duration of antiplatelet therapy, it is highest during the duration extending between three months and one year post initiation of antiplatelet therapy.
Related Concept Videos
 01:27
Urinary Tract Calculi IV: Nutrition Therapy and Prevention
 02:04
Conservation of Small Populations
 01:55
Secondary Active Transport
 01:22
Bleeding in Fresh Concrete
Bleeding can cause several issues in the concrete structure. Sometimes, the rising water gets trapped beneath large aggregate...
 01:11
Secondary Healthcare System
 01:25
What is Population Genetics?