Successful revascularization versus medical therapy in diabetic patients with stable right coronary artery chronic total occlusion: a retrospective cohort study
Related Experiment Video
Updated: Jan 20, 2026
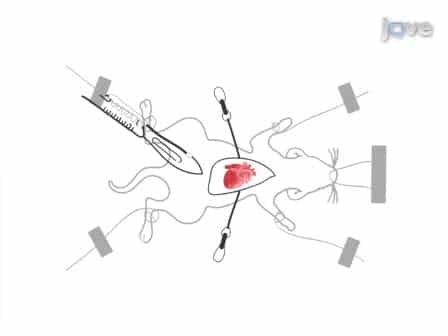
Use of a Hanging Weight System for Coronary Artery Occlusion in Mice
Published on: April 19, 2011
Yunfeng Yan1, Mingduo Zhang1, Fei Yuan1
1Department of Cardiology, Beijing Anzhen Hospital, Capital Medical University, Beijing Institute of Heart, Lung and Blood Vessel Diseases, 2 Anzhen Road, Chaoyang District, Beijing, 100029, China.

Insights
For diabetic patients with stable right coronary artery chronic total occlusion (CTO), successful revascularization significantly reduces the risk of death compared to medical therapy. Coronary artery bypass grafting may offer additional benefits for repeat revascularization.
Area of Science:
- Cardiology
- Interventional Cardiology
- Diabetology
Background:
- Conflicting evidence exists regarding the necessity of reopening stable right coronary artery chronic total occlusion (RCA-CTO).
- Diabetic patients with coexisting coronary artery disease face severe health challenges.
- The optimal management strategy for stable RCA-CTO in diabetic patients remains unclear.
Purpose of the Study:
- To investigate the necessity of reopening stable RCA-CTO in diabetic patients.
- To compare the clinical outcomes of successful revascularization versus medical therapy for stable RCA-CTO in this population.
Main Methods:
- A cohort of 943 diabetic patients with symptomatic stable angina or silent ischemia due to RCA-CTO was analyzed.
- Patients were divided into successful revascularization (CTO-SR) and medical therapy (CTO-MT) groups.
- Cox regression and propensity score matching analyses were employed to evaluate all-cause death, with sensitivity analyses performed.
Main Results:
- Successful revascularization (CTO-SR) was associated with significantly lower all-cause mortality compared to medical therapy (CTO-MT) (adjusted HR: 0.429-0.445).
- CTO-SR demonstrated superiority in reducing cardiac death, repeat revascularization, and myocardial infarction.
- Subgroup analyses showed mortality benefits for CTO-SR via percutaneous coronary intervention (PCI) and greater benefits in repeat revascularization with coronary artery bypass grafting (CABG).
Conclusions:
- Successful revascularization provides significant clinical benefits for diabetic patients with stable RCA-CTO compared to medical management.
- Coronary artery bypass grafting (CABG) may be a preferred revascularization strategy for improved repeat revascularization outcomes.
Background:
The territory of the right coronary artery (RCA) is smaller than that of the left anterior descending artery. Previous studies have reported conflicting results when considering whether stable RCA-chronic total occlusion (CTO) should be reopened. The coexistence of diabetic and coronary artery diseases represents a severe situation. Therefore, we aimed to determine if stable RCA-CTO in diabetic patients was necessary to be reopened. To our knowledge, no studies have focused on this topic to date.
Methods:
We enrolled diabetic patients with RCA-CTO who had clinical presentations of symptomatic stable angina or silent ischemia. RCA-CTO was treated with either successful revascularization (the CTO-SR group) or medical therapy (the CTO-MT group). The primary endpoint was all-cause death. Both Cox regression and propensity score matching analyses were used. Sensitivity analysis was performed based on subgroup populations and relevant baseline variables.
Results:
A total of 943 patients were included: 443 (46.98%) patients in the CTO-MT group and 500 (53.02%) patients in the CTO-SR group. After a mid-term follow-up (CTO-SR: 48 months; CTO-MT: 42 months), we found that CTO-SR was superior to CTO-MT in terms of all-cause death (adjusted hazard ratio [HR] [model 1]: 0.429, 95% conference interval [CI] 0.269-0.682; adjusted HR [model 2]: 0.445, 95% CI 0.278-0.714). The superiority of CTO-SR was consistent for cardiac death, possible/definite cardiac death, repeat revascularization, target vessel revascularization (TVR) and repeat nonfatal myocardial infarction. Subgroup analysis confirmed the mortality benefit of CTO-SR by percutaneous coronary intervention (the successful CTO-PCI subgroup, 309 patients in total). While CTO-SR by coronary artery bypass grafting (the CTO-CABG subgroup, 191 patients in total) offered patients more benefit from repeat revascularization and TVR than that offered by successful CTO-PCI.
Conclusions:
For stable RCA-CTO patients with diabetes, successful revascularization offered patients more clinical benefits than medical therapy. CTO-CABG might be a more recommended way to accomplish revascularization. Trial registration This study was not registered in an open access database.


Related Concept Videos
 01:30
Coronary Artery Disease I: Introduction
 02:17
Ecological Succession
 01:26
Coronary Artery Disease II: Pathophysiology
 01:27
Coronary Artery Disease V: Interprofessional Care
 01:30
Coronary Artery Disease III: Clinical Manifestations
 01:26
Coronary Artery Disease IV: Preventive Measures