Related Experiment Video
Updated: Jan 20, 2026

Optimized Management of Endovascular Treatment for Acute Ischemic Stroke
Published on: January 18, 2018
Intravenous Thrombolysis for Acute Ischemic Stroke After Recent Myocardial Infarction: Case Series and Systematic
João Pedro Marto1,2, Linda Azevedo Kauppila3, Cláudia Jorge4
1From the Department of Neurology, Hospital Egas Moniz, Centro Hospitalar Lisboa Ocidental, Portugal (J.P.M., S.C., M.V.-B.).

Background and Purpose- The safety of IV r-tPA (intravenous tissue-type plasminogen activator) for acute ischemic stroke (AIS) treatment after recent myocardial infarction (MI) is still a matter of debate. We studied the safety of delivering IV r-tPA to AIS patients with a MI within the preceding 3 months. Methods- Retrospective review of consecutive AIS admitted to 2 tertiary university hospitals' and systematic literature review for AIS patients with history of MI in the previous 3 months. Patients were divided into 2 groups: treated or not treated with standard IV r-tPA dose for AIS. Cardiac complications (cardiac rupture/tamponade, intracardiac thrombus embolization, or life-threatening arrhythmias) were compared between groups and assessed by type of MI (non-ST-segment-elevation myocardial infarction [STEMI], or STEMI) and time elapsed between vascular events. Results- One hundred and two patients were included; 46 (45.1%) were derived from literature review. Median age (interquartile range) was 64 (53-75) years old, and 69 (67.6%) were men. Forty-seven (46.1%) received IV r-tPA. In the treated group, 25 (53.2%) and 23 (48.9%) patients had, respectively, concurrent AIS and MI and STEMI, in comparison with 12 (21.8%; P=0.002) and 36 (65.5%; P=0.110) patients in the nontreated. Four (8.5%) IV r-tPA-treated patients died from confirmed or presumed cardiac rupture/ tamponade, all with a STEMI in the week preceding stroke. This complication occurred in 1 (1.8%) patients in the nontreated group (P=0.178). There were no differences in thrombus embolization (1 [2.1%) versus 2 [3.6]; P=1.000) and life-threatening arrhythmias (3 [6.4%) versus 7 [12.7]; P=0.335). No non-STEMI patients receiving IV r-tPA had cardiac complications. Conclusions- In patients with AIS and recent or concurrent MI, MI type and the time elapsed between the 2 events should be taken into consideration when deciding to deliver IV r-tPA. Although recent non-STEMI or concurrent events seem safe, STEMI in the week preceding stroke should prompt caution. The low number of events and publication bias may have influenced our conclusions.
Background and Purpose- The safety of IV r-tPA (intravenous tissue-type plasminogen activator) for acute ischemic stroke (AIS) treatment after recent myocardial infarction (MI) is still a matter of debate. We studied the safety of delivering IV r-tPA to AIS patients with a MI within the preceding 3 months. Methods- Retrospective review of consecutive AIS admitted to 2 tertiary university hospitals' and systematic literature review for AIS patients with history of MI in the previous 3 months. Patients were divided into 2 groups: treated or not treated with standard IV r-tPA dose for AIS. Cardiac complications (cardiac rupture/tamponade, intracardiac thrombus embolization, or life-threatening arrhythmias) were compared between groups and assessed by type of MI (non-ST-segment-elevation myocardial infarction [STEMI], or STEMI) and time elapsed between vascular events. Results- One hundred and two patients were included; 46 (45.1%) were derived from literature review. Median age (interquartile range) was 64 (53-75) years old, and 69 (67.6%) were men. Forty-seven (46.1%) received IV r-tPA. In the treated group, 25 (53.2%) and 23 (48.9%) patients had, respectively, concurrent AIS and MI and STEMI, in comparison with 12 (21.8%; P=0.002) and 36 (65.5%; P=0.110) patients in the nontreated. Four (8.5%) IV r-tPA-treated patients died from confirmed or presumed cardiac rupture/ tamponade, all with a STEMI in the week preceding stroke. This complication occurred in 1 (1.8%) patients in the nontreated group (P=0.178). There were no differences in thrombus embolization (1 [2.1%) versus 2 [3.6]; P=1.000) and life-threatening arrhythmias (3 [6.4%) versus 7 [12.7]; P=0.335). No non-STEMI patients receiving IV r-tPA had cardiac complications. Conclusions- In patients with AIS and recent or concurrent MI, MI type and the time elapsed between the 2 events should be taken into consideration when deciding to deliver IV r-tPA. Although recent non-STEMI or concurrent events seem safe, STEMI in the week preceding stroke should prompt caution. The low number of events and publication bias may have influenced our conclusions.
Related Concept Videos
 01:10
Review and Preview
Percentiles are a type of fractile that partition data into...
 01:13
Review and Preview
 01:10
Resistors In Series
In a series circuit, the...
 01:20
Random and Systematic Errors
 01:17
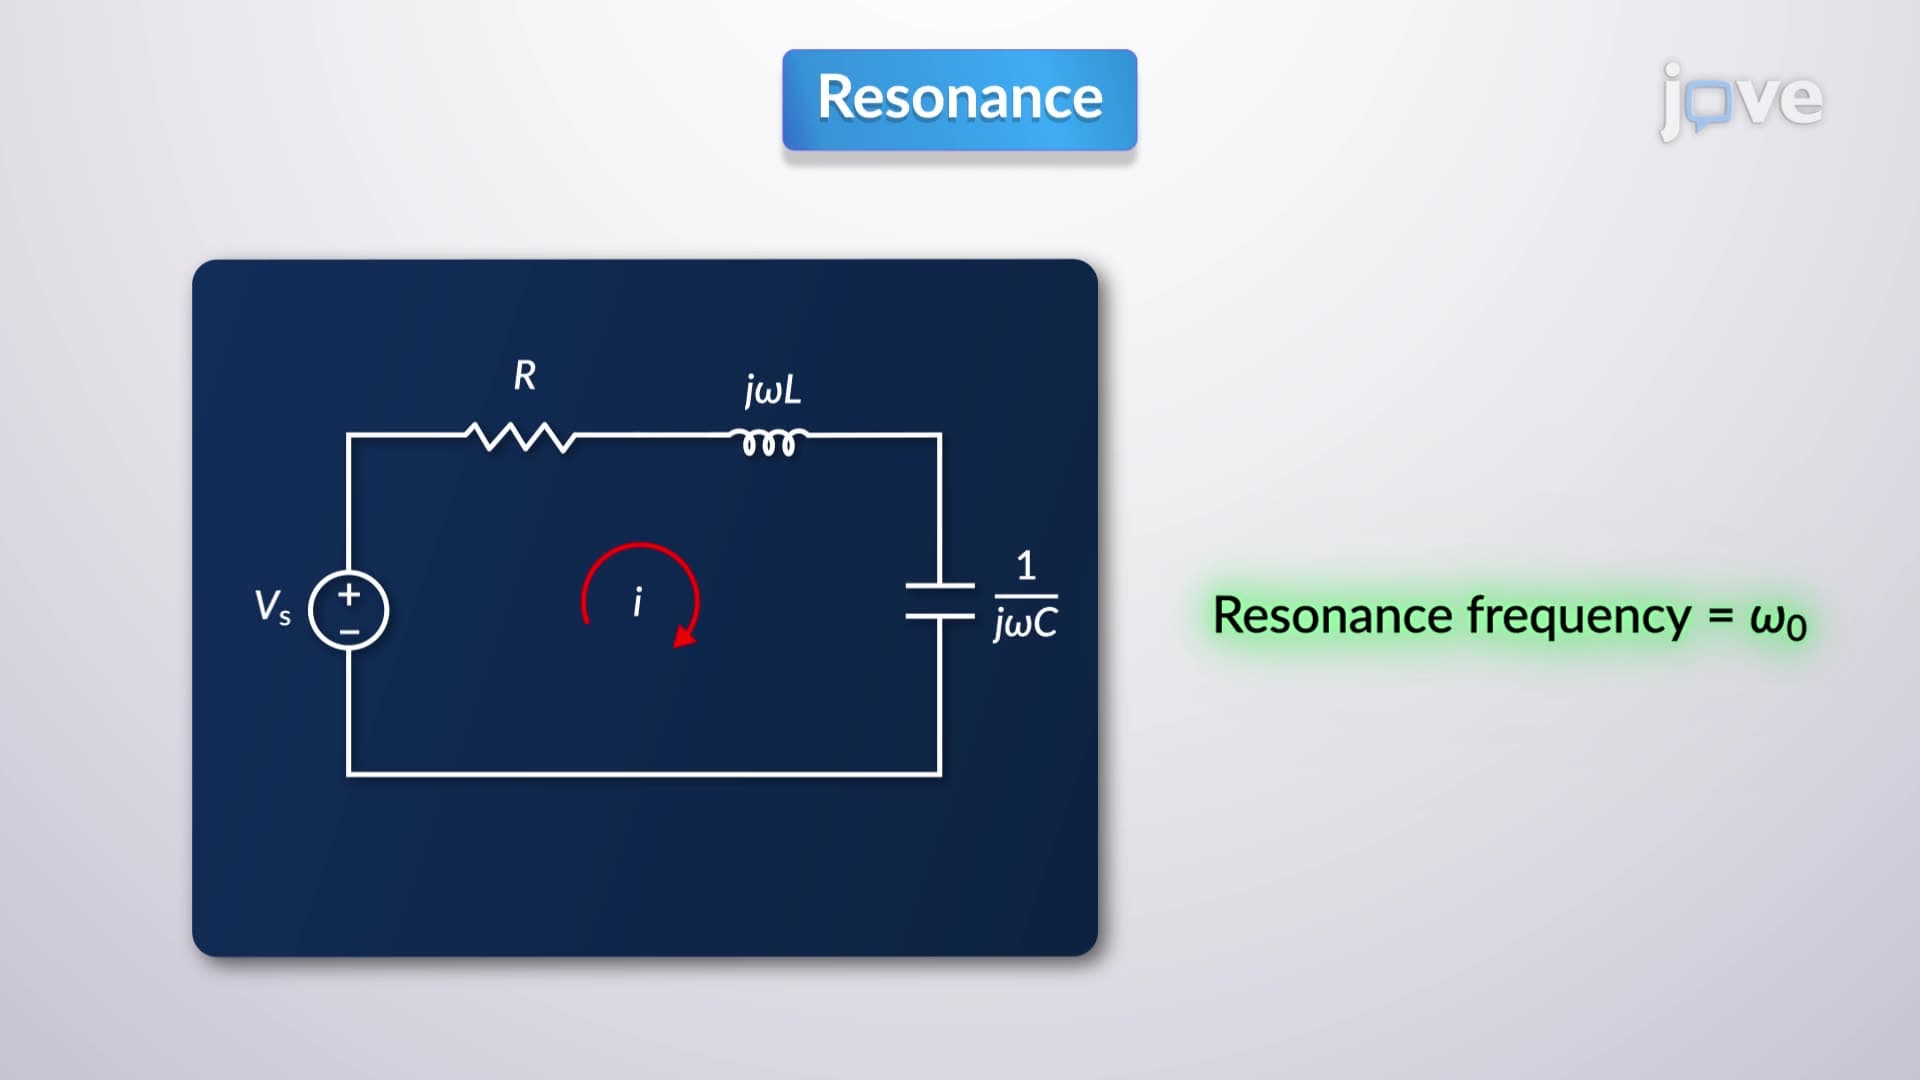
Series Resonance
 01:17
Systematic Sampling Method
Systematic sampling is one of the simplest methods...