Related Experiment Video
Updated: Jan 20, 2026


Sentinel Lymph Node Mapping and Biopsy for Endometrial Cancer at Early Stage with Laparoscopy
Published on: August 19, 2021
Cranial nerve outcomes in regionally recurrent head & neck melanoma after sentinel lymph node biopsy
John E Hanks1, Pratyusha Yalamanchi2, Kevin J Kovatch2
1Department of Otolaryngology-Head & Neck Surgery, University of California-Davis Medical center, Ann Arbor, Michigan, U.S.A.

Objective:
Characterize long-term cranial nerve (CN) outcomes following sentinel lymph node biopsy (SLNB) based management for head and neck cutaneous melanoma (HNCM).
Methods:
Longitudinal review of HNCM patients undergoing SLNB from 1997-2007.
Results:
Three hundred fifty-six patients were identified, with mean age 53.5 ± 19.0 years, mean Breslow depth 2.52 ± 1.87 mm, and 4.9 years median follow-up. One hundred five (29.4%) patients had SLNB mapping to the parotid basin. Eighteen patients had positive parotid SLNs and underwent immediate parotidectomy / immediate completion lymph node dissection (iCLND), with six possessing positive parotid non-sentinel lymph nodes (NSLNs). Fifty-two of 356 (14.6%) patients developed delayed regional recurrences, including 20 total intraparotid recurrences: five following false negative (FN) parotid SLNB, three following prior immediate superficial parotidectomy, two following iCLND without parotidectomy, and the remaining 12 parotid recurrences had negative extraparotid SLNBs. Parotid recurrences were multiple (4.9 mean recurrent nodes) and advanced (n = 4 extracapsular extension), and all required salvage dissection including parotidectomy. Immediate parotidectomy/iCLND led to no permanent CN injuries. Delayed regional HNCM macrometastasis precipitated 16 total permanent CN injuries in 13 patients: 10 CN VII, five CN XI, and one CN XII deficits. Fifty percent (n = 10) of parotid recurrences caused ≥1 permanent CN deficits.
Conclusions:
Regional HNCM macrometastases and salvage dissection confer marked CN injury risk, whereas early surgical intervention via SLNB ± iCLND ± immediate parotidectomy yielded no CN injuries. Further, superficial parotidectomy performed in parotid-mapping HNCM does not obviate delayed intraparotid recurrences, which increase risk of CN VII injury. Despite lack of a published disease-specific survival advantage in melanoma, early disease control in cervical and parotid basins is paramount to minimize CN complications.
Level Of Evidence:
4 (retrospective case series) Laryngoscope, 130:1707-1714, 2020.
More Related Videos
 06:37
Multispectral Real-time Fluorescence Imaging for Intraoperative Detection of the Sentinel Lymph Node in Gynecologic Oncology
Published on: October 20, 2010
 07:51
The Application of 1% Methylene Blue Dye As a Single Technique in Breast Cancer Sentinel Node Biopsy
Published on: June 1, 2019
Related Concept Videos
 01:26
Arteries of the Head and Neck
The internal carotid arteries supply blood to the anterior portion of the cerebrum. They enter the...
 01:19
Veins of Head and Neck
On the other hand, the vertebral veins, unlike their arterial counterparts, are not primarily responsible for brain drainage. Instead, they drain the cervical vertebrae, spinal cord, and some small...
 01:14
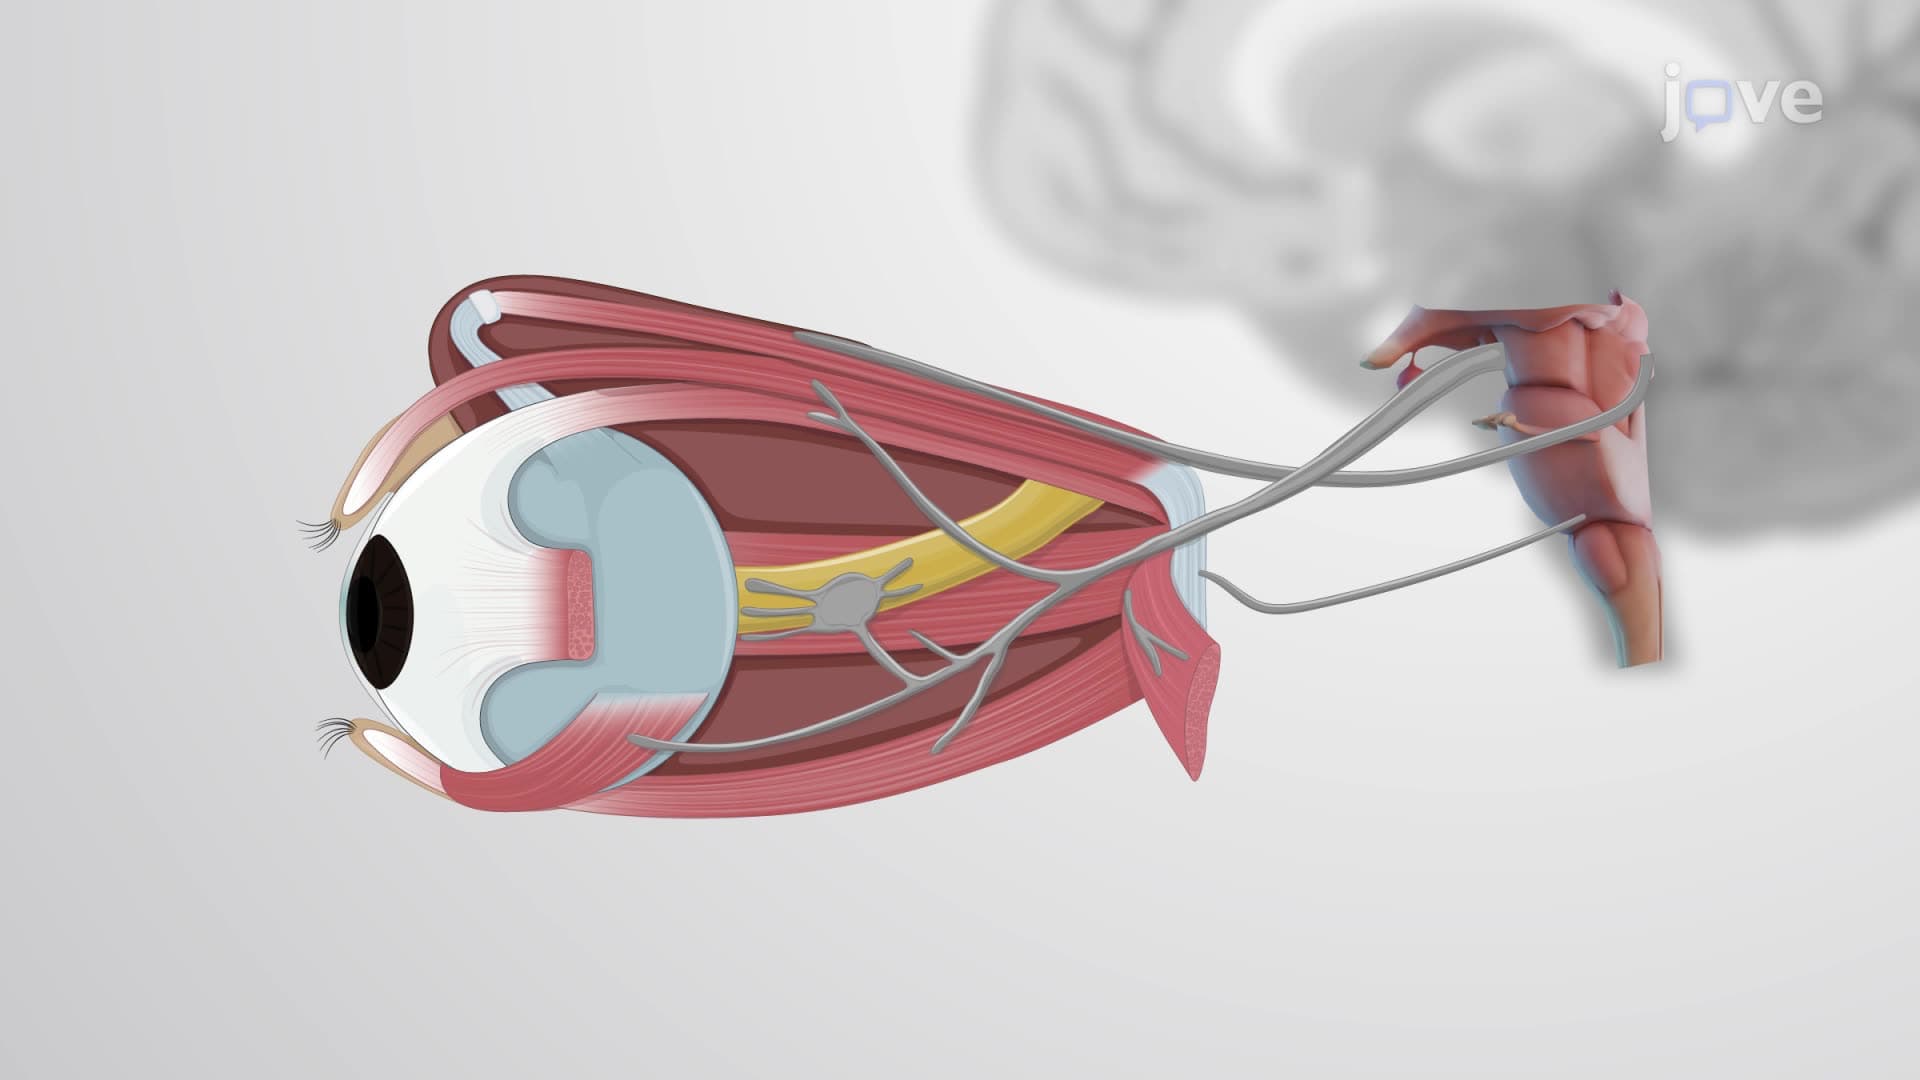
Cranial Nerves: Types Part I
Olfactory Nerve (Cranial Nerve I)
The olfactory nerve, or cranial nerve I, is unique as it is purely sensory and dedicated to the sense of smell. This nerve originates in the olfactory epithelium of the...
 01:22
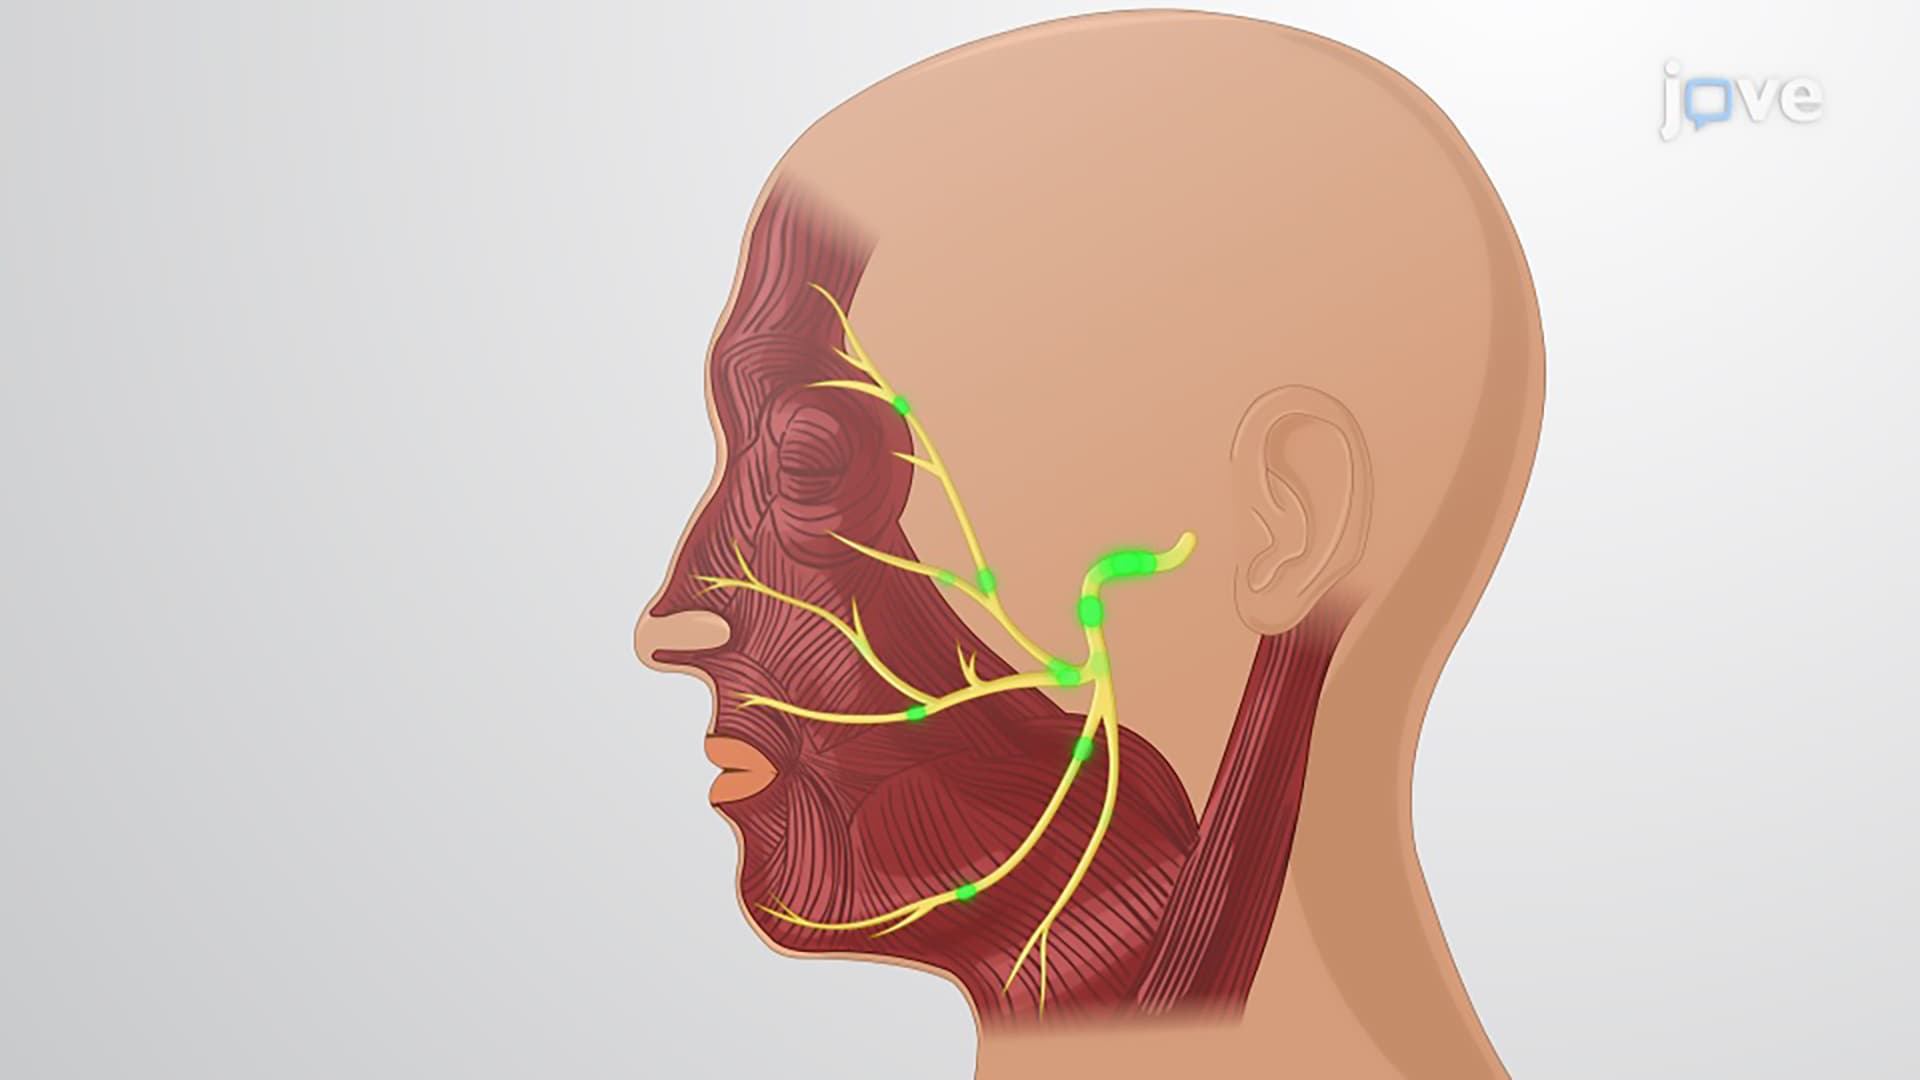
Cranial Nerves: Types Part II
Facial Nerve (Cranial Nerve VII)
Cranial nerve VII, or the facial nerve,...
 01:23
Detailed Structure and Function of Lymph Nodes
From a histological perspective, lymph nodes can be split into two main areas: the superficial cortex and the deep medulla. The outer cortex is populated by dendritic cells, macrophages, and B lymphocytes, which are densely packed into follicles. When these B-lymphocytes are presented...
 01:19
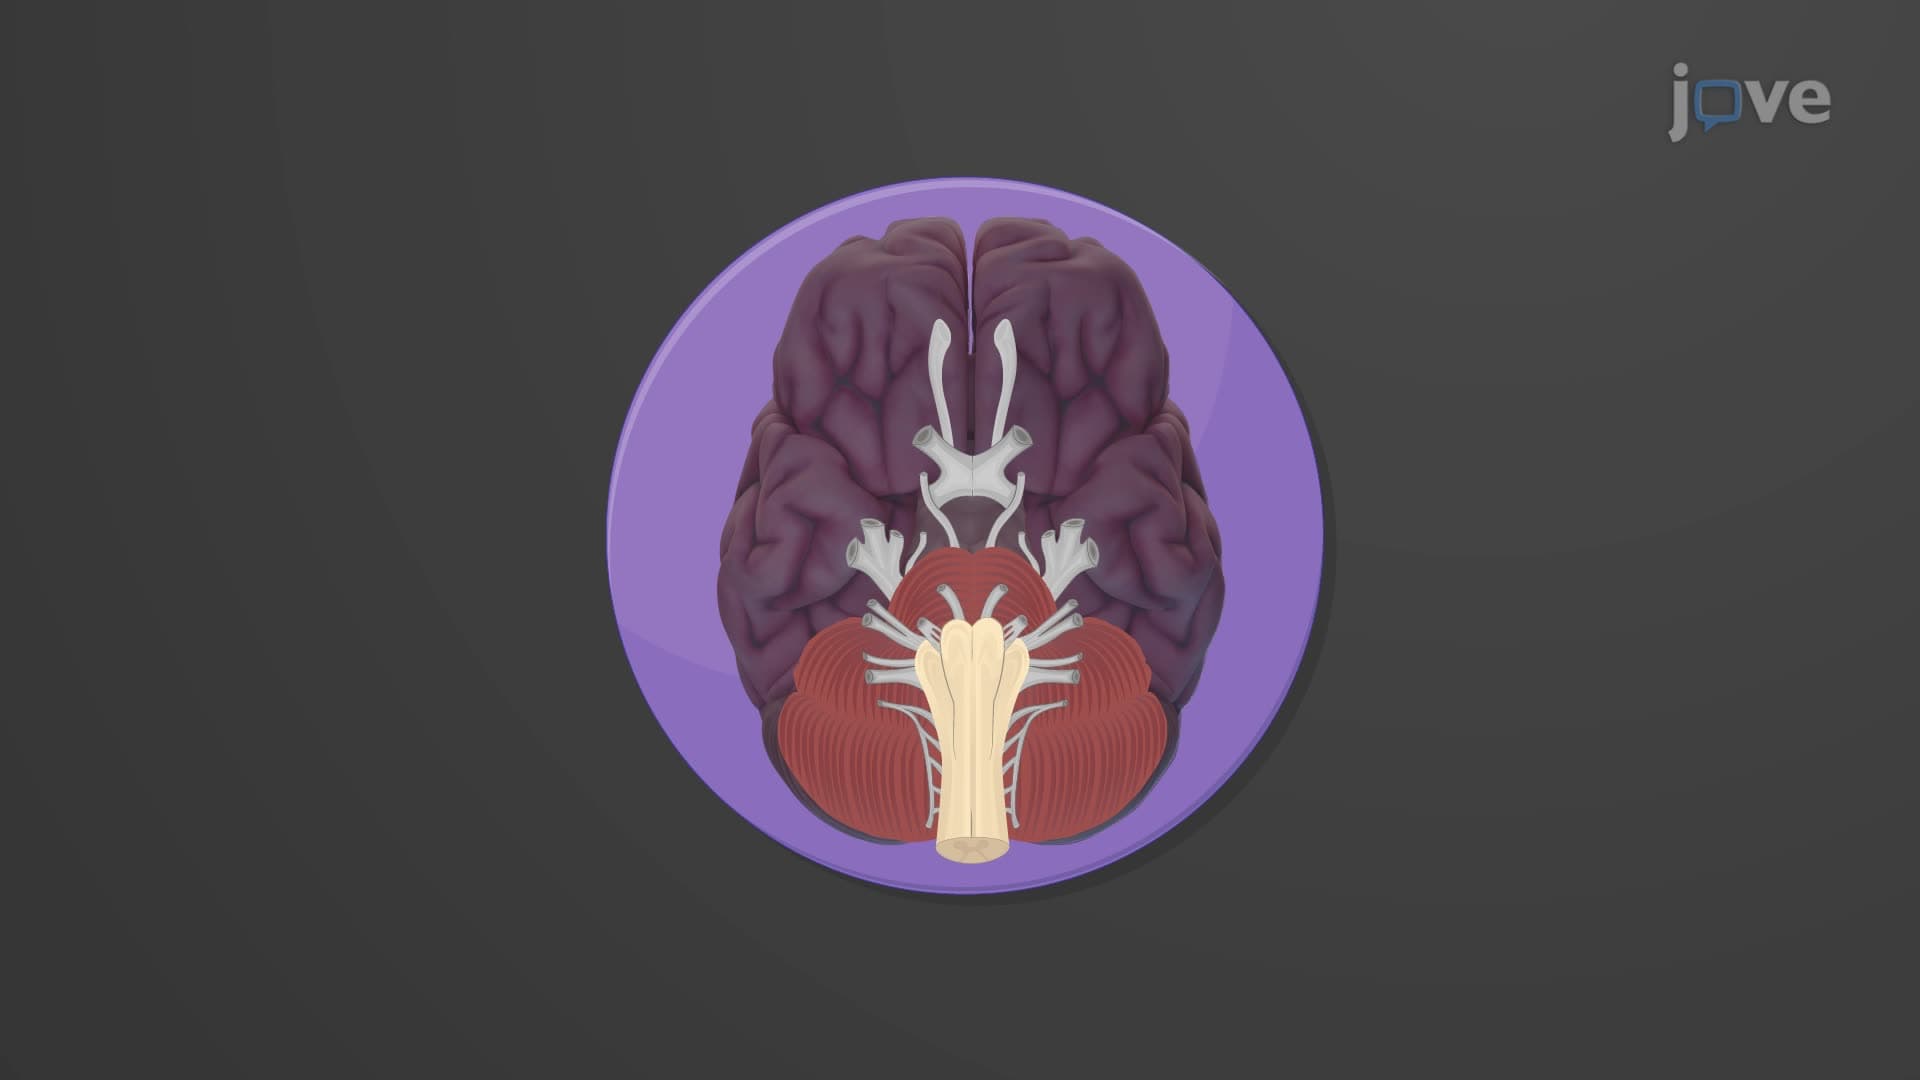
Cranial Nerves: Overview and Anatomy