Related Experiment Video
Updated: Jan 20, 2026


Home-Based Prescribed Pulmonary Exercise in Patients with Stable Chronic Obstructive Pulmonary Disease
Published on: August 24, 2019
Effects of Pharmacist-Conducted Medication Reconciliation at Discharge on 30-Day Readmission Rates of Patients With
Divita Singh1, Germin Fahim2,3, Hoytin Lee Ghin3
1University of Florida, Gainesville, FL, USA.

Purpose:
To analyze effect of pharmacist-conducted medication reconciliation on 30-day readmission rates in chronic obstructive pulmonary disease (COPD) and identify common medication errors among patient with readmissions.
Methods:
Pharmacists were educated on discharge medication reconciliation for patients with COPD. A retrospective chart review was conducted on patients who underwent pharmacist-conducted discharge medication reconciliation to determine 30-day readmissions. Medication errors analyzed included medication omissions and dose or frequency errors. Previously collected internal research without pharmacist-conducted medication reconciliation served as the control.
Results:
There were 65 patients in the control group and 50 in the intervention group. About 25% of patients in the control group and 26% of patients in the intervention group had any cause readmissions within 30 days of discharge (P = .87). Both the control and the intervention group had similar COPD-related readmissions of 12.3% and 12.6%, respectively. Medication dose or frequency errors consisted of 68.9% and 46.7% of total errors in the control and the intervention groups, respectively. Long-acting muscarinic antagonist (LAMA) or long-acting beta 2-agonist (LABA) were the most common drug classes to be incorrectly dosed or omitted at discharge. In the intervention group, 30 errors were identified. Due to inability to coordinate discharges, pharmacists intervened on 13 errors, 7 of which were accepted by the prescriber.
Conclusion:
Pharmacist-conducted medication reconciliation at discharge did not affect 30-day readmission rates of patients with COPD. Confounding factors included a small sample size, passive pharmacist education, and discharge issues. The most common medication errors at discharge were dosing or frequency errors of LABAs or LAMAs.
More Related Videos
 02:34
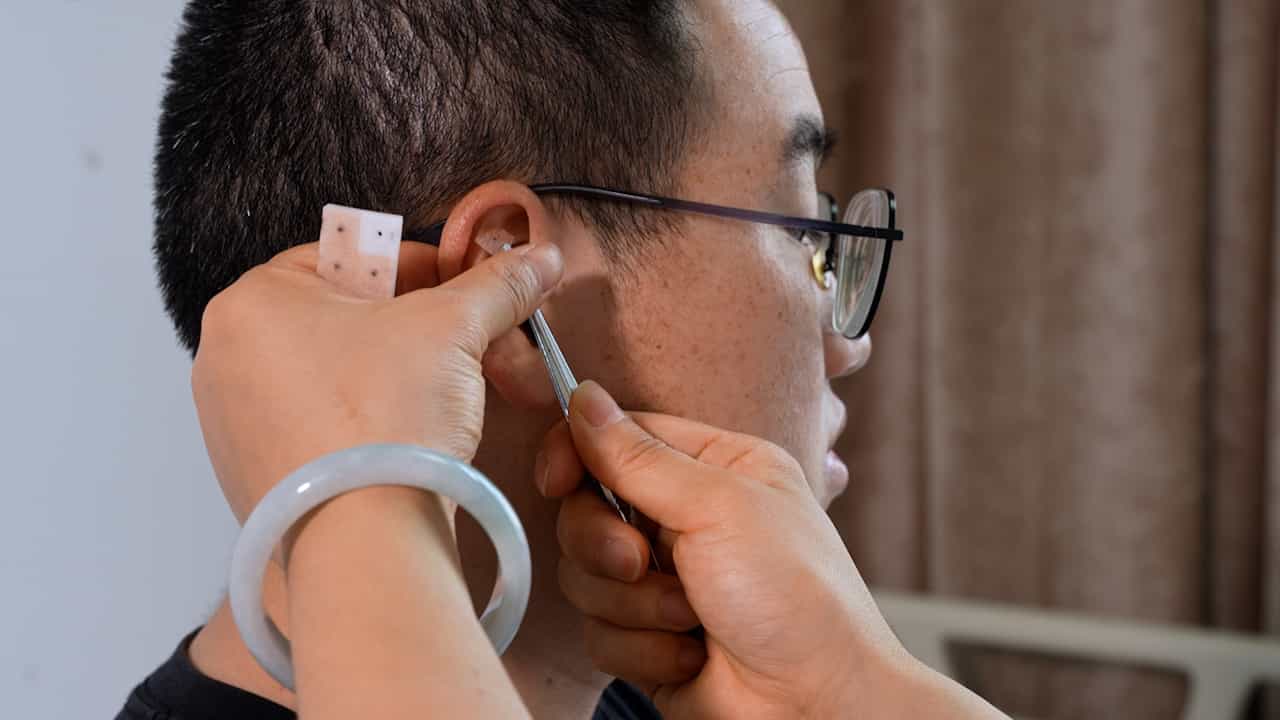
Author Spotlight: Efficacy of Auricular Pressure Bean Therapy in Reducing Wheezing Symptoms
Published on: May 10, 2024
 03:25
Author Spotlight: Exploring Non-Pharmacological Therapies for Chronic Respiratory Diseases — Linking Intestinal Microbiome Insights to COPD Treatment
Published on: December 27, 2024
Related Concept Videos
 01:22
Chronic Obstructive Pulmonary Disease
Smoking is a primary risk factor for COPD, with over 80% of patients having a history of it. Patients typically experience progressive dyspnea or labored breathing, frequent coughing, and recurrent pulmonary infections. Many eventually succumb to respiratory failure, characterized by...
 01:20
Chronic Obstructive Pulmonary Disease-I: Introduction
 01:29
Chronic Obstructive Pulmonary Disease-V: Management
Smoking Cessation
 01:20
Chronic Obstructive Pulmonary Disease-II: Pathophysiology
Chronic Inflammation
 01:30
Chronic Obstructive Pulmonary Disease-V: Nursing Management
Assessment
 01:25
Chronic Obstructive Pulmonary Disease-III: Symptoms and Complications.
Symptoms of COPD can be classified as primary or systemic. Primary symptoms relate to reduced airflow, while systemic or extrapulmonary symptoms relate to COPD's broader impact on the body.
Primary Symptoms of COPD: