Final height in growth hormone-deficient childhood cancer survivors after growth hormone therapy
G Rodari1,2, A Cattoni3,4, A Albanese3
1Paediatric Unit, Royal Marsden NHS Foundation Trust, Sutton, UK. rodarigiulia@gmail.com.

Insights
Recombinant human growth hormone (rhGH) therapy in childhood cancer survivors with growth hormone deficiency (GHD) did not achieve predicted final height but prevented further height loss. Outcomes were significantly poorer in those receiving craniospinal or total body irradiation.
Area of Science:
- Pediatric Endocrinology
- Oncology
- Growth Hormone Therapy
Background:
- Growth hormone deficiency (GHD) is a common hypothalamic-pituitary disorder in childhood cancer survivors (CCS).
- Previous studies suggest recombinant human growth hormone (rhGH) does not fully restore final height (FH) to the predicted mid-parental height (MPH) in CCS.
- Further analysis of FH outcomes in CCS treated with rhGH is warranted.
Purpose of the Study:
- To evaluate final height (FH) outcomes in childhood cancer survivors (CCS) treated with recombinant human growth hormone (rhGH).
- To compare FH in CCS who received different types of radiotherapy (cranial vs. craniospinal/TBI).
- To identify factors influencing final height in this population.
Main Methods:
- Retrospective analysis of 87 childhood cancer survivors (CCS) treated with rhGH for growth hormone deficiency (GHD).
- Patients were stratified into two groups based on radiotherapy: cranial irradiation or non-irradiated tumors (Group A) vs. craniospinal or total body irradiation (TBI) (Group B).
- Some patients received gonadotropin-releasing hormone analogues (GnRHa) in addition to rhGH.
Main Results:
- rhGH treatment resulted in height gain but mean final height (FH) was not significantly different from baseline height SDS and remained below mid-parental height (MPH).
- 67% of patients did not reach their MPH, with significantly poorer outcomes in Group B (craniospinal/TBI).
- Baseline height and delay in starting rhGH were significant predictors of FH; GnRHa addition did not significantly alter FH.
Conclusions:
- rhGH and GnRH analogues therapy, while not achieving catch-up growth to MPH, effectively prevented further height loss in CCS with GHD.
- Final height was within the normal range but statistically significantly below MPH, particularly in patients who underwent craniospinal or total body irradiation (TBI).
- This highlights the need for careful management and realistic expectations for growth outcomes in irradiated CCS.
Purpose:
Growth hormone deficiency (GHD) is the most prevalent hypothalamic-pituitary (HP) disorder found in childhood cancer survivors (CCS). The published studies assessing GHD in CCS concluded that recombinant human GH (rhGH) does not restore final height (FH) to that predicted from mid-parental height (MPH). Thus, wider analyses on final height outcomes after rhGH in CCS are needed.
Methods:
Retrospective study on final height (FH) in 87 CCS treated with rhGH. Patients were divided into: Group A (n =48) who underwent cranial radiotherapy or had non-irradiated tumours of HP area, and B (n =39) who were treated with craniospinal or total body irradiation (TBI). 19/87 patients with central precocious/early puberty also received GnRH analogues.
Results:
Height (HT) gain after 1 and 2 years of rhGH was 0.38 ± 0.35 SDS and 0.18 ± 0.30 SDS, respectively (P < 0.0001); mean FH was in the normal range (- 0.85 ± 1.34 SDS), though not significantly different from HT SDS at baseline. 67% overall failed to reach MPH especially in Group B (P < 0.0001). However, height loss (HT SDS-MPH SDS) at FH improved or remained stable compared to baseline in 26/45 patients (58%). On stepwise regression analysis, major determinants of FH were HT at baseline (P < 0.0001) and delay before start of rhGH (P = 0.012). There was no significant difference in FH when GnRHa was added to rhGH.
Conclusion:
rhGH and GnRH analogues therapy, when indicated, though failing to induce catch-up growth, prevented further height loss leading to a FH within the normal range but still below MPH, this latter being statistically significant in children who received craniospinal and TBI.


Related Concept Videos
 01:56
Plant Hormones
 02:13
Types of Hormones
 01:21
Types of Hormones
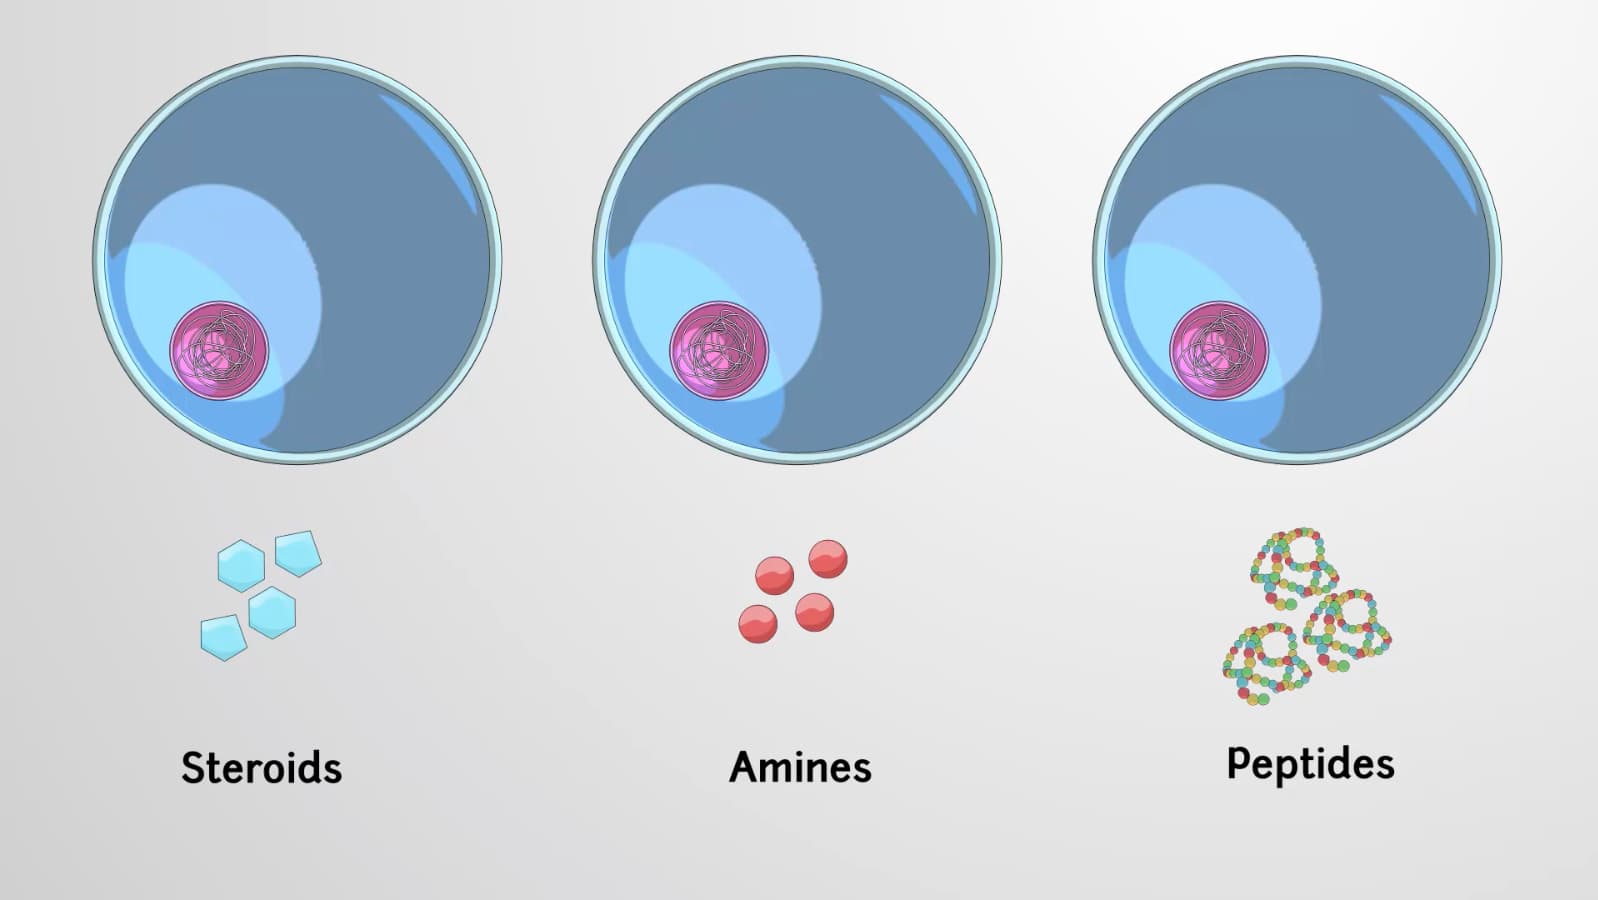
Steroids and eicosanoids fall under the category of lipid-soluble hormones. Steroids are derived from cholesterol and feature four interconnected carbon rings with variable side chains. Notable examples include estradiol from ovaries and testosterone from testes, exemplifying the critical roles of these lipid-soluble hormones in reproductive physiology. Eicosanoids, derived...
 01:33
Hormonal Regulation
 01:40
Hormonal Regulation
 03:02
Primary and Secondary Growth in Roots and Shoots