Related Experiment Video
Updated: Jan 20, 2026
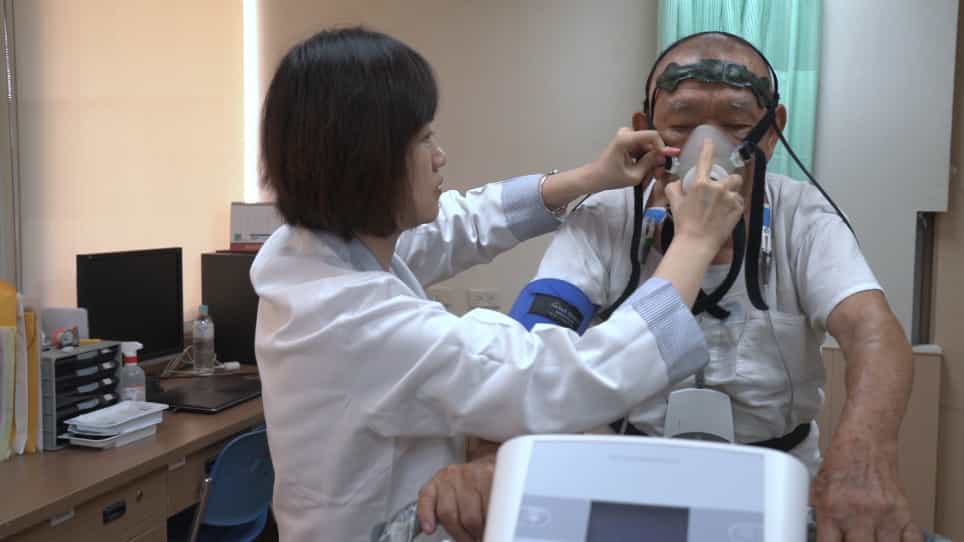
Integration of Brain Tissue Saturation Monitoring in Cardiopulmonary Exercise Testing in Patients with Heart Failure
Published on: October 1, 2019
Cardiopulmonary Exercise Testing, Impedance Cardiography, and Reclassification of Risk in Patients Referred for Heart
Jonathan Myers1, Jeffrey W Christle2, Amanda Tun1
1VA Palo Alto Health Care System, Division of Cardiovascular Medicine, Palo Alto, California; Stanford University, Stanford California.

Insights
Impedance cardiography (ICG) combined with cardiopulmonary exercise testing (CPX) significantly improves risk assessment for adverse events in heart failure (HF) patients. This approach enhances prediction beyond traditional CPX measures alone.
Area of Science:
- Cardiology
- Exercise Physiology
- Medical Technology
Background:
- Impaired cardiac output response to exercise is a key indicator of chronic heart failure (HF).
- Accurate risk stratification is crucial for managing HF patients and predicting adverse outcomes.
Purpose of the Study:
- To evaluate if impedance cardiography (ICG) during exercise, combined with cardiopulmonary exercise test (CPX) responses, can reclassify risk for adverse events in HF patients.
- To determine the added value of noninvasive hemodynamic data from ICG to established CPX risk markers.
Main Methods:
- 1236 patients evaluated for HF underwent CPX and ICG during exercise.
- Clinical, ICG, and CPX variables were analyzed for association with a composite outcome (cardiac death, HF hospitalization, transplant, LVAD).
- Cox proportional hazards analyses and Net Reclassification Improvement (NRI) were used to assess risk prediction and reclassification.
Main Results:
- Peak VO2, VE/VCO2 slope, and oxygen uptake efficiency slope from CPX were significant risk predictors.
- Changes in cardiac index, cardiac time interval, and left cardiac work index from ICG were also strong predictors.
- Combining impaired CPX and ICG responses indicated a sevenfold higher risk of adverse events.
- Adding ICG responses to CPX models resulted in significant NRIs (0.34-0.89), demonstrating improved risk reclassification.
Conclusions:
- Cardiac hemodynamics assessed by ICG provide valuable information that complements CPX measures.
- ICG enhances the reclassification of risk for adverse events in patients with heart failure.
- The combination of ICG and CPX offers a more comprehensive approach to risk stratification in HF.
Background:
An impaired cardiac output response to exercise is a hallmark of chronic heart failure (HF). We determined the extent to which impedance cardiography (ICG) during exercise in combination with cardiopulmonary exercise test (CPX) responses reclassified risk for adverse events in patients with HF.
Methods And Results:
CPX and ICG were performed in 1236 consecutive patients (48±15 years) evaluated for HF. Clinical, ICG and CPX variables were acquired at baseline and subjects were followed for the composite outcome of cardiac-related death, hospitalization for worsening HF, cardiac transplantation, and left ventricular assist device implantation. Cox proportional hazards analyses including clinical, noninvasive hemodynamic, and CPX variables were performed to determine their association with the composite endpoint. Net reclassification improvement (NRI) was calculated to quantify the impact of adding hemodynamic responses to a model including established CPX risk markers on reclassifying risk. There were 422 events. Among CPX variables, peak VO2 and indices of ventilatory inefficiency (VE/VCO2 slope, oxygen uptake efficiency slope) were significant predictors of risk for adverse events. Among hemodynamic variables, change in cardiac index, peak cardiac time interval, and peak left cardiac work index were the strongest predictors of risk. Having 5 impaired CPX and ICG responses to exercise yielded a sevenfold higher risk for adverse events compared with having no abnormal responses. Combining ICG responses to CPX resulted in NRIs ranging between 0.34 and 0.89, attributable to better reclassification of events.
Conclusion:
Cardiac hemodynamics determined by ICG complement established CPX measures in reclassifying risk among patients with HF.
More Related Videos
 10:21
Evaluation of Hydration Status by Bioelectrical Impedance Vector Analysis in Patients with Ischemic Heart Disease Undergoing Exercise Stress Test
Published on: September 22, 2023
 07:44
Author Spotlight: Implementation of BIVA for Analyzing Disease Risk Factors in Patients with Low Body Cell Mass
Published on: July 14, 2023
Related Concept Videos
 01:30
Heart Failure IV: Classification and Diagnostic Evaluation
 01:29
Heart Failure II: Pathophysiology
 01:17
Pathophysiology of Heart Failure
 01:27
Heart Failure I: Introduction
 01:22
Heart Failure VI: Adjunct Therapies
 01:22
Heart Failure Drugs: Diuretics