Related Experiment Video
Updated: Jan 20, 2026
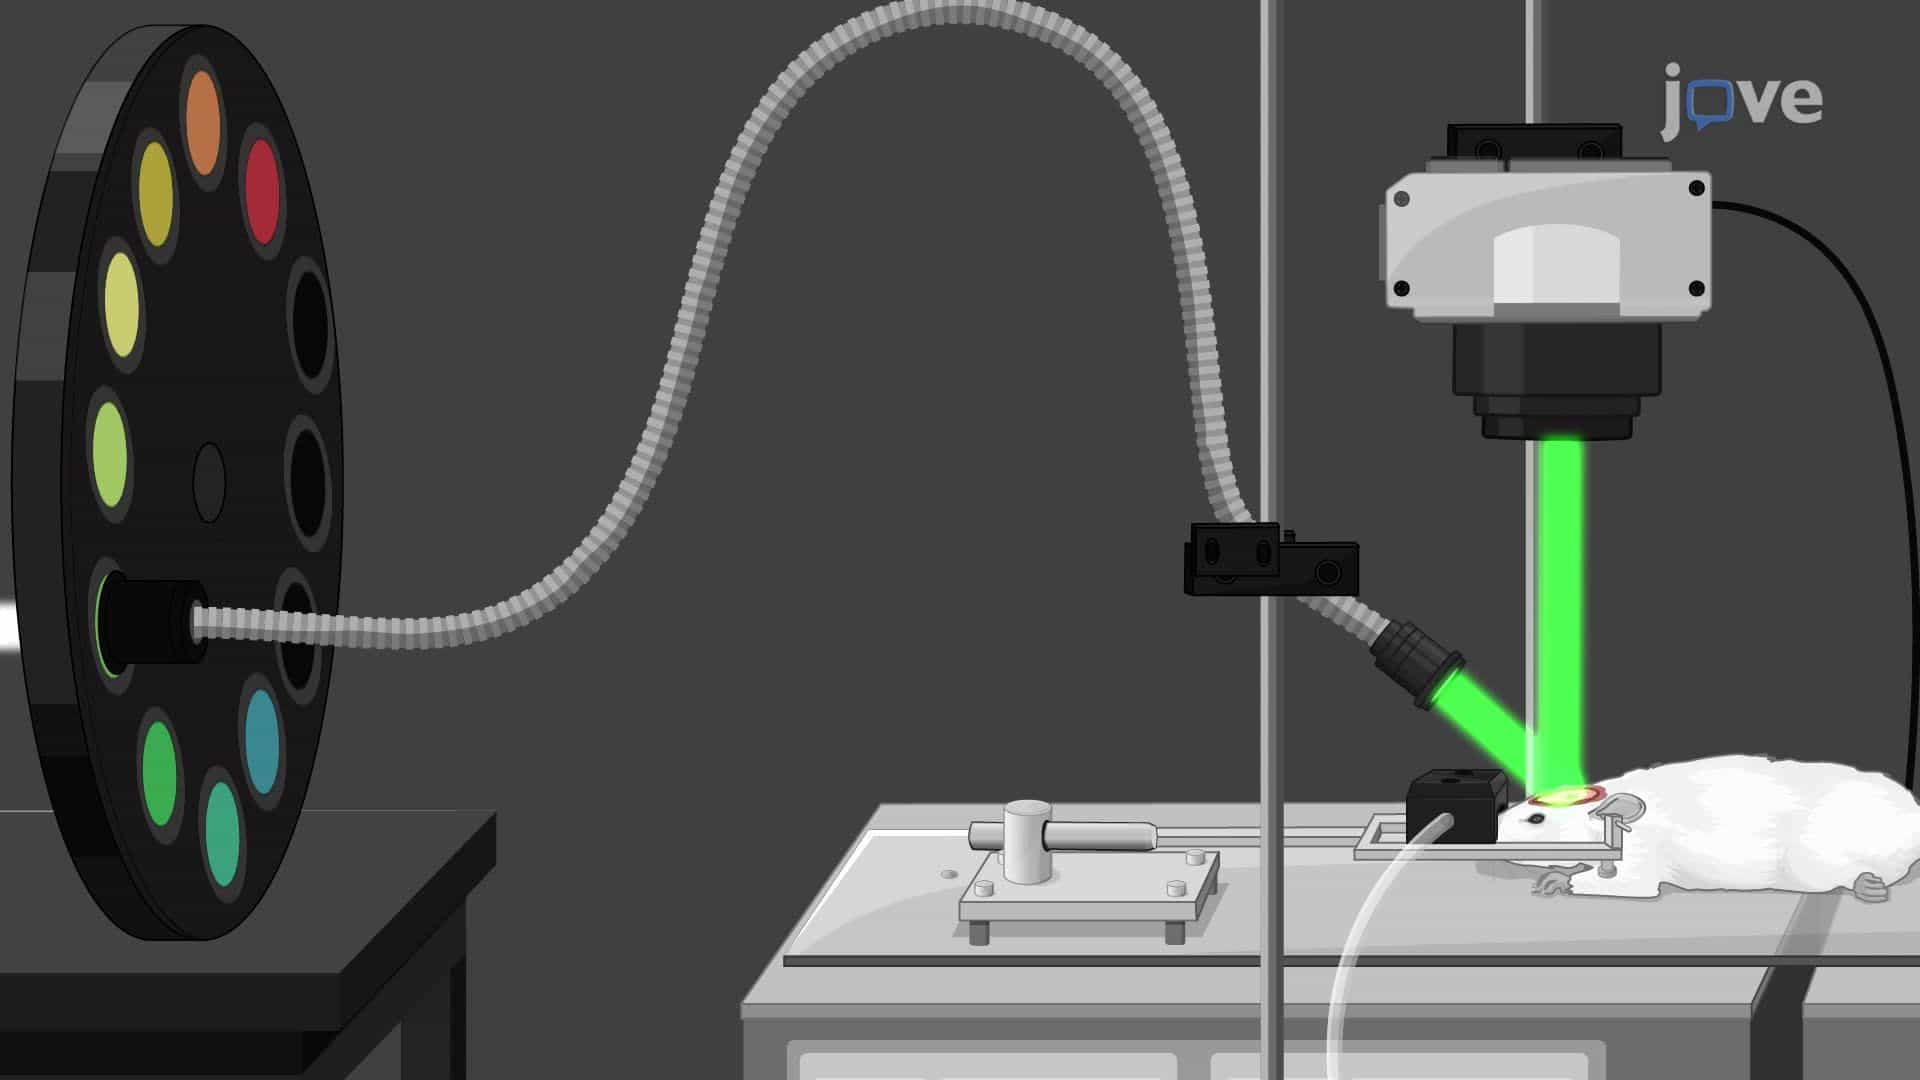

Multispectral Diffuse Reflectance Imaging of Rat Cerebral Blood Flow and Tissue Structure
Published on: June 17, 2025
Cerebral Blood Flow Predicts the Infarct Core: New Insights From Contemporaneous Diffusion and Perfusion Imaging
Shalini Amukotuwa1, Matus Straka2, Didem Aksoy2
1From the Department of Radiology (S.A.), University of Melbourne, Australia.

Abstract:
Background and Purpose- The aim of this study is to determine the spatial and volumetric accuracy of infarct core estimates from relative cerebral blood flow (rCBF) by comparison with near-contemporaneous diffusion-weighted imaging (DWI), and evaluate whether it is sufficient for patient triage to reperfusion therapies. Methods- One hundred ninety-three patients enrolled in the DEFUSE 2 (Diffusion and Perfusion Imaging Evaluation for Understanding Stroke Evolution) and SENSE 3 (Sensitivity Encoding) stroke studies were screened, and 119 who underwent acute magnetic resonance imaging with DWI and perfusion imaging within 24 hours of onset were included. Infarct core was estimated using reduced rCBF at 12 thresholds (<0.20-<0.44) and compared against DWI (apparent diffusion coefficient <620 10-6mm2/s). For each threshold, volumetric agreement between the rCBF and DWI core estimates was assessed using Bland-Altman, correlation, and linear regression analyses; spatial agreement was assessed using receiver operating characteristic analysis. Results- An rCBF threshold of 0.32 yielded the smallest mean absolute volume difference (14.7 mL), best linear regression fit (R2=0.84), and best spatial agreement (Youden index, 0.38; 95% CI, 0.34-0.41) between rCBF and DWI, with high correlation (r=0.91, P<0.05), a small mean volume difference (1.3 mL) and no fixed bias (P<0.05). At this threshold, 110 of 119 (92.4%) patients were correctly triaged when applying 70 mL as the volume limit for thrombectomy. Spatial agreement was better for prediction of large infarcts (>70 mL) than small infarcts (≤70 mL), with Youden indices of 0.53 (95% CI, 0.49-0.56) and 0.34 (95% CI, 0.30-0.37), respectively. Conclusions- Strong correlation and agreement with near-contemporaneous DWI indicate that infarct core estimates obtained using rCBF are sufficiently accurate for patient triage to reperfusion therapies. The identified optimal rCBF threshold of 0.32 closely approximates the threshold currently used in clinical practice.

Related Concept Videos
 02:16
Multispectral Diffuse Reflectance Imaging of Rat Cerebral Blood Flow and Tissue Structure
 02:31
Diffuse Correlation Spectroscopy to Assess Cerebral Blood Flow in a Mouse Model
 05:09
Diffuse Correlation Spectroscopy to Measure Cerebral Blood Flow in a Human Subject
 03:38
Developing a Cerebral Blood Flow Atlas for Blood Flow Mapping
 03:47
Functional Imaging of Cerebral Blood Flow Using Transcranial Doppler Ultrasound
 13:16
Intravascular Perfusion of Carbon Black Ink Allows Reliable Visualization of Cerebral Vessels