Related Experiment Video
Updated: Jan 20, 2026

The Role of Indocyanine Green Fluorescence in Complex Laparoscopic Cholecystectomy Navigation
Published on: January 31, 2025
Comparison of laparoscopic cholecystectomy and delayed laparoscopic cholecystectomy in aged acute calculous
Dengtian Lin1, Shuodong Wu2, Ying Fan1
1Division of Hepatobiliary Surgery, Department of Surgery, Shengjing Hospital Affiliated With China Medical University, Liaoning, China.

Background:
In elderly patients with calculous acute cholecystitis, the risk of emergency surgery is high, and percutaneous cholecystostomy tube drainage (PC) combined with delayed laparoscopic cholecystectomy (DLC) may be a good choice. We retrospectively compared laparoscopic cholecystectomy (LC) to DLC after PC to determine which is the better treatment strategy.
Method:
We performed a retrospective cohort analysis of 752 patients with acute calculous cholecystitis. Patients with the following conditions were included: (1) age > 65 years old; (2) patients with a grade 2 or 3 severity of cholecystitis according to the 2013 Tokyo Guidelines (TG13); (3) the surgeons who performed the LC were professors or associate professors and (4) the DLC was performed in our hospital after PC. Patients who missed their 30-day follow-up; were diagnosed with bile duct stones, cholangitis or gallstone pancreatitis or were pregnant were excluded from the study. A total of 51 of 314 patients who underwent LC and 73 of 438 patients who underwent PC + DLC were assessed. PC + DLC and LC patients were matched by cholecystitis severity grade according to the TG13, and the National Surgical Quality Improvement Program (NSQIP) calculator was used to predict mortality (n = 21/group). Preoperative characteristics and postoperative outcomes were analysed.
Results:
Compared to the matched LC group, the DLC group had less intraoperative bleeding (42.2 vs 75.3 mL, p = 0.014), shorter hospital stays (4.9 vs 7.4 days, p = 0.010) and lower rates of type A bile duct injury (4.8% vs 14.3%, p = 0.035) and type D (0 vs 9.5%, p = 0.002) according to Strasberg classification, residual stones (4.8 vs 14.3%, p = 0.035) and gastrointestinal organ injury (0 vs 3.6%, p < 0.001). Patients in the DLC group had lower incidences of ICU admission and death and a significantly lower incidence of repeat surgery.
Conclusion:
In elderly patients treated for acute calculous cholecystitis, the 30-day mortality and complication rates were lower for PC + DLC than for LC. However, the total hospitalisation time was significantly prolonged and the costs were significantly higher for PC + DLC.
Related Concept Videos
 03:27
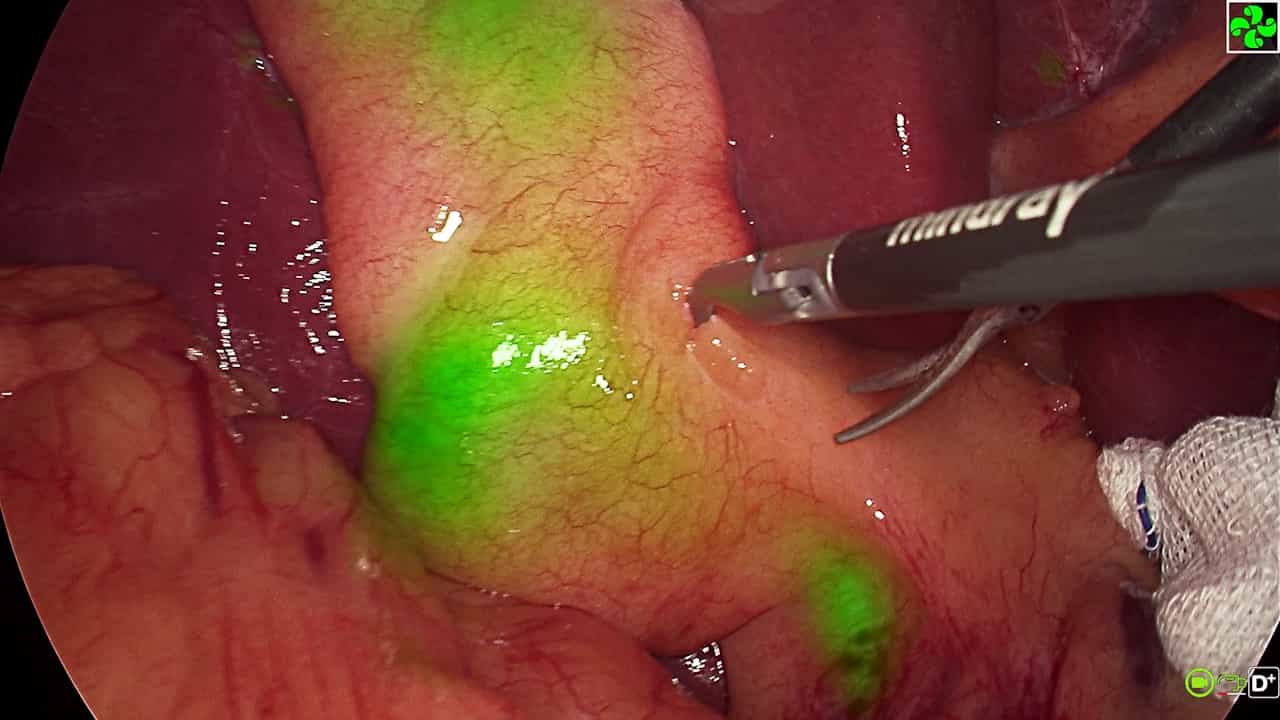
The Role of Indocyanine Green Fluorescence in Complex Laparoscopic Cholecystectomy Navigation
 04:02
Laparoscopic Cholecystectomy with Indocyanine Green Fluorescence: Choledochoscopic Stone Extraction and Primary Duct Suture
 08:57
Laparoscopic Pancreatoduodenectomy With Modified Blumgart Pancreaticojejunostomy
 04:23
Application of Hemostatic Devices in Laparoscopic Hepatectomy
 03:49
Application of Microwave Ablation in Laparoscopic Partial Splenectomy
 03:43
Laparoscopic Non-Mesh Cerclage Pectopexy for Pelvic Organ Prolapse